CBT isn't magic and it won't fix everything
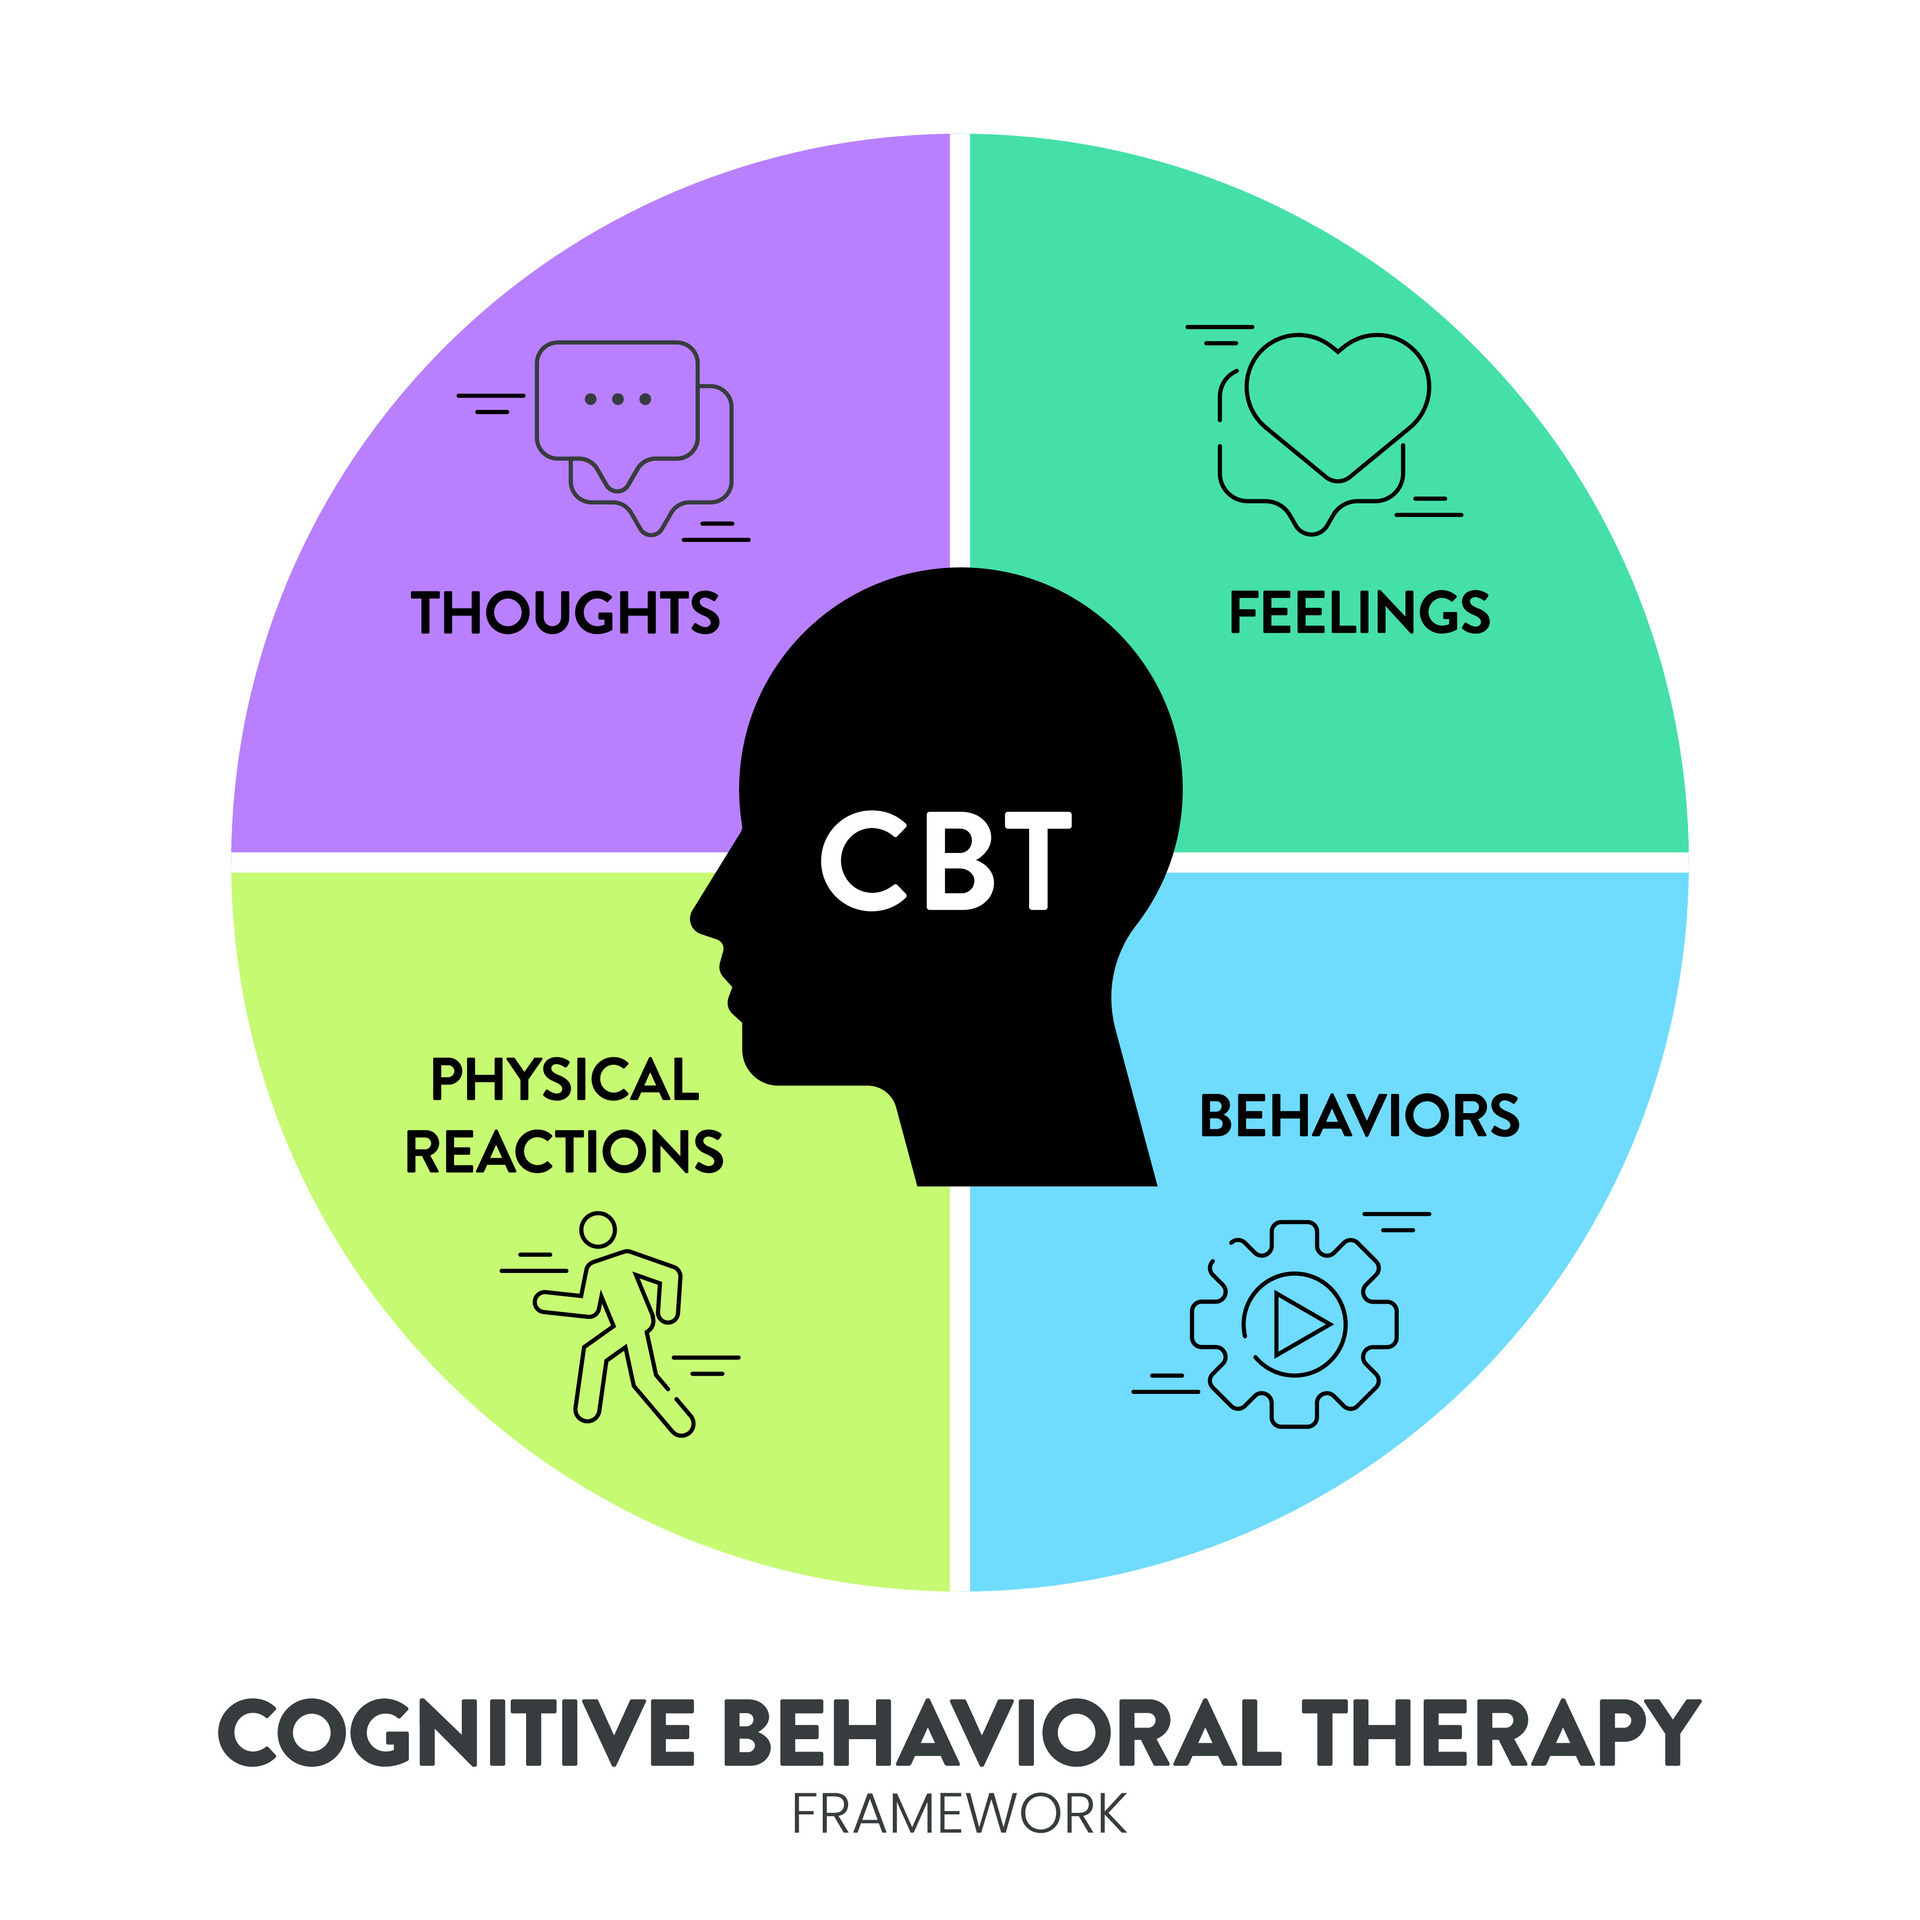
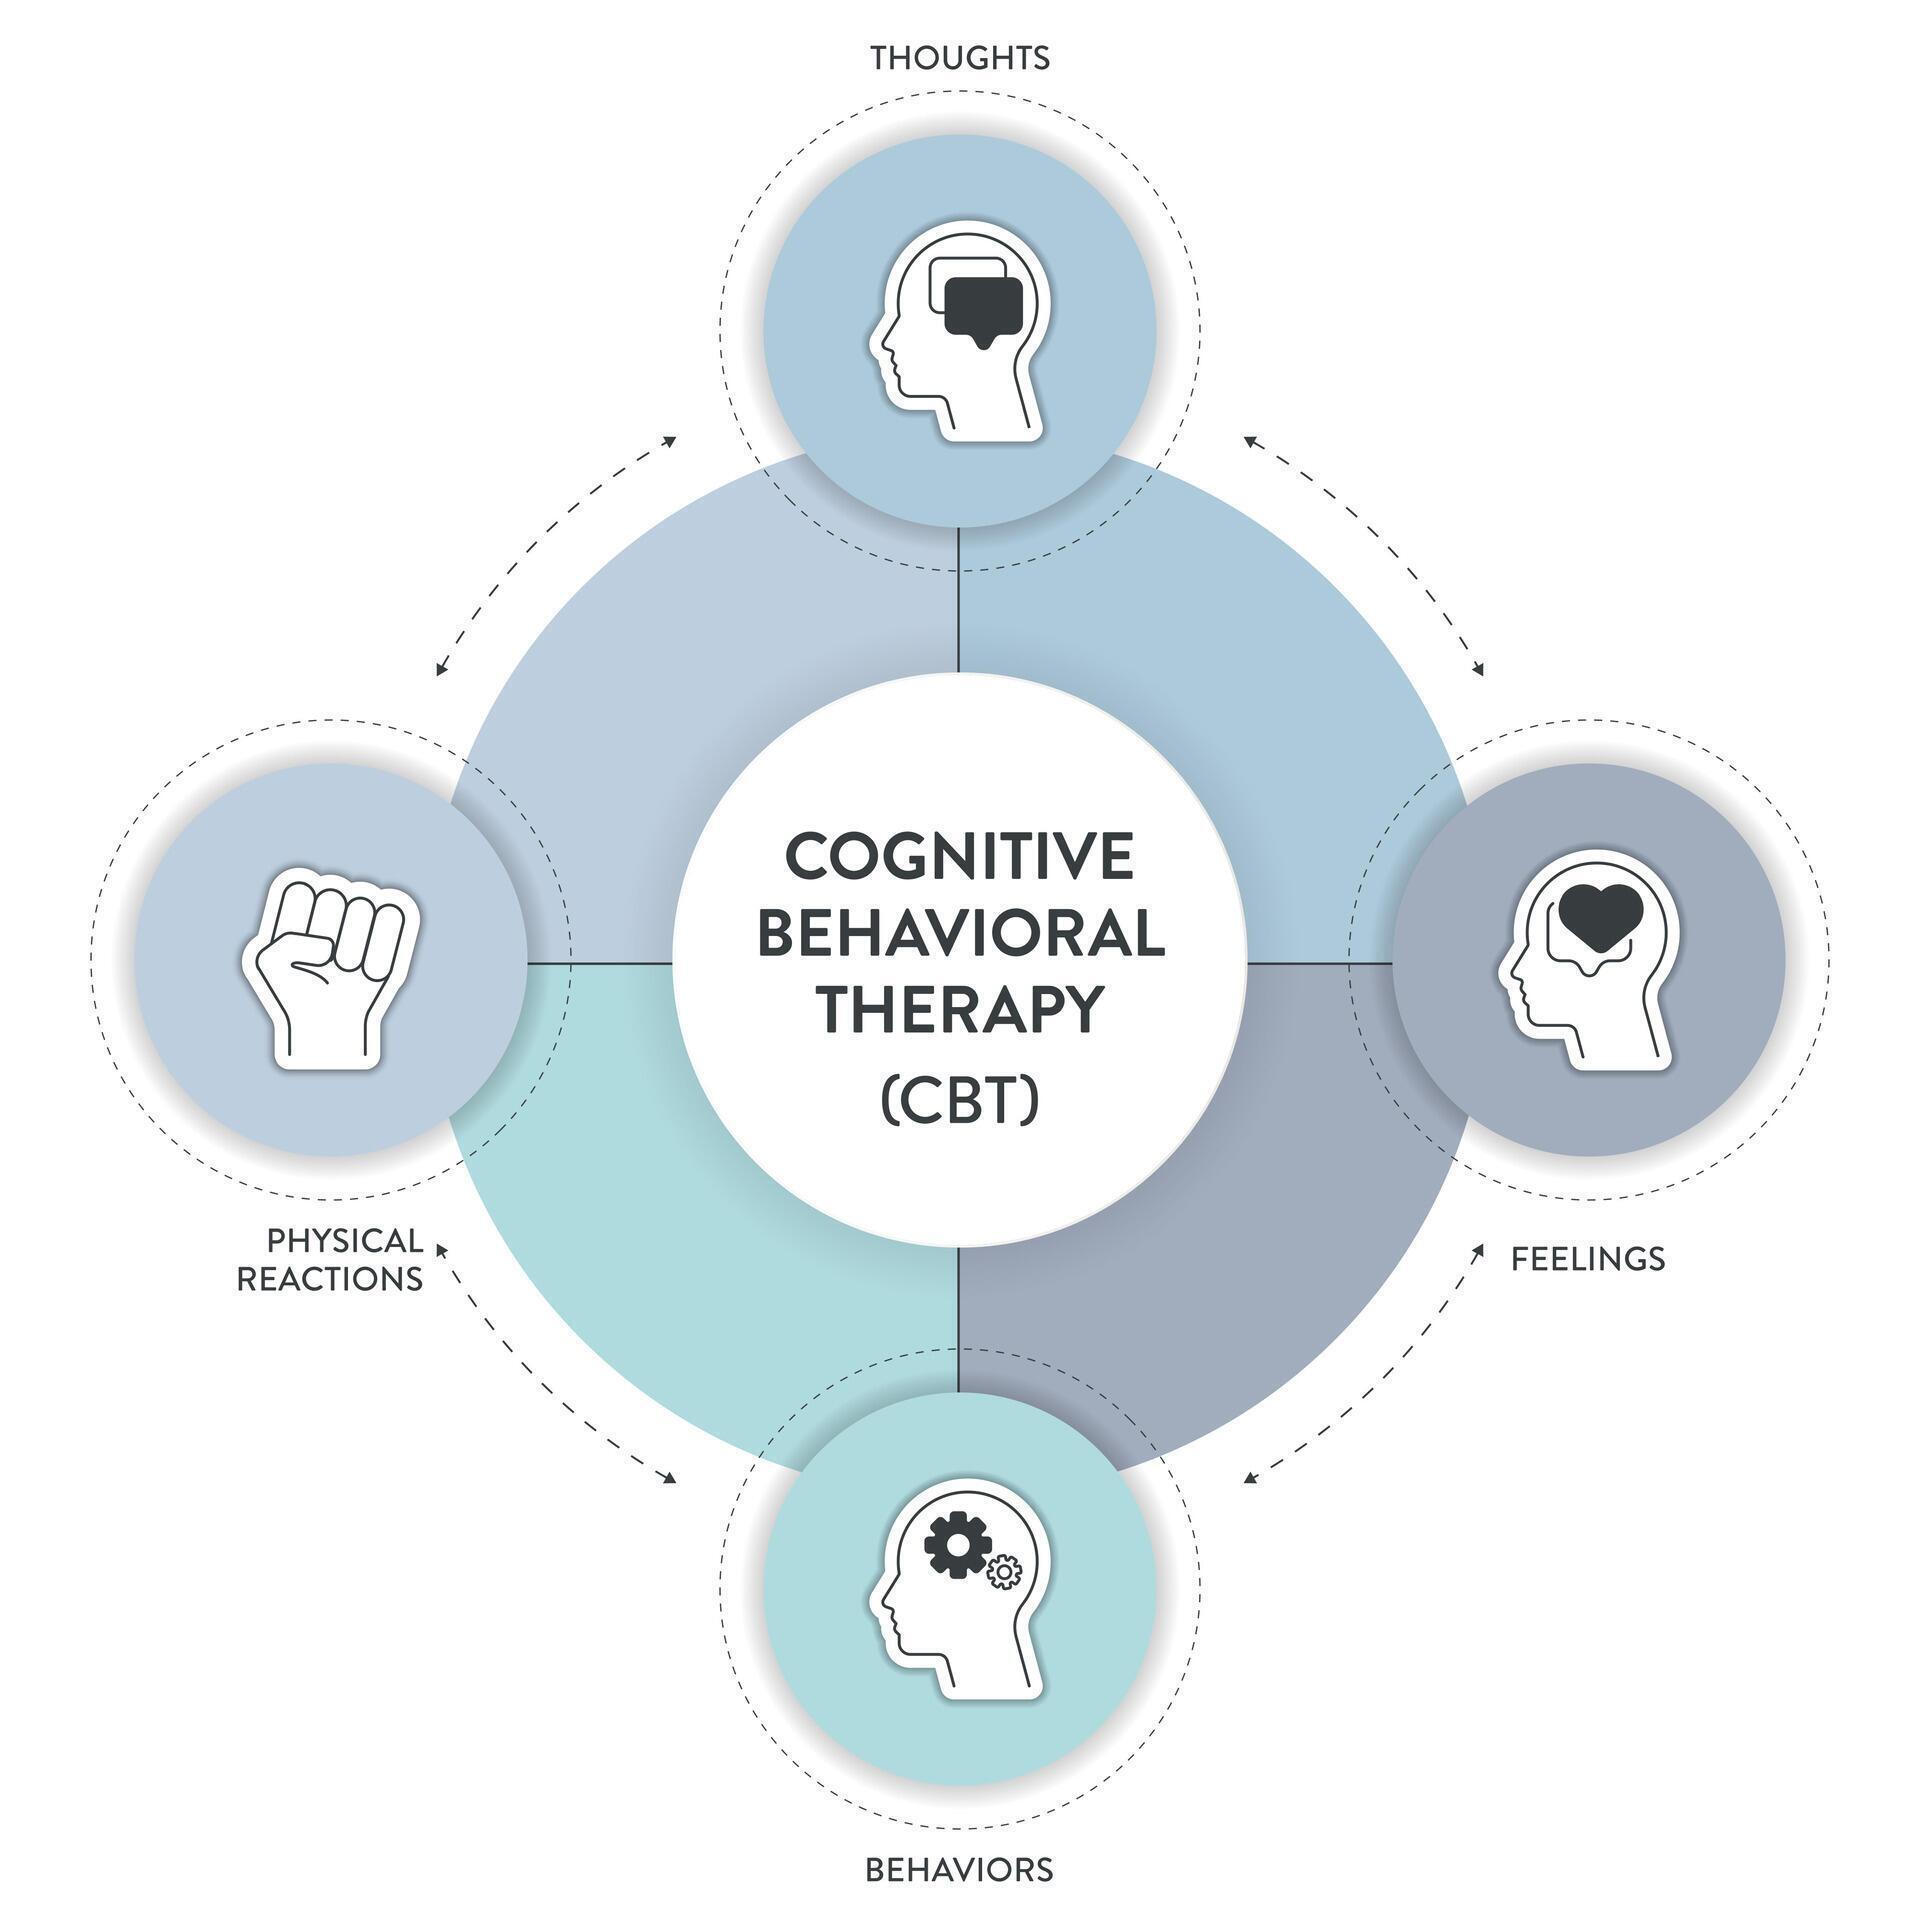
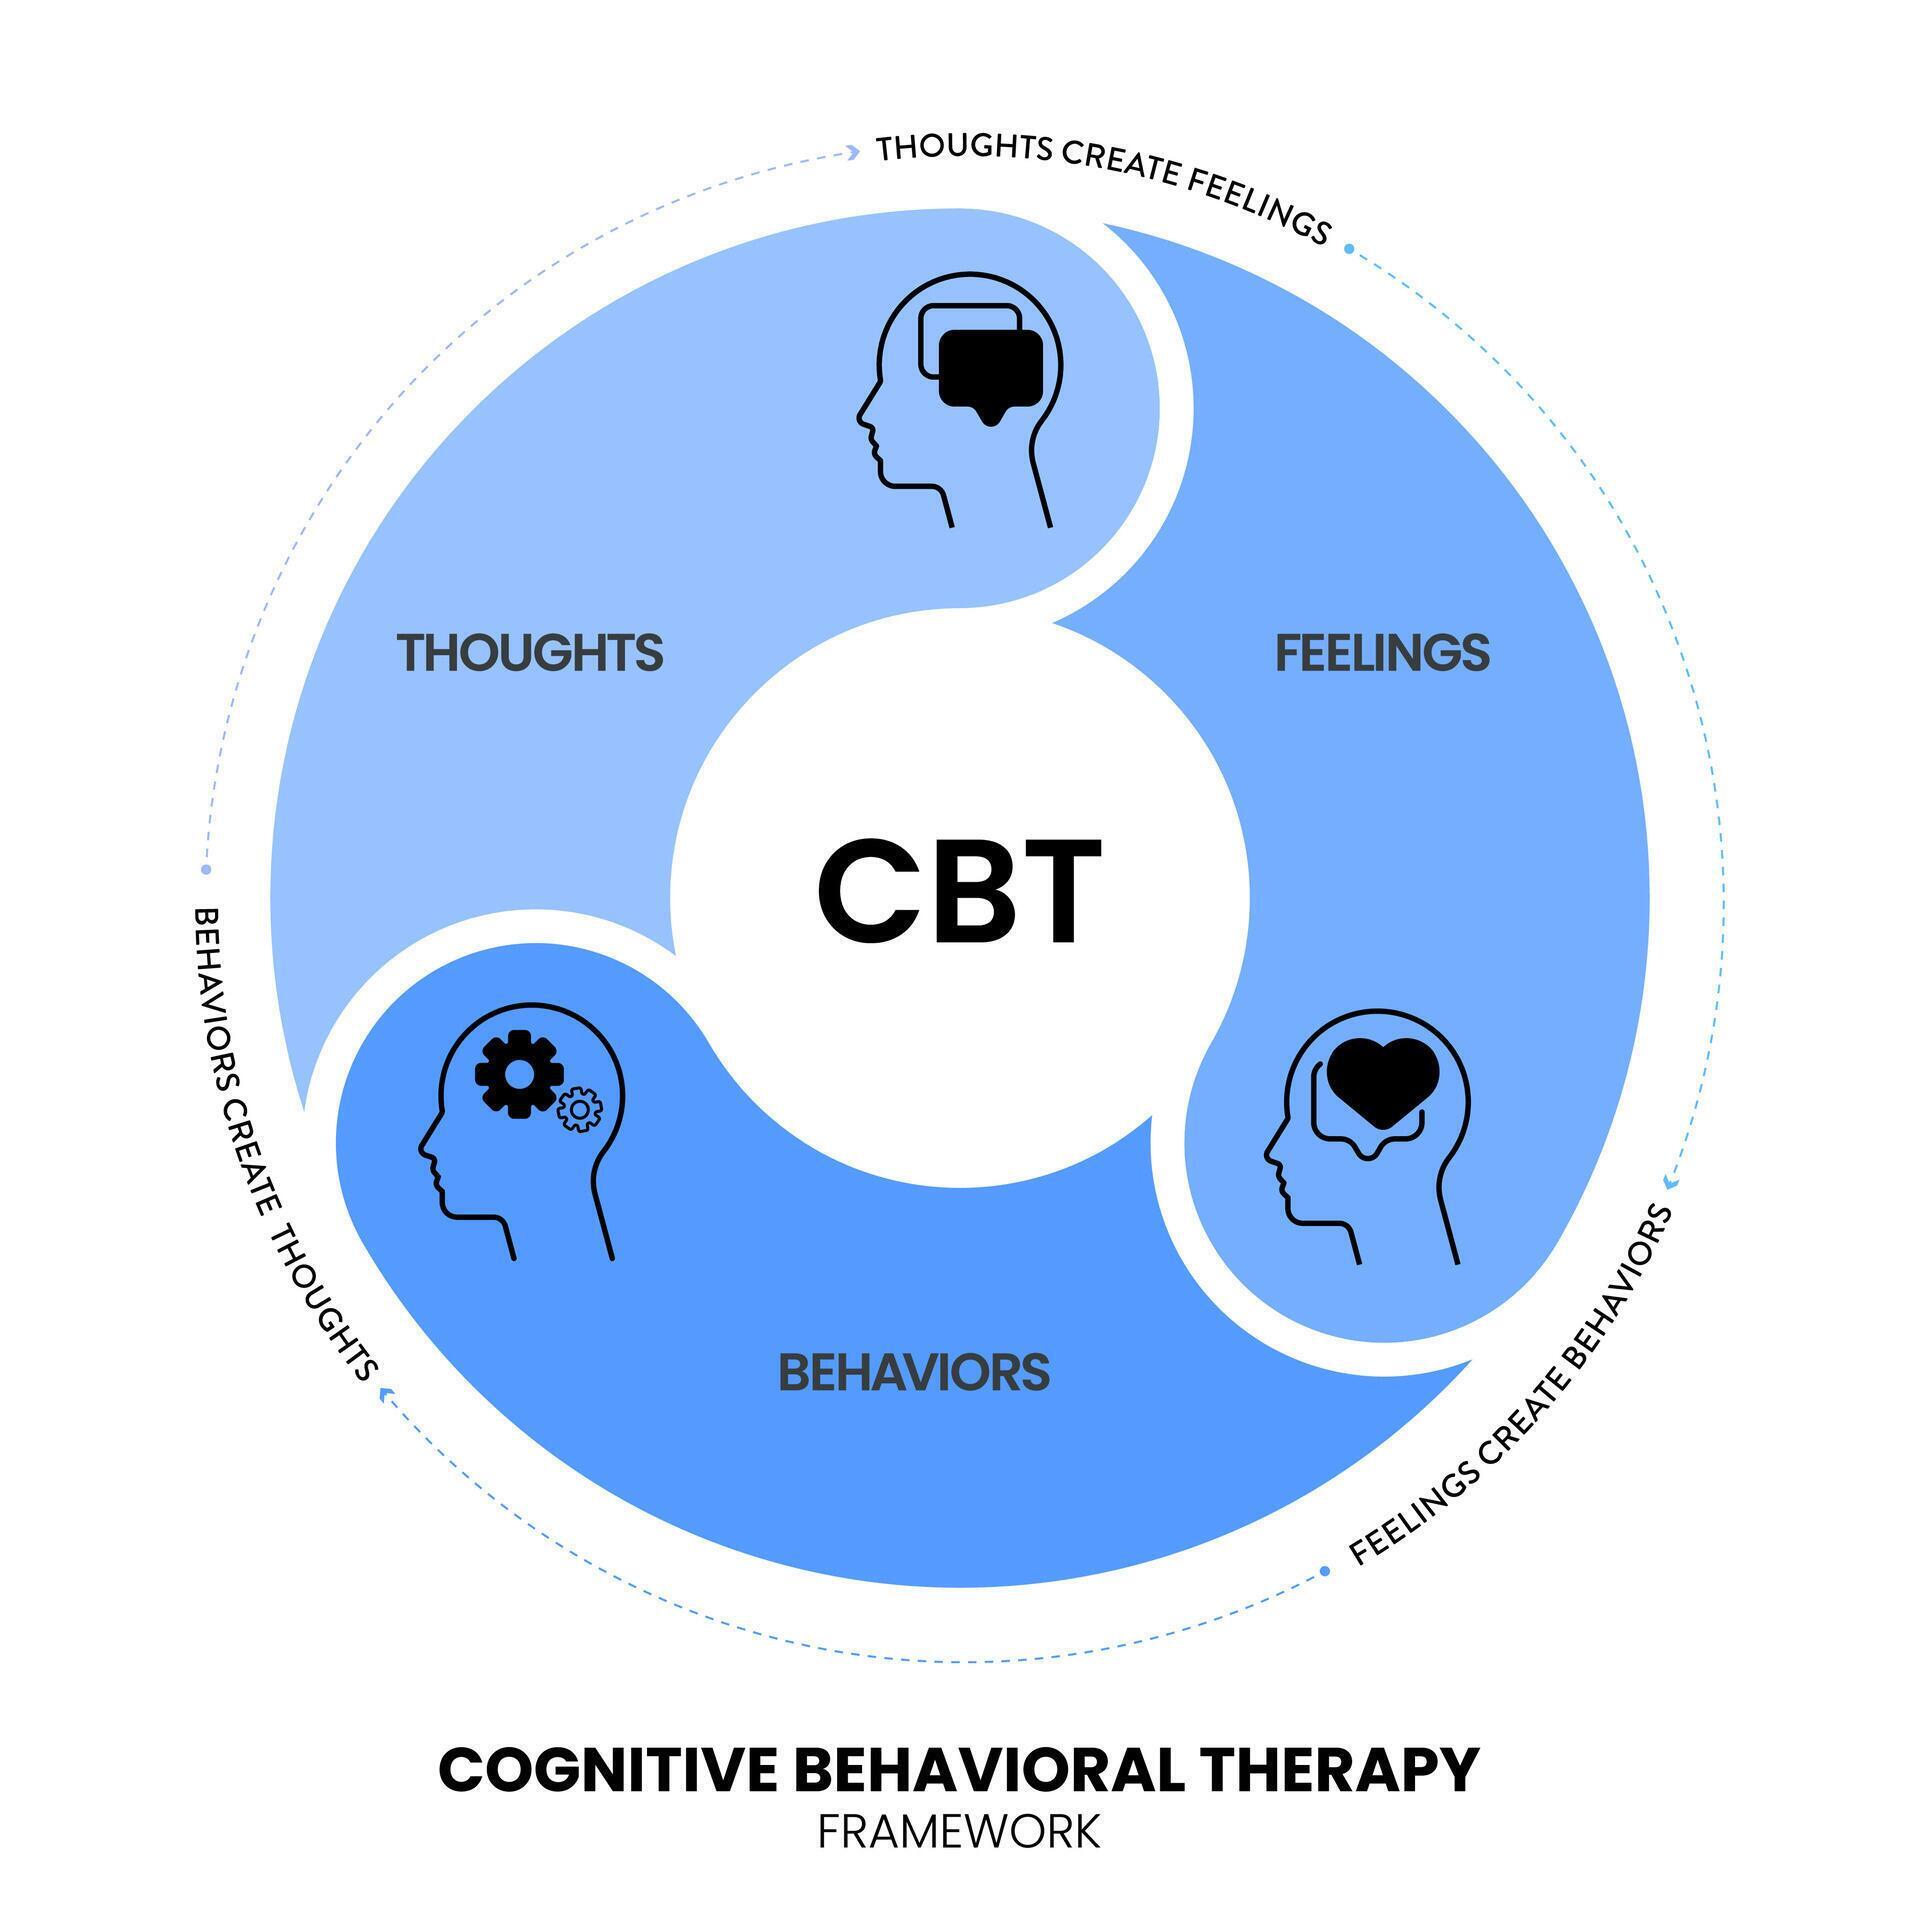
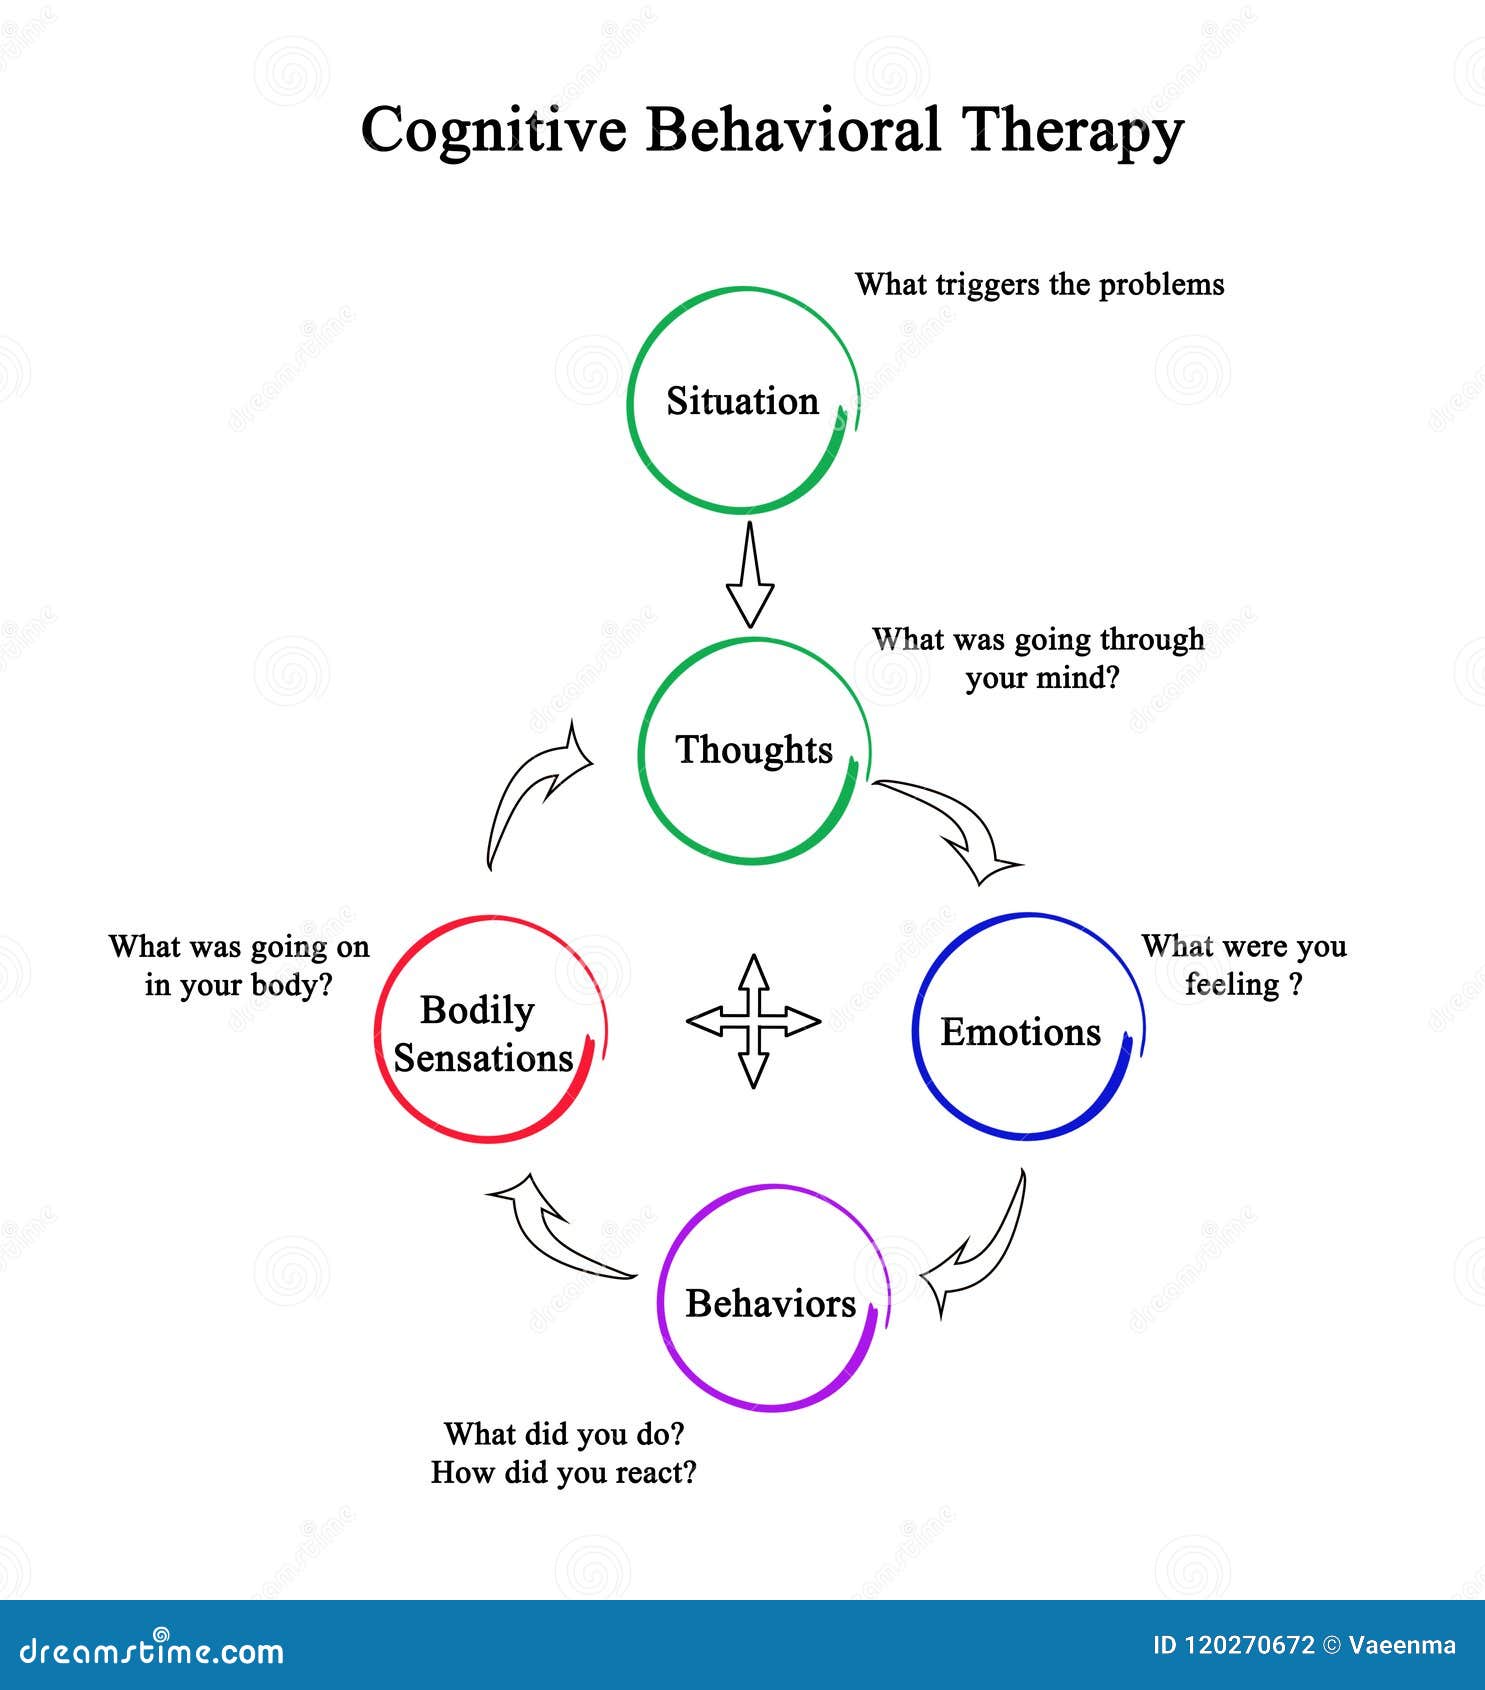
Cognitive Behavioral Therapy S works because it targets the feedback loop between thought, emotion, and behavior rather than pretending thoughts are just abstract nonsense floating around your head. You learn to catch automatic negative thoughts in real time, examine whether they actually hold up, and then run experiments to test new behaviors. That's the whole engine. The harder part is consistency and being brutally honest with yourself when you fill out your thought records, which most people skip after the first two weeks because it feels tedious. I've run through this process hundreds of times with people, and the biggest misconception is that CBT is just positive thinking dressed up in clinical language. It isn't. Positive thinking doesn't change neural pathways. What changes them is behavioral activation combined with cognitive restructuring done repeatedly until the brain stops automatically generating the old response. The "S" variation some clinicians use emphasizes skill-building and structured worksheets, which is basically the same thing with more homework assigned between sessions. Here's the practical method. First, you identify a specific problem situation — not "I feel anxious," but "I avoid sending emails to my boss after 6pm and then catastrophize about being fired." You write that down. Then you track the automatic thought that precedes the emotional spike. "If I send this email now, they'll think I'm lazy and resentful, and eventually I'll get called into HR." Next you rate how much you believe that thought on a scale of zero to one hundred. Most people rate it around eighty-five percent conviction even though it's entirely unproven.
Then comes the work. You generate evidence for and against the thought. You look for cognitive distortions — all-or-nothing thinking, fortune telling, mind reading. You develop a balanced alternative thought that's actually supported by evidence. "My boss has never criticized my work timing, and sending an email after hours is common in this company." You rate your belief in the original thought again. It usually drops to thirty or forty percent. You also design a behavioral experiment, like actually sending an email after six and tracking what happens. Usually nothing bad happens. That disconfirmation matters more than any reframe you can talk yourself into.
Where this actually falls apart
CBT struggles significantly with trauma-related disorders, obsessive-compulsive disorder, and personality disorders. Standard CBT protocols have modest effect sizes for depression, roughly 0.7 to 0.8 compared to waitlist controls, which is solid but nowhere near a cure. For OCD, you need Exposure and Response Prevention specifically, not standard CBT. For complex trauma, particularly when shame and attachment wounds are central, the cognitive restructuring piece can feel hollow and even harmful if the therapist pushes it too hard too early. People with borderline personality traits often benefit more from DBT or schema therapy. There's also the compliance problem. CBT requires between-session homework. Without it, outcomes drop substantially. I've seen clients do well in session and then go home and avoid every single assigned exercise, usually because the thought records felt exposing or the behavioral experiments triggered genuine panic. The workaround I use is lowering the barrier dramatically. Instead of a full three-column thought record, the person writes one sentence: "I thought X, I felt Y." That's it. Once they're doing that daily for two weeks, I gradually expand it. Nobody builds a habit from a task that feels like a chore on day one. Another edge case that trips people up is when the automatic thoughts are actually rational. If someone is in an abusive relationship and their thought is "my partner will punish me if I speak up," cognitive restructuring won't help because the thought is accurate. The intervention needs to shift to safety planning and behavioral change, not examining evidence for and against a survival response. I learned this the hard way with a client who kept "failing" at restructuring exercises. The thoughts weren't distorted. They were adaptive. We switched to risk assessment and concrete action steps and the treatment actually moved forward.
Get the Full Details

What actually helps people stick with it
Get a notebook or use a simple app for thought records. Don't overcomplicate it. The tool doesn't matter, but the externalization does. Writing the thought down reduces its emotional intensity immediately because it moves from a diffuse bodily experience to a concrete object you can examine. Pair the homework with an existing habit. Fill out your thought record right after your morning coffee, not at night when you're already mentally depleted. Expect the initial sessions to feel mechanical. They are. You're literally rerouting decades-old thought patterns, and that takes repetition before it feels natural. If standard CBT isn't reaching you after eight to twelve sessions, it's not a failure of the method necessarily. It might mean you need a different modality, a medication evaluation, or a therapist who specializes in your particular presentation. CBT is a tool, not a religion. It handles anxiety and depression reasonably well for mild to moderate cases. Beyond that, or when the issues are rooted in deeper relational or traumatic patterns, it hits a ceiling pretty quickly.