
Getting CBT to Work With Kids Isn't the Same as With Adults
Most therapists learn CBT through adult frameworks. That causes problems when you bring those models to a child. The cognitive restructuring piece, the part where you identify a thought, challenge it, and replace it, doesn't translate cleanly into a nine-year-old brain. Kids don't have the prefrontal cortex development to sit down and logically dismantle an anxious thought. They need the work to move through their body, their play, and their immediate sensory experience first. The thinking part comes later, and only after the nervous system has some regulation capacity. I spent years running CBT-informed groups for anxious and ADHD kids before I stopped trying to make them do thought records on whiteboards. One kid, Leo, age eight, would literally shut down every time I asked him to write down what he was thinking. Not because he couldn't think, but because the act of transcribing his internal state felt like exposure without any coping ramp. What worked was switching to a card sort. We used emoji cards and feeling Thermometers, and he pointed instead of writing. He still did the cognitive work, just through a different output channel. I learned that the technique matters less than the delivery method for this population.
Cognitive Behavioral Therapy Techniques For Children That Actually Hold Up
The core techniques in pediatric CBT diverge from adult practice in specific, measurable ways. Let me walk through the ones I use most and the ones I see fail repeatedly. Psychoeducation Through Stories This is your baseline. You can't do CBT with a kid who doesn't understand what's happening to them. The standard approach is to explain the fight-or-flight response using a brain analogy. I use the lizard brain versus the thinking brain framework, though some kids respond better to the alarm system versus the control room version. The key detail most people skip: you have to draw it. A kid can forget a verbal explanation in thirty seconds. A drawing of a brain with a red siren and a little person pressing buttons sticks. I spend roughly ten to fifteen minutes on this in the first session, sometimes longer if the parent is present and needs the same grounding.
Emotion Coaching Before Restructuring Here's a counter-intuitive point that beginners consistently miss. You need to build an emotion vocabulary before you touch cognitive restructuring. A child who cannot label what they feel cannot examine the thought behind the feeling. I see therapists rush to challenge catastrophic thinking in kids who still call everything "mad" or "bad." It doesn't work. The child has no hooks to hang the new thought on. Spend two or three sessions just expanding the emotional lexicon. Use the Feelings Wheel or a simplified version. Have them rate emotions on a scale of one to five, not just present or absent. Behavioral Experiments Replace Socratic Questioning
Get the Full Details
Socratic questioning, the back-and-forth where the therapist guides the client to discover the answer, works poorly with children under ten. Their working memory capacity limits how many steps they can hold simultaneously. Instead, I use behavioral experiments. If a kid believes that going to the cafeteria will cause them to vomit, you don't debate that thought. You design a graduated exposure where they go to the cafeteria for two minutes, then four, then ten, and you track the actual outcome against their prediction. The data does the restructure. This is significantly more efficient than trying to talk a child out of a fear, and it usually cuts the number of sessions needed for exposure work by about half. Thought Challenging Adapted for Kids When you do do cognitive work with children, you adapt the adult thought record into something they can physically interact with. The most effective format I've found is the Catch-Check-Change method, which maps directly onto the standard CBT cognitive triangle but uses language a kid can hold. Catch the thought by giving it a name or a face. Check it by asking what evidence supports it and what evidence contradicts it, framed as detective work. Change it by creating a new thought that's at least partially true, not falsely positive. The falsly positive part is important. Telling a kid who failed a math test that they're a genius at math doesn't restructure anything, it just creates resistance. The new thought has to be believable.
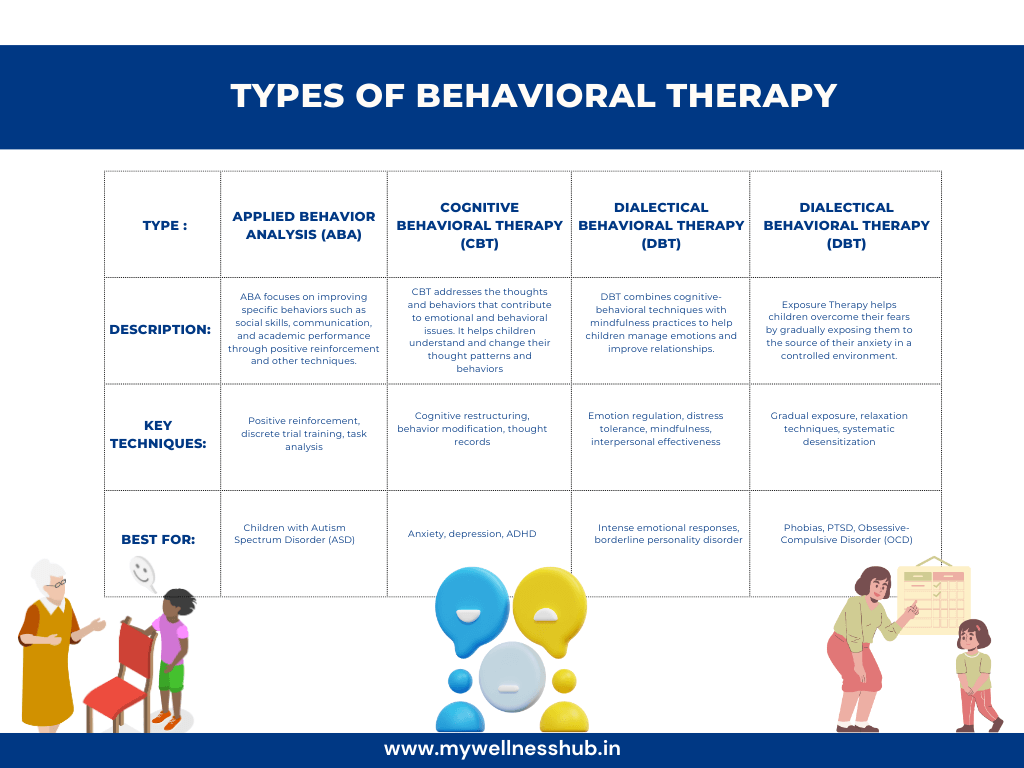
Exposure and Response Prevention for OCD ERP is the gold standard for pediatric OCD, and it looks different than adult ERP. Kids need more parent involvement in the early phases, and the exposures have to be shorter and more frequent rather than long and infrequent. A typical exposure hierarchy for a cleaning-related obsession might start with touching a doorknob and waiting two minutes before washing, progressing to touching the doorknob and waiting ten minutes, then washing with one hand instead of two. The response prevention piece, stopping the compulsion, is where most parents accidentally undermine treatment by allowing extra washing or reassurance seeking. You have to coach the parents separately on this. It's the single most common reason pediatric ERP stalls.
The Mechanics of a Pediatric CBT Session
A standard forty-five minute session for a child ages seven to twelve follows a loose structure, though I adjust it based on the day. We start with a check-in that's mostly observational. I watch how they move, how long they sustain attention, whether they make eye contact. That baseline tells me what techniques will land today. Then we do a brief skill review from last week, maybe five minutes. The main work is the intervention, thirty to thirty-five minutes. We close with a preview of what's coming next and a small homework assignment that's actually doable, not something that requires parental enforcement for more than twenty minutes a day. Homework in pediatric CBT is where most programs break down. A thought record worksheet is useless if the kid won't fill it out. I assign homework that's embedded in existing routines, like catching one anxious thought during dinner and naming it out loud, or practicing a breathing exercise while brushing teeth. The habit stacking makes compliance significantly higher without requiring additional supervision. Parents get their own parallel work. I run separate parent sessions every fourth week, usually twenty minutes, to address accommodation behaviors, model the language at home, and troubleshoot homework adherence. Without the parent component, progress in child CBT drops noticeably. The research consistently shows this, and my caseload has confirmed it repeatedly.

Where This Approach Fails Completely
I want to be blunt about the limitations because I see well-meaning therapists and parents try to force this into situations where it won't work. Cognitive Behavioral Therapy Techniques For Children do not work as a standalone intervention for moderate to severe depression in adolescents. When a teen's depression is backed by neurochemical dysregulation, CBT alone has a response rate around thirty-five percent. Medication combined with therapy raises that to approximately fifty-five to sixty percent. Saying CBT is the first-line treatment for pediatric depression is technically correct but practically misleading. You need to assess severity before committing to a therapy-only track. Autistic children process CBT differently, and the standard protocols need significant modification. Literal interpretation of metaphors, sensory overload from certain exposure exercises, and differences in Theory of Mind mean you can't just copy the adult CBT manual and hand it to an Autistic kid. The exposure hierarchy has to account for sensory triggers, not just social or cognitive ones. Some Autistic kids respond exceptionally well to CBT, others don't engage at all with the talk-based framework. When a child isn't responding after four to six sessions, I reassess the diagnosis and the fit, not double down on the technique.
Children with active trauma histories, especially complex trauma, often destabilize with standard CBT techniques. Exposure work can trigger flashbacks rather than process fear. Cognitive restructuring can feel invalidating when the child's threat perception is based on actual past danger, not cognitive distortion. For these kids, I phase the treatment. Regulation and safety first, sometimes for months, before introducing any cognitive or exposure work. The standard twelve-to-fourteen session CBT protocol is not appropriate here. Trauma-focused CBT exists for a reason, and it's structurally different from standard CBT. There's also a socioeconomic bottleneck that nobody talks about enough. CBT requires homework compliance, parent coaching, and regular attendance. Families working multiple jobs, families without reliable transportation, families dealing with housing instability, those kids fall through the gaps regardless of how well the technique works in theory. I've had kids who were ready to make real progress drop out because their parent couldn't make the Thursday appointment twice a month. The technique wasn't the failure, the delivery system was.
What to Look for in a Practitioner
If you're evaluating a therapist for a child, ask specifically about their CBT training. Not just that they use CBT, but how much structured CBT training they've completed and how many child cases they've handled. Many generalist therapists add CBT techniques to an existing modalities without the depth needed for pediatric application. A therapist who's done the certification in pediatric CBT will know the difference between standard exposure and developmentally appropriate exposure, and they'll adjust the pace accordingly. Watch the first session closely. A competent pediatric CBT therapist will spend significant time on psychoeducation, will involve the parents in the treatment plan from session one, and will give you a clear picture of what the work looks like week by week. If the therapist is vague about the structure or seems to be improvising based on how the child behaves that day without a framework, that's a signal. CBT is structured by design. It shouldn't feel like free-floating exploration. The best outcome data I've seen comes from therapists who treat the child and the family system simultaneously. A kid learning coping skills at school but returning to an environment where anxiety is accommodated or modeled will regress quickly. The skills don't transfer unless the environment supports them. This isn't a flaw in CBT, it's a limitation of any individual therapy model when applied to a child embedded in a family system.
Progress metrics matter too. Ask how the therapist measures change. Good CBT practice includes regular symptom tracking, either through standardized scales like the SCARED or CMAS-R for anxiety, or through simple weekly ratings. If you're not getting data on whether the treatment is moving the needle, you're flying blind. Ten sessions in and you should be able to tell whether this is working or whether you need to pivot.


