The Real Work Behind Beck's Model
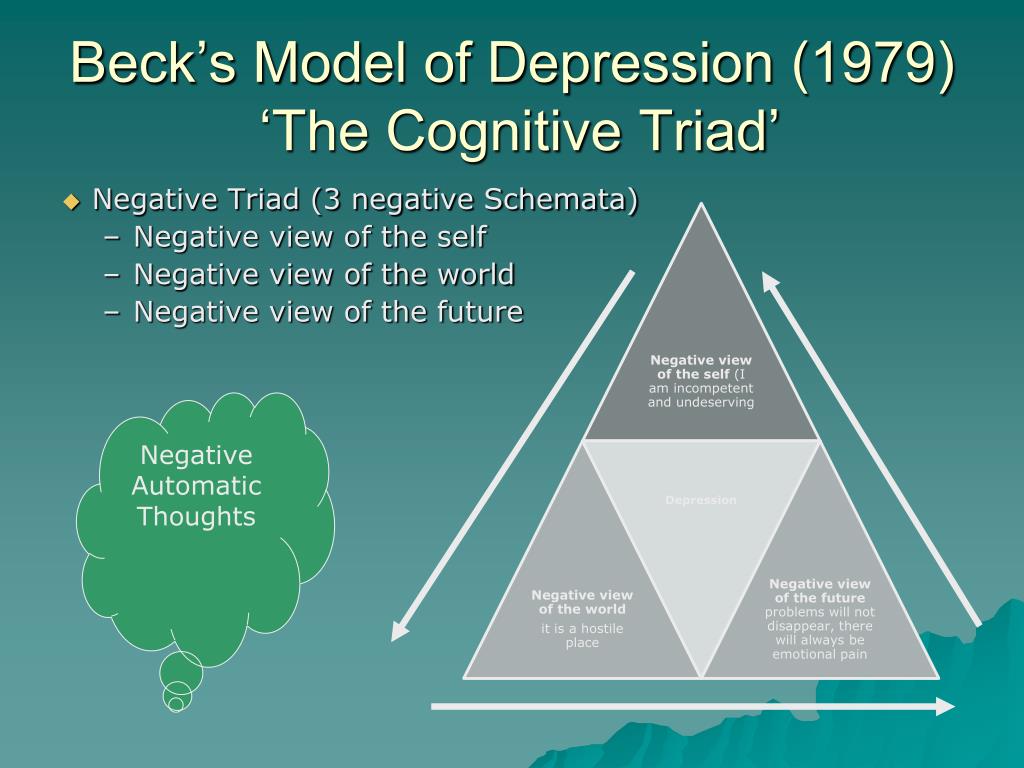
Most people encounter Cognitive Therapy Of Depression Beck through a Google search after their therapist mentioned it, or after reading a headline that claims CBT cures depression in six weeks. Neither is accurate. The therapy was developed by Aaron T. Beck in the 1960s when he noticed his depressed patients were having rapid, automatic negative thoughts about themselves, the world, and the future. He called these cognitive triads. They weren't philosophical observations. They were measurable, recordable data points that correlated with symptom severity. The model is straightforward on paper. Distorted thinking drives emotional distress. Change the thinking, change the distress. In practice, it is a structured, collaborative, skill-building process that requires homework, active participation, and a therapist who knows how to Socratic-discipline a patient who doesn't want to examine their own mind. It is not a listening exercise. It is not supportive counseling disguised as something more clinical.
Cognitive Therapy Of Depression Beck: How It Actually Works
Session structure typically runs between 45 and 60 minutes. The beginning is a mood check and agenda setting. You tell the therapist what you want to cover. The therapist suggests items based on previous sessions and what they think matters most. You negotiate. This isn't bureaucracy. It establishes collaboration, which is a core mechanism of change in Beck's framework. The middle of the session involves a targeted intervention. This could be identifying a cognitive distortion, conducting an experiment to test a belief, reviewing thought records from the week, or behavioral activation. The end includes summarizing what was done, assigning new homework, and checking whether the agenda was covered. Sessions usually range from 12 to 20 for a standard course of treatment, though some patients need longer and some finish earlier. The thought record is the primary tool. Patients document situations, automatic thoughts, emotions, and evidence for and against the thought, then generate a balanced alternative response. Most beginners mess this up by writing essays instead of concise entries. A thought record should take three to five minutes per entry. If someone is spending twenty minutes on one, they are ruminating, not processing.
Behavioral activation is equally important. Depression causes withdrawal. Withdrawal reinforces depression. Breaking the cycle means scheduling activities before motivation appears. Motivation follows action, not the other way around. This seems obvious until you watch a patient sit in session and honestly say they cannot imagine doing anything for the next three weeks, and they aren't being dramatic. They genuinely cannot access the concept of an activity.
Get the Full Details

The Parts People Get Wrong
The biggest mistake I see is treating cognitive restructuring as positive thinking. It isn't. It is evidence-based reasoning. Telling a depressed patient to look on the bright side is useless and often damaging because it invalidates their actual experience. Cognitive therapy asks the patient to evaluate their thoughts the way a court evaluates evidence. Is there proof? What is the counter-evidence? What would a neutral observer conclude? The goal is accuracy, not optimism. Another common failure point is skipping behavioral activation because the therapist or patient is obsessed with changing thoughts. Thoughts and behaviors reinforce each other. Working on one without the other slows progress significantly. I have seen patients who spent eight sessions dissecting the same core belief about worthlessness while their functioning continued to deteriorate because they hadn't started re-engaging with anything in their life. That is not therapy. That is intellectualization as avoidance. Socratic questioning requires real skill. A therapist who just asks leading questions that guide the patient toward the therapist's preferred conclusion is not practicing CBT. They are doing something else entirely. The patient must arrive at the alternative interpretation themselves. The therapist's role is to ask questions that reveal gaps in the patient's own reasoning, not to insert their own perspective disguised as inquiry.
I ran into a specific edge case last year that illustrates this. A patient came in with severe depression and a core belief that they were fundamentally unlovable. Standard cognitive restructuring wasn't moving the needle. We tried thought records, behavioral experiments, guided discovery. Nothing shifted the belief. The problem wasn't that the evidence was unclear. The problem was that the belief was serving a function. It was protecting the patient from the risk of trying again and failing. Once we identified that protective function and addressed it directly, the work accelerated. The belief wasn't a logic problem. It was a fear management strategy. This is the kind of thing that doesn't appear in the manuals.
When It Doesn't Work and What to Do Instead
Cognitive therapy has real limitations. It struggles with patients who have significant cognitive impairment, active psychosis, or severe personality disorders without comorbid depression. It is less effective for chronic, treatment-resistant depression where biological factors dominate. About 50 to 60 percent of patients respond adequately to CBT alone. The rest need medication, combination treatment, or a different therapeutic approach entirely. If someone has tried CBT and it didn't help, the failure could be due to several factors. The therapist may not have been adequately trained. The patient may not have completed homework. The diagnosis may have been incorrect. The depression may be secondary to an undiagnosed medical condition like hypothyroidism. These are all possibilities worth checking before concluding the therapy itself failed. For patients who don't respond to standard CBT, alternatives include interpersonal therapy, which focuses on relationship patterns rather than cognitive distortions. Psychodynamic therapy addresses underlying emotional conflicts that may predate the depressive episode. For moderate to severe depression, the combination of CBT and antidepressant medication consistently outperforms either treatment alone. This isn't a compromise. It's the most robust finding in the depression treatment literature.

The Beck Institute offers official training and certification pathways if you are looking for properly trained therapists. Their directory is one of the more reliable resources available. Self-help books based on Beck's model exist and can be useful for mild depression, but they lack the interpersonal corrective element that makes therapy effective. Reading about cognitive restructuring is not the same as doing it with a skilled therapist.
What Actually Changes
Research shows CBT produces changes in neural activity patterns similar to what antidepressants produce, but the mechanism is different. Medication alters neurotransmitter availability. CBT alters the patterns of thinking that drive those neurotransmitter systems. Neither approach is superior in a vacuum. They work through different pathways toward the same endpoint. Predictors of good outcome include external motivation, ability to complete homework, sufficient cognitive capacity to engage in structured work, and a therapeutic alliance that is collaborative rather than conflicted. Predictors of poor outcome include high levels of avoidance, passive interpersonal style, and therapists who spend more time agreeing with the patient than challenging unhelpful thinking. The homework component is where most people drop out. Not because the work is hard. Because it is boring and uncomfortable. Depression makes everything feel meaningless. Asking a depressed person to track their thoughts weekly feels like adding chores to an already overwhelming life. The therapists who keep patients engaged are the ones who make the connection between the homework and the patient's own stated goals explicit. If the patient says they want to get their life back, the therapist shows how the thought record directly serves that goal. If that link isn't clear, the patient won't do the work.
Cognitive Therapy Of Depression Beck remains one of the most empirically supported interventions in all of psychology. That is a factual statement, not a recommendation. It works well for the right patients with the right therapist. It doesn't work for everyone. Understanding which category you fall into before starting is the difference between wasting six months and finding actual relief.