What it actually is
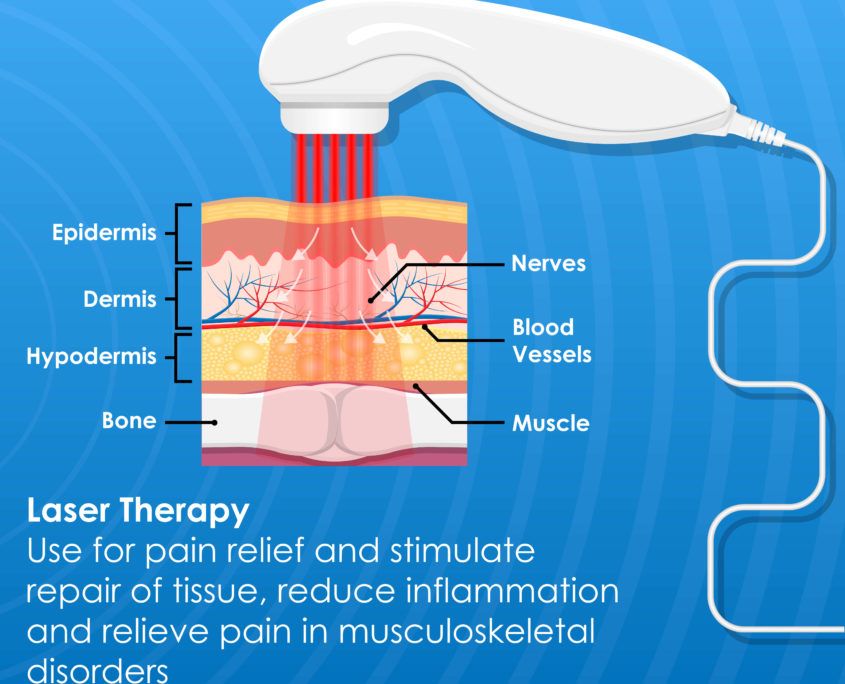
Cold laser therapy, sometimes called low-level laser therapy (LLLT) or photobiomodulation (PBM), is just delivering specific wavelengths of light into tissue at power levels that don't generate noticeable heat. The idea is that photons interact with cytochrome c oxidase in the mitochondria, which nudges cells to produce more ATP and shift into a repair mode. It's not magic. It's photon biology. A good device will sit in the red to near-infrared range—usually between 630nm and 905nm—and the wavelength you pick determines how deep the light actually penetrates. I started using these units around 2018 when I was dealing with some stubborn soft-tissue cases that weren't responding to standard protocols. The first few months were mostly me burning through trial and error. You'll see a lot of products claim they treat everything from plantar fasciitis to carpal tunnel to post-surgical swelling. Most of those claims are either weakly supported or flat-out inflated. The science exists, but it's messy and very parameter-dependent. That's the part nobody puts on the marketing page.
How to use Cold Laser Therapy without making a mess of it
Here's the practical workflow I end up going through most of the time, because it's the one that actually holds up in a real clinic setting where you're trying to treat people, not run experiments: Step one: pick the right wavelength. If you're treating something superficial—skin, tendons close to the surface, trigger points in the upper traps—stick to red light around 630-660nm. It doesn't penetrate past about 1-2cm but it concentrates energy where you want it. For deeper structures like the knee joint, hip flexors, lumbar paraspinals, or sciatic nerve pathways, you need near-infrared around 808-850nm. This reaches roughly 3-5cm into tissue. I once wasted about forty minutes treating a gluteus medius issue with a 660nm device because I had it on my bench and didn't check the specs. The patient felt nothing. Switched to 810nm and the response was noticeable by the third session. Don't skip this step. Step two: calculate your dose. Dose is measured in joules per square centimeter (J/cm²). The formula is simple: power in watts multiplied by time in seconds, divided by the treatment area in cm². So a 500mW probe delivering to a 4cm² spot for 30 seconds gives you 0.5 × 30 / 4 = 3.75 J/cm². Most conditions respond somewhere between 4 and 12 J/cm² depending on depth. Superficial issues often need the lower end. Deep joint or nerve work tends to need the upper end. There's a biphasic dose response, which means too little does nothing and too much can actually inhibit the cellular response. This is important and widely ignored. More isn't better. I've seen people run 20 J/cm² and wonder why the patient feels worse afterward.
Step three: set up the probe and the movement. There are two approaches. Stationary contact, where you hold the probe against the skin and deliver the full dose to one spot, and motion mode, where you slowly glide the probe across the area. Stationary works fine for small targeted spots like a trigger point or an acupoint. Motion mode is better for larger areas like the entire lumbar region or the knee. When I do motion mode, I move at roughly 1-2 cm per second. If you move faster than that, you're under-dosing. If you move slower, you risk over-dosing specific spots along the path. I usually mark the treatment zone with a skin-safe pen so I can keep a consistent pattern and not miss patches. Skipping this detail leads to uneven results and patients who can't tell if anything happened. Step four: determine session length and frequency. A typical acute soft-tissue case gets treated two to three times per week for about two to three weeks. Chronic cases might need three to four sessions per week for four to eight weeks, then a taper. I've found that stretching sessions out too far—like once a week for chronic issues—drastically reduces effectiveness. The cellular cascade needs repetition to build. One session every seven days barely registers. Consistency matters more than intensity here. Step five: document everything. Write down the wavelength, power output, treatment time, area size, total joules, and J/cm² for every session. Not because anyone will read it, but because six weeks later when you're trying to figure out why a patient improved or didn't improve, you'll have no idea what you actually did. I lost about three months tracking a sacroiliac case because I never wrote down the parameters I used in the first two weeks. Terrible habit. Don't do it.
Get the Full Details
One thing worth noting about the actual feel: the patient shouldn't feel much of anything. Maybe a faint warmth, maybe nothing at all. If they feel hot, you've either got a device that's actually outputting thermal-level power (some cheap "laser" devices are just LEDs or worse, diode heaters disguised as lasers) or you're focusing too much power on too small an area. Check your device specs before you ever put it on someone. I once had a patient complain about burning during what I thought was a standard 10mW session. Turned out the probe I was using had a cracked lens and was concentrating output into a hotspot. Swapped probes and the complaint stopped. Equipment maintenance isn't glamorous but it's non-negotiable.
Where it actually works and where it doesn't
Here's the honest breakdown. Things that have decent evidence behind them: lateral epicondylitis (tennis elbow), knee osteoarthritis, post-surgical edema and pain, diabetic neuropathy symptoms, myofascial trigger points, and some wound healing applications. The evidence here isn't "miracle cure" level but it's solid enough that professional guidelines in physical therapy and sports medicine actually mention it. Things with weak or inconsistent evidence: fibromyalgia widespread pain, autoimmune conditions, internal organ issues, anything claimed for systemic disease treatment. Those claims come from low-quality studies or are straight fabrication. Things that completely fail: anything requiring penetration beyond about 5cm without specialized high-power near-infrared arrays, fractures, infections, and malignancies. Do not use cold laser on cancerous tissue. There are case reports of it stimulating tumor metabolism. It's not worth the risk. The biggest pitfall I see people make is treating the wrong thing because they assume the laser will fix pain. It doesn't. It modulates inflammation and supports cellular repair. If the pain comes from mechanical compression like a herniated disc pressing on a nerve root, laser therapy might take the edge off but it won't decompress anything. You need a different intervention. I had a patient come in with radicular leg pain that I treated with laser for four sessions with minimal change. Imaging showed a significant L5 disc herniation. We escalated to targeted decompression work and the leg pain resolved in two weeks. The laser would have kept doing whatever it was doing indefinitely if I hadn't recognized the mismatch. Another common mistake is using devices with no verification. Cheap consumer-grade units often list a power output on the box that bears no relationship to what actually comes out of the probe. I tested five different "500mW" devices with a calibrated power meter and only two were within 15% of their stated output. The rest ranged from 40% to 120% of label claim. If you're doing this professionally, budget for a power meter. It costs about $150-300 and saves you from wasting months on treatments that aren't actually delivering dose. That's a detail most guides skip entirely.
Practical troubleshooting and edge cases
One specific problem I ran into that took me a while to solve involved treating the suprachoroid area around the shoulder for rotator cuff tendinopathy. The anatomy there is tricky because the supraspinatus tendon sits shallow under the deltoid but the subacromial space has complex curvature. Standard stationary pointing missed the actual tendon belly consistently. My workaround was combining two things: I used a 4cm² near-infrared probe in slow motion mode, tracing the subacromial corridor from the lateral humeral head toward the greater tuberosity, and I positioned the arm in 30 degrees of abduction with slight external rotation to open that space. That changed the effective penetration depth by about 1cm compared to the arm at the side. The patient went from a 7/10 pain level at rest to a 3/10 after four sessions over two weeks. Without the positioning adjustment, the same protocol produced almost nothing. Another edge case is treating patients with darker skin tones. Melanin absorbs light across the visible and near-infrared spectrum, so higher Fitzpatrick skin types (IV-VI) will absorb more of the photon energy at the surface before it reaches deeper targets. This doesn't mean you can't treat these patients—it means you may need to increase treatment time by 20-40% or use longer wavelengths like 905nm which penetrate deeper and are less affected by melanin absorption. I learned this the hard way with a patient whose baseline pain scores weren't budging despite what I thought was adequate dosing. Dropped the wavelength to 810nm, bumped the time by about 30%, and saw the first real improvement in session three. Always adjust for skin pigmentation. Standard protocols written for lighter skin will underdose darker skin. If you're looking to get into this properly, you'll need a legitimate device. There's no software download that replaces hardware here—this isn't a visual effect or a calculator. But there are calculators and treatment planning tools that help. I use a custom spreadsheet that takes wavelength, power, time, and area inputs and spits out J/cm² along with recommended protocols based on condition and tissue depth. It's saved me countless hours of re-deriving the math mid-session. If you want a starting point, search for "photobiomodulation dose calculator" and there are several open-source versions floating around. The one I modified from Dr. Tor quaile's published tables is probably the most clinically aligned. Pair that with a proper device and a power meter and you're in a better position than most people who walk into this field.

The limitations you need to accept
Cold laser therapy is not fast. Even in responsive cases, patients usually need three to six sessions before they notice a meaningful shift. It's not a one-and-done. It's also not reliable for everyone. Maybe 60-70% of appropriate cases show clear benefit. The rest either don't respond or respond minimally. Don't pretend otherwise. If a patient isn't improving after four sessions, reassess the diagnosis, the parameters, or the likelihood that laser is even the right tool. Pushing through eight more sessions with the same setup just wastes time and money. The devices themselves have limitations. Battery-powered units drop output as the battery depletes, which means a "500mW" setting might be 380mW by the end of a treatment day. Always check output at the start of each session. LED arrays have narrower beam patterns than true laser diodes, which affects how you calculate dose over irregular surfaces. And some so-called "laser" devices are actually just high-powered LEDs with no coherence. They can still produce photobiomodulation effects—LED light works—but the dose calculations and penetration characteristics differ slightly from true coherent laser sources. Know what you're actually using. I've been around this long enough to see trends come and go. Cold laser therapy is one of the few modalities that's stuck around because it actually does something measurable in the right situations. It's just not as simple as the marketing makes it sound. Get the parameters right, respect the dose-response curve, adjust for individual variables, and don't expect it to solve problems it was never designed to solve. The patients who benefit the most are the ones where you've actually thought through what's happening before you turn the device on.