Working Through the Coles 7 Steps Occupational Therapy Process
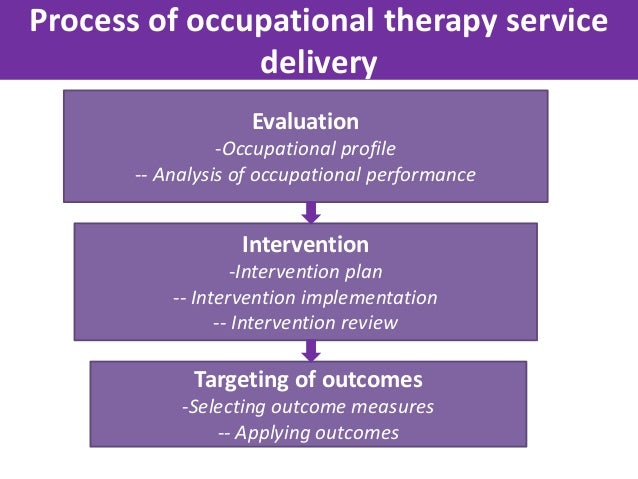
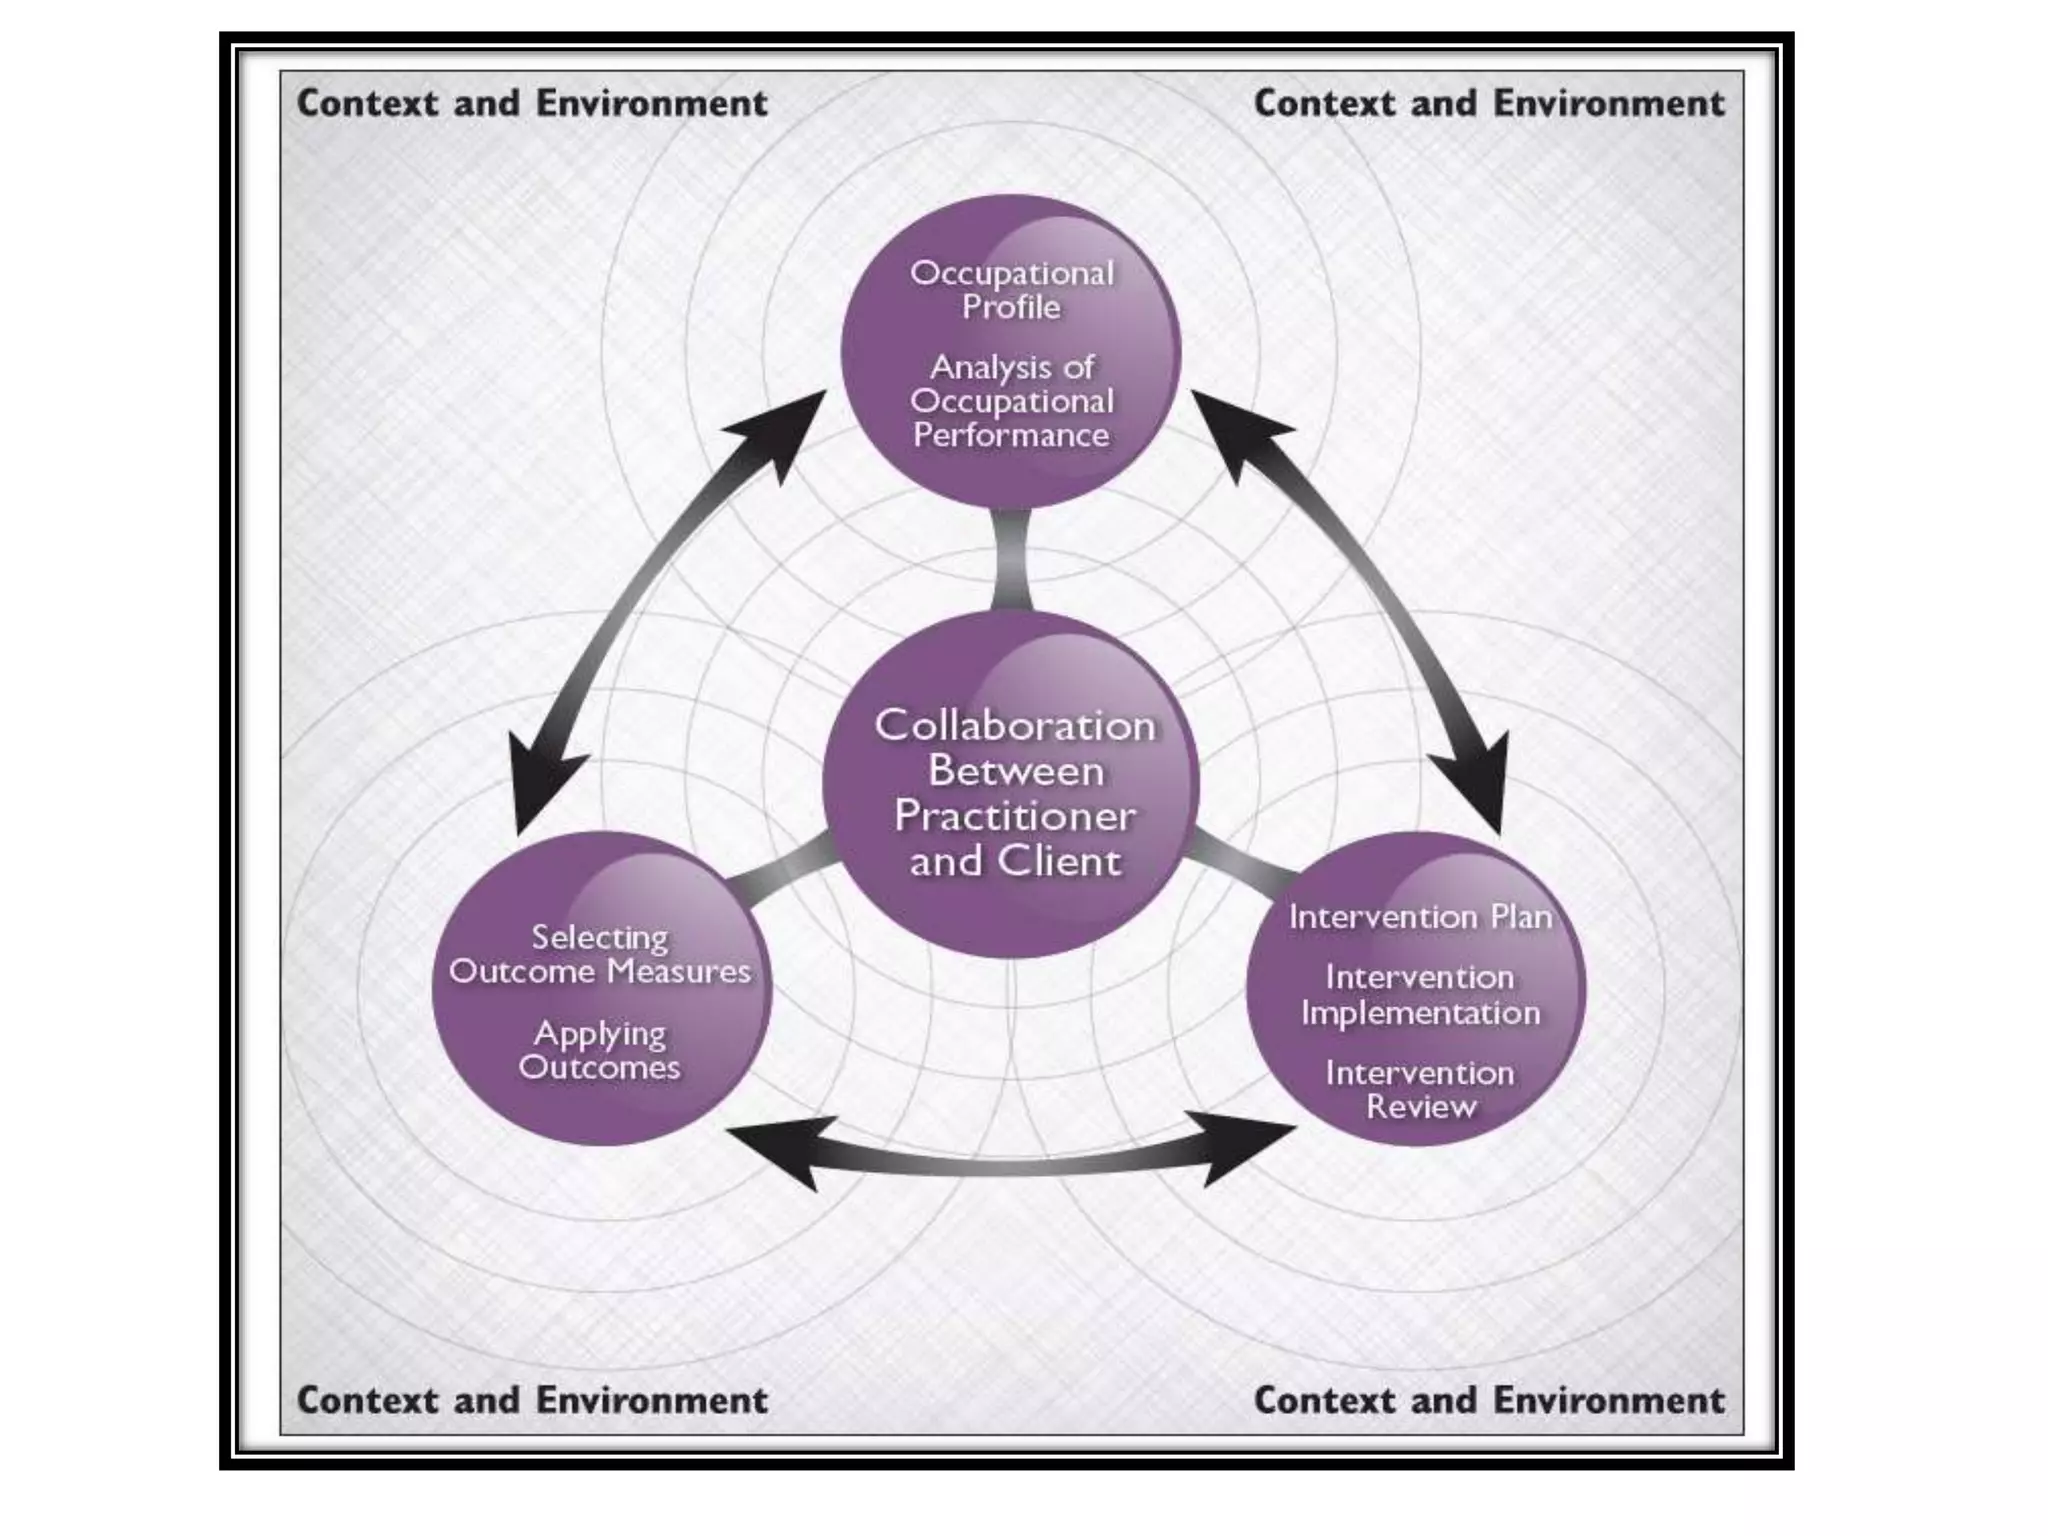
I've spent years navigating occupational therapy assessments and intervention planning, and the Coles 7 Steps Occupational Therapy framework has come up repeatedly in both my own practice and when discussing case files with colleagues. It's not the only way to structure an OT evaluation, but it's one of the cleaner models I've encountered for team communication and documentation purposes. The framework breaks down the clinical reasoning process into seven distinct phases. Here's how it actually plays out on a real caseload. Step one is activity analysis. This is where most people rush through because they've done it a hundred times before, but it's also where I've seen the biggest variation in quality. You're breaking down a client's occupation into its component parts — body functions, body structures, and performance skills required to complete the task. I once had a client assigned to a straightforward kitchen retraining program who, under close activity analysis, turned out to require significant upper extremity endurance work before he could even stand at the stove for five minutes. Skipping that step would have wasted weeks of therapy on tasks his body wasn't ready for yet.
Step two involves client interviews and goal setting. The COPM style interview comes in handy here. You're not asking "what do you want to improve?" You're asking specific questions about what activities are currently problematic and why they matter to that person. A retired accountant might not care about "improved ADL independence." What they care about is making their morning coffee without dropping the cup because their grip strength has deteriorated. The specificity matters for everything downstream. Step three is standardised assessment administration. This is where you pull tools like the AM-PAC, the Motor Assessment Scale, or the Berg Balance Scale depending on your client population. Don't treat these like box-ticking exercises though. I once saw an assessor use a Berg score to justify discharge when the client's actual reported difficulty was with stair negotiation — an activity the Berg doesn't adequately capture. The number looked fine. The client was still unsafe going up and down stairs at home. Step four is the physical examination. Range of motion, strength testing, sensation screening, balance assessment, coordination work. I've found that documenting baseline measurements with actual numbers — degrees of flexion, kilograms of grip force, time to complete the Timed Up and Go — makes progress measurement infinitely clearer than descriptive language. "Improved mobility" means nothing six months later. "TUG improved from 18 seconds to 11 seconds" is something you can measure against.
Step five is synthesising the findings into a problem list. This is where the framework really earns its keep. You're pulling together everything from the first four steps and creating a structured, ranked list of issues that directly impact the client's ability to perform occupations. I've seen people skip this step and go straight to intervention planning, which usually leads to treatment plans that address random symptoms rather than the underlying barriers to participation. That's inefficient and frustrating for everyone involved. Step six is intervention planning and goal writing. SMART goals are standard but often poorly executed. I prefer to frame goals around the specific activities identified in step two, measurable by the assessments used in step three, and time-bound to a realistic rehabilitation timeline. A goal like "client will independently transfer from bed to wheelchair with minimal assistance within four weeks" tells you exactly what success looks like and when to evaluate whether you're on track. Step seven is re-assessment and outcomes measurement. This is the step most people half-ass because they're already behind on documentation for the next client. It's also the step that determines whether your intervention plan was effective or whether you need to pivot. Re-administering the same standardised measures at follow-up allows you to track change objectively. I've found that scheduling the re-assessment before starting the intervention — booking the next appointment while the current one's still fresh — dramatically improves completion rates because it's already committed to the calendar.
Get the Full Details

Where This Framework Falls Short
The seven-step model isn't universal. It works well in hospital and rehabilitation settings where structured assessment is expected and resources allow for proper time allocation. It breaks down in community-based caseloads where you might have twenty minutes with a client and fifteen minutes of documentation time, not the hour-plus each step ideally requires. There's also a genuine tension between this framework's sequential structure and the reality of clinical reasoning, which is often iterative and non-linear. You might start with intervention and immediately discover you need more assessment data. The model doesn't really account for bouncing back between steps. In practice, I treat it as a checklist to make sure nothing's missed rather than a strict linear pathway. If you're working with complex neurology cases — stroke survivors with aphasia, traumatic brain injury clients with cognitive deficits — you'll find that the standardised assessment tools in step three often aren't valid for that population. You need alternative measures like the FIM or the Wolf Function Rating Scale instead. The framework's flexibility depends entirely on your willingness to adapt it rather than follow it rigidly.
The Coles 7 Steps Occupational Therapy approach gives you a reliable backbone for documentation and clinical reasoning. It won't replace the judgment calls that come with every case, but it will make sure those judgment calls are informed rather than improvised. That's usually enough.