Understanding Tuberculosis Testing
Tuberculosis testing is one of those medical procedures that sounds more complicated than it actually is, but the interpretation side is where things get messy. Most people coming through my office have been given a skin test, a blood test, or sometimes both, and they walk away confused about what the numbers mean. Here is how it works in practice, not just what the pamphlet says. The two main screening methods are the tuberculin skin test (TST), also called the Mantoux test, and the interferon-gamma release assay (IGRA), which is a blood test. They detect immune sensitization to Mycobacterium tuberculosis, but they do not tell you whether you have latent infection or active disease. That distinction matters a lot. A positive TST or IGRA means you have been exposed to TB bacteria at some point. It does not mean you are sick right now. You still need a chest X-ray and clinical evaluation to figure out what kind of infection you have.
Como Es El Examen De La Tuberculosis
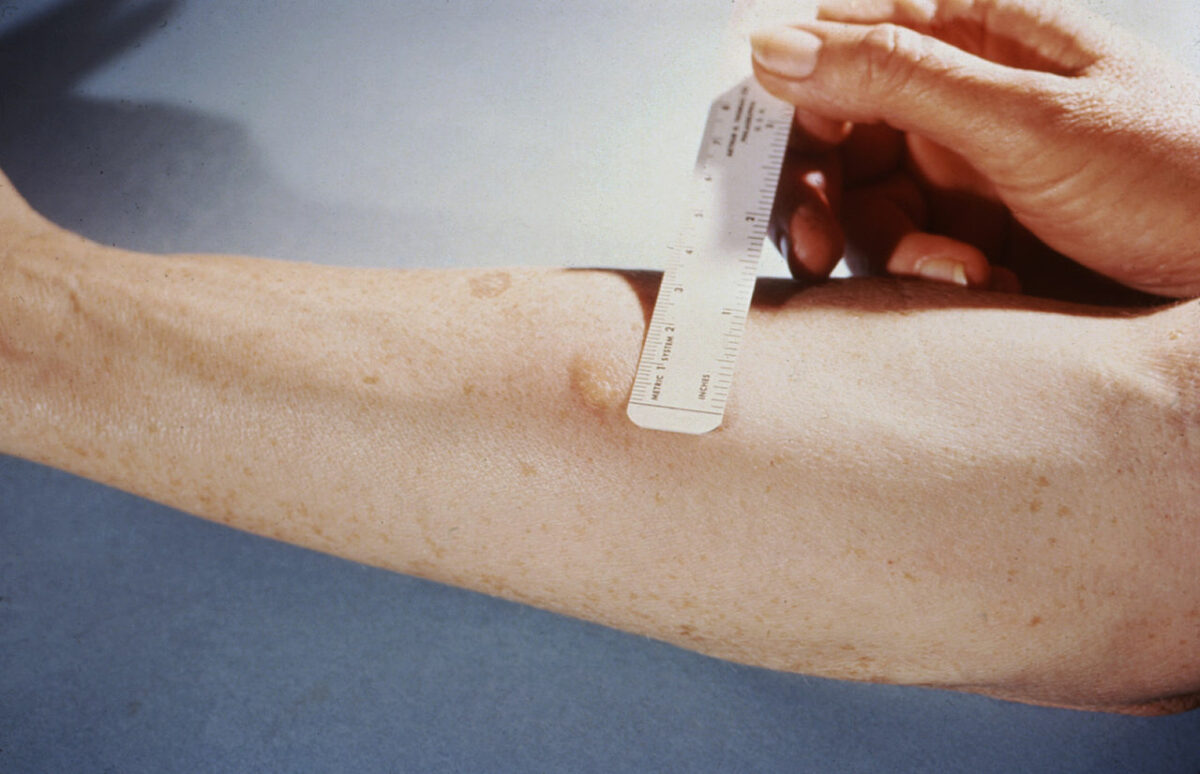
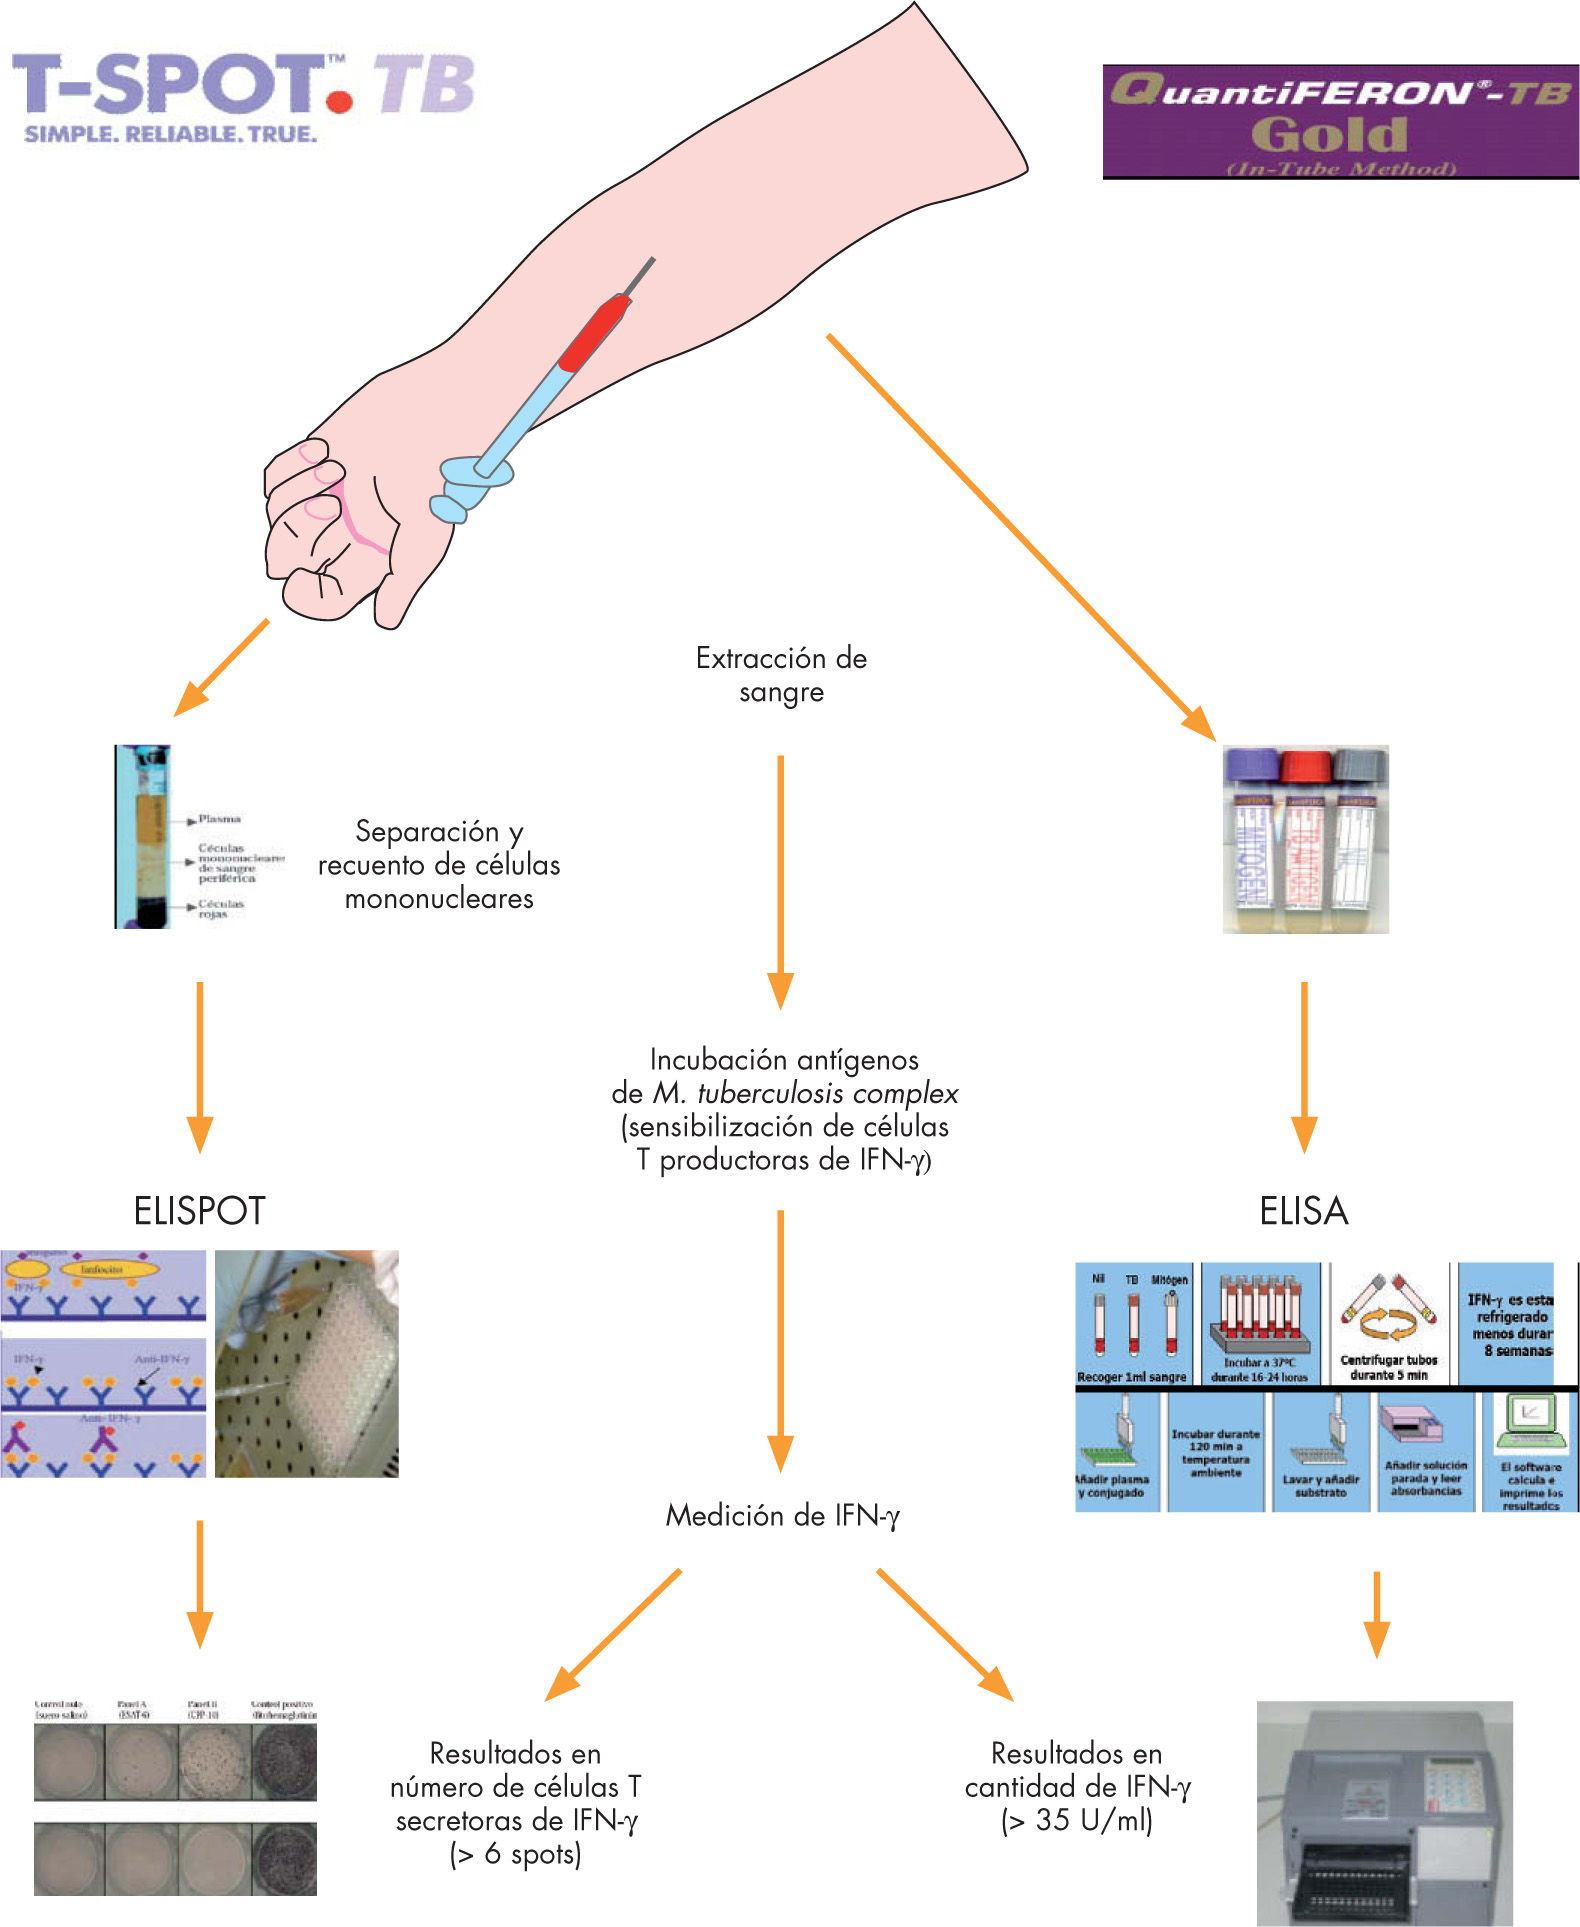
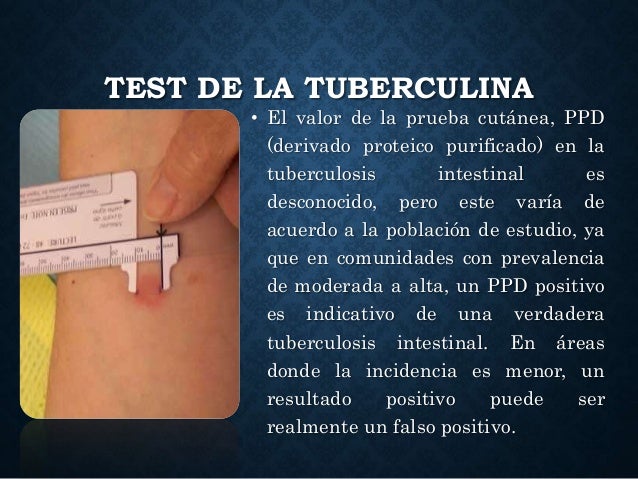
When people ask me about this, they usually want to know what to expect physically. The skin test is straightforward. A small amount of PPD (purified protein derivative) is injected intradermally into the forearm. You get a small raised bump, called a wheal, right when it is done. That wheal disappears within 10 to 15 minutes. The important part comes back 48 to 72 hours later when you return to have the induration measured. Not the redness. The induration. The firm, raised swelling you feel under the skin. If you measure the red area instead of the palpable induration, you are going to get inflated readings and unnecessary follow-ups. I had a patient last year who brought in a photo from a clinic that had measured the redness rather than the induration. They reported a 20-millimeter positive reaction. When I re-examined the arm, the actual induration was about 4 millimeters, which for her risk profile was negative. She avoided three months of unnecessary isoniazid treatment and a week of liver function monitoring. It is a common mistake. Clinics that do high-volume TB screening often rush the reading and default to measuring whatever looks bigger. The blood test, the IGRA, is simpler logistically. You draw blood once, send it to a lab, and get a result in a few days. There is no return visit. The two common versions are the QuantiFERON-TB Gold Plus and the T-SPOT.TB. Both measure interferon-gamma released by T-cells when they encounter TB-specific antigens. The T-SPOT uses an ELISPOT method and counts individual spot-forming cells. The QuantiFERON uses a colorimetric method and measures concentration in whole blood. They are roughly equivalent in specificity, though the T-SPOT tends to be slightly more sensitive in immunocompromised populations.
One thing most people do not realize is that the IGRA is not completely immune to false positives from the BCG vaccine. The antigens used in both QuantiFERON and T-SPOT are ESAT-6, CFP-10, and sometimes TB7.7. These proteins are encoded by the RD1 region of the M. tuberculosis complex genome and are absent from all BCG strains and most environmental mycobacteria. That is why the tests are more specific than the skin test. But if a lab uses older reagents or the sample hemolysis is significant, you can still get questionable results. I have seen QuantiFERON samples flagged as gray zone due to low internal control values, which usually means the patient is anergic or the blood cell viability dropped during transport. That gray zone result is worth paying attention to. Anergy, or the inability to mount an immune response, can happen in people with advanced HIV, active disseminated TB, recent live-virus vaccines, or chronic steroid use. If your test comes back indeterminate or borderline, do not just accept it as negative. Ask for a repeat test or switch to the other modality. In one case I dealt with, a patient on biologic therapy for rheumatoid arthritis had two consecutive indeterminate IGRA results. We did a TST anyway and it came out strongly positive. He had latent TB that would have been missed if we had trusted the blood tests alone.
Get the Full Details

Interpreting the Results
Interpretation depends entirely on your risk category. The CDC criteria are not arbitrary. A 5-millimeter induration is considered positive for people who are most likely to progress to active disease if infected. That includes HIV-positive individuals, recent contacts of someone with active TB, people with fibrotic changes on chest X-ray consistent with old TB, organ transplant recipients, and anyone on immunosuppressive therapy equivalent to more than 15 milligrams of prednisone daily for a month or longer. A 10-millimeter cutoff applies to higher-risk groups that are not in the highest tier. This includes recent immigrants from high-prevalence countries, injection drug users, residents and employees of congregate settings like prisons and nursing homes, healthcare workers, children under four, and people with certain clinical conditions like diabetes, chronic renal failure, or weight loss. The 15-millimeter cutoff is for people with no known risk factors. If you have a 12-millimeter reaction and zero risk factors, that is negative. Period. Do not let anyone pressure you into treatment for that. I have seen it happen, especially in urgent care clinics where the provider sees a positive test and immediately writes a prescription without considering the clinical context.
For the IGRA, there are no millimeter measurements. The result is non-reactive, reactive, or indeterminate. Non-reactive means no evidence of TB infection. Reactive means infection is likely. Indeterminate means the test could not be interpreted and needs to be repeated. The key thing about a reactive IGRA is that it requires confirmation. You do not start treatment based on a single reactive blood test. Guidelines say you need clinical correlation, a chest X-ray, and ideally a second test if the first is reactive but the pretest probability is low. Two reactive tests in someone with low pretest probability still carry a meaningful false-positive rate.
What Happens After a Positive Test
A positive screening test triggers a workup for active tuberculosis. You get a chest X-ray. If the X-ray is clear and you have no symptoms, you have latent TB infection, not active disease. Symptoms that matter include cough lasting more than three weeks, hemoptysis, fever, night sweats, and unintentional weight loss. If the X-ray shows abnormalities suggestive of TB, you need sputum induction or bronchoscopy for acid-fast bacilli smear and culture, plus nucleic acid amplification testing. Treatment for latent TB is not something to take lightly. The standard regimen used to be nine months of isoniazid. Now there are shorter options like three months of isoniazid plus rifapentine once weekly, or four months of rifampin daily. Each has tradeoffs. Rifampin interacts with a huge number of medications. I had a patient on anticoagulation therapy whose INR spiked because we did not account for the rifampin interaction. It took weeks to recalibrate. Isoniazid carries a risk of hepatotoxicity and peripheral neuropathy. Pyridoxine supplementation is mandatory with isoniazid to prevent nerve damage. The biggest issue with latent TB treatment is adherence. A nine-month course of pills has a completion rate of about 60 percent in real-world settings. The shorter regimens improve that significantly. From what I have seen, the three-month once-weekly regimen gets completion rates closer to 80 percent because the direct observation requirement keeps people accountable. But it requires a clinic visit every week, which is a barrier for working people. The four-month rifampin daily regimen is the easiest to tolerate but still demands daily pill-taking for over 30 days straight.
Limits and Failures of TB Screening
No test is perfect. The skin test has well-documented issues with both over- and under-diagnosis. False positives come from prior BCG vaccination, exposure to non-tuberculous mycobacteria, and technician error in reading. False negatives happen in people who are anergic, who were recently infected and have not yet seroconverted, or who had the test read outside the valid 48-to-72-hour window. Reading before 48 hours gives a falsely small measurement. Reading after 72 hours can miss the peak induration. The blood test has its own problems. It is more expensive per test, usually around $80 to $150 out of pocket without insurance compared to roughly $15 to $30 for a skin test. It requires a venipuncture, which some patients cannot tolerate. It is affected by delays in processing the blood sample. The QuantiFERON tube needs to be processed within 12 to 16 hours of collection. If the lab is across town and the phlebotomist ships it at the end of the day, the result may be indeterminate. The T-SPOT is more forgiving on timing but still has practical constraints. Neither test detects active TB reliably on its own. You can have active pulmonary TB and still test negative on both TST and IGRA if your immune system is too suppressed to mount a response. Conversely, you can have a strongly positive IGRA and completely normal lungs with no signs of active disease. The tests measure immune memory, not bacterial load. That is why clinical judgment matters more than any single number.
If you are getting tested for employment, immigration, or school requirements, make sure you understand which test they accept. Some programs require the skin test specifically. Others accept either. Immigration physicians in the United States often prefer the IGRA because it eliminates the need for a return visit, but that is a convenience issue, not a medical one. The clinical accuracy is comparable when both tests are done correctly. The most practical advice I can give is to ask questions. Ask what size induration is being used as the cutoff for your risk group. Ask whether they are measuring induration or erythema on a skin test. Ask whether a lab result is reactive, non-reactive, or indeterminate on a blood test. Ask what the next step is if your test is positive. Most clinics will give you a result and hand you a pamphlet. You deserve to understand what that result actually means for your health.