
Building a Presentation on Asthma Diagnosis
I spent about three weeks putting together a solid presentation on how bronchial asthma gets diagnosed because the existing slides I found were either too basic or full of outdated guidelines. Most of them skipped important diagnostic criteria or listed spirometry without explaining what actually qualifies as a positive result. I wanted something that would work for medical students and also be accurate enough that a practicing clinician wouldn't cringe when shown. The structure I ended up with starts with the clinical presentation. You need to establish symptoms first—wheezing, dyspnea, chest tightness, and chronic cough that worsens at night or early morning. These are standard but easy to gloss over too quickly in a slide deck. I made sure each symptom gets its own callout with the epidemiological context that roughly 300 million people worldwide live with asthma and the prevalence varies dramatically by region and socioeconomic status. Next comes the spirometry section, and this is where most presentations get it wrong. They show a flow-volume loop and label it "obstructive pattern" without walking through the actual numbers. I included the specific criteria: FEV1/FVC ratio below the lower limit of normal (not just below 0.70 in adults—that's an oversimplification that misses early disease in older patients). The post-bronchodilator improvement threshold of at least 12% and 200ml in FEV1 is non-negotiable and I made sure it's prominent.
Here's something I learned the hard way during a residency presentation. A senior attending pointed out that I'd failed to mention that up to 25% of patients with classic asthma symptoms can have normal spirometry between exacerbations. That single omission made the entire diagnostic algorithm look naive. I went back and added a dedicated slide on peak expiratory flow variability monitoring and challenge testing for those cases.
Key Diagnostic Tools to Include
Beyond spirometry, your presentation should cover fractional exhaled nitric oxide (FeNO) testing. It's not diagnostic on its own but it's increasingly part of guideline recommendations for confirming eosinophilic airway inflammation. Values above 50 ppb in adults support an asthmatic etiology. I've seen too many decks either ignore FeNO entirely or present it as a standalone confirmatory test when it should really be framed as supportive evidence alongside clinical assessment. Imaging is another section that gets handled poorly. Chest X-rays in asthma are typically normal or show hyperinflation. The value isn't in diagnosing asthma—it's in ruling out alternatives like pneumonia, pneumothorax, or cardiac failure. I structured that slide to emphasize differential diagnosis rather than positive findings, which is more clinically useful. Allergy testing deserves attention too. Skin prick testing and specific IgE measurements help identify triggers and support the diagnosis in atopic individuals, but they're adjunctive. The common mistake is presenting allergy results as definitive proof of asthma when they only demonstrate atopy. I made that distinction explicit with a side-by-side comparison table.
Get the Full Details
Structuring the Content for Different Audiences
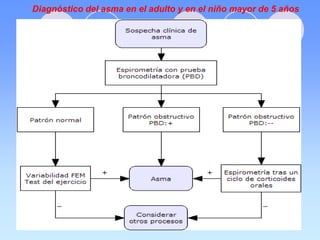
The approach changes depending on who you're presenting to. For medical students, you need more foundational physiology—explaining airway hyperresponsiveness, reversible obstruction, and the inflammatory cascade. For nursing staff or respiratory therapists, the focus shifts to diagnostic workflow, when to refer for pulmonology, and recognizing red flags that suggest alternative diagnoses. I built two versions because one size doesn't work here. One practical issue I ran into was slide density. Early drafts had too much text per slide, which is the default mistake when you're trying to cover a comprehensive diagnostic algorithm. The fix was using visual algorithms—flow charts showing the stepwise diagnostic approach per GINA guidelines—combined with speaker notes that contain the detailed information. This way the slides remain clean and the depth stays accessible without cluttering the visual space.
Common Pitfalls in Asthma Diagnosis Presentations
The biggest error I encountered across multiple existing presentations was conflating asthma with COPD without addressing the overlap syndrome. Patients with ACO (asthma-COPD overlap) exist and they're becoming more common as smoking rates shift and populations age. A diagnostic presentation that doesn't acknowledge this gap leaves viewers with an incomplete mental model. I added a section comparing diagnostic features of asthma versus COPD versus ACO with tables that highlight overlapping and distinguishing features. Another recurring problem is the underrepresentation of pediatric diagnosis. Childhood asthma diagnosis relies heavily on clinical history because spirometry is less reliable in young children. The presentation needs to address age-specific criteria, including the use of trial therapies and response monitoring in children under five where objective testing is limited. I found guidelines vary considerably here between pediatric and adult sections, and most slide decks ignore this discrepancy entirely. Cost and accessibility issues are rarely mentioned but they matter in real clinical practice. Spirometry isn't universally available in primary care settings in many regions. FeNO testing is even less accessible. A presentation that assumes all diagnostic tools are equally available creates a distorted picture of how diagnosis actually happens outside tertiary centers. I included a brief note on resource-stratified diagnostic approaches because omitting this made the content feel disconnected from everyday practice.
The diagnostic criteria themselves have shifted over the years, and many presentations circulate with outdated information. The GINA guidelines moved away from recommending short-acting beta agonists as sole rescue therapy, and while this is primarily a treatment change, it has diagnostic implications because uncontrolled symptoms on SABA-only therapy should prompt re-evaluation of the diagnosis. Keeping guidelines current is harder than it sounds because you have to verify every referenced document against the latest publication date.

Final Notes on Accuracy
I cross-referenced everything against the latest GINA report, the Mexican Society of Pneumology and Angiology guidelines (since the original topic is in Spanish and those guidelines are relevant for Latin American contexts), and the ATS/ERS statement on spirometry interpretation. Having conflicting sources isn't unusual in this area, so noting where guidelines diverge is more honest than pretending consensus exists where it doesn't. The resulting deck runs about 45 slides with speaker notes, covers the full diagnostic pathway from suspicion through confirmation, and explicitly marks areas where clinical judgment supersedes algorithmic criteria.



