The Real Mechanics of Evaluating Whether Someone Can Handle Their Own Trial
Most people think competency is binary. It isn't. You either understand the proceedings and can assist counsel, or you don't. The Dusky standard from 1960 still governs this in federal courts and most states, but applying it in practice requires navigating a lot of gray area that textbooks don't cover well. I recently finished an evaluation for a defendant who scored well above the clinical cutoff for intellectual disability on the WAIS-IV. He should have been cleared. When I broke down his functional understanding of what "pleading guilty" actually meant versus "going to trial," he couldn't distinguish between the two concepts at all. He thought pleading guilty would make the charges disappear. We spent another three hours on adaptive functioning and found his real-world conceptualization was severely impaired despite average-scale IQ scores. That's the kind of result that doesn't show up in a quick screening.Competency To Stand Trial Assessment: What Actually Gets Measured
A proper Competency To Stand Trial Assessment covers several domains. You're looking at whether the defendant understands the charges against them, comprehends the roles of judge, jury, prosecutor, and defense attorney, grasps the range of possible sentences, and can communicate effectively with their lawyer about case strategy. The ability to reason through legal decisions matters just as much as the factual recall. I use a combination of structured instruments and clinical interview. The MacArthur Competence Assessment Tool-Criminal Adjudication (MacCAT-CA) is the standard benchmark for understanding and reasoning. The Interview Instructions for Competency (IIC) helps establish what the person was actually told and whether they processed it. These get supplemented by record review—psychiatric history, prior evaluations, medications, substance use patterns—and collateral information whenever it's available. The NECKO and GVFRS come up occasionally in some jurisdictions, but they're not universally adopted. Different states have different statutory definitions of competency, which creates real problems when a defendant is being transferred across lines.Common Pitfall: A lot of evaluators focus too heavily on the defendant's ability to recite facts and not enough on reasoning under stress. I've watched people nail every factual question during a calm interview and then completely fall apart when asked to weigh the pros and cons of accepting a plea deal versus going to trial. The reasoning component is where a lot of apparently competent defendants fail, and it's also where laypeople and some clinicians tend to underweight its importance.
How I Actually Run Through an Evaluation
Here's the practical breakdown of how this typically goes. First session, I'm establishing rapport and gauging basic orientation while also observing how the person handles ambiguity. Second session covers the structured instruments—MacCAT-CA, IIC, clinical interviews around the specific charges. Third session, if needed, is focused on areas that came up as unclear, usually reasoning about specific case-related decisions. I build in breaks because cognitive fatigue significantly affects performance, and I've seen too many evaluations go sideways because the defendant just ran out of steam. I check for malingering separately. The FEFS-2 is useful, but it's not foolproof. I look at performance validity tests embedded in cognitive batteries, review the MCMPI or PAI if they're available, and compare self-reported symptoms against documented history. If someone claims they've been hearing voices ordering them to refuse to participate but there's zero documentation of that in any hospital or correctional records, that's a red flag worth investigating. The hardest part isn't the instruments. It's the context. In competency restoration, we often see people who appear competent on testing but struggle to apply that understanding to their actual case. A defendant might correctly name all the players in the courtroom and describe what a trial involves, then tell me they want to represent themselves because they don't trust their lawyer to handle the testimony. That's not incompetence on the MacCAT-CA. It's a strategic decision or a paranoid ideation issue, and those require different interventions.A Case Where Standard Protocols Fell Apart
I worked a case a few years back involving a defendant with bipolar disorder who was cycling through a manic episode during the evaluation window. His speech was rapid, his answers were technically accurate, but his reasoning was scattered across multiple tangential threads. He could tell me the elements of the charge but couldn't explain why his alibi might not hold up. Standard testing would have produced an ambiguous result. What I ended up doing was splitting the evaluation into three shorter sessions across two weeks, coordinating with his psychiatrist to stabilize medication between appointments, and focusing the later sessions on case-specific reasoning rather than general legal knowledge. By the third session, his thought process was coherent enough to make a reliable assessment. Without that adjusted schedule, I would have had to render an uncertain opinion, which helps nobody.The Restoration Question and Its Limits
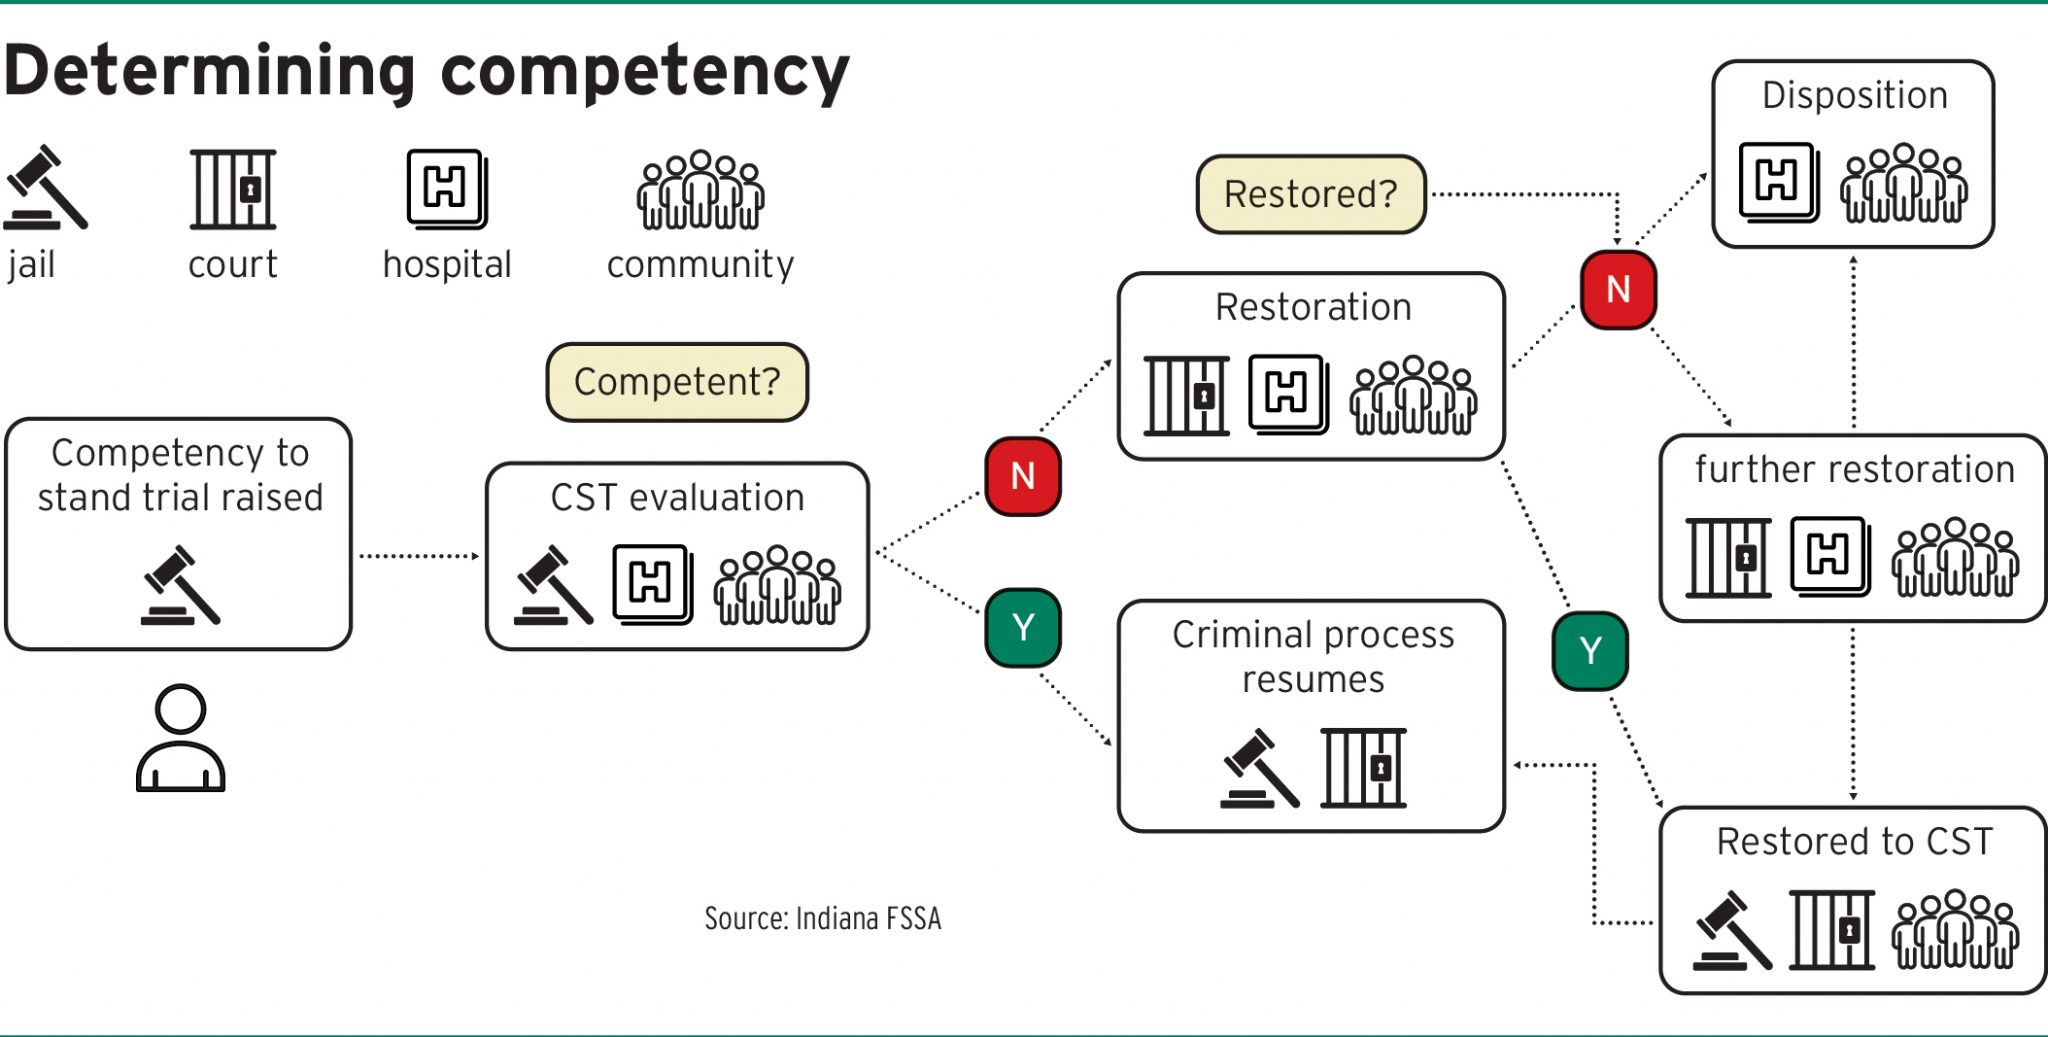
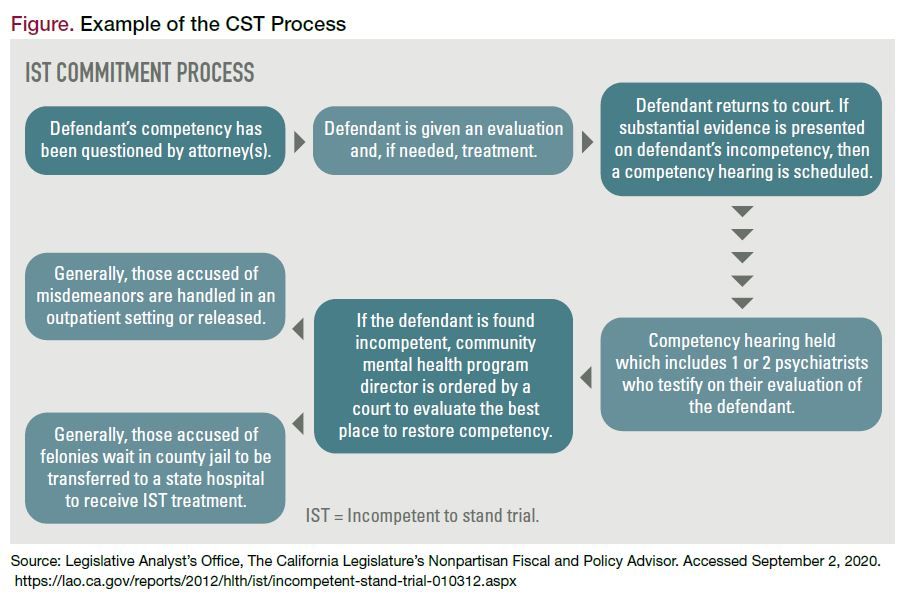
If a defendant is found incompetent, the next question is always restoration. That means providing treatment or intervention aimed at bringing the person back to competency. Most commonly this involves psychiatric treatment, medication adjustment, or competency-specific education. Theoretically straightforward. Practically, it's where a lot of systems break down. Restoration can take anywhere from a few weeks to over a year depending on the underlying condition. Psychosis-related incompetence usually responds faster to medication than intellectual disability or traumatic brain injury. But the timeline is unpredictable, and defendants can sit in commitment for extended periods while waiting for restoration to work. Courts sometimes impose due process time limits, but those vary wildly by jurisdiction. The bigger issue is that restoration doesn't guarantee the person will be capable of assisting counsel once restored. I've seen individuals who regain baseline competency but still lack the capacity to make reasoned decisions about their case because the underlying cognitive deficit persists. That's a distinction evaluators need to flag clearly in their reports.Downside most people miss: Competency evaluations are snapshot assessments. They reflect the defendant's functioning at one point in time. A person can be restored and then decompensate again if they stop taking medication or if stressors escalate. This isn't theoretical—I've had follow-up evaluations where a defendant who passed competency a month earlier failed it completely because they'd stopped their antipsychotics and was actively paranoid about their lawyer sabotaging the case.