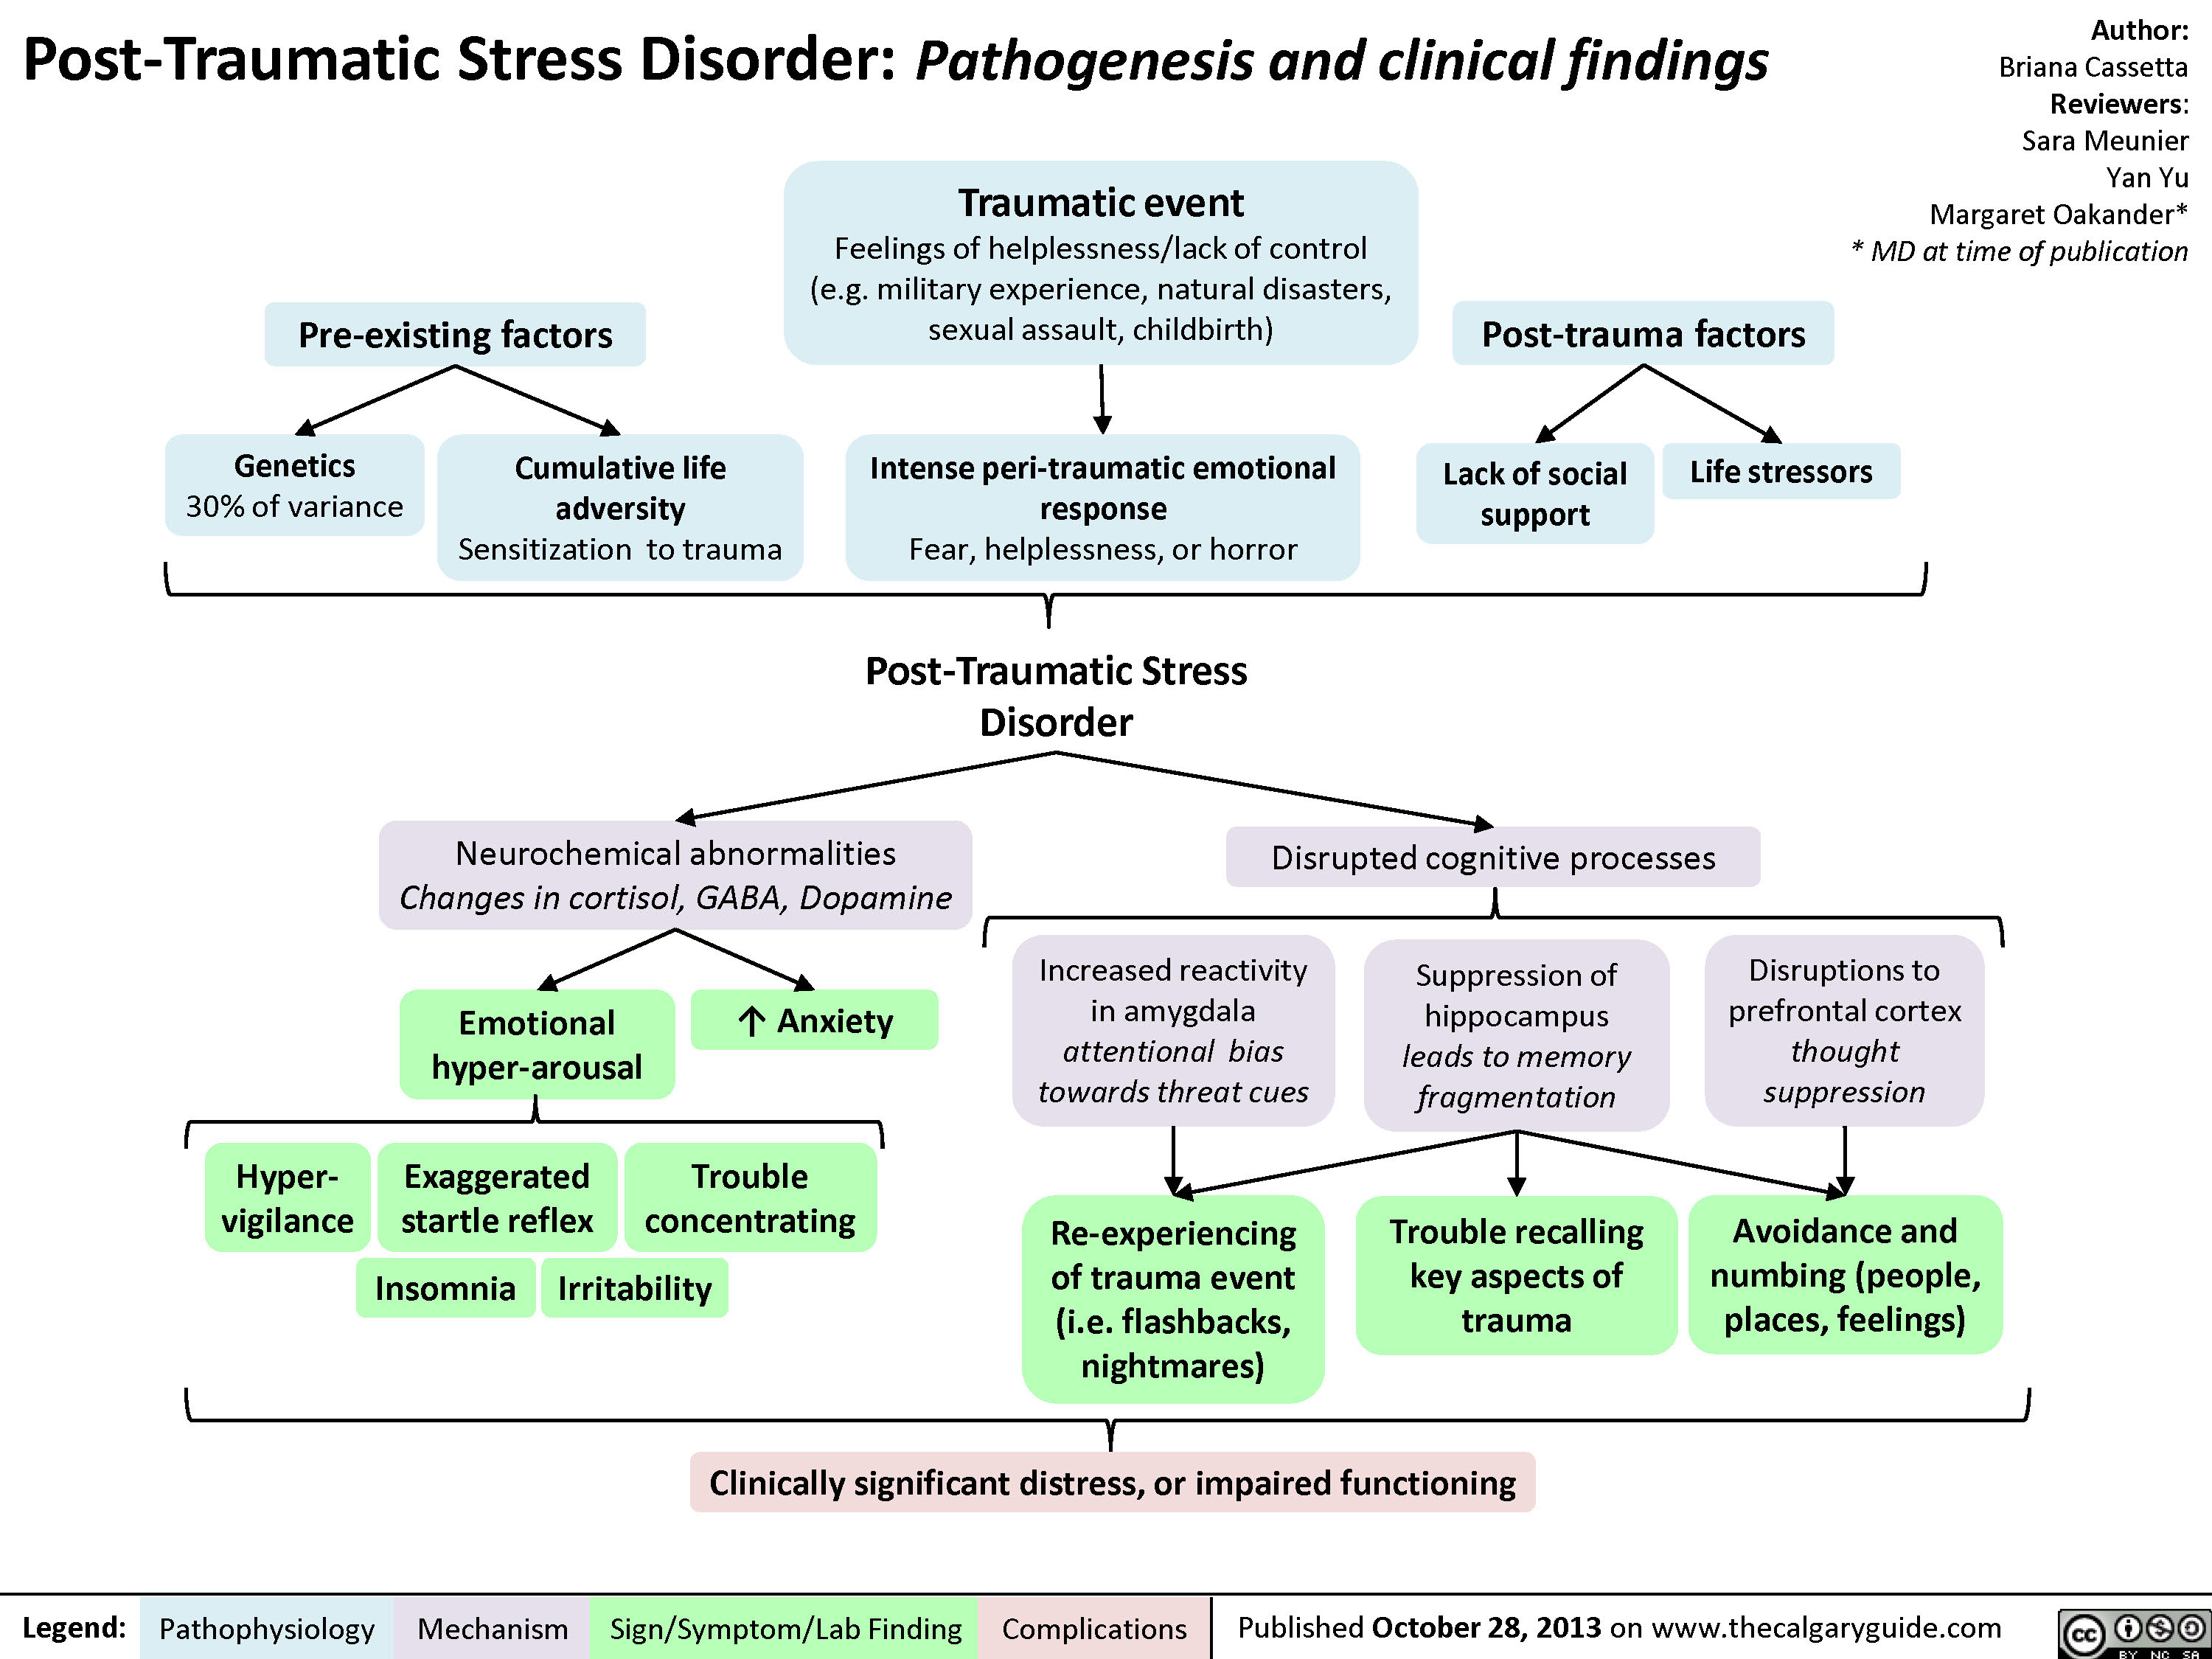
What actually happens when you treat Complex Post Traumatic Stress Disorder
Most people confuse C-PTSD with regular PTSD and approach it the same way, which is a mistake that slows recovery significantly. The disorder stems from repeated, prolonged trauma rather than a single incident. Childhood abuse, long-term domestic violence, captivity situations, and chronic neglect all fall into this category. The nervous system doesn't recover the same way because there was never a clear moment where the threat ended. I spent years watching patients stall in treatment because we pushed standard PTSD protocols on a condition that operates differently. The core issue isn't justback or avoidance. It's emotional regulation collapse, chronic shame, relational instability, and a fragmented sense of self. Those things don't resolve through exposure therapy alone.
Working with Complex Post Traumatic Stress Disorder: A practical framework
The phase-oriented model remains the most reliable structure for treatment. You spend time on stabilization first, then move into trauma processing, and finally work on integration and relational repair. The problem is that most clinicians underestimate how long the stabilization phase takes. I've seen people spend eight to fourteen months just building basic emotional regulation skills before they're ready to touch any traumatic material. Trying to rush that process usually triggers severe decompensation. Here's a specific edge case that cost me two years of trial and error. A patient I worked with had a history of prolonged childhood abuse and would dissociate mid-session the moment we approached any narrative about the trauma. Standard grounding techniques weren't enough. She'd check out completely and we'd lose the entire session. The workaround was to abandon verbal processing entirely and shift to bottom-up somatic work. We started with pendulation, which is alternating attention between a neutral body sensation and a mildly activated one, staying well below her dissociation threshold. We also used external orientation exercises—having her name objects in the room, press her feet into the floor, track her breath without trying to change it. It took about six weeks of purely regulatory work before she could tolerate even a fraction of a trauma memory without shutting down. What I learned from that was that somatic resourcing isn't just a warm-up exercise. For complex trauma, it is the primary intervention, not a precursor to the real work. EMDR is commonly used for C-PTSD but requires significant modification. Standard EMDR protocols assume the patient can tolerate distress while processing a specific memory. Complex trauma patients often can't because their nervous system lacks the developmental capacity for emotional regulation. The modified approach uses more resource development before any targeting, longer sets of bilateral stimulation, and frequent check-ins to monitor window of tolerance. Some practitioners use the phased EMDR protocol specifically designed for complex cases, which includes extended preparation and installation of positive cognition before any trauma processing begins.
Medication management is another area where expectations need calibration. SSRIs like sertraline and fluoxetine can help with co-occurring depression and anxiety, but they don't address the core features of C-PTSD. Prazosin may reduce nightmares related to trauma. Sometimes low-dose atypical antipsychotics are used short-term for severe dissociation or emotional dysregulation. No medication treats the underlying attachment wounds or the chronic shame that characterizes this condition. Medication should be viewed as a stabilizing tool, not a treatment in itself. One counter-intuitive insight that many clinicians miss is that standard CBT techniques can actually worsen C-PTSD symptoms in some cases. When you ask someone to examine and challenge their thoughts, you're engaging their prefrontal cortex, which is exactly the brain region that gets downregulated during trauma responses. For complex trauma patients, the priority is building bottom-up regulation first, then gradually introducing top-down cognitive work. Skipping that sequence is one of the most common reasons treatment fails for this population. Another overlooked nuance is the role of interpersonal neurobiology. C-PTSD develops in relational contexts, so recovery also has to happen in relational contexts. Individual therapy alone is often insufficient because the wound was relational. Group therapy, when properly structured, can provide corrective emotional experiences that one-on-one treatment cannot replicate. The group setting allows patients to test new interpersonal behaviors in real time and receive immediate feedback. Not all groups are appropriate though. Open, unstructured groups can be triggering for people with significant attachment trauma. Structured programs with clear boundaries and trained facilitators work better.
Get the Full Details

Common pitfalls in treatment The biggest mistake is treating C-PTSD like a checklist of symptoms rather than a developmental disorder. This isn't about eliminating flashbacks and calling it recovery. The work involves rebuilding a coherent sense of self, learning to tolerate intimacy, developing secure attachment patterns, and processing grief over lost childhood or stolen years. Those are fundamentally different goals than standard PTSD treatment. Another pitfall is the assumption that symptom remission equals functional recovery. A patient might no longer have panic attacks or night terrors but still struggle to hold a job, maintain relationships, or manage basic daily responsibilities. Functional recovery requires separate, targeted intervention. Skills training in emotional regulation, interpersonal effectiveness, and distress tolerance addresses areas that trauma processing alone won't touch.
Resource availability is a genuine bottleneck. Phase-oriented treatment for C-PTSD requires clinicians trained in complex trauma who understand neurobiology, attachment theory, and somatic approaches. Those clinicians are concentrated in urban areas and have long waitlists. Rural and underserved populations often have no access to this level of care. Telehealth has improved access somewhat, but the quality of virtual therapy for complex trauma remains debated, especially for patients who dissociate easily or have severe relational trauma. Self-help resources have limitations that deserve honest acknowledgment. Books like The Body Keeps the Score and Complex PTSD: From Surviving to Thriving provide useful psychoeducation and validation. They can help people understand what's happening to them and reduce shame. But they cannot replace professional treatment. Some self-help approaches recommend exposure to trauma memories without proper grounding skills, which can be harmful. The guidance here is informational, not therapeutic. If you're dealing with C-PTSD symptoms, professional evaluation is essential before attempting any structured self-treatment. The timeline for meaningful improvement is measured in years, not months. Even with consistent, high-quality treatment, most people see significant symptom reduction within 18 to 36 months. Full functional recovery often takes longer. That reality discourages some people from starting treatment, but it also means the expectation should be realistic from the beginning. Setting a goal of complete elimination of all symptoms is usually counterproductive. A more achievable framework focuses on building capacity—capacity for emotional regulation, capacity for connection, capacity for tolerance of distress without dissociation or self-harm.
For those seeking clinical support, the International Society for the Study of Trauma and Dissociation maintains a provider directory at isstd.org, and the National Child Traumatic Stress Network has a resource center at nctsn.org. These directories help locate clinicians with specific training in complex trauma. Insurance coverage varies widely, and many therapists who specialize in this area operate on a cash basis, so financial planning is a practical consideration before starting treatment. The most important factor in outcomes appears to be the therapeutic alliance. Research consistently shows that the quality of the relationship between therapist and client is one of the strongest predictors of treatment success across all modalities. For C-PTSD patients, who often have deep mistrust of authority figures and caregivers, finding a therapist who feels safe and consistent is not a secondary concern. It is the foundation upon which everything else is built. If a particular therapeutic approach isn't working, switching modalities is reasonable. If the relationship feels unsafe or invalidating, switching clinicians is often the more critical move.