
What Complex PTSD Actually Looks Like in Assessment
Standard PTSD criteria were built around single-incident trauma — a car crash, an assault, a natural disaster. Complex PTSD shows up differently. It comes from prolonged, inescapable trauma where escape isn't an option. Childhood abuse, captivity situations, domestic violence over years, organized abuse. The symptom profile expands beyond flashbacks and avoidance into emotional dysregulation, negative self-concept, and interpersonal difficulties. That's why generic screening tools miss a significant portion of cases. I've worked with assessment workflows long enough to know the gap between what a standard PCL-5 returns and what the full clinical picture looks like. The tool most people end up relying on when they need something that actually covers the CPTSD spectrum is a combination approach — not a single questionnaire. Below I'll walk through the practical setup, what instruments to use, how to score them, and where people routinely go wrong.
Choosing the Right Complex Ptsd Assessment Tool
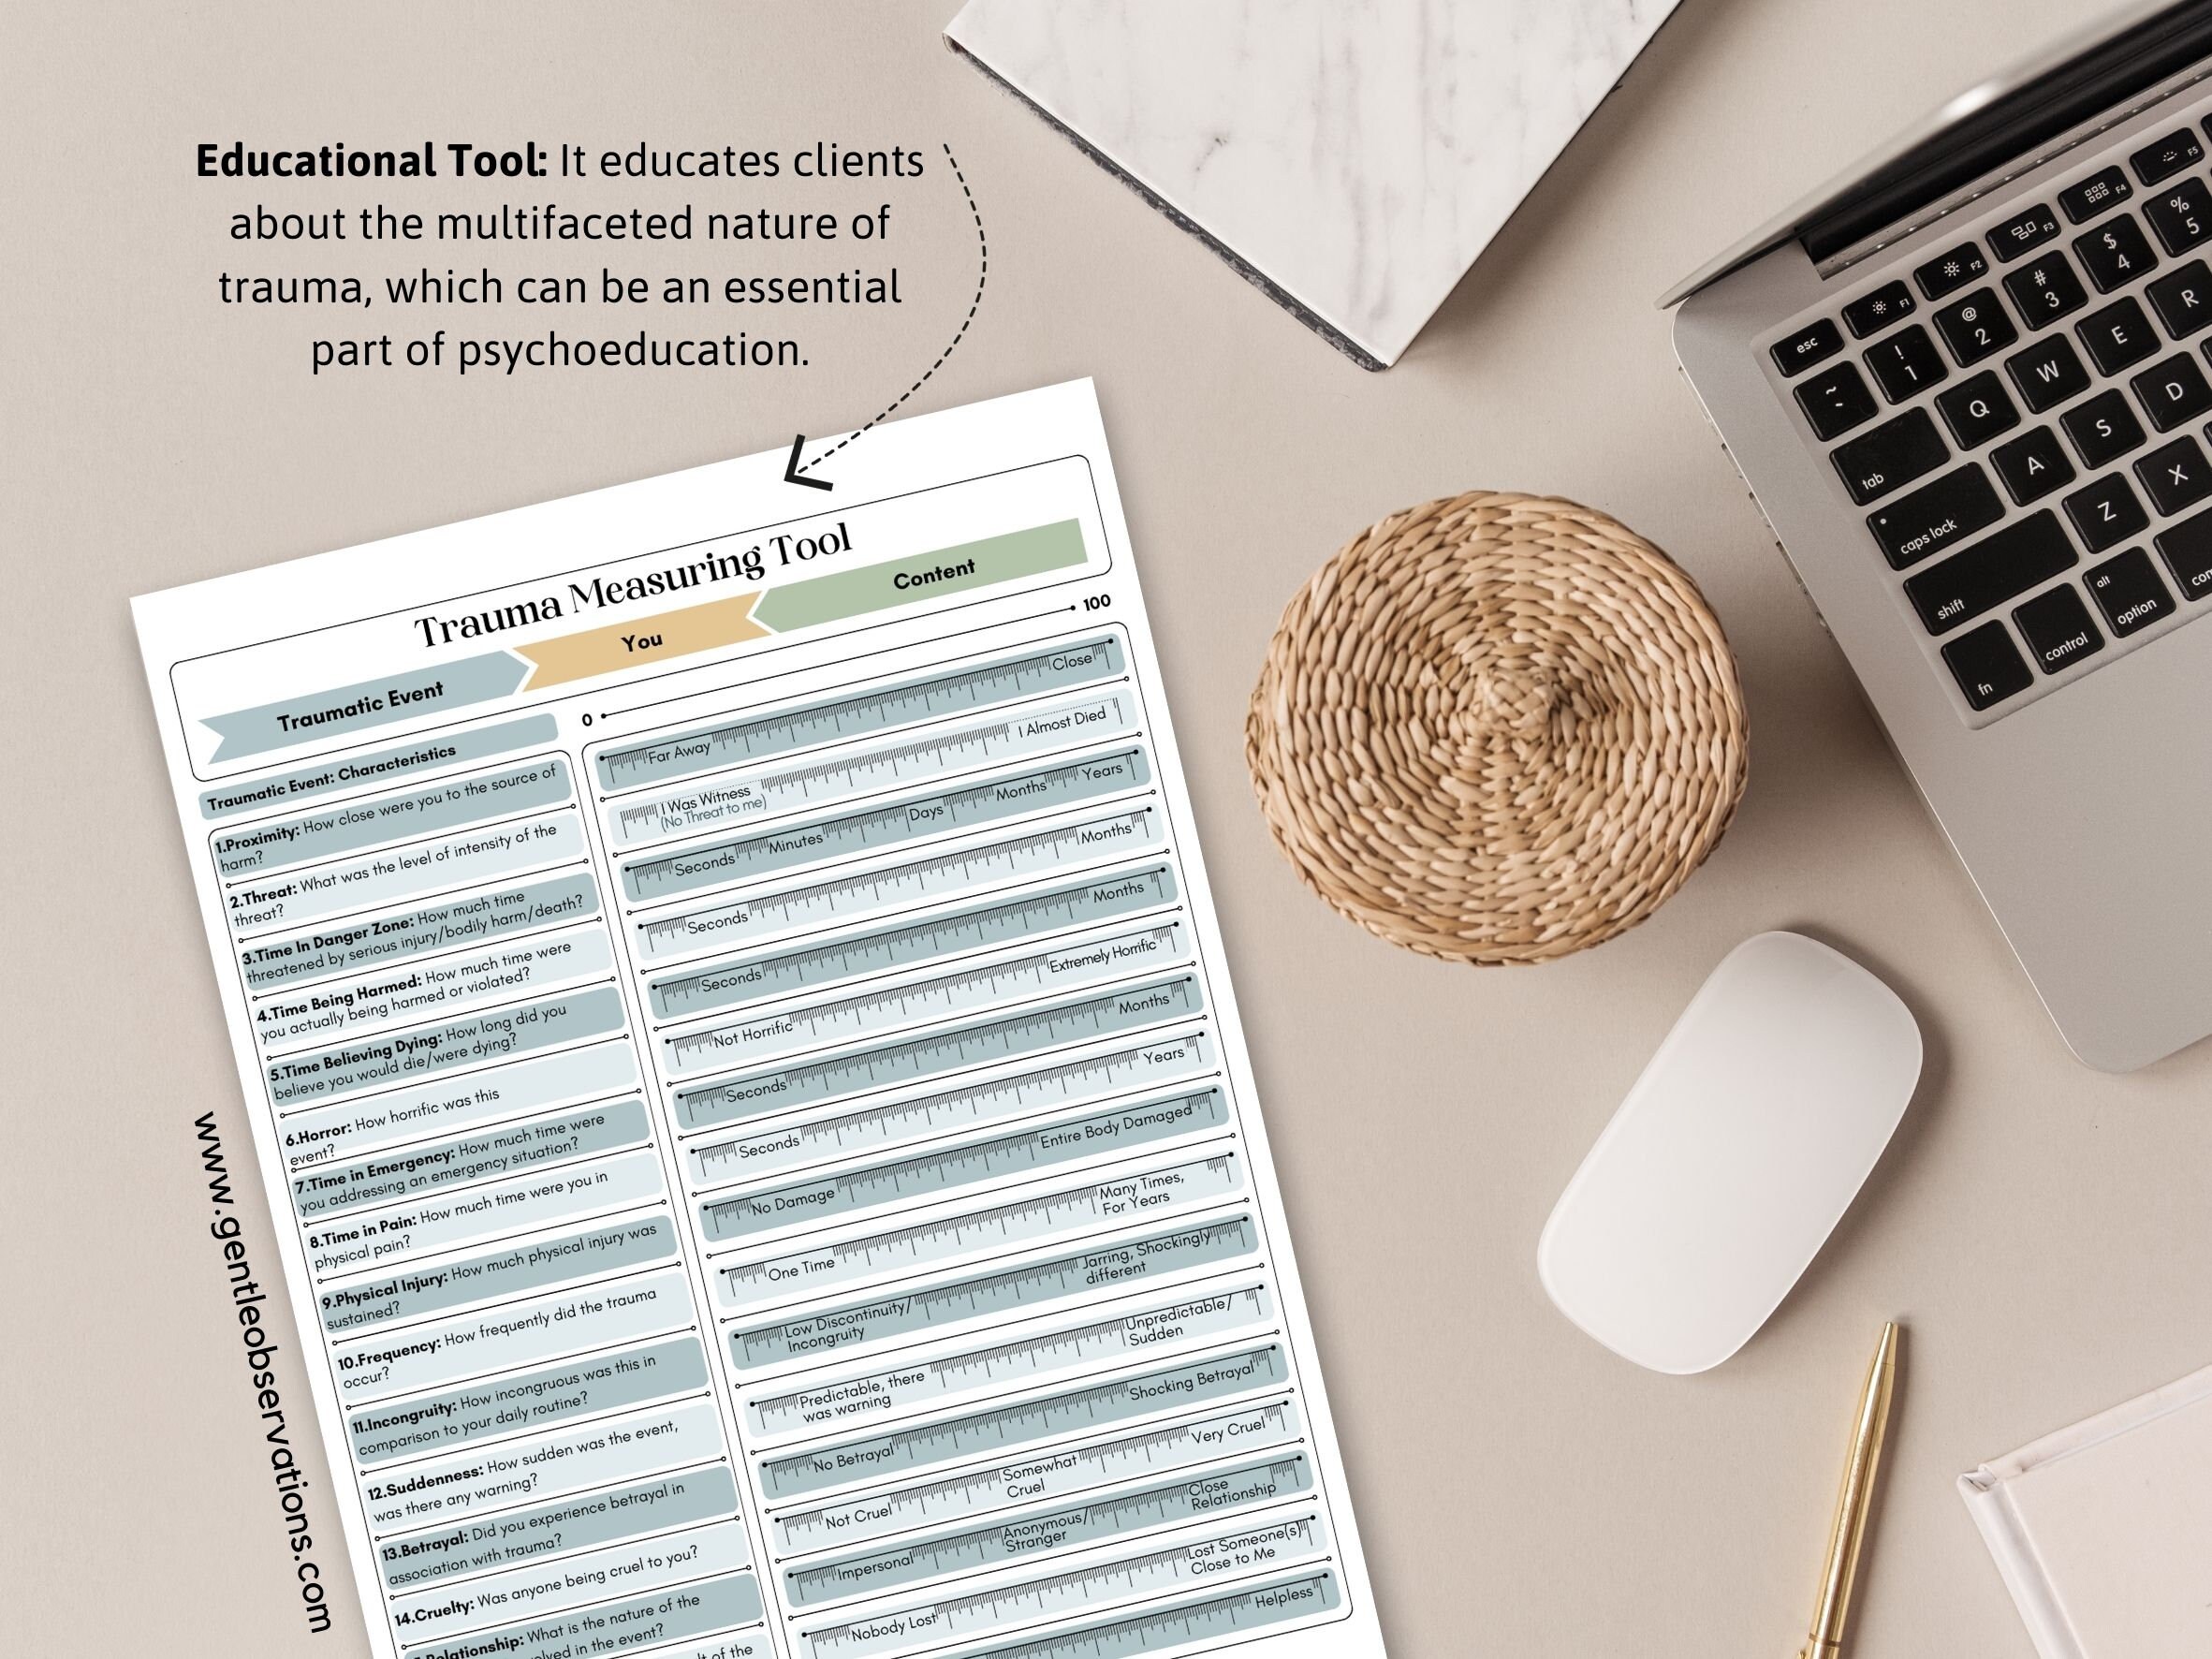
There isn't one universally accepted single instrument. The field converged on a small stack that, used together, covers the ICD-11 CPTSD specification well enough for most clinical and research settings. Here's the core set: 1. ISO-SCID (International Trauma Questionnaire – Structured Clinical Interview for DSM-5 and ICD-11) — The gold-standard structured interview for CPTSD per ICD-11. Takes about 20-30 minutes. Covers the six core symptoms: re-experiencing, avoidance, negative self-concept, emotional dysregulation, interpersonal difficulties, and disturbance in relationships. 2. ITQ (International Trauma Questionnaire) — The self-report version. 27 items. Screens for both PTSD and CPTSD in roughly 10 minutes. Good for initial triage and repeated monitoring. Validated across multiple languages and trauma populations.
3. PCL-5 (PTSD Checklist for DSM-5) — Still useful as a complement. Captures the intrusion/avoidance/arousal domain well. Doesn't cover the CPTSD extensions on its own, so it needs the ITQ alongside it. 4. DES-II (Dissociative Experiences Scale) — Complex trauma almost always involves some degree of dissociation. The DES-II flags this. About 15 minutes. Essential if you're seeing treatment-resistant cases or people who describe "losing time."
Get the Full Details

How to Set Up the Assessment Workflow
Here's the sequence that actually works in practice. Don't skip steps — the order matters for accuracy. Step 1: Self-report screening (10-15 min) Start with the ITQ. If the scores land in the probable PTSD range but below CPTSD, you still flag for follow-up. If they hit the CPTSD threshold on all three clusters (re-experiencing + avoidance AND negative self-concept + emotional dysregulation + interpersonal difficulties), you move to Step 2. I typically have clients complete the ITQ before their first session and review it during intake. This saves time and gives you a starting hypothesis.
Step 2: Structured clinical interview (20-30 min) The ISO-SCID is where you verify the screening results and resolve ambiguity. Self-report tools have a false-positive rate around 15-20% for CPTSD specifically. The structured interview brings that down significantly. Key tip: ask about the timeline carefully. ICD-11 requires that the trauma exposure lasted months to years, or was of a kind from which escape was difficult or impossible. A single prolonged event (like a year-long kidnapping) counts. Multiple discrete events (like annual natural disasters) do not. This distinction trips up even experienced clinicians. Step 3: Differential diagnosis pass (10-15 min)
Complex PTSD shares significant overlap with borderline personality disorder, bipolar disorder, and ADHD. The ISD-SCID includes differential diagnosis guidance, but you need to actively check for each. A quick rule I use: BPD typically shows identity disturbance and anger dysregulation without the prominent re-experiencing/avoidance cluster. Bipolar has distinct episodic mood shifts. ADHD shows chronic attention issues from childhood regardless of trauma timing. If the trauma timeline and symptom pattern don't fit neatly, refer for a full diagnostic evaluation. Step 4: Dissociation and comorbidity screening (10 min) Run the DES-II and a brief substance use screen (AUDIT-C is fine). About 40% of CPTSD cases have a co-occurring substance use disorder, and dissociation severity correlates with treatment resistance. I've seen cases where the dissociation was so severe that standard exposure-based protocols failed until it was addressed first. This isn't a minor detail — it changes the treatment plan.
Scoring and Interpretation
The ITQ uses a 5-point Likert scale (0-4). The scoring algorithm requires: This pattern gives you a probable CPTSD diagnosis per ICD-11 criteria. The cutoff is conservative by design — it prioritizes specificity over sensitivity. You'll miss some mild cases, but you won't over-diagnose. For clinical decision-making, that tradeoff is usually the right one. The PCL-5 scores 0-80 across 20 items. A cutoff of 31-33 is commonly used for probable PTSD. But again, this alone doesn't capture CPTSD. I keep both numbers on the same page during review. When the PCL-5 is elevated but the ITQ doesn't meet CPTSD thresholds, I look more carefully at the trauma history. Sometimes the person had a single severe event rather than prolonged trauma — that's PTSD, not CPTSD, and the treatment implications differ.
Common Pitfalls I've Seen
Pitfall 1: Using only the PCL-5 or CRIES-8 These tools screen for PTSD. They will miss CPTSD entirely because they don't measure negative self-concept, emotional dysregulation, or interpersonal difficulties. If you're only using a standard PTSD checklist, you're not assessing complex trauma. Period. Pitfall 2: Not establishing the trauma timeline
ICD-11 CPTSD requires prolonged or repeated trauma. A person who survived a single violent robbery has PTSD, not CPTSD. A person who endured 15 years of childhood abuse has CPTSD. The distinction matters for treatment planning. I once had a case where the client described severe symptoms that looked like CPTSD on the ITQ, but the structured interview revealed a single 6-month captivity event. That's a borderline case — prolonged, but not "prolonged and repeated" in the way the criteria intend. We flagged it as PTSD with severe features instead. The treatment path was different. Pitfall 3: Skipping the dissociation screen This one costs people sessions. I had a client who went through three months of standard PTSD protocols with zero improvement. The DES-II came back at 28 (high dissociation). Once we adjusted the treatment to address dissociation first — grounding techniques, phase-oriented approach — progress became visible within weeks. The dissociation wasn't a side note. It was the barrier.

Where These Tools Fall Short
No self-report or structured interview is perfect. The ITQ has known limitations: it's relatively new (published 2017), so longitudinal data is still accumulating. Cultural validity varies — the emotional dysregulation and interpersonal difficulty items don't translate cleanly across all cultures. A person from a collectivist background might score low on interpersonal difficulties simply because they don't interpret social strain the same way a Western clinician expects. The ISO-SCID requires trained administrators. It's not something you can comfortably self-administer or hand to an untrained colleague. Factor in the training time and you're looking at several hours of preparation before you can reliably use it. If you need a lighter-weight alternative for settings where the ITQ/ISO-SCID aren't feasible, the CTQ-SF (Childhood Trauma Questionnaire – Short Form) is a reasonable proxy for identifying the trauma history that precedes CPTSD. It doesn't diagnose CPTSD itself, but it tells you whether the exposure history fits. Pair it with the PCL-5 and you've got something workable in about 20 minutes total.
Downloading Assessment Instruments
Most of these tools are freely available for clinical and research use. The ITQ and ISO-SCID are maintained by the WHO and can be downloaded directly from the International Trauma Questionnaire website. The PCL-5 is publicly available through the National Center for PTSD (ptsd.va.gov). The DES-II requires a license but is affordable for individual practitioners. The CTQ-SF is also freely available from its developers at Boston University. I don't recommend scanning PDFs from unofficial sources. Scored protocols and manuals from legitimate sites ensure you're using the current version with proper scoring algorithms. Several older versions of the ITQ had scoring errors that inflated CPTSD prevalence estimates. It's a small thing, but it matters when you're making clinical decisions based on the output.
Practical Takeaways
Use the ITQ as your primary screen. Follow positive screens with the ISO-SCID. Always include a dissociation measure. Don't rely on PTSD-only checklists. Establish the trauma timeline carefully. And when the tools give you an ambiguous result, that's usually a signal to slow down and gather more clinical information rather than force a label. Complex PTSD assessment isn't about finding the right tool. It's about using the right combination of tools in the right order, then interpreting the results within the full clinical context. The instruments tell you where to look. They don't tell the whole story.


