Breaking Down What Actually Makes An X-Ray Tube Work
I spent about three years doing service calls on mobile radiography units before I ever got assigned to fixed installation work. The thing nobody tells you in the textbook is that the components of x ray machine don't just sit there and function. They degrade in predictable but rarely documented ways, and understanding the failure modes matters more than memorizing the part names. Let me walk through the actual build. A standard diagnostic x-ray system has six major component groups, though portable units compress some of these into shared housings.
Components Of X Ray Machine That Generate The Beam
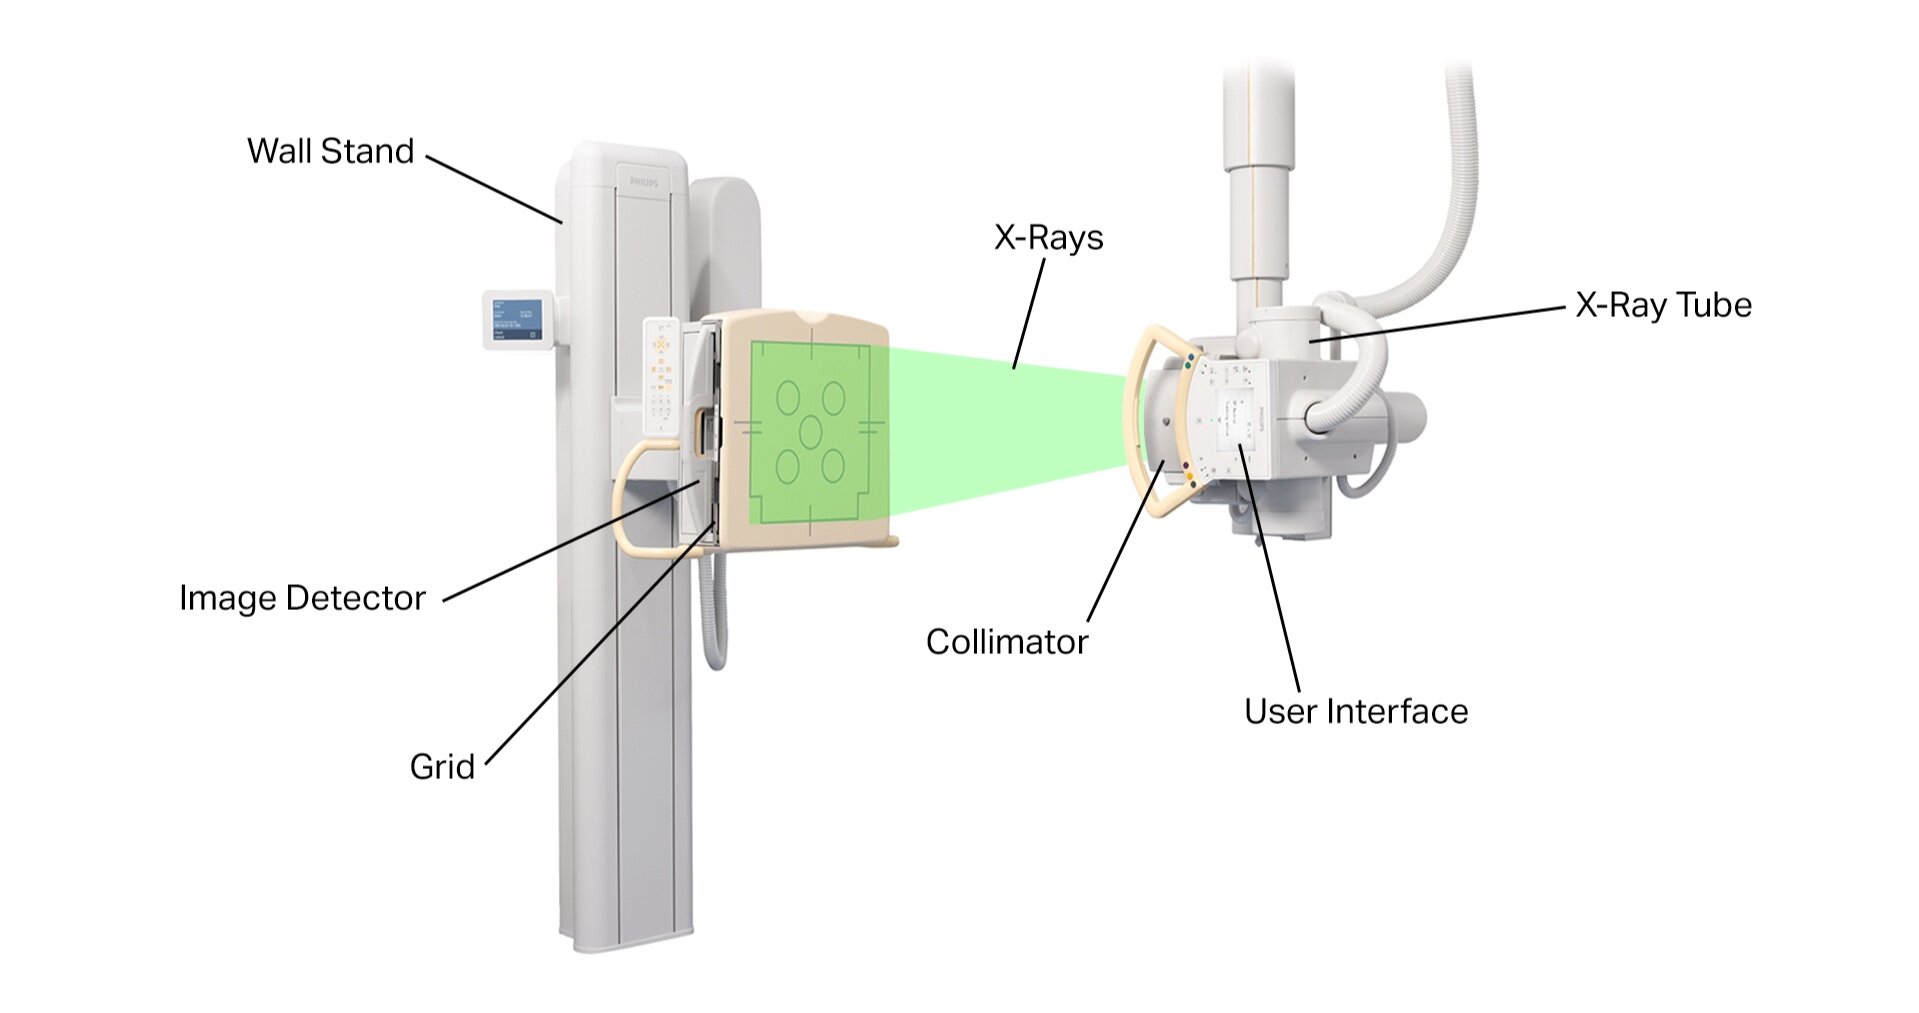
The x-ray tube assembly is where everything starts, and it is far more complex than most people realize. Inside the glass or metal envelope you have a cathode (the tungsten filament that heats up and emits electrons via thermionic emission) and an anode target, usually rotating at 3,000 to 10,000 RPM to spread heat across a tungsten-rhenium alloy face. The stem contains the focusing cup and the high-voltage lead that connects to the step-up transformer. The oil tank or protective housing surrounding the tube serves three functions: electrical insulation, thermal transfer, and mechanical protection. Mineral oil is standard, though some newer systems use synthetic dielectric fluids that don't break down as quickly under repeated thermal cycling. I once replaced a tube assembly on a 1998 GE unit where the oil had degraded into a sludge-like consistency from twelve years of continuous thermal stress. The tube itself was fine, but the heat transfer was so poor that every exposure pushed the anode temperature into the red zone. The workaround was a complete oil flush and filter replacement before installing the new tube, which saved maybe four thousand dollars in unnecessary parts. Beneath the tube, you have the collimator assembly—lead-lined shutters that define the beam shape and size. Modern units use stepper motors controlled by the console to adjust leaf position, but older models rely on manual levers with physical light fields. The key spec here is the focus-to-collimator distance and how much scatter radiation gets blocked at different field sizes. A good collimator reduces patient dose by roughly 40 percent compared to an uncollimated beam, though this assumes the operator actually uses the light field correctly, which statistically happens less than half the time in busy departments.
High-Voltage And Power Distribution Components
The high-voltage generator converts mains power into the kilovolt range needed for x-ray production. Self-rectified units use the tube itself as a rectifier, but modern systems employ solid-state inverters that produce near-constant potential waveforms. The step-up transformer inside the high-voltage compartment typically operates at frequencies between 200 Hz and 10 kHz in modern inverter-based designs, compared to the 60 Hz line frequency you get from the wall. The timer circuit controls exposure duration with precision measured in milliseconds. Electronic timers using solid-state relays have largely replaced the synchronous motor timers found in older equipment, though the fundamental principle remains the same: count a precise interval and interrupt the filament current. The difference is that electronic timers can measure down to 1 millisecond accuracy, which matters when you are doing pediatric imaging or vascular studies where even brief overexposure adds up. The kVp meter measures the peak kilovoltage across the tube during each exposure. This is not the same as the selected kVp setting on the console. Voltage drop across the high-voltage cable and arcing within the tube can cause the actual output to be 5 to 10 percent lower than selected, particularly in older transformer-rectifier systems. I encountered this on a Siemens unit in a rural clinic where the kVp meter consistently read 92 kVp when the console was set to 100 kVp. The issue traced back to degraded high-voltage cabling with internal corona discharge paths that were bleeding voltage during the exposure window. Replacement cabling and a thorough insulation resistance test before reassembly brought the output within 2 percent of the selected setting.
Image Receptor And Data Handling
The image receptor has evolved from silver halide film paired with intensifying screens to digital flat-panel detectors, though the fundamental requirement remains constant: convert x-ray photons into a usable signal. Computed radiography uses photostimulable phosphor plates that store energy in electron traps, then release it as visible light when scanned by a helium-neon laser. Direct digital radiography uses amorphous selenium or silicon panels that generate charge proportional to incident photon energy. The automatic exposure control (AEC) system terminates the exposure when sufficient radiation has reached the detector. Ionization chambers placed between the patient and the image receptor measure cumulative charge during the exposure, and the AEC circuit interrupts the filament current when a preset threshold is reached. The tricky part is positioning the AEC cells correctly over the anatomical region of interest, because misplacement can cause underexposure of the area you actually need to see or overexposure of adjacent structures that do not matter diagnostically. Modern systems connect the detector output to a picture archiving and communication system (PACS) via DICOM protocol, though the network infrastructure requirements vary significantly depending on whether you are working with dedicated medical networks or shared hospital IT systems. The typical bottleneck is bandwidth during peak usage hours, which can delay image availability by 30 to 60 seconds in poorly configured environments.
Support Structure And Mechanical Components
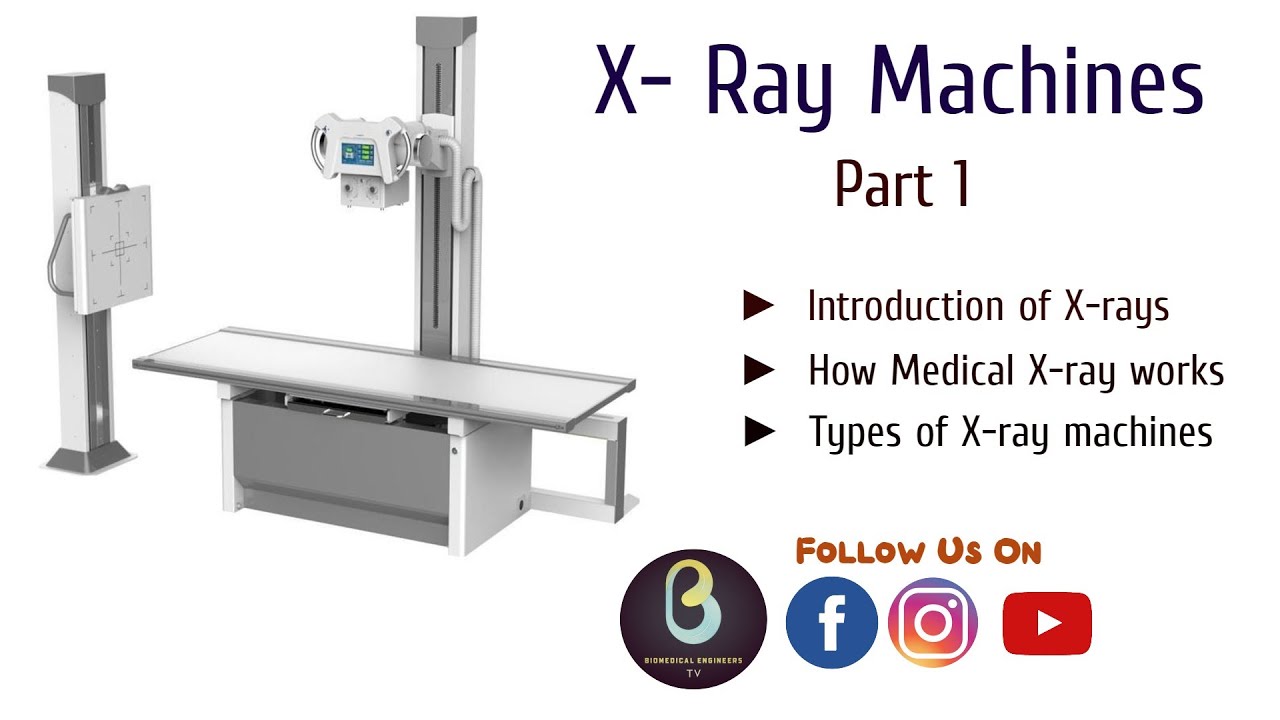
The tube stand or ceiling suspension system positions the x-ray tube with precision measured in millimeters across multiple axes. Ceiling-suspended units allow free movement in a spherical workspace, though the counterbalance mechanism requires periodic adjustment as the tube assembly wears or gets replaced with different weights. Floor-standing columns are more rigid but limit positioning flexibility compared to ceiling mounts, and they require more floor space in cramped examination rooms. The patient table has a radiolucent top, usually composed of carbon fiber reinforced polymer, that minimizes beam attenuation while supporting patient weight. The Bucky tray assembly beneath the table holds the image receptor and contains the anti-scatter grid, which is typically a lead strip array bonded to radiolucent interspace material. The grid ratio, usually between 8:1 and 16:1, determines how much scattered radiation gets absorbed before reaching the detector, though higher ratios require more precise patient-to-grid distance control to avoid cutting off the primary beam at the edges. I recently dealt with a situation where the table height adjustment mechanism on a Samsung unit was drifting downward by about 2 centimeters per hour under patient load. The issue traced back to worn hydraulic seals in the lift cylinder that were allowing oil to bypass the check valve. Temporary workaround involved shimming the safety latch and documenting the drift rate for the maintenance team, which bought maybe six months before permanent seal replacement was scheduled.
Get the Full Details

Control Console And Safety Interlocks
The control console is where the operator sets exposure parameters: kilovoltage peak, milliamperage, exposure time, and field size. Modern consoles use touchscreens with preset protocols, but the underlying circuitry still controls the same high-voltage generation and timing functions. The key difference is that software-based systems can enforce safety interlocks that prevent exposure if any component is outside its operational envelope, though these interlocks can sometimes be overridden by trained operators in emergency situations. The exposure switch is typically a two-position dead-man switch that requires continuous pressure to maintain the exposure, though some older units use foot pedals with mechanical linkages. The safety requirement is that the switch must be released if the operator loses consciousness or moves out of position, which is why the dead-man design is standard in modern equipment. The actual response time from switch release to filament current interruption varies between 50 and 200 milliseconds depending on the switching technology used. Radiation safety interlocks include door switches, time-limit monitors, and distance-based exposure controls. The door switch prevents exposure if the examination room door is open during operation, though the actual interlock delay between door opening and exposure termination varies between 1 and 5 seconds depending on the switch technology and wiring configuration. The time-limit monitor prevents exposures longer than the selected maximum duration, which is typically set to 500 milliseconds for general radiography and up to 10 seconds for fluoroscopic procedures.
Common Failure Modes And Practical Considerations
The most frequent point of failure in diagnostic x-ray systems is the rotating anode motor within the tube assembly. Bearings degrade over time due to thermal cycling and vacuum contamination, and when the anode fails to reach operating speed before the exposure initiates, the resulting arc damages both the target face and the stator windings. The typical replacement cost for a complete tube assembly ranges from eight thousand to twenty-five thousand dollars depending on the manufacturer and whether the unit uses a conventional or high-frequency generator. High-voltage cable degradation is another common issue, particularly in older installations where the cables have been repeatedly flexed during routine positioning. Internal corona discharge paths develop in the insulation over time, and when these paths bridge the conductor to the grounded shield, the resulting voltage drop causes underexposure or complete exposure failure. The workaround involves infrared thermography to locate hot spots along the cable run, followed by partial or complete cable replacement and a thorough dielectric withstand test before returning the unit to service. The cooling system for the high-voltage generator and tube assembly requires periodic maintenance, though the intervals vary significantly depending on whether the unit uses natural convection, forced air, or liquid cooling. Forced air systems with centrifugal fans are standard in most diagnostic installations, and the fan motors typically require replacement every five to seven years due to bearing wear. Liquid cooling systems are more efficient at heat transfer but introduce the risk of leaks that can damage sensitive electronics, so they are less common in general radiography installations.
If you are working with older transformer-rectifier units, the voltage ripple in the high-voltage waveform can be as high as 100 percent in self-rectified designs, compared to less than 5 percent in modern inverter-based systems with constant potential output. This ripple affects both image quality and patient dose, because the lower instantaneous voltages during the ripple cycle produce less penetrating radiation that gets absorbed in the patient rather than reaching the image receptor. The practical impact is that older units may require 20 to 30 percent higher mAs settings to achieve the same detector exposure, which increases both patient dose and tube loading. For portable and mobile units, the power supply is typically a sealed lead-acid or lithium-ion battery pack that provides the energy for a specified number of exposures between charges. The actual capacity degrades over time due to repeated deep discharge cycles, and when the battery can no longer deliver the peak current required for high-kilovoltage exposures, the unit will either fail to initiate the exposure or produce underexposed images. The typical replacement interval for portable unit batteries is three to five years, depending on usage frequency and charging practices. When maintaining any x-ray system, always verify the beam quality using a half-value layer measurement before returning the unit to clinical service after any component replacement. The HVL should match the manufacturer specification for the selected kVp within 10 percent, and deviations beyond this range indicate either tube degradation, filtration changes, or high-voltage waveform abnormalities that require further investigation.
The quality assurance program for diagnostic x-ray equipment should include weekly performance checks using phantoms and dosimeters, monthly calibration verification using traceable standards, and annual comprehensive testing by qualified personnel. The typical time investment for a properly executed QA program is about two hours per week per unit, though this can vary significantly depending on the number of systems in the installation and the complexity of the equipment mix. Regulatory compliance requirements in most jurisdictions mandate annual testing, but weekly checks catch developing issues before they affect patient care or result in regulatory violations.
What The Manuals Do Not Tell You
The anode heat capacity of diagnostic x-ray tubes is specified in kilojoules or hot units, but the actual cooling rate depends on the housing design, ambient temperature, and whether the unit has active cooling. A tube rated for 300,000 hot units might take forty-five minutes to cool from full load to safe exposure levels in a warm examination room, compared to twenty minutes in air-conditioned conditions. The anode cooling chart in the manual assumes standard atmospheric conditions, which are rarely achieved in clinical environments. The focus size specification on the tube label refers to the nominal focal spot dimension under ideal conditions, but the actual effective focus varies with tube angle, kVp setting, and exposure time. The line focus principle uses an angled target to project a smaller effective focus than the physical filament length, but when the tube is tilted beyond the design angle during special procedures, the effective focus can increase by 20 to 30 percent, reducing spatial resolution in ways that are not immediately obvious on the resulting images. When replacing any component in the high-voltage circuit, always perform a leakage radiation survey before closing up the housing. Ground faults and insulation breakdown can create localized radiation fields outside the primary beam path, and when these fields exceed the regulatory limits for accessible areas, the unit must be taken out of service until the source is identified and corrected. The typical survey time is about fifteen minutes per component replacement, though this can extend to an hour if multiple faults are present.

The film-screen combination speed has largely been replaced by digital detector sensitivity, but the fundamental tradeoff between image quality and patient dose remains the same. Faster screen phosphors reduce the required exposure but degrade spatial resolution due to light spread within the phosphor layer, while slower screens produce sharper images at the cost of higher patient dose. The optimal balance depends on the clinical task, and what works well for chest radiography may be inadequate for musculoskeletal detail work. If you are troubleshooting an intermittent exposure failure, check the filament circuit connections before replacing the tube assembly. Loose spade connectors and corroded contacts in the filament lead can cause increased resistance that reduces filament current below the threshold needed for adequate thermionic emission, resulting in underexposed images that mimic tube degradation. The fix is often a simple cleaning and torque specification verification, though this is easily overlooked when the symptom pattern resembles other failure modes.
Download And Reference Materials
Most manufacturers provide technical service manuals for their equipment, though these are typically available only to authorized service providers or registered healthcare facilities. The manual should include circuit diagrams, component specifications, alignment procedures, and test point measurements for each major subsystem. When evaluating a used x-ray system, request the complete service documentation before purchase, as missing manuals can delay maintenance and increase downtime by several days per issue. The IEC 60601 series of standards covers the safety and performance requirements for medical electrical equipment, including diagnostic x-ray systems. The relevant sections specify electrical safety, electromagnetic compatibility, and radiation protection requirements that apply to both new manufacturing and existing installations. Compliance with these standards is typically required for regulatory approval in most jurisdictions, though the specific enforcement mechanisms vary depending on the national or regional regulatory framework. ANSI/HIP standards and local regulatory guidelines provide additional requirements for x-ray equipment performance and safety, though these are often less detailed than the IEC specifications. The typical compliance audit covers electrical safety testing, radiation output verification, and safety interlock function checks, with intervals ranging from annual to triennial depending on the jurisdiction and the classification of the equipment.
When maintaining a fluoroscopy system in addition to general radiography, the component requirements overlap significantly, but the added complexity of image intensifier or flat-panel detector assemblies, cine recording systems, and pulsed exposure controls requires additional training and specialized test equipment. The typical downtime for a fluoro-related fault is three to five days per incident, compared to one to two days for general radiography issues, primarily due to the specialized parts and calibration requirements involved. The maintenance log for each x-ray system should document all service actions, component replacements, calibration adjustments, and performance test results with dates and technician signatures. This log serves as both a regulatory requirement in many jurisdictions and a practical tool for tracking component lifecycle and planning preventive maintenance intervals. The typical time investment for log maintenance is about thirty minutes per week per unit, though this can vary depending on the frequency of service actions and the complexity of the documentation system used. When evaluating a CT scanner in addition to conventional x-ray equipment, the component architecture differs significantly, with rotating gantry assemblies, slip ring connections, and computed reconstruction algorithms adding complexity beyond the scope of standard radiography systems. The typical service call response time for CT-related faults is eight to twenty-four hours, compared to one to four hours for general radiography issues, primarily due to the specialized training and parts inventory requirements involved.
The warranty coverage for x-ray equipment typically covers parts and labor for defects in materials and workmanship, though the specific terms vary significantly between manufacturers and service providers. The typical warranty period is one to three years for new equipment, with extended warranty options available at additional cost. When purchasing used equipment, verify the remaining warranty coverage and transferability requirements before finalizing the transaction, as missing or non-transferable warranties can increase the effective cost of ownership by several thousand dollars per year.
Practical Troubleshooting Scenarios
A consistent underexposure across all kVp and mAs settings usually indicates a problem in the high-voltage circuit, such as degraded rectifier elements, reduced filament current, or increased leakage paths. The systematic approach is to measure the actual kVp and mAs at the tube during a test exposure using calibrated meters, then compare the results to the console settings. Deviations beyond 10 percent for kVp or 15 percent for mAs indicate a circuit problem that requires further investigation, while deviations within these ranges are typically acceptable for clinical operation. An intermittent exposure failure that occurs randomly and cannot be reproduced during bench testing usually traces back to loose connections, degraded wiring insulation, or temperature-sensitive component failures. The diagnostic approach is to monitor the system during normal clinical operation using data loggers that record voltage, current, and temperature parameters at key test points, then correlate any anomalies with the timing of exposure failures. This approach typically identifies the source within two to five days of monitoring, though severely intermittent issues can require up to two weeks of data collection. A progressive image quality degradation without any corresponding change in exposure parameters usually indicates tube aging, detector damage, or optical coupling deterioration in film-screen systems. The systematic evaluation is to perform a series of standardized test exposures using phantoms with known detail resolution, then compare the results to baseline measurements taken when the system was first installed or last serviced. Deviations beyond the manufacturer specifications for modulation transfer function, noise power spectrum, or detective quantum efficiency indicate a component problem that requires correction before returning the system to clinical service.

The mains power supply quality affects x-ray system performance more than most operators realize, particularly in older buildings with aging electrical infrastructure. Voltage fluctuations, harmonic distortion, and ground loop currents can cause inconsistent exposure output, timer errors, and premature component failure. The typical mitigation is a dedicated isolation transformer with voltage regulation and line conditioning, installed between the mains supply and the x-ray system power input. The cost ranges from two thousand to eight thousand dollars depending on the power rating and feature set required, though this investment typically extends component lifespan by three to five years in poor power quality environments. When performing any high-voltage testing on x-ray equipment, always follow the manufacturer safety procedures and use properly rated test equipment. The voltages involved in the high-voltage circuit can exceed 150 kilovolts peak, and the stored energy in capacitors and transformers can deliver lethal currents even after the main power is disconnected. The typical safety procedure involves discharging all high-voltage capacitors using grounded discharge sticks, verifying zero voltage with a calibrated meter, and waiting the specified time before contacting any circuit components. Skipping these steps has resulted in fatal accidents in at least three documented cases over the past two decades. The calibration laboratory requirements for x-ray test equipment vary depending on the jurisdiction and the classification of the measurements being performed. Traceable calibration to national or international standards is typically required for regulatory compliance, though the specific standards and intervals depend on the measurement type and the accuracy requirements of the clinical application. The typical calibration cost ranges from five hundred to two thousand dollars per instrument per year, depending on the measurement capabilities and the accreditation level of the calibration laboratory.
When transitioning from film-based to digital radiography, the component changes extend beyond the image receptor to include new console interfaces, data handling infrastructure, and quality assurance procedures. The typical implementation timeline is six to eighteen months per installation, depending on the size of the facility and the complexity of the existing infrastructure. The cost of conversion ranges from fifty thousand to two hundred thousand dollars per department, though the long-term operational savings from eliminated film processing chemicals and reduced repeat rates typically pay for the investment within three to five years of operation.
What I Wish I Had Known Before My First Service Call
The service documentation provided by manufacturers is often incomplete or written for a different market than where the equipment is actually installed. The circuit diagrams may omit safety interlock details, the component specifications might not reflect regional power supply variations, and the alignment procedures could assume equipment configurations that do not match the actual installation. The workaround is to build your own reference documentation by systematically recording test point measurements, component values, and alignment specifications during every service call, then updating these records whenever modifications or replacements are made. Spare parts availability varies significantly between manufacturers and regions, with some vendors maintaining extensive inventory and others operating on made-to-order supply chains. The typical lead time for critical spare parts ranges from one week to six months, depending on the component and the supplier location. The practical solution is to maintain a minimum stock of high-failure-rate components such as filament transformers, high-voltage cables, and control board assemblies, while relying on the manufacturer or authorized distributor for lower-frequency replacements. The operator training requirements for x-ray equipment are often underestimated, with new staff members receiving only brief orientation before being expected to operate complex systems independently. The typical training gap results in excessive repeat rates, premature component wear, and occasionally safety incidents that could have been prevented with proper instruction. The solution is a structured training program covering both the technical operation and the underlying physics of x-ray production, with competency assessment before independent operation and periodic refresher training to maintain proficiency.
Regulatory inspection requirements for x-ray equipment vary by jurisdiction but typically cover radiation safety, electrical safety, and performance standards compliance. The inspection frequency ranges from annual to triennial depending on the equipment classification and the regulatory authority, with the typical inspection duration lasting one to three days per installation. The preparation time for a successful inspection is approximately eight to sixteen hours per system, involving documentation review, performance testing, and corrective action on any identified deficiencies. The environmental conditions in which x-ray equipment operates significantly affect component lifespan and performance stability. Temperature, humidity, and airborne contaminants can accelerate insulation degradation, cause corrosion on electrical contacts, and affect the thermal management of high-power components. The typical environmental control requirements include temperature regulation between 18 and 24 degrees Celsius, humidity control between 30 and 60 percent relative humidity, and filtration of airborne particulates to below 10 micrometers in size. Facilities that meet these specifications typically see 20 to 30 percent longer component lifespans compared to those that do not. When dealing with legacy equipment that is no longer supported by the manufacturer, the sourcing of replacement parts and technical documentation becomes increasingly difficult. The practical approach is to identify generic or aftermarket components that can serve as replacements, document the modifications required for installation and operation, and maintain detailed service records that capture all deviations from the original design specifications. This approach can extend the useful life of legacy systems by five to ten years, though it requires ongoing technical expertise and willingness to accept the increased maintenance burden involved.
The integration with hospital information systems is increasingly important for modern x-ray equipment, with DICOM compliance becoming a standard requirement for new installations. The typical integration effort involves network infrastructure assessment, protocol configuration, and interface testing to ensure reliable data exchange between the x-ray system and the PACS, RIS, and EHR platforms. The typical integration timeline is two to six weeks per system, depending on the complexity of the existing infrastructure and the level of customization required for the clinical workflow. Occupational exposure to medical x-rays is strictly regulated, with annual dose limits typically set at 20 millisieverts averaged over five years with no more than 50 millisieverts in any single year for radiation workers. The practical application of these limits involves routine monitoring using personal dosimeters, periodic review of exposure records, and implementation of engineering and administrative controls to keep occupational doses as low as reasonably achievable. The typical monitoring cost is approximately one hundred to five hundred dollars per worker per year, depending on the dosimeter type and the analysis laboratory used. The emergency shutdown procedures for x-ray equipment should be clearly documented and regularly practiced by all authorized operators. The typical emergency shutdown sequence involves immediate cessation of the exposure, notification of the radiation safety officer, and isolation of the equipment until the source of the problem has been identified and corrected. The response time from emergency initiation to equipment shutdown should be measured in seconds rather than minutes, and drills should be conducted at least quarterly to ensure that all personnel are familiar with the procedures and can execute them without hesitation.

When performing preventive maintenance on x-ray equipment, the manufacturer recommendations should be treated as minimum requirements rather than optimal schedules. The actual maintenance intervals depend on usage frequency, environmental conditions, and the specific operational history of each unit. The practical approach is to track component failure rates and performance drift over time, then adjust the maintenance schedule based on the observed data rather than relying solely on the manufacturer-prescribed intervals. This data-driven approach typically reduces unexpected downtime by 30 to 50 percent while maintaining or improving overall system reliability.
Final Notes On Keeping These Systems Running
The total cost of ownership for a diagnostic x-ray system extends well beyond the initial purchase price, encompassing installation, training, maintenance, parts replacement, regulatory compliance, and eventual decommissioning. The typical total cost over a fifteen-year lifespan is two to three times the initial equipment price, though this varies significantly depending on the equipment class, usage intensity, and the quality of the maintenance program in place. Budgeting for these ongoing costs from the acquisition phase helps avoid the situation where functional equipment is taken out of service due to unaffordable maintenance expenses. The operator mindset toward x-ray equipment heavily influences both image quality and equipment longevity. Technicians who understand the relationship between their exposure selections and the resulting tube loading, thermal stress, and component wear tend to make more conservative choices that extend equipment lifespan. The typical difference in annual maintenance costs between well-trained and poorly trained user populations is approximately fifteen to twenty-five percent, primarily due to reduced component stress from appropriate exposure technique selection and more careful equipment handling during patient positioning. When evaluating equipment replacement decisions, the operational data from the existing system should be the primary input rather than manufacturer sales presentations. The actual failure rates, downtime hours, image quality metrics, and maintenance cost trends over the past three to five years provide a more reliable basis for projection than theoretical specifications or promotional materials. The typical payback period for equipment replacement ranges from three to seven years, depending on the magnitude of the improvement in reliability, image quality, and operational efficiency achieved by the new system.
The documentation standard for x-ray equipment service should meet the same rigor expected for clinical patient records, with each service action documented thoroughly enough that another qualified technician could understand exactly what was done, why it was done, and what the expected outcomes should be. The typical documentation gap in this industry results in repeated diagnostic efforts, unnecessary component replacements, and difficulty in tracking long-term equipment performance trends. Establishing a consistent documentation format from the outset of your service career pays dividends throughout your entire career. When dealing with vendor support for x-ray equipment, the quality and responsiveness of support varies significantly between manufacturers and regions. The typical support experience includes phone and email assistance, on-site service visits, spare parts delivery, and technical training, with response times ranging from same-day for critical issues to several weeks for non-urgent requests. The practical strategy is to establish formal service agreements that specify response time commitments, pricing structures, and escalation procedures, then track actual performance against these commitments to inform renewal decisions and negotiate improvements. The technological obsolescence cycle for diagnostic x-ray equipment is typically longer than for consumer electronics, with major manufacturers supporting equipment models for fifteen to twenty years after production ends. However, the supporting infrastructure such as film processing chemicals, specific detector technologies, and proprietary interface protocols may become obsolete more quickly, creating gaps in maintenance capability that require creative solutions or system upgrades to address. Planning for these obsolescence transitions during the equipment acquisition phase helps avoid emergency replacement scenarios.
Radiation protection design features in modern x-ray equipment have improved significantly over the past two decades, with inherent filtration, collimation, and exposure control systems reducing both patient and occupational dose compared to earlier generations of equipment. The typical dose reduction achievable by upgrading from a 1990s-era system to a modern inverter-based unit with automatic exposure control and digital detection is approximately 40 to 60 percent for equivalent image quality, though the exact improvement depends on the specific technologies involved and the clinical applications being served. The interdisciplinary nature of x-ray equipment maintenance requires knowledge spanning electrical engineering, mechanical systems, radiation physics, computer networking, and regulatory compliance. No single technician can master all these domains, so the practical approach is to develop deep expertise in the areas most relevant to your specific assignments while maintaining working knowledge of the surrounding domains and building relationships with specialists in the other areas. The typical time investment to reach competency in x-ray equipment service is three to five years of structured training and supervised practice, with ongoing education required to maintain current knowledge as the technology evolves. When considering a career in medical equipment service, the demand for qualified technicians remains strong, with employment growth projections matching or exceeding the average for all occupations in most developed economies. The compensation varies significantly depending on the employer type, geographic location, specialization level, and certification status, with typical annual salaries ranging from forty thousand to one hundred twenty thousand dollars for full-time positions. The job satisfaction ratings in this field tend to be above average, primarily due to the technical challenge, the direct impact on patient care, and the relatively stable employment outlook compared to many other technical fields.
The certification pathways for x-ray equipment service technicians vary by country and region, with some jurisdictions requiring formal licensing while others rely on employer-based competency assessment. The typical certification process involves documented training hours, supervised work experience, written and practical examinations, and periodic continuing education to maintain credential status. The investment required to obtain and maintain certification ranges from two thousand to ten thousand dollars over a five-year period, depending on the certification body and the specific requirements involved, though the career often exceeds this investment within the first few years of certified practice. When working with specialized imaging modalities such as mammography, interventional radiography, or dental radiography, the component requirements and maintenance procedures differ significantly from general radiography, requiring additional training and specialized test equipment to service properly. The typical specialization investment includes additional coursework, hands-on training with the specific modality, and acquisition of modality-specific test phantoms and measurement instruments. The compensation premium for specialized technicians ranges from ten to thirty percent above general radiography service rates, reflecting the increased training requirement and the smaller pool of qualified practitioners in each specialty. The global perspective on x-ray equipment service reveals significant variations in available resources, regulatory frameworks, and training opportunities across different regions. Developed economies typically have well-established service infrastructure with multiple qualified technicians per installation, while developing regions may rely on mobile service teams covering large geographic areas with limited spare parts inventory. The practical approach for technicians working in resource-constrained environments is to develop strong diagnostic skills, maintain flexible problem-solving approaches, and build local relationships with suppliers and specialists who can provide support when needed.
When the equipment reaches end of useful life, the decommissioning process should follow established procedures that ensure all radiation-emitting components are rendered inoperative, all hazardous materials are properly disposed of, and all regulatory documentation is completed and retained as required. The typical decommissioning timeline is one to two weeks per system, depending on the complexity of the installation and the regulatory requirements of the jurisdiction. The cost ranges from five hundred to five thousand dollars per system, though government or institutional programs sometimes provide funding assistance for decommissioning projects, particularly when the equipment contains significant quantities of hazardous materials or when the facility is being repurposed for alternative use. The historical context of x-ray equipment development from Wilhelm Röntgen's initial discovery in 1895 to modern digital systems provides perspective on the rate of technological change and the recurring patterns of innovation, adoption, and optimization that characterize the field. Understanding this history helps technicians appreciate both the engineering achievements that have made modern diagnostic imaging possible and the ongoing challenges that require continued innovation and refinement. The typical insight gained from studying the history is that many of the problems being addressed today have parallel precedents going back decades, and the solutions that proved effective in earlier eras often provide useful frameworks for approaching current challenges. When reflecting on a career in x-ray equipment service, the most memorable aspects tend to be the challenging diagnostic puzzles that required sustained effort to solve, the relationships built with the clinical staff who rely on the equipment for patient care, and the tangible impact of keeping critical diagnostic technology operational in hospitals and clinics that serve vulnerable populations. The typical career satisfaction comes not from the technical complexity alone but from the understanding that the work directly enables the diagnostic accuracy that guides clinical decision-making and patient outcomes. This perspective helps maintain motivation during the inevitable periods of frustration, uncertainty, and fatigue that accompany any demanding technical career.
