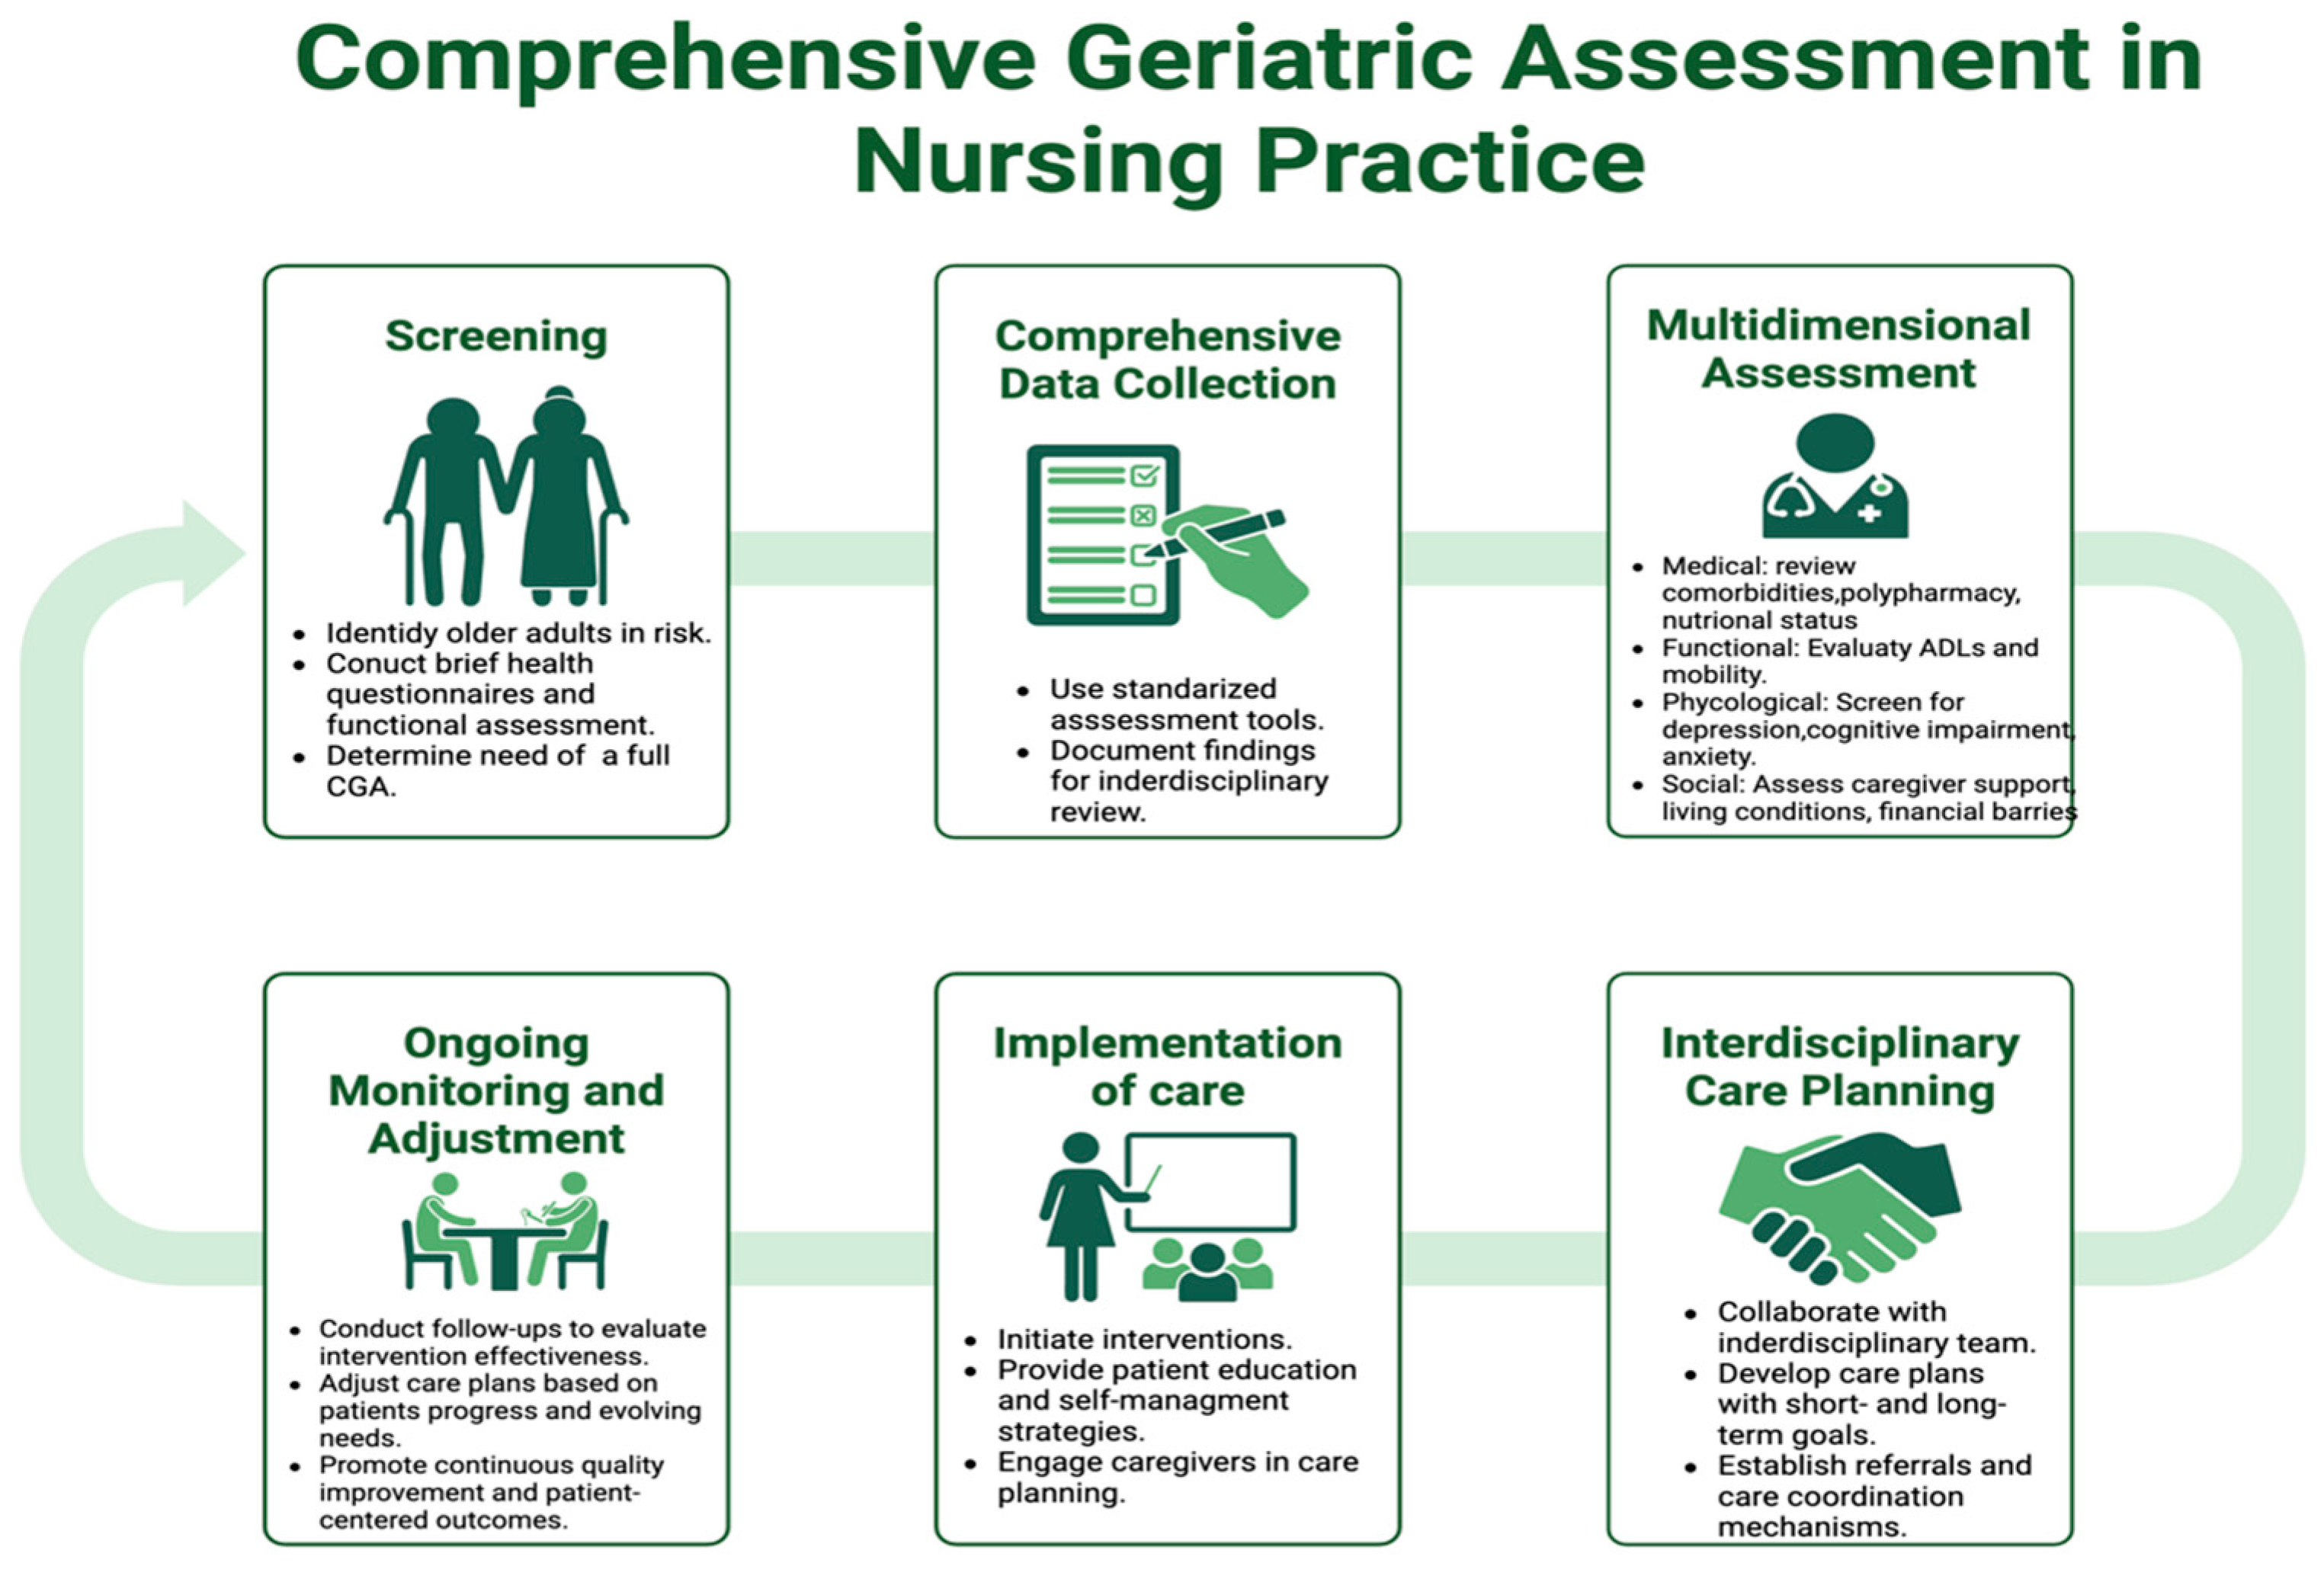
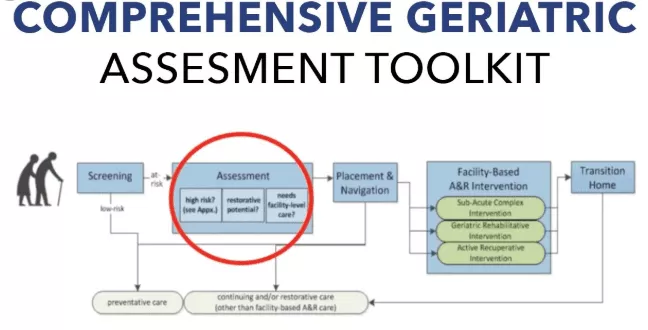
Most people treat it like a checkbox exercise. They print out a falls risk sheet, ask someone how many medications they take, and call it a day. That's not Comprehensive Geriatric Assessment. It's a data collection form with delusions of grandeur.
A real C-GA looks at the whole picture. Functional status, cognition, mood, polypharmacy, social support, frailty markers, sensory deficits, nutrition, continence. You're mapping a person, not filling out a questionnaire.
Comprehensive Geriatric Assessment in practice
Here's how it actually plays out. You need time. I usually block 45 to 90 minutes depending on complexity. If you're rushing through this in 15 minutes, you're missing things. The assessment starts before you even see the patient. You review the chart for recent hospitalizations, lab trends, medication changes, and caregiver notes. Those patterns tell you where to focus.
The core components break down like this.
Functional assessment. You're not asking if they can manage at home. You're measuring their instrumental activities of daily living and basic activities of daily living. Use the Lawton scale for IADLs and the Katz index for ADLs. But here's what most people skip. You observe them. Watch how they transfer from chair to standing. Note the time it takes. Check for hesitation. That's data a questionnaire won't give you.
Cognitive screening. Mini-Cog works fine for quick sweeps. Montreal Cognitive Assessment catches more mild impairment. But MoCA has a ceiling effect with educated patients. I've seen people score 30 and still have significant executive dysfunction. If the numbers look clean but something feels off, dig deeper. Clock draw test plus a verbal fluency task catches frontotemporal issues that MoCA might miss entirely.
Medication review. This is where things get messy. Polypharmacy isn't just about counting pills. It's about identifying potentially inappropriate medications using Beers criteria or STOPP/START tools. I had a patient on a proton pump inhibitor for three years without a documented indication. His albumin was low, he had recurrent C. difficile infections, and nobody connected the dots because they were looking at isolated problems. Stopping the PPI resolved the recurrent infections within two weeks. That's the kind of thing C-GA surfaces.
Mood assessment. Geriatric depression often presents atypically. Not as sadness but as apathy, cognitive complaints, or somatic symptoms. Use the GDS-15. But don't stop there. Anxiety, adjustment disorders, and complicated grief are common too. I recently worked with a woman who scored in the normal range on depression screening but had severe health anxiety driving repeated ED visits. Her family thought she was just being difficult. She wasn't. She had undiagnosed generalized anxiety disorder layered on top of early dementia.
Social determinants matter more than you think. Living situation, caregiver availability, financial resources, transportation, health literacy. A patient with excellent clinical outcomes but no one to drive them to follow-up appointments is a failed intervention waiting to happen. Use the PRIME-MD or PHQ-9 alongside a social interview. I keep a running list of community resources in my practice because spending ten minutes navigating them during the assessment itself is wasteful.
Frailty evaluation. Clinical frailty scale takes about two minutes. You show the patient a pictorial scale and they pick the row that matches their baseline. It's validated, quick, and surprisingly accurate. Frailty predicts everything from post-surgical complications to hospital readmission. If you're not measuring it, you're flying blind.
Nutritional screening. Malnutrition in older adults is embarrassingly common and rarely diagnosed early enough. Use the MNA-SF. Albumin is useless as a standalone marker because it reflects inflammation as much as nutrition. Prealbumin is better but still inflammatory-sensitive. I weigh patients every visit and track trends. Unintentional weight loss of more than five percent in six months is a red flag that deserves investigation, not just a dietary supplement prescription.
What nobody tells you about this process
The biggest problem isn't assessment tools. It's poor documentation. You can identify twenty risk factors in an hour but if the care team can't access that information later, none of it matters. I started using structured templates built into the EHR rather than free text notes. Templates force you to address each domain. Free text notes get written by someone who already decided which two problems they cared about.
Another issue. Family members are often unreliable historians. They minimize decline to avoid institutionalization conversations. They also overstate independence because they're exhausted and need the patient to function better than they do. I always try to speak to the patient alone for at least part of the assessment. Caregivers will fill in gaps, but they'll also smooth over problems.
Coordination is the real bottleneck. Comprehensive Geriatric Assessment generates a list of problems. Maybe fifteen of them. What do you prioritize? The answer isn't obvious. Falls risk, uncontrolled diabetes, depression, medication interactions, social isolation, cognitive decline, malnutrition, urinary incontinence. They all interact. Treating one in isolation makes another worse. I've seen blood pressure go dangerously low after aggressively treating hypertension in a frail patient who was already borderline orthostatic. The assessment should catch that interaction before treatment starts.
The multidisciplinary component is non-negotiable. Medicine alone doesn't solve these problems. Physical therapy for mobility and balance. Occupational therapy for adaptive equipment and home safety. Pharmacotherapy for deprescribing. Social work for resource navigation. Nutrition for intake. Speech therapy for swallowing and cognition. This isn't optional consulting. These are core members of the assessment team.
Where it breaks down
Time and reimbursement. Most insurance models don't pay adequately for the full C-GA process. Patients expect quick visits. Administrators want throughput. The assessment gets truncated because there's no financial incentive to do it properly. I've done it anyway in private practice because the outcomes justify the time investment, but it's a constant tension.
Standardization across settings is nearly impossible. A hospital-based assessment looks different from a home-based one, which looks different from a clinic visit. Transfer of information between settings is unreliable. I've had patients complete thorough assessments in hospital only for their primary care provider to restart medications that were intentionally deprescribed because the hospital discharge summary never made it to the office chart.
Cultural and linguistic barriers complicate everything. Standardized tools like MoCA and GDS aren't equally valid across languages and education levels. I use translated versions when available and note the limitation. When translations aren't available, I rely more on observation and collateral history. Neither approach is ideal.
The single worst edge case I dealt with involved a patient with normal Mini-Mental State scores but profound executive dysfunction from normal pressure hydrocephalus. The MMSE was 28. The gait assessment showed magnetic gait. The CT scan confirmed ventriculomegaly. Shunt placement reversed most of the cognitive and functional decline. A routine cognitive screen would have missed this completely. The functional observation caught it. That's the lesson. Don't let a normal number make you complacent.
Getting started without a geriatrics fellowship
You don't need to become a specialist to do this well. Start with the essential domains. Functional status, cognition, medications, mood, nutrition. Build templates around those five. Use validated tools for each. The key is consistency. Doing a partial assessment every time beats doing a perfect one sporadically.
Document systematically. Use the same structure for every patient. It creates patterns you can recognize across visits. A patient whose gait speed dropped from 0.8 to 0.6 meters per second between visits is declining even if they "feel fine." Numbers don't lie the way memory does.
Follow up on findings. Identification without intervention is just documentation. Close the loop. Refer to PT. Adjust medications. Connect with social services. Reassess in sixty to ninety days. The cycle matters more than the snapshot.
I stopped trying to do everything in one visit about three years ago. Now I do the core assessment in the first encounter and spread targeted evaluations across subsequent visits. Cognition this month, med review next month, functional re-evaluation after that. It's more sustainable and patients respond better when you're not dumping a dozen questionnaires on them at once.
Gallery Comprehensive Geriatric Assessment
Comprehensive Geriatric Health Assessment Core Competencies and Skills ...
Comprehensive Geriatric Assessment Form | PDF | Geriatrics | Dementia
Comprehensive Geriatric Assessment Summary | PDF
A Comprehensive Geriatric Assessment (CGA) is an evidence-based form of ...
Comprehensive Geriatric Assessment (CGA): An Overview - GlobalRPH