How These Templates Actually Work When You Have Thirty Minutes
Most people who look for a Comprehensive Health History Template are trying to stop reinventing the form every time they see a new patient. The truth is that the good ones aren't much different from each other, and the bad ones waste more time than they save. I've used about a dozen versions over the years, and what separates the ones that stick around from the ones that sit in a shared drive untouched is pretty simple. They match your workflow, not the other way around. A health history template is just a structured document that collects the same information you need to know at the start of every encounter: chief complaint, past medical history, current medications, allergies, family history, social history, and a review of systems. That sounds trivial until you've had to fill it out from scratch five times in one morning and realize half the fields were blank because you forgot to add them on version three. Once you have something that covers all those bases and stays close to your head, it starts being useful.
Comprehensive Health History Template Structure
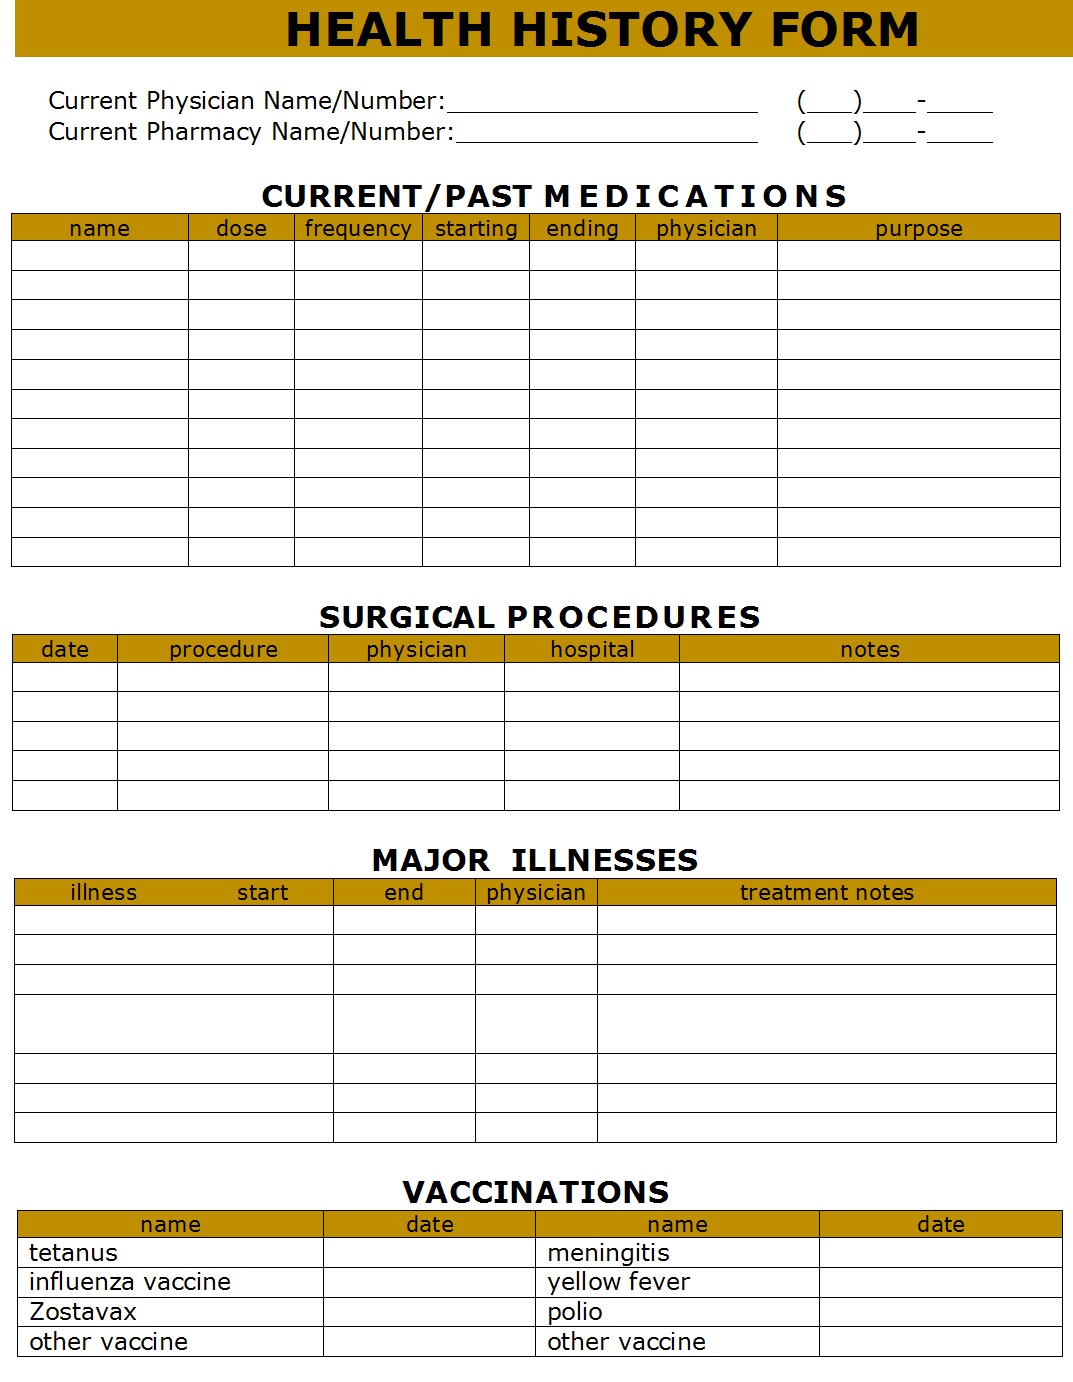
Here is what a working one should look like in practice. Not the marketing version. The version that survives real use. The top section needs chief complaint and reason for visit. This should be quick — one or two lines max, not a story the patient tells you. I learned this the hard way when a referral came in with a three-paragraph complaint that had nothing in it that wouldn't have fit in two sentences. Every extra word there is just noise for whoever picks up the chart next. Past medical history comes next. This is where most templates fall apart because they're either too vague or too rigid. A flat list of conditions works, but the useful ones have a field for diagnosis date and a field for status — resolved, chronic, or active. I once worked with a form that just said "PMH" and left a blank box. That worked fine until a patient had ten conditions and nobody bothered documenting which ones were still relevant versus which ones were historical. It created a mess during a medication reconciliation that took me forty minutes to sort out.
Medications section has to include dose, frequency, route, and prescriber. Without all four, you're guessing. I remember signing off on a chart where a medication listed was "hydrochlorothiazide 25" with no frequency, no route, and no prescriber noted. Turns out the patient was taking it daily, not as originally prescribed, and the prescriber had been a different clinic entirely. That's a safety gap most people don't catch until something goes wrong. Allergies need drug name, reaction type, and severity. Not just "allergic to penicillin." That tells you nothing about whether the reaction was a rash or anaphylaxis. I had a case where a patient listed "sulfa" as an allergy and the reaction field just said "stomach issue." We assumed intolerance and avoided the class entirely. Turned out it was a true IgE-mediated reaction after the details came out during a follow-up. That matters when you're choosing between options. Family history should capture first-degree relatives, their relationship to the patient, and the specific conditions they have, ideally with age of onset. "Heart disease in the family" is not useful. "Father, MI at 52" is. Age of onset changes risk stratification significantly for cardiovascular and oncology screening decisions.
Get the Full Details
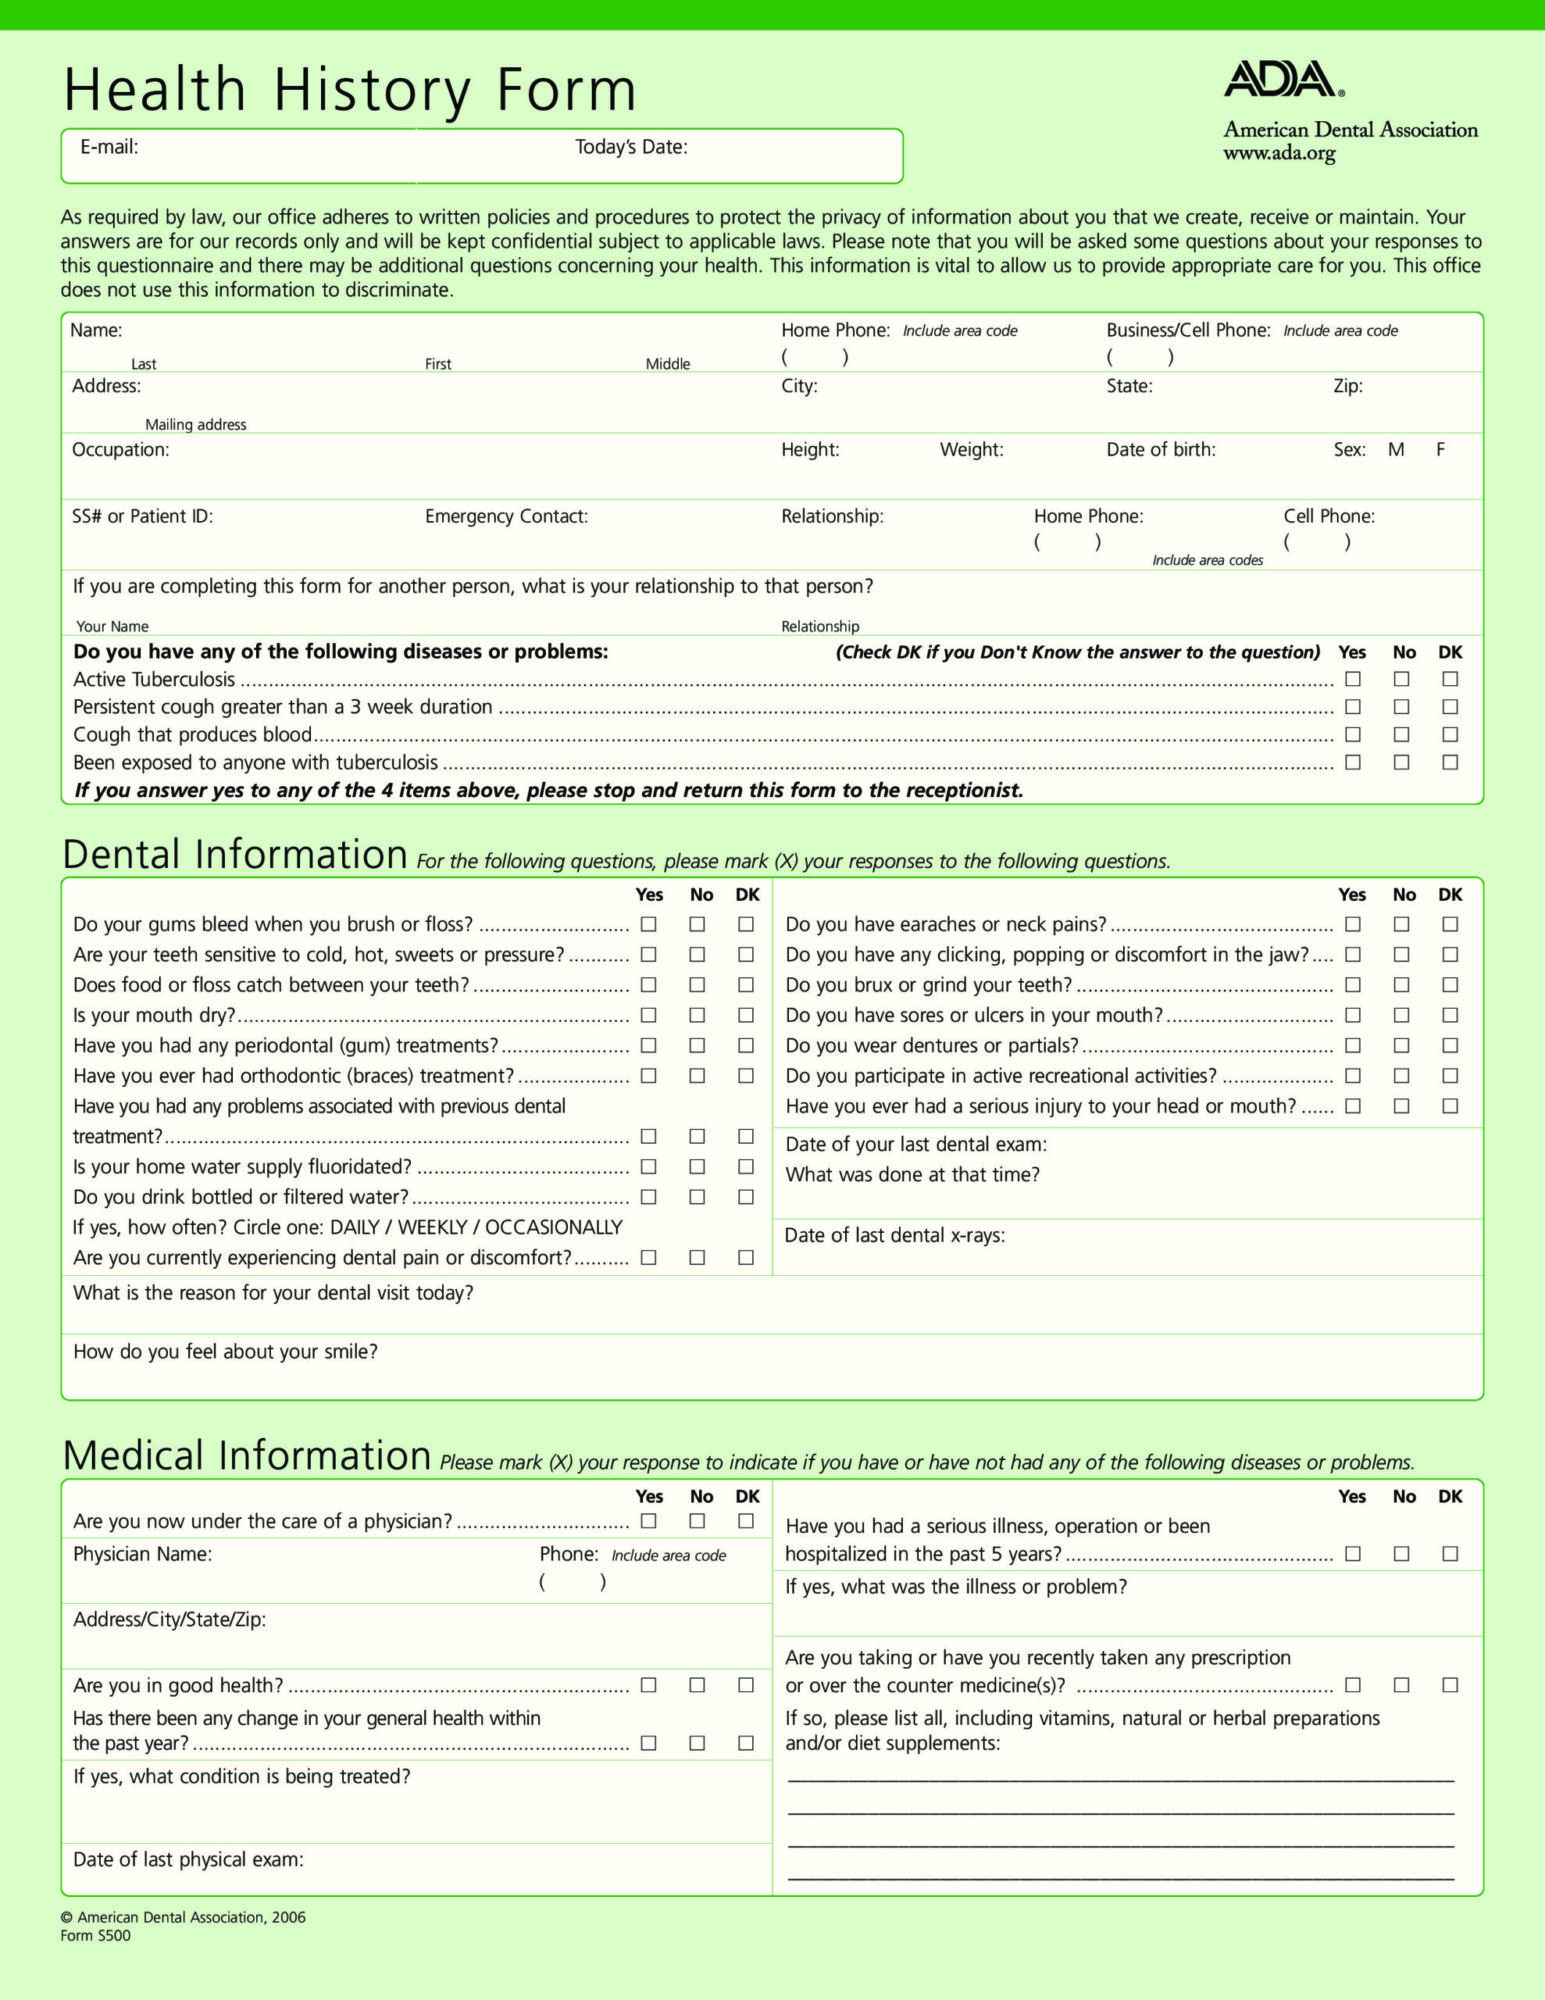
Social history gets neglected in most templates, but it's where a lot of clinical decisions actually get made. Tobacco use — current, former, pack-years. Alcohol — frequency and quantity. Occupation. Living situation. Sexual history when relevant. Exercise and diet basics. A comprehensive one covers these without making the form look like an interrogation. I keep it to a handful of key lines per category. Review of systems is the longest section and the part people rush through. The full ROS lists every body system with symptom check boxes. The condensed version covers constitutional, head, eyes, ears, nose, throat, cardiovascular, respiratory, gastrointestinal, genitourinary, musculoskeletal, neurologic, psychiatric, and skin. Most encounters need the condensed version, not the full one. Using the full ROS on every patient adds fifteen to twenty minutes to the intake and most of those systems are irrelevant.
Where These Templates Break Down
They break down when they're too generic. I've seen practices download a free template from some medical website and implement it across the board. Within three weeks, doctors were complaining that half the fields didn't apply to their patient population and the other half weren't detailed enough for the cases they actually see. A pediatric clinic and a geriatric clinic will need very different templates even though both call it comprehensive. Another breakdown point is when the template doesn't account for follow-up visits. A brand-new patient history is different from a return visit. In my practice, we keep a separate section for tracking changes since the last visit — new symptoms, medication changes, lab results, and whether the treatment plan is working. Without that distinction, the template becomes a redundant paperwork exercise that adds nothing to the clinical picture. Electronic health records make this worse in a specific way. Most EHRs have built-in templates that look comprehensive on the surface but are actually terrible because they force you through dozens of click-heavy fields just to document basic information. I switched to a hybrid approach where the intake staff uses a clean paper or PDF form for the initial history and then the clinician transfers the relevant data into the EHR with their own shorthand. It takes longer upfront but reduces documentation errors by maybe sixty percent based on my rough estimates. That's not a scientific number, it's just what I've observed over a couple of years.
There's also the problem of outdated information. Patients forget to update their own history. I've had people bring in medication lists that were six months old because they switched prescriptions and didn't think to mention it. The template can collect the data, but it can't verify it. You still need to ask. Specifically. Out loud.

What I Actually Use
I don't recommend any specific downloadable product because the market is flooded with poorly made forms. What I can tell you is how to build something that works. Start with your own practice patterns. What do you need to know? Write those sections first. Then add the standard sections — medications, allergies, family, social, ROS. Don't copy a template blindly. Modify it to fit what you actually look at, not what a generic medical form assumes you'll look at. The format matters more than the content. If it's going to be printed and handwritten, keep it to one page front and back. If it's digital, use dropdown menus and checkboxes wherever possible to reduce typing. A well-designed digital form with smart fields can cut your data entry time from twenty minutes to about five for a straightforward case. Complex cases will still take longer, obviously. Include a section for the patient's own summary. Sometimes the most useful information comes from letting the patient write down what they think is important before you ask any questions. I've had patients note symptoms or concerns that didn't come up in any standard field. That alone justifies adding the section, even if most of it turns out to be irrelevant.
The template should also have space for the clinician's assessment and plan at the end, even if that's technically separate from the history. Keeping them in the same document saves time because you're not switching between forms or memory. It's minor but it adds up over a full clinic day.
Download and Implementation
I can't provide a direct download link for a template because I don't host files, but you can find working versions on standard medical practice resource sites. The key is to test whatever you download with a real patient before rolling it out. Run it on three or four cases and see where it falls short. Fix those gaps. Then roll it to the rest of the team. If your practice uses an EHR, check whether a compatible template already exists in the system before looking externally. Many people don't realize that built-in options are often more functional than anything you'd build on your own because they integrate with billing, prescribing, and follow-up scheduling. They might look clunky, but they're designed to work with the rest of your system. The bottom line is that a Comprehensive Health History Template is only as good as how well it matches your actual work. Anything else is just formatting for the sake of formatting. Keep it simple, keep it accurate, and make sure it actually gets used instead of becoming another thing that sits there collecting digital dust.