Getting Compression Therapy For Venous Insufficiency Right
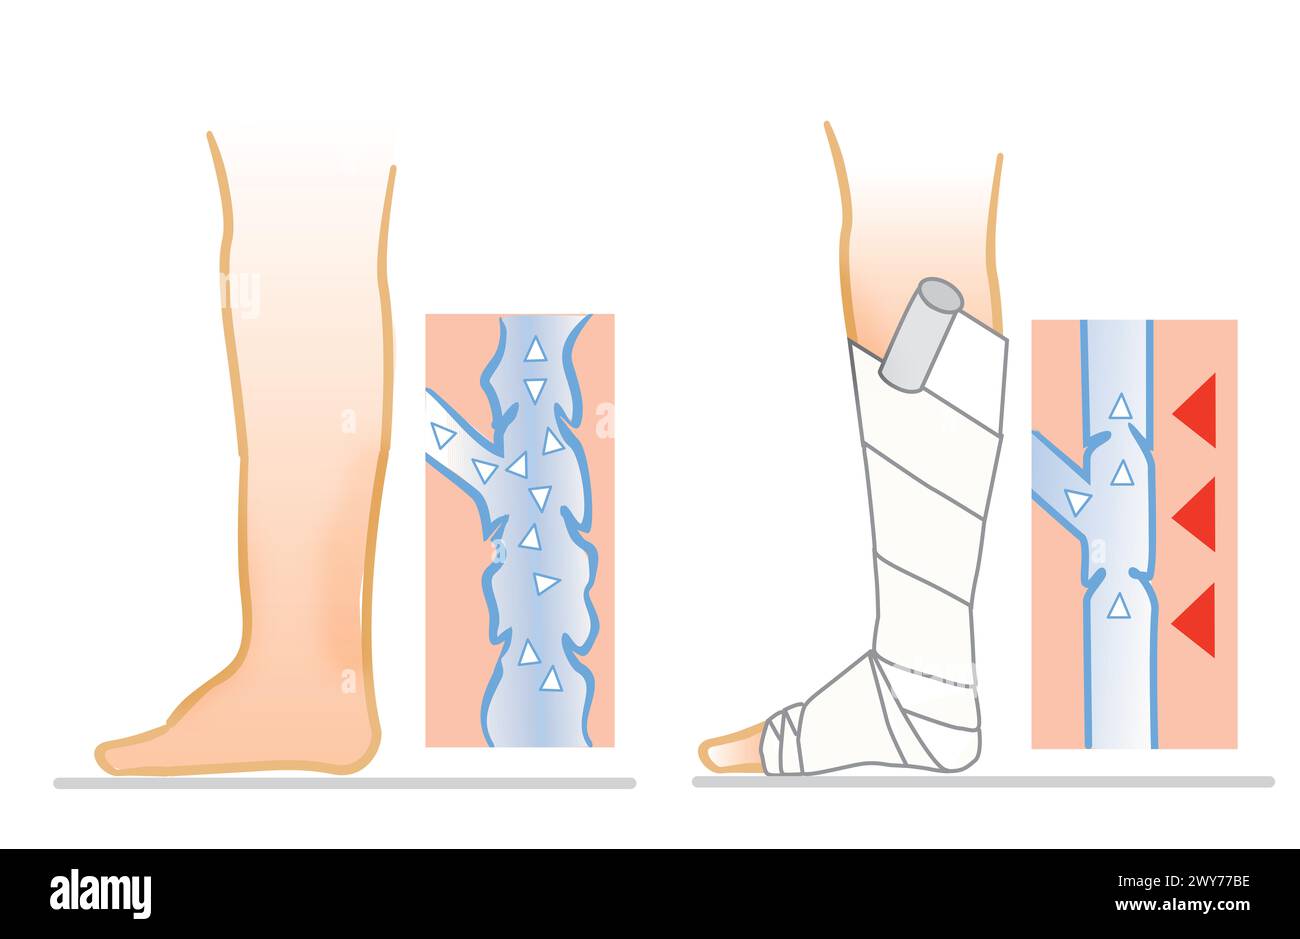
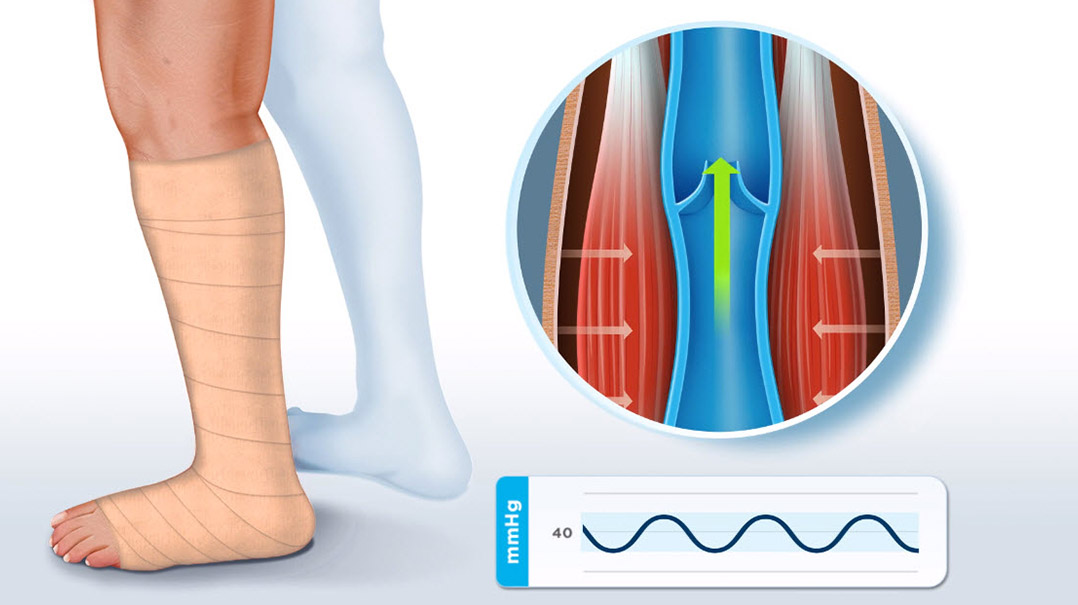
I've dealt with venous insufficiency patients for years, and the thing that separates effective compression therapy from frustrating waste of money is understanding the mechanics, not just buying the cheapest pair of stockings online. Most people don't realize that graduated compression works by creating a pressure gradient, not just squeezing your leg uniformly. Here's what actually happens under the fabric. You need distal pressure to be highest at the ankle—typically 20-30 mmHg for mild cases, 30-40 mmHg for moderate to severe—and it decreases as you move up the leg. This gradient encourages venous return toward the heart. If the pressure is equal throughout or higher proximally than distally, you're basically strangling blood flow instead of helping it. I've seen patients waste hundreds of dollars on improper compression because they didn't measure correctly. You need to measure the ankle at its widest point, the calf at its fullest circumference, and the thigh if you're doing thigh-highs. The measurements should be taken at the end of the day when swelling is at its peak. Measuring in the morning gives you false readings that result in ill-fitting garments.
The application technique matters just as much as the fit. Turn the stocking inside out to the heel point, insert your foot, make sure the heel sits correctly in the heel pocket, then pull it up smoothly without rolling or bunching. Any wrinkles create pressure points that can damage tissue. I had a patient once who developed skin breakdown because she kept bunching her compression hose around her ankle instead of smoothing them flat against her skin. When it comes to material choice, knit fabrics breathe better but lose elasticity faster. Weave fabrics maintain compression longer but can feel restrictive. For patients who need to wear them all day, especially in warm climates, I usually recommend starting with open-toe styles to reduce heat buildup and allow better circulation to the digits. Closed-toe options work fine for office settings where temperature is controlled. The duration of wear matters too. Most guidelines suggest putting them on first thing in the morning before edema develops, wearing them throughout the day, and removing them before bedtime. Some patients report improved symptoms when they elevate their legs for 15-20 minutes after removing the stockings in the evening. I find this timing helps manage the fluid shift without causing orthostatic issues.
There's a common misconception that compression therapy cures venous insufficiency. It doesn't. The condition is chronic and progressive. Compression manages symptoms and prevents complications like ulcers and deep vein thrombosis, but it doesn't fix the underlying valvular incompetence. Patients need to understand this distinction or they'll develop unrealistic expectations and stop using the therapy prematurely. For severe cases with significant edema or active ulceration, wrap systems might be more appropriate than pre-formed stockings. These allow adjustable compression and accommodate changing limb volumes throughout treatment. I've used both systems in clinical practice, and the choice depends on the patient's mobility, dexterity, and stage of disease. One practical tip that isn't obvious: keep a pair of rubber gloves or use powder to help with donning. Silicone-based aids work well but can degrade certain fabric types over time. I usually recommend checking the manufacturer's instructions before applying any lubricants. Wrong products can damage the elastic fibers and reduce compression effectiveness within weeks rather than months.
Get the Full Details

Replacement frequency is another overlooked factor. Most quality compression garments maintain their therapeutic compression for about 3-6 months with proper care, then lose 20-30% of their effectiveness. Washing in lukewarm water with mild soap, air drying away from direct heat, and storing flat rather than folded helps extend lifespan. Tossing them in the dryer might seem convenient, but it degrades the elastane fibers rapidly. If you're dealing with bilateral compression needs and have limited mobility or arthritis, consider assisted donning devices. These tools can reduce application time from 10-15 minutes per leg to under 3 minutes and prevent injury from excessive bending or straining. The initial investment pays off quickly if daily application has been a barrier to consistent therapy. There are also contraindications to watch for. Peripheral arterial disease with ankle-brachial index below 0.8 requires caution or modification of compression levels. Diabetes with peripheral neuropathy needs close monitoring for skin changes since reduced sensation can mask developing problems. Contact dermatitis from certain fabric types happens more often than people realize—switching to hypoallergenic materials or adding a silk liner can resolve the issue without abandoning therapy.
The real-world challenge with Compression Therapy For Venous Insufficiency is adherence. Patients often stop wearing their stockings because of discomfort, inconvenience, or aesthetic concerns. Addressing these barriers proactively—by selecting appropriate compression levels, discussing styling options, and setting realistic expectations—improves long-term outcomes significantly compared to simply prescribing the garment and hoping for compliance.