What a Concussion Assessment Tool Actually Is
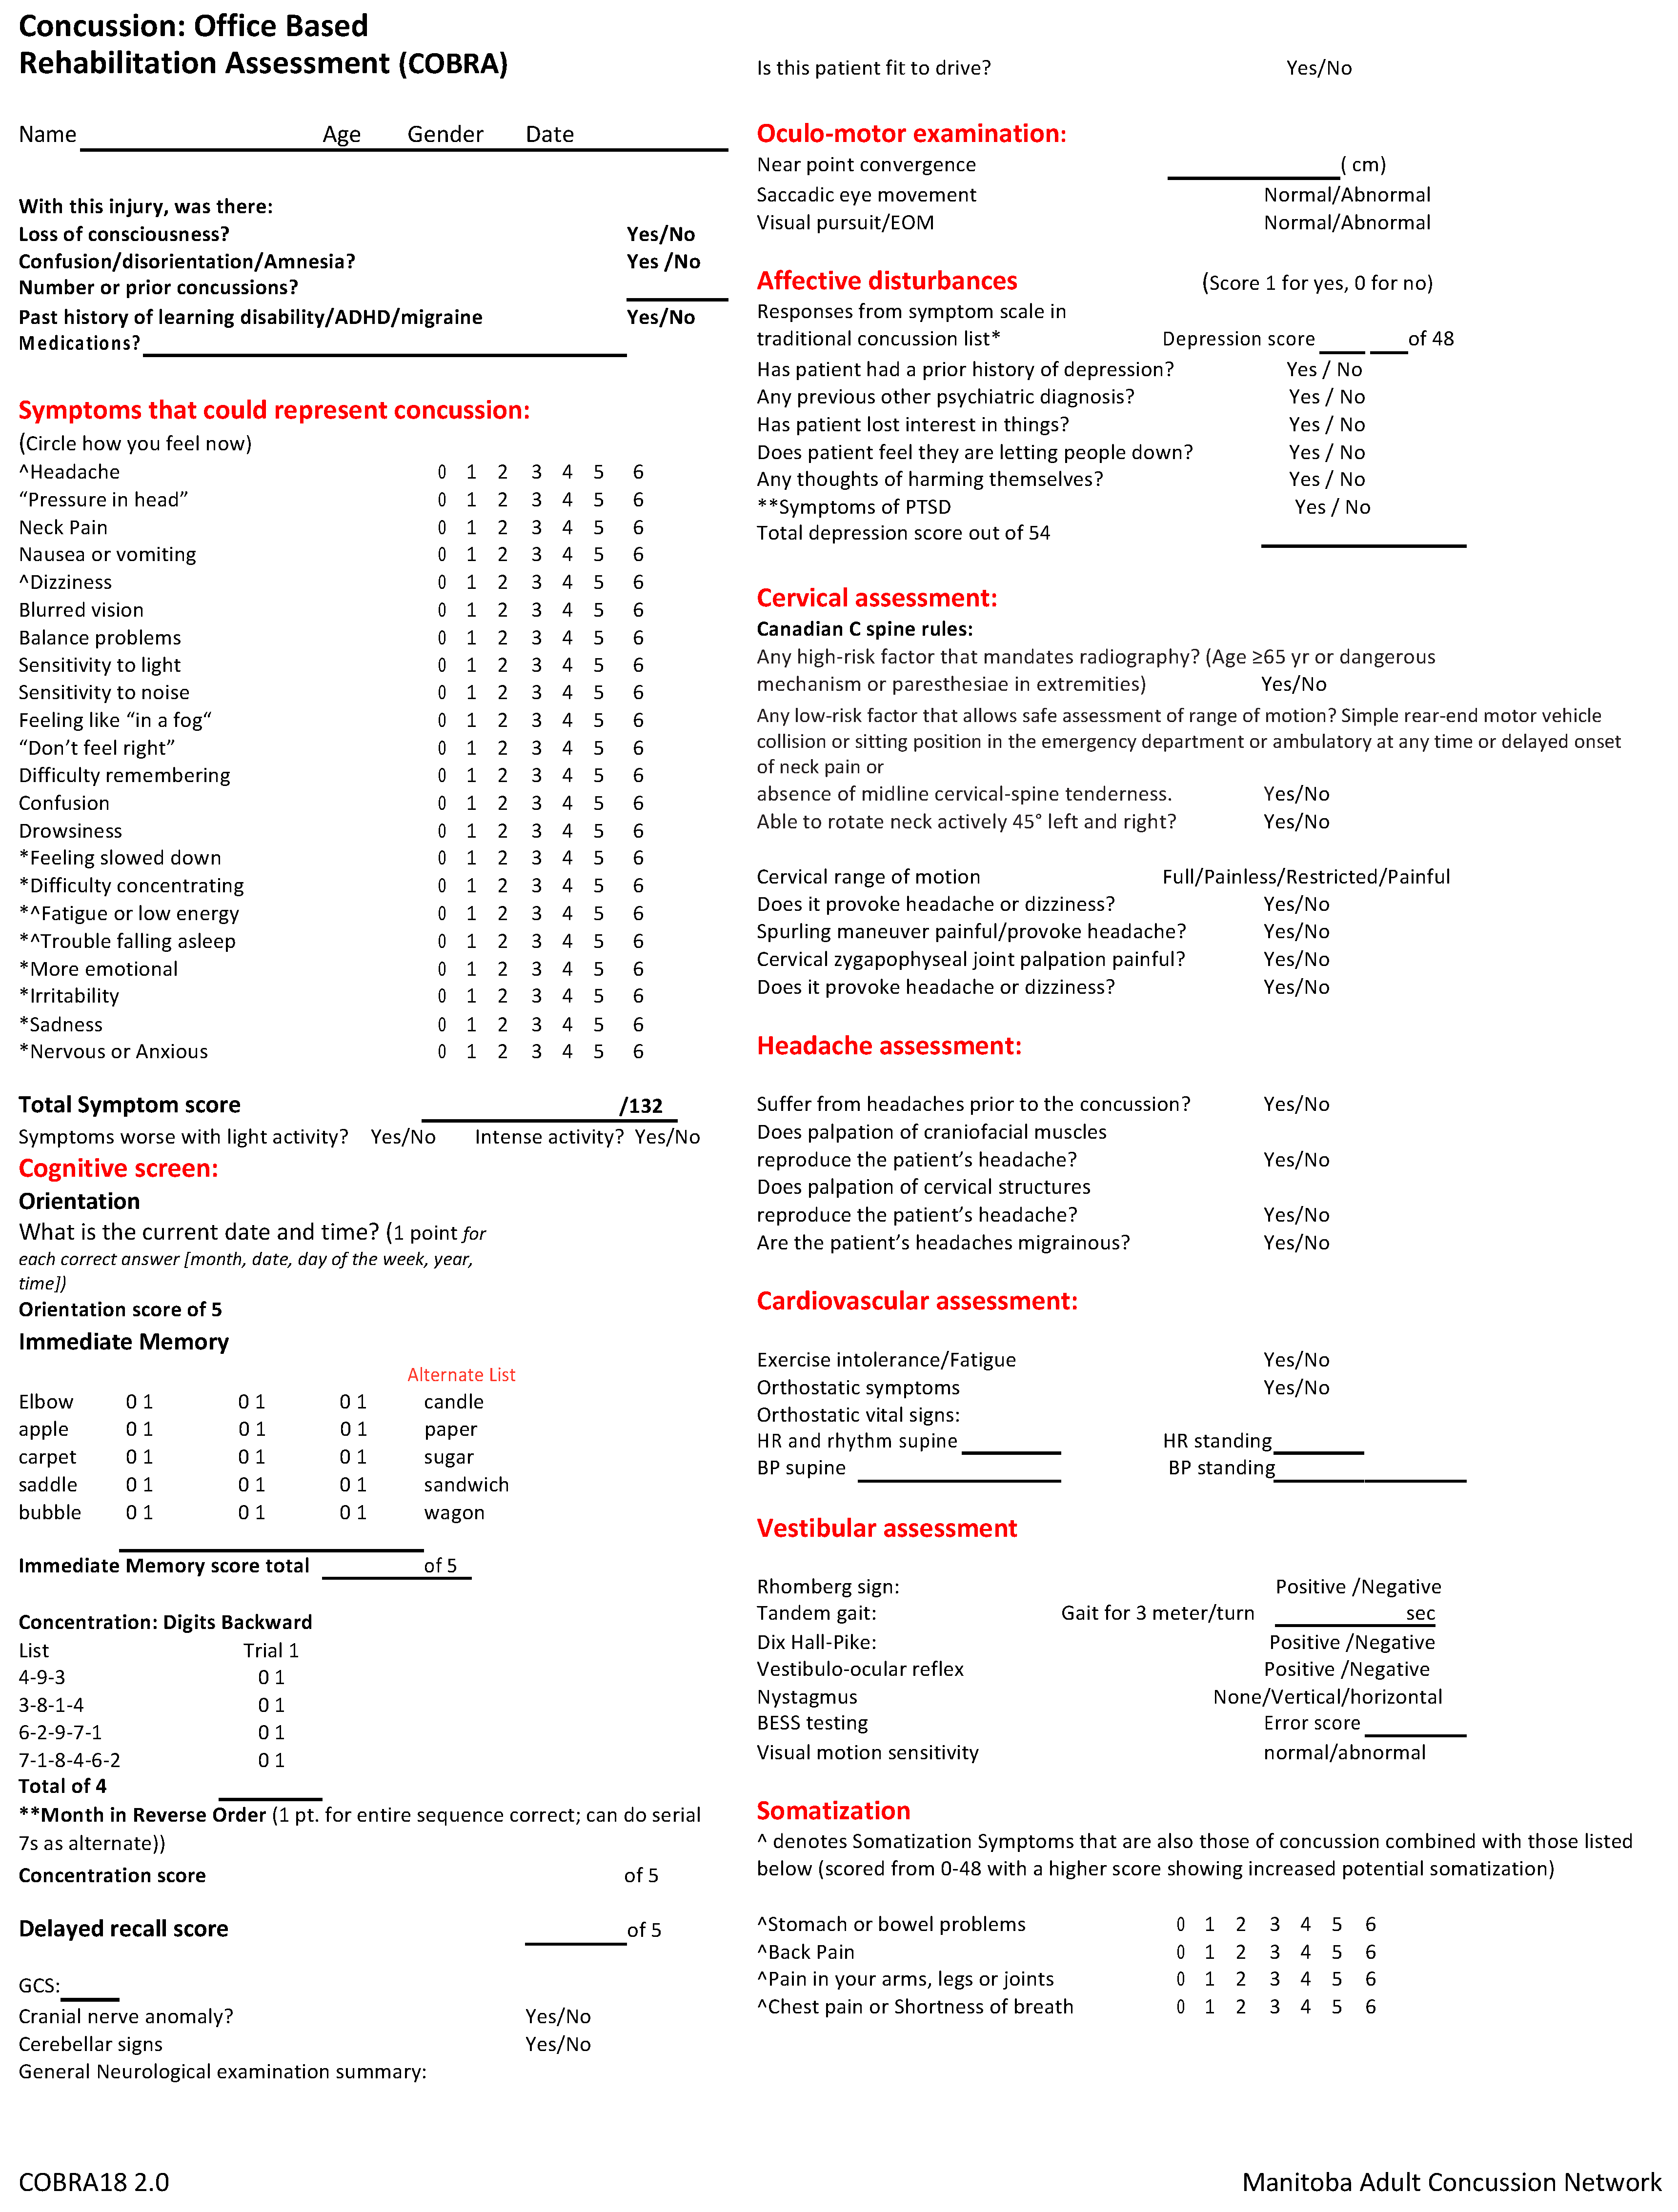
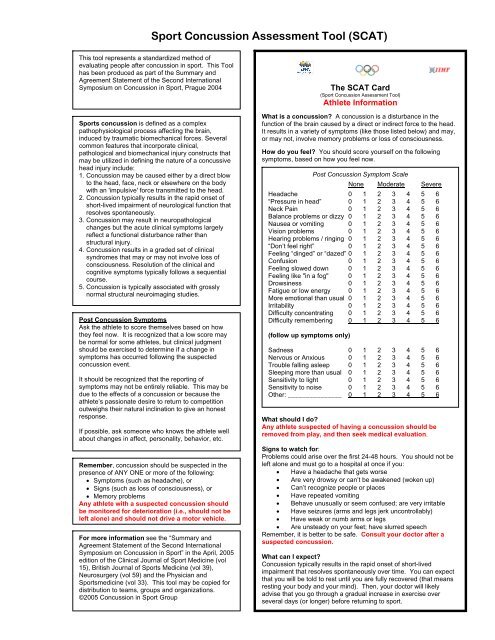
A Concussion Assessment Tool is a structured clinical instrument used to evaluate athletes or patients after a head impact. The most widely referenced version is the SCAT6, published by the Fifth International Consensus Meeting on Concussion in Sport. It's not a single test, but a battery of assessments designed to give a baseline picture of someone's neurological status. The SCAT6 combines several components: symptom evaluation, cognitive screening, balance testing, and a neck exam. The symptom scale runs through 22 items rated 0 to 6, giving a maximum score of 132. Higher scores indicate more severe symptoms. The cognitive portion includes oriented questions, immediate memory recall, concentration tasks, and the Modified Card Sorting Test. Balance is checked with the Standardized Assessment of Concussion (SAC) Balance Exam, usually a three-stance test measuring total time and errors. What I learned early on is that the tool was originally built for use by clinicians on the sideline, not by coaches or athletic trainers working alone. The original SCAT versions explicitly required a licensed healthcare professional to administer and interpret them. That distinction matters because misinterpretation is where things go wrong. I've seen athletes cleared too fast because the tester focused only on the symptom score and ignored the balance and cognitive components. The symptom scale alone is a poor standalone indicator, especially in the first 24 hours when many athletes underreport due to desire to return or actual altered awareness.
One specific problem I ran into involved a college football player who presented with a normal SCAT6 after a routine hit. His symptom score was zero, his cognitive tests were perfect, and his balance looked fine. He was ready to return. Two days later he developed a full post-concussion syndrome with persistent headaches, light sensitivity, and sleep disruption. The issue was that the initial assessment happened during the acute inflammatory window when symptoms hadn't yet peaked. Concussion symptoms often have a delayed onset curve, typically worsening over the first 24 to 72 hours. My workaround was straightforward: I stopped doing single-assessment clearances and started requiring a follow-up SCAT6 at 48 hours minimum before any return-to-play decision. It added time but caught the cases that would otherwise slip through. The tool also includes a Greytriage component and a delayed recall memory test. These are useful but not always implemented correctly. I've watched people skip the delayed recall and treat the initial immediate memory as sufficient data. That's a mistake. Delayed recall taps into a different cognitive pathway and tends to remain impaired longer than immediate recall. The Modified Card Sorting Test, which assesses executive function and cognitive flexibility, is another part I see consistently rushed. A proper administration takes about three to five minutes, not the thirty seconds some people allot it. Time pressure during sideline assessment is real, but cutting corners on those subtests makes the overall result less reliable. There are newer versions and alternatives worth mentioning. The Child SCAT6 exists for athletes under sixteen. The SIDM (Sport Concussion Identification and Management) protocol and the Concussion Error-Spotting Tool represent different approaches. Some sports organizations have moved toward computerized neurocognitive testing platforms like ImPACT or CNS Vital Signs, which offer quantified baselines and can detect subtle changes that paper-based tools might miss. None of these are perfect replacements, and each has trade-offs.
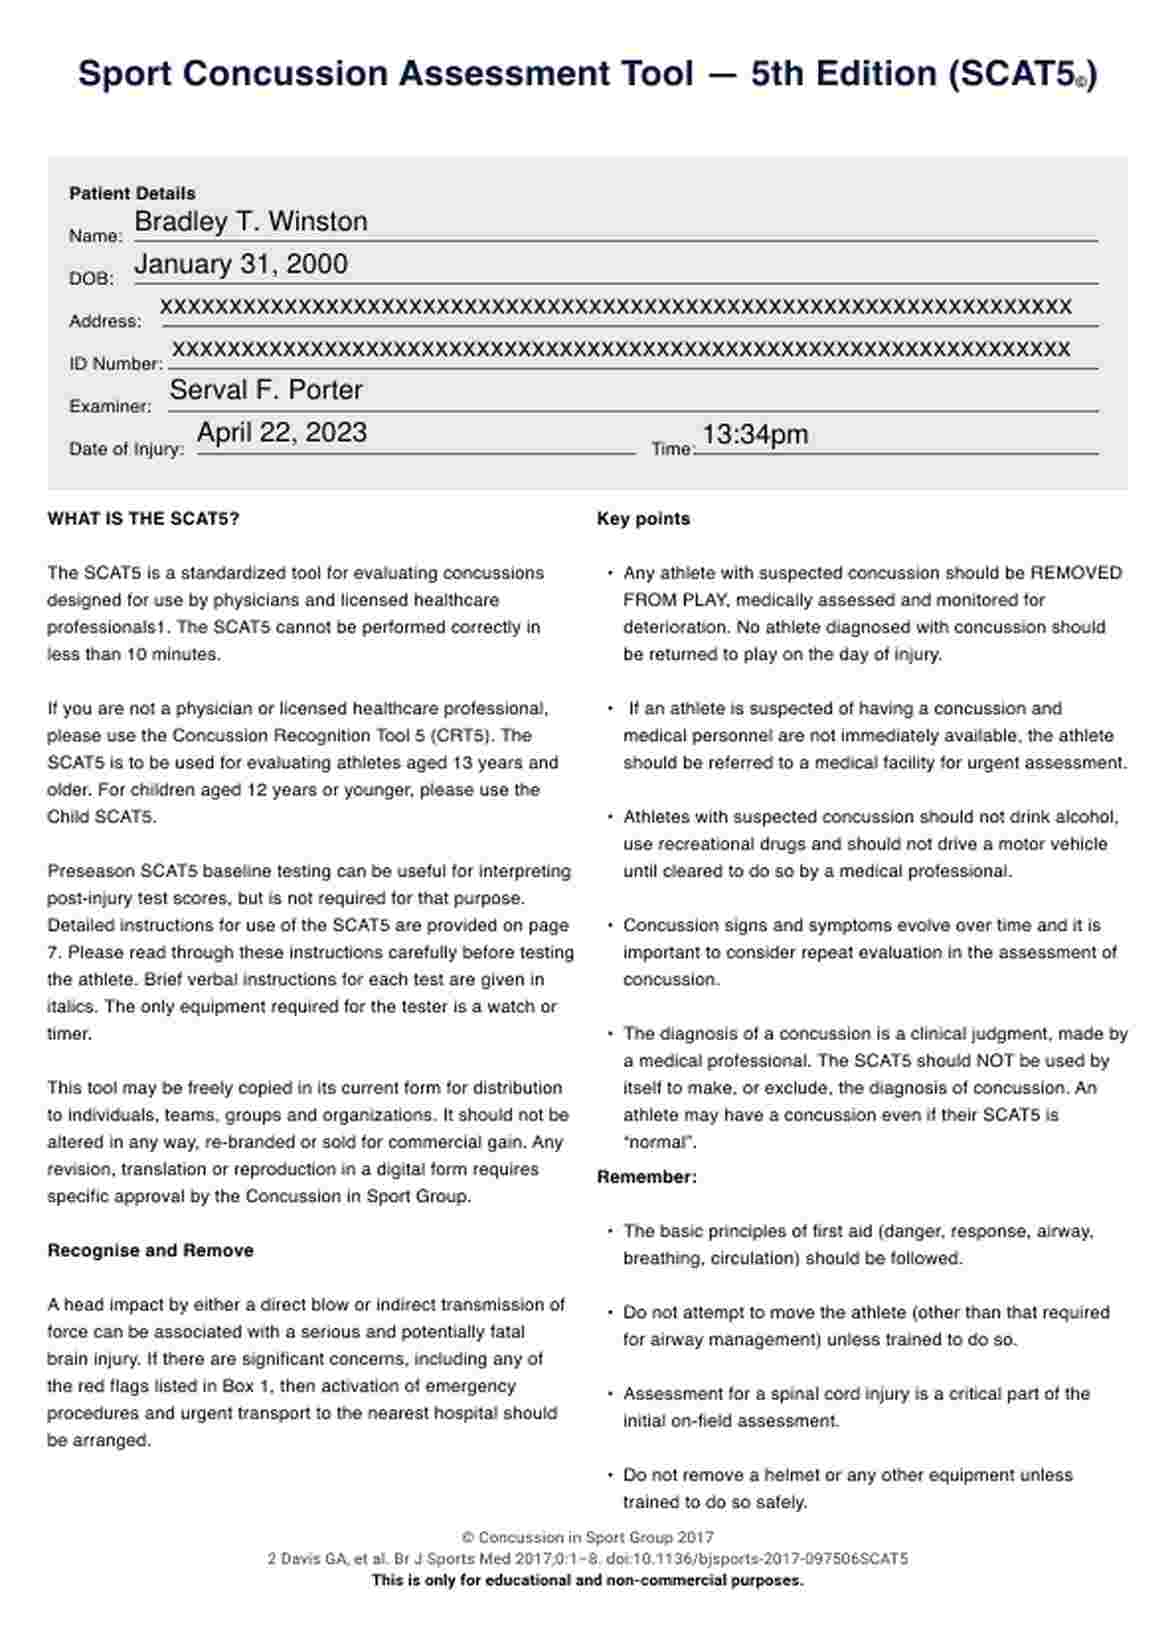
The biggest limitation of any paper-based concussion assessment tool is its dependence on the person administering it. Inter-rater reliability is moderate at best. Two clinicians can look at the same patient and arrive at different conclusions, particularly on the balance exam where scoring discretion exists. A study published in the British Journal of Sports Medicine found that sideline administrators without extensive training scored concussion tools significantly lower in accuracy compared to trained medical professionals. This isn't a flaw in the tool itself, it's a flaw in the administration chain. Another counter-intuitive point is that a normal Concussion Assessment Tool does not rule out a concussion. It indicates the absence of observable signs at that moment. The brain can sustain injury without immediately producing measurable symptoms or deficits. Neuroimaging like CT and MRI often comes back normal in concussion cases because the injury is functional, not structural. That's why the tool exists alongside clinical judgment rather than replacing it. If you're looking to download an official SCAT6, it's freely available on the Concussion in Sport Group website. They publish it directly, no registration required. The document includes detailed administration instructions, scoring guides, and notes on when to consider referral to a specialist. I'd recommend printing the instructions section and keeping it with your kit, not just the score sheets. Reading through the administration guidelines once took me about twenty minutes and reduced my early assessment errors noticeably.
Get the Full Details
The tool works best when combined with other data: pre-season baselines, serial re-assessments over several days, and input from people who know the athlete's normal behavior patterns. A teammate noticing that someone seems off is sometimes more telling than any single test score. I always factor in reports from coaches and parents alongside the formal assessment results. Return-to-play protocols vary by sport and organization, but most follow a stepwise progression once the Concussion Assessment Tool shows normalized results. You don't jump from rest to full contact. The standard steps involve symptom-limited activity, light aerobic exercise, sport-specific exercise, non-contact training, full contact practice, and finally return to play. Each step requires at least twenty-four hours minimum, and you go back a step if symptoms recur. The whole process typically spans at least five to seven days for mild cases, longer for anything more significant. I don't consider this tool a definitive diagnostic instrument. It's a screening and monitoring tool. That's what the consensus statements say, and I've seen enough cases to agree. When I encounter something beyond what the SCAT6 can capture, I refer to a neurologist or concussion specialist. The tool tells you a lot, but it doesn't tell you everything.