Understanding How These Guidelines Actually Work in Practice
Congestive Heart Failure Clinical Practice Guidelines
Most people treat clinical guidelines like rulebooks you read once and then follow blindly. That approach breaks down quickly in real clinical settings. The 2022 AHA/ACC/HFSA guidelines for heart failure represent the current standard, and they're substantially different from older versions you might still see referenced in hospital protocols. The big shift was moving from a purely ejection-fraction-based classification system to a four-stage framework that covers the entire disease continuum. You'll find yourself constantly cross-referencing sections because the recommendations aren't neatly compartmentalized the way most textbooks try to present them. Here's what most summaries miss. The guidelines use a conditional recommendation structure that heavily depends on patient phenotype. A patient with heart failure with reduced ejection fraction (HFrEF) gets a very different treatment ladder than someone with preserved ejection fraction (HFpEF). And recently added is heart failure with mildly reduced ejection fraction (HFmrEF), which sits in an awkward middle zone where the evidence base is thinner. I once spent two weeks trying to reconcile conflicting guideline language for a 72-year-old woman with HFpEF, hypertension, and moderate mitral regurgitation. The guidelines told me to prioritize SGLT2 inhibitors, then mineralocorticoid receptor antagonists, but didn't give clear direction on how aggressive blood pressure targets should be while also managing volume status. I ended up setting a systolic target of 130 mmHg and using low-dose torsemide titrated weekly rather than the higher doses the algorithm seemed to imply. That patient stayed out of the hospital for 14 months after that adjustment. The diagnostic section has tightened considerably. You now need both clinical assessment and objective imaging confirmation before committing to most pharmacologic interventions. BNP and NT-proBNP remain useful, but the guidelines explicitly note that obesity can suppress BNP levels by roughly 50 percent, leading to false reassurance. I've seen this trip up cardiologists who weren't accounting for body mass index when interpreting labs. Echocardiography is no longer optional for initial workup. You need at minimum an ejection fraction measurement, left ventricular geometry assessment, and valvular evaluation. The guidelines specify that if the initial echo is technically inadequate, you should proceed to cardiac MRI or contrast echocardiography rather than proceeding with treatment decisions based on uncertain data.
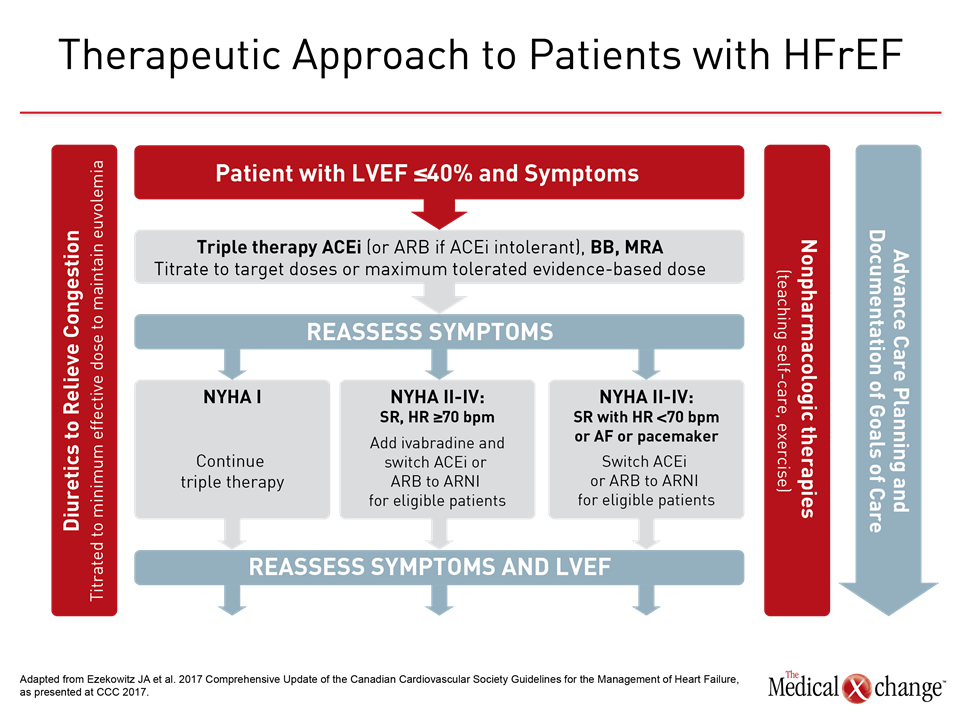
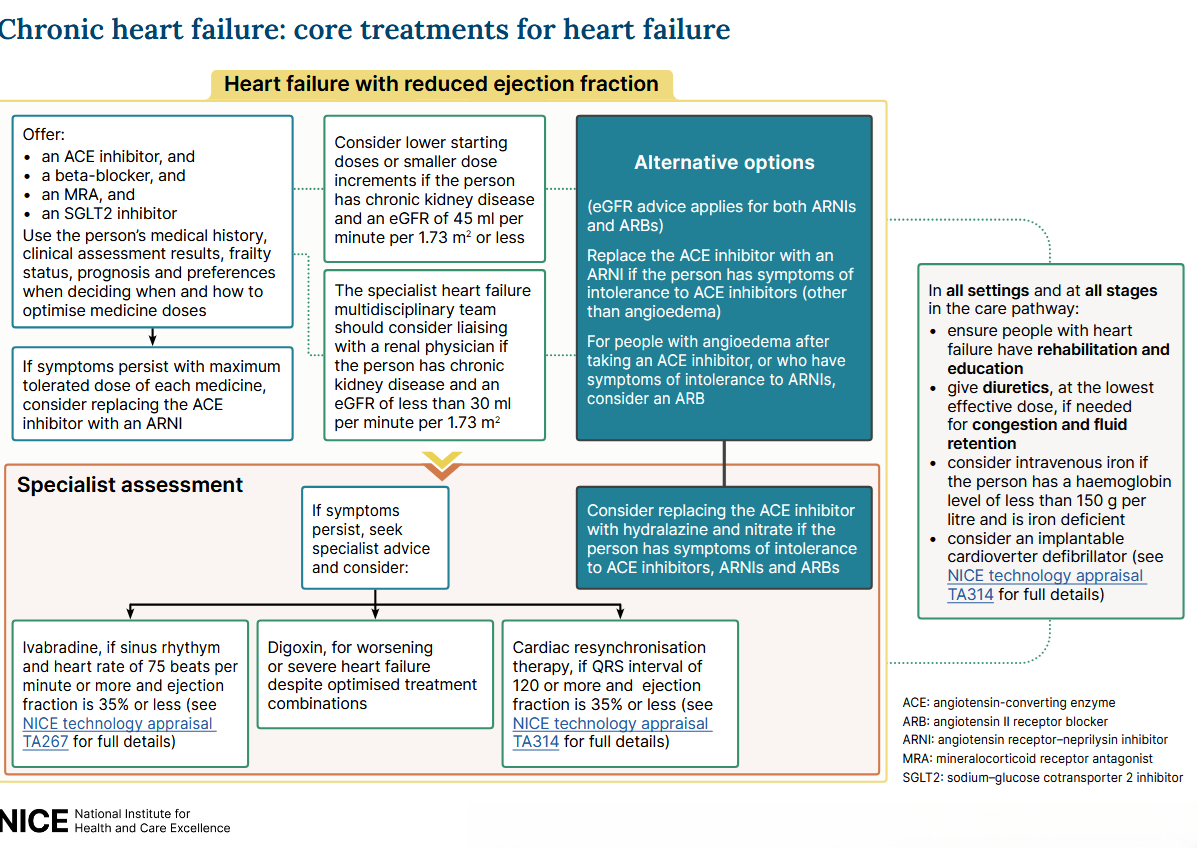
Pharmacotherapy represents the largest section and the most frequent source of confusion. The cornerstone HFrEF treatment now includes four pillars: beta-blockers proven to reduce mortality (carvedilol, metoprolol succinate, bisoprolol), ARNI therapy with sacubitril/valsartan, mineralocorticoid receptor antagonists (spironolactone or eplerenone), and SGLT2 inhibitors (dapagliflozin or empagliflozin). The sequencing matters less than most clinicians assume. Recent trials suggest you can initiate all four simultaneously in stable patients rather than the traditional stepwise approach, which typically cuts initiation time from three to four months down to about two weeks. The catch is monitoring. Starting all four at once means watching potassium, creatinine, and blood pressure every two weeks for the first month. If you skip that monitoring schedule, you'll miss hyperkalemia or acute kidney injury until it becomes clinically apparent, which is usually too late to prevent damage. The ARNI section deserves special attention because there are still significant misunderstandings about it. You must stop the ACE inhibitor or ARB for at least 36 hours before starting sacubitril/valsartan due to angioedema risk. I've watched resident physicians skip this washout period because the patient was already on lisinopril and the transition felt urgent. The angioedema rate isn't high, maybe 2 to 3 percent, but when it happens it's unpredictable and can be life-threatening. Always verify the washout period before writing the order. The starting dose is 24/26 mg twice daily for patients who were previously on ACE inhibitor or ARB therapy, and 49/51 mg twice daily for patients who were treatment-naive or were on lower-dose ARB. You uptitrate every two to four weeks based on tolerance. Blood pressure monitoring is essential during this period. For HFpEF, the landscape changed dramatically with the 2022 guidelines. SGLT2 inhibitors are now recommended as a Class 2a suggestion specifically for HFpEF patients to reduce hospitalizations. This was a significant departure from previous guidelines that offered little pharmacologic direction for this population. The EMPEROR-Preserved and DELIVER trials provided the evidence, showing roughly a 20 percent relative risk reduction in cardiovascular hospitalization or death. But the absolute benefit is modest, and the guidelines acknowledge this. You should counsel patients honestly about what to expect. The medication won't reverse underlying diastolic dysfunction or eliminate symptoms entirely. It reduces the likelihood of another hospital admission, which is a meaningful outcome but not a cure.
I encountered a problematic edge case last year with a 68-year-old male who had HFrEF, atrial fibrillation, and stage 4 chronic kidney disease with an eGFR of 28. The guidelines recommend SGLT2 inhibitors for HFrEF regardless of diabetes status, but the prescribing information and trial data for dapagliflozin and empagliflozin historically excluded patients below eGFR 30. The guidelines themselves acknowledge this gap and state that use in advanced CKD may be considered based on clinical judgment. I initiated empagliflozin 10 mg daily with close monitoring of renal function and electrolytes. His eGFR dipped to 24 within the first month, which triggered a hold. After adjusting diuretics and optimizing volume status, it recovered to 27. He remained on the medication for six months before I discontinued it due to persistent renal decline. The literature on this scenario is sparse, and the guidelines don't provide clear enough direction for end-stage renal disease. If you're working with similar patients, consult nephrology early and document your clinical reasoning thoroughly. Device therapy recommendations are another area where the guidelines diverge from common practice assumptions. ICD implantation for primary prevention requires an LVEF of 35 percent or less despite at least three months of optimal medical therapy. That three-month wait is critical. Some trials showed early harm with device implantation before patients had adequate time to respond to guideline-directed medical therapy. Don't rush this. If the patient's EF improves to above 35 percent on medications alone, the ICD indication disappears entirely. Cardiac resynchronization therapy follows similar logic but has additional criteria regarding QRS duration and morphology. LBBB with QRS greater than 150 ms carries the strongest evidence. Patients with non-LBBB patterns or narrower QRS complexes derive significantly less benefit, and the guidelines reflect this with weaker recommendations. Advanced heart failure referral criteria deserve more attention than they typically receive. The guidelines recommend considering heart transplant or durable mechanical circulatory support evaluation when patients experience recurrent hospitalizations despite optimized therapy, declining renal function, worsening hepatic congestion, or persistent functional limitations. The COAPT and MITRA-FR trials refined our understanding of mitral regurgitation management in this context. Not every severe secondary MR case benefits from transcatheter intervention. Patient selection based on left ventricular size and right ventricular function separates responders from non-responders. I once referred a patient too late because I was waiting for the EF to drop further before considering advanced therapies. She died from progressive right heart failure while waiting. The guidelines don't give exact EF thresholds for referral timing, which is one of their frustrating ambiguities. When in doubt, refer earlier rather than later. Evaluation teams would rather assess a patient who doesn't need advanced intervention than discover too late that one was needed.
Get the Full Details
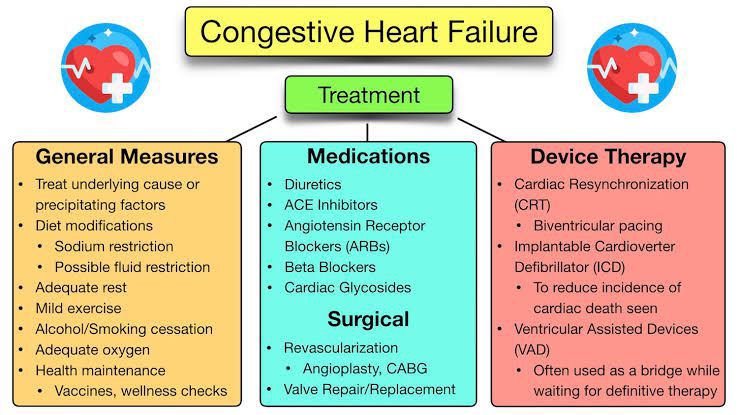
Monitoring and follow-up protocols are where compliance with guidelines tends to fall apart in routine practice. The guidelines recommend follow-up within one to two weeks after any hospital discharge for heart failure, and within one to two weeks after initiating or uptitrating major therapeutic agents. Most clinics structure their post-discharge visits around three weeks, which misses the window where early readmission risks are highest. Readmission rates drop significantly when the first post-discharge contact happens within the recommended timeframe. The guidelines also specify laboratory monitoring schedules: basic metabolic panel and magnesium within one week of starting or changing doses of ACE inhibitors, ARBs, ARNIs, or MRAs, and again at one month and every three to six months thereafter. Hemoglobin A1c should be checked annually for patients on SGLT2 inhibitors, though the frequency isn't as critical as ensuring it gets done at all. I've lost track of how many patients I've seen whose SGLT2 inhibitor was started without anyone ever documenting a baseline A1c. Lifestyle and dietary counseling remain part of the guidelines but lack the precision of pharmacologic recommendations. Sodium restriction to less than 2 grams per day is advised, though the evidence for this specific threshold is weaker than most clinicians assume. The REAL-ChF trial found that strict sodium restriction in patients with chronic heart failure and reduced ejection fraction actually increased natriuretic peptide levels and wasn't associated with improved outcomes. The guidelines acknowledge this nuance but still recommend moderation rather than strict restriction for most patients. Fluid restriction is more clearly indicated for patients with serum sodium below 130 mmol/L. I tell my patients to avoid adding salt at the table and to read labels rather than aiming for an arbitrary gram count that's nearly impossible to track accurately in daily life. palliative care integration is addressed in the guidelines for the first time with notable explicitness. Advanced heart failure patients who aren't candidates for transplant or mechanical support should have goals-of-care discussions early in the disease trajectory, not during acute crises. The guidelines classify this as a Class 1 recommendation, which is rare for non-interventional advice. Early palliative care involvement has been shown in randomized trials to improve quality of life and sometimes even survival in heart failure populations. Hospice referral criteria include a 6-month prognosis with typical disease trajectory, recurrent hospitalizations, declining functional status, and comorbid conditions that limit life expectancy. Many clinicians hesitate to introduce these conversations because they feel premature or defeatist. The guidelines don't frame it that way. They present it as standard comprehensive care.
The practical limitations of these guidelines are worth stating plainly. They cannot account for every comorbidity combination, drug interaction, or social determinant of health that affects treatment adherence. A patient who can't afford sacubitril/valsartan or can't manage a twice-daily dosing schedule will get different outcomes regardless of what the guideline recommends. Formulary restrictions, prior authorization delays, and medication costs create gaps between guideline-recommended therapy and what patients actually receive. I've seen patients on three different heart failure medications switched off a preferred agent because insurance approved a less effective alternative. The guidelines don't address these systemic barriers, and clinicians bear the burden of navigating them. Another structural limitation is that the guidelines lag behind emerging evidence. The 2022 version incorporated trials published through 2021. New data on Finerenone, vericiguat, and sotatercept continues to accumulate. The guidelines themselves note that periodic updates are necessary as evidence evolves. Waiting for the next major guideline revision shouldn't delay adopting well-supported new therapies when they become available in clinical practice. Conversely, adopting every new drug immediately without waiting for guideline endorsement can expose patients to therapies with incomplete safety profiles. Balancing this tension requires clinical judgment that no document can fully automate. Accessing the full guidelines: The complete AHA/ACC/HFSA 2022 Guideline for the Management of Heart Failure is publicly available through the American Heart Association website, the Journal of the American College of Cardiology, and the Heart Failure Society of America. Most institutional libraries provide free access to the full text. A condensed version appears in the Circulation journal. I recommend reading the full document rather than relying on summary articles, because the evidence tables and conditional recommendations contain important nuances that summaries routinely omit.
Implementation checklist for clinicians: verify ejection fraction with adequate imaging before initiating pillar therapy, ensure 36-hour washout before ARNI transition, establish a monitoring schedule for renal function and electrolytes before starting any new medication class, arrange early follow-up within 14 days of discharge or therapy change, consider advanced heart failure referral before patients reach crisis points, and integrate palliative care discussion for eligible patients. These steps align with the current guideline framework and address the most common points where clinical practice deviates from recommended standards.