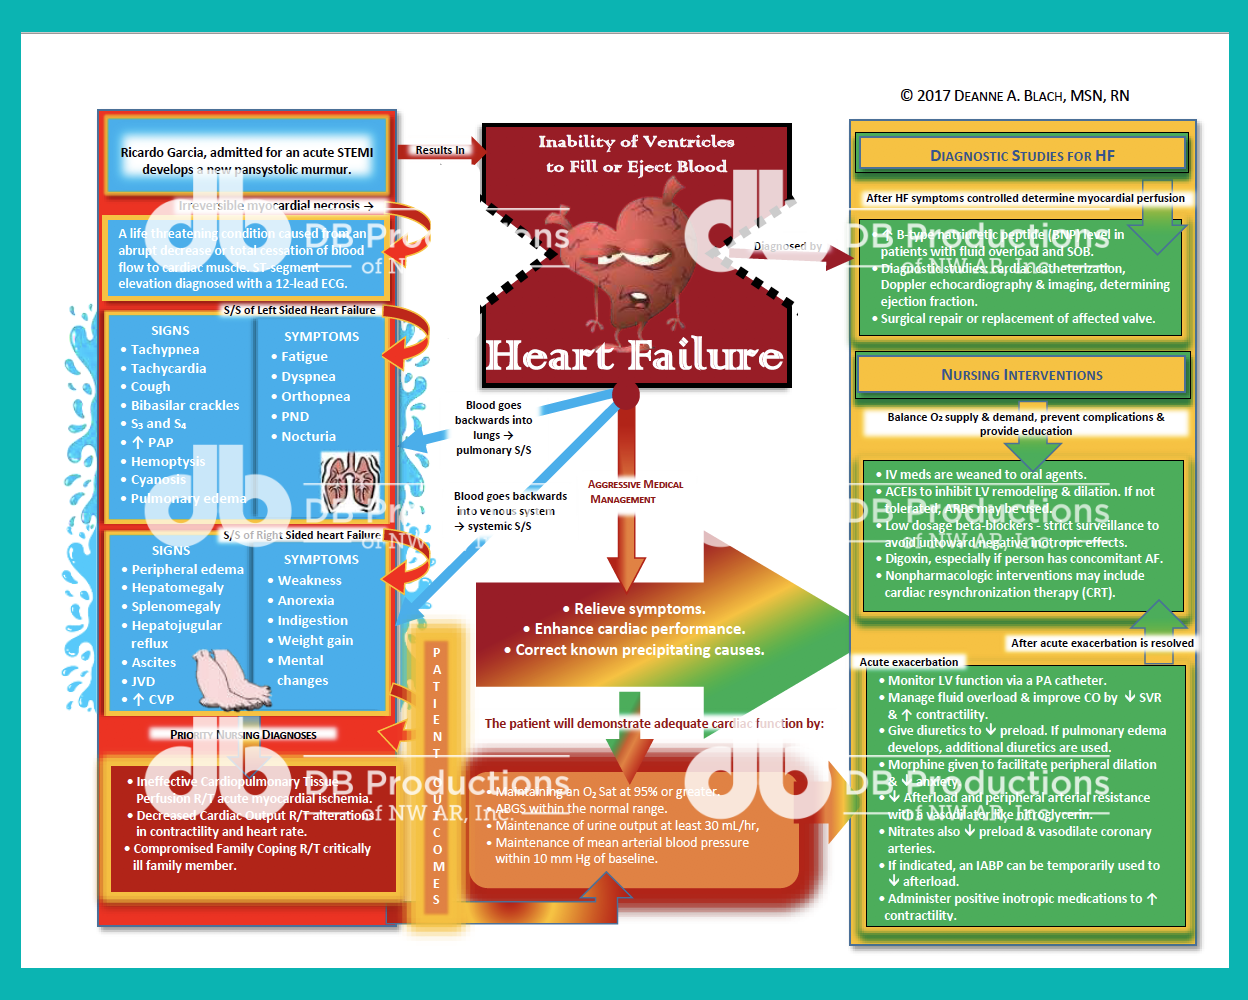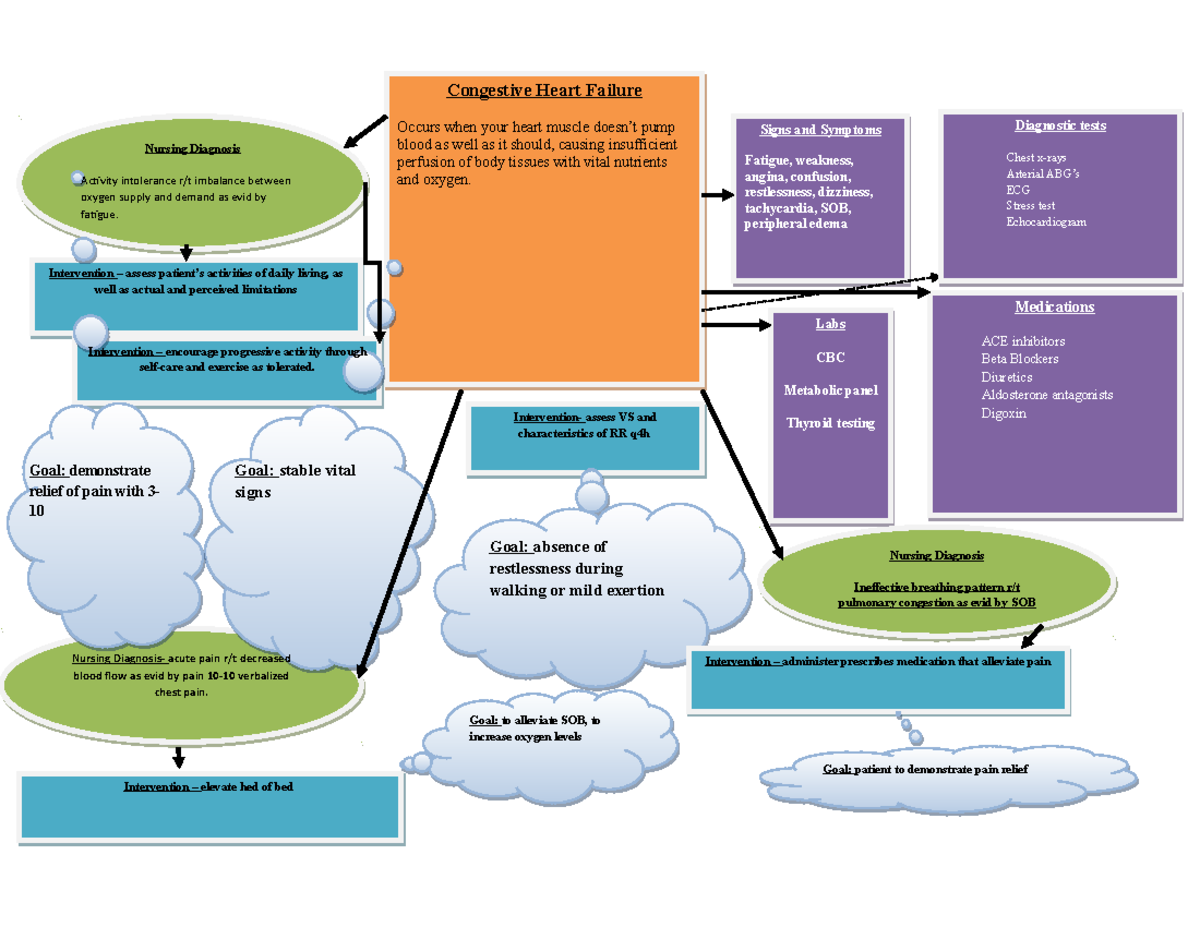
So you need a CHF concept map. Here is how to actually build one that works.
A concept map for Congestive Heart Failure is just a visual way of connecting the pathophysiology to the clinical picture. You start with the core problem—reduced cardiac output—and branch out from there into causes, compensatory mechanisms, symptoms, and treatments. That is the basic framework. Most people overcomplicate it by trying to include every possible detail on a single page. It stops being useful after about a year of nursing school when you are dealing with patients who don't fit neatly into textbook boxes. I built my first CHF concept map around 2018 for a pharmacology rotation. I used a blank whiteboard and colored markers. The red ink was for everything related to volume overload, blue for perfusion issues, black for the compensatory pathways. The visual separation mattered more than I expected. When you are studying for shelf exams, color coding lets you scan a full page in about thirty seconds and spot gaps in your understanding immediately. It is not a new idea, but most study guides skip over the physical layout entirely. The central node should be heart failure itself, but the branching structure depends on what you are trying to learn. If you are in a pathophysiology course, start with ventricular dysfunction and trace forward to RAAS activation, sympathetic nervous system stimulation, and fluid retention. If you are prepping for clinical rotations, flip it around. Start with the presenting symptoms—dyspnea, orthopnea, peripheral edema—and work backward to figure out which mechanism is driving each one. Both approaches are valid. They serve different purposes.
Here is where beginners consistently mess up. They draw lines between concepts without labeling the relationships. A line from "fluid retention" to "edema" means nothing unless you write "causes" or "results in" on that connector. The links are the actual knowledge. Without them, you just have a bunch of terms floating in space. I spent an entire night rewriting a map I had already drawn because I hadn't bothered with labeled connectors the first time. Took twenty minutes to fix once I realized the problem. For treatment branches, keep the categorization tight. Diuretics, ACE inhibitors, beta blockers, ARNIs, aldosterone antagonists, SGLT2 inhibitors—that is the standard pharmacological toolkit. Don't just list drug names. Write what each class does and why it matters in this specific context. Furosemide reduces preload. ACE inhibitors reduce afterload. Entresto blocks natriuretic peptide breakdown. That level of specificity is what turns a memorization aid into a reasoning tool. I ran into a specific edge case during my third year that nearly broke my entire system. A patient came in with what looked like typical left-sided CHF—bilateral crackles, orthopnea, elevated BNP—but the echo showed preserved ejection fraction. My original map was built entirely around systolic dysfunction. Every branch pointed toward reduced contractility. I had to pause and add an entirely separate section for HFpEF, which has a completely different emphasis on diastolic stiffness, atrial fibrillation prevalence, and hypertension as the primary driver rather than ischemic damage. I ended up creating a parallel branching structure that split off from the main node and only crossed back at the treatment level, where guidelines converge on diuresis and comorbidity management. It made the map more complex but also more clinically accurate. Takes about ten extra minutes to maintain those cross-branches.
Tools matter less than you would think. I have seen people use CmapTools, MindMeister, Lucidchart, hand-drawn sketches on legal pads, and actual whiteboards. The output quality depends on the person, not the software. I recommend starting on paper if you are doing this for personal study. Writing things by hand forces you to process the information differently than typing. Once the map is stable and you want a shareable version, digitizing it is straightforward. Most platforms let you export to PDF or image in one click. The biggest limitation of any concept map for CHF is that heart failure is inherently dynamic. Your map will be static. A patient can shift from compensated to decompensated status within hours. The RAAS cascade isn't always the dominant pathway—sometimes it's primarily sympathetic overdrive or renal sodium handling gone wrong. Your map suggests a linear model when the reality is far messier. I learned this the hard way when a patient on my cardiology rotation had severely elevated BNP but minimal structural changes on echo, and the entire framework I had built around pump failure didn't explain their presentation at all. It turned out to be high-output heart failure secondary to severe anemia. Worth adding a note about non-standard presentations somewhere on the map, even if it feels like clutter. If you are doing this for a class assignment, check the rubric before you invest time. Some professors want hierarchical organization. Others just want to see that you can identify and connect the right concepts. A messy but accurate map beats a clean but shallow one every time. I've seen students lose points not because their map was wrong, but because it was too simplistic and missed the bidirectional relationships between, say, renal function and diuretic response.
Get the Full Details
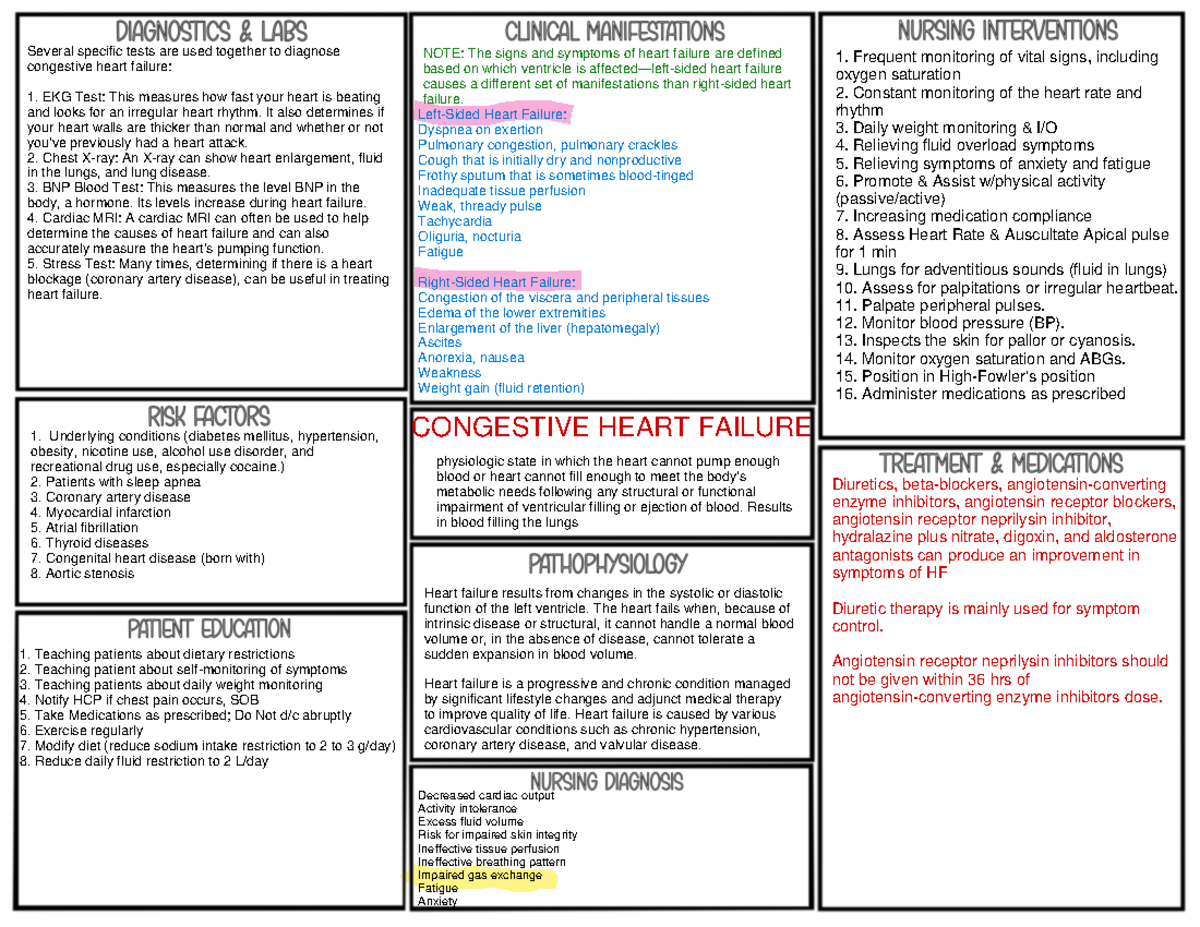
One thing that isn't obvious: update your map as you go through clinical rotations. The version you build in week one is not the version you need by week eight. Add the complications you actually encounter. Pulmonary hypertension as a consequence of left heart disease. Cardiorenal syndrome. The relationship between diuretic resistance and gut edema. These aren't footnote details. They are the things that actually come up in case discussions and affect real treatment decisions. You don't need to make it look pretty. I once had a TA tell me my map looked like "a spider had a stroke on a napkin." It was also the most complete one in the room and got full marks. Function over aesthetics every time with these things.