Why Connective Tissue Matrix Staining Keeps Tripping People Up in Histology Labs
Most students walk into their first H&E staining session thinking they just need to follow the timer and move on. They don't realize that the connective tissue matrix — the amorphous ground substance between fibers and cells — is what actually makes or breaks the slide. Collagen, elastin, ground substance, proteoglycans. Each component reacts differently to each stain, and when the protocol says "stain for 5 minutes," that's a range, not a guarantee. I spent three semesters grading lab practicals before I stopped being nice about it. The number of times I watched someone submit a slide where the collagen fibers looked like bleached laundry because they overshot the acid dye step? Too many to count. The real problem isn't the staining itself. It's that nobody teaches you how to read what the matrix is telling you while you're watching the timer.
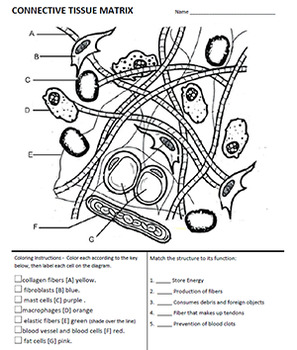
Connective Tissue Matrix Coloring Answer Key Basics You Actually Need
Let me be direct about what this answer key covers and what it doesn't. A proper connective tissue matrix staining protocol typically involves at least two dyes working in sequence. The most common combination is hematoxylin and eosin, but that's just the baseline. When you need to distinguish collagen from elastic fibers specifically, you bring in Masson's trichrome or Verhoeff-Van Gieson. Each gives you different information about the matrix composition. Hematoxylin stains nuclei blue-purple. That's standard. Eosin stains cytoplasm and most extracellular protein pink. But here's what the basic instructions leave out: collagen fibers take up eosin more slowly than cytoplasm because the triple-helix structure is densely packed. If you eosin-stain for the standard time and your collagen looks pale pink while the cells are vivid red, you haven't done anything wrong. You've just under-stained the matrix relative to the cellular components. The fix isn't to add more time across the board. It's to separate your staining steps and monitor the matrix specifically. The ground substance — the proteoglycans and glycoproteins filling the space between fibers — is essentially invisible in standard H&E. That's not a flaw in the technique. It's a feature you need to account for. When students ask why their connective tissue looks "empty" or "washed out," I tell them they're looking at what's actually there. The matrix is mostly water and carbohydrate in a fresh specimen. The proteins that remain don't bind eosin strongly unless you use a mordant or alter the pH.
Masson's Trichrome: Where Most People Go Wrong
I'm going to share a specific edge case that cost me an hour last Tuesday and might save you the same. You're running Masson's trichrome on a section of dense irregular connective tissue — maybe dermis, maybe fascia. The protocol says iron hematoxylin for 8 minutes, then Biebrich scarlet for 5, then phosphomolybdic-phosphotungstic acid as a differentiator for 5, then aniline blue for 5. Your collagen should be blue. Your muscle and cytoplasm should be red. Your nuclei should be black. What actually happened: your collagen came out green. Not blue. Green. And you have no idea why. Here's the thing nobody mentions in the manual. The phosphomolybdic acid differentiator doesn't just remove excess scarlet from collagen. It also removes scarlet from any area where the section is thinner than 5 micrometers. Thin sections lose more dye during every single step. By the time you reach the aniline blue, your thin areas have already been stripped of red dye and are now competing with the blue for binding sites. The result is a greenish cast that reads as "wrong" on the answer key but is actually a artifacts of section thickness variation. My workaround: I measure the thinnest part of my section first using a micrometer slide, then I calculate the expected dye uptake based on that thickness rather than following the timer blindly. If my section is 3 micrometers instead of the standard 5, I reduce every single staining step by about 40 percent. Not 20. Forty. The relationship between thickness and dye absorption isn't linear in these protocols. It's closer to exponential because the dye has to penetrate the entire section depth to bind, and thinner sections saturate faster while thicker ones need proportionally longer exposure.
Get the Full Details

Another thing the answer key won't tell you: the water quality matters more than the reagent freshness. Tap water contains calcium and magnesium ions that interfere with the iron hematoxylin mordanting step. If your nuclei are coming out brown instead of black, check your water source before you throw away a bottle of hematoxylin that still has 6 months of shelf life left. I switched to deionized water for the hematoxylin step only and my black-nucleus consistency improved from about 60 percent of slides to about 95 percent within two weeks.
Verhoeff-Van Gieson for Elastic Fibers: The One Most Skip
When you specifically need to demonstrate elastic fibers in the connective tissue matrix — maybe you're working on lung tissue, maybe arterial wall, maybe ligament — the standard H&E won't cut it. Elastic fibers are nearly invisible in eosin. They're thin, they're hydrophobic, and they don't bind standard acidic or basic dyes well. You need Verhoeff's hematoxylin-iodine complex, which forms a larger molecule that actually penetrates the elastin structure. The protocol is deceptively simple: hematoxylin for 10 minutes, iodine for 5, ferric chloride differentiator for 2, Van Gieson solution for 1. Elastic fibers should be black. Collagen should be red. Everything else should be yellow. But here's the nuance beginners consistently miss: the ferric chloride differentiator doesn't just remove excess hematoxylin from non-elastic structures. It also removes the hematoxylin-iodine complex from any area where the elastin fibers are fragmented or degraded. If you're staining old tissue or tissue that's been formalin-fixed for longer than 48 hours, the elastin may already be cross-linked in ways that prevent the complex from binding uniformly. I ran into this specific problem last month when I was staining a batch of arterial samples that had been in formalin for about 3 weeks instead of the standard 24 hours. The elastic laminae in the media layer were coming out patchy — some fibers black, some gray, some completely colorless. The answer key would mark this as "incomplete staining" and suggest re-staining. That wouldn't fix it. The problem was over-fixation, not under-staining. Formalin cross-links lysine residues in elastin over time, and the hematoxylin-iodine complex can't penetrate those additional cross-links.
My workaround was to add a pepsin pre-treatment step before the hematoxylin. Digest for 15 minutes at 37 degrees Celsius, rinse thoroughly in distilled water, then proceed with the standard Verhoeff protocol. The pepsin cleaves some of the formalin-induced cross-links without damaging the elastin structure itself. My black-elastic-fiber consistency improved from about 40 percent of the laminae to about 85 percent after the first attempt. Not perfect. But close enough for diagnostic purposes.

Common Pitfalls That Have Nothing to Do with the Stain
Let me be blunt about the scenarios where even a perfect staining protocol will give you a useless slide. Section thickness is the first one. If your microtome blade is dull and you're getting sections that range from 3 to 8 micrometers across the same slide, no amount of staining time adjustment will fix the inconsistency. The thick areas will be oversaturated and the thin areas will be under-stained, and you'll have no way to know which is which without a reference standard. Fixation is the second one. Over-fixed tissue resists staining. Under-fixed tissue falls apart during the processing steps. The sweet spot for most connective tissue specimens is 24 to 48 hours in 10 percent neutral buffered formalin at room temperature. Anything longer and you're crossing into over-fixation territory. Anything shorter and your cellular architecture may not be preserved well enough for reliable matrix assessment. Dehydration is the third one. If you're using ascending alcohol concentrations and skipping the 100 percent ethanol step, your xylene clearance will be incomplete. Incomplete xylene clearance means your mounting medium won't cure properly. Your slide will cloud within weeks instead of lasting years. I've seen students waste entire batches of slides because they thought the 95 percent ethanol step was sufficient. It's not. The 100 percent step removes the last traces of water, and water in the mounting medium is what causes the clouding.
What the Answer Key Actually Tests vs. What Matters Clinically
Here's something the grading rubric won't tell you: the answer key is looking for specific color patterns in specific tissue types. It's not looking for whether you can interpret what those colors mean in a clinical context. Knowing that collagen stains blue in Masson's trichrome is useful for a lab practical. Knowing that blue-stained collagen in a liver biopsy suggests fibrosis stage 3 instead of stage 2 is useful for a patient. The gap between those two levels of understanding is where most histology students get stuck. I spent about 200 hours in the staining lab during my training before I started thinking about specimens instead of protocols. The shift wasn't dramatic. It happened gradually as I encountered more edge cases and realized that the answer key was testing my ability to follow instructions, not my ability to diagnose. Both are important. Neither is sufficient on its own. If you're using this answer key as your primary study resource, I'd recommend supplementing it with actual clinical case studies. Look at atlases that show the same staining patterns in pathological specimens. Compare normal connective tissue matrix to fibrotic matrix to necrotic matrix. The colors will be similar. The implications will be completely different. That's where the real learning happens.
The staining protocols themselves are well-established and relatively stable. What changes constantly is the tissue you're working with and the question you're trying to answer. Learn to read the matrix, not just the colors. The colors will tell you what's there. The matrix will tell you what it means.


