The reality of getting credentialed for CIMT
CIMT certification isn't a single program. It's a scattered landscape of workshops, university courses, and professional organization endorsements, and most people don't realize how much that matters until they're trying to get reimbursed or credentialed by an employer. The therapy itself is well established — restraint of the less-affected upper extremity combined with intensive task-specific training for the affected side — but the credentialing pathway varies enough that it creates real confusion in practice. I spent about two years navigating this for a clinic that wanted to implement CIMT as a standard post-stroke protocol. What I learned is that the certificate you walk away with from any given workshop is only as valuable as the specific competencies it claims to cover and whether the issuing body is recognized by the payers and institutions you actually deal with.
How to actually get your Constraint Induced Movement Therapy Certification
The most commonly referenced training originates from the work of Taubenberger and colleagues building on Edward Taub's original research. The standard workshop format runs approximately 16 hours split across two or three days and covers restraint device fitting, dose calculation, shaper techniques, and outcome measurement using tools like the Wolf Motor Function Test and the Action Research Arm Test. Several professional organizations offer their own endorsement tracks. The Academy of Neurologic Physical Therapy has a certification pathway that requires completion of an approved educational module plus documented clinical hours and a case study review. The American Occupational Therapy Association maintains a directory of recognized CIMT training providers. Neither one controls who actually delivers competent care — they control who gets on the list that hospital credentialing committees accept. Here is the part that nobody mentions in the marketing materials: many of these programs assume you already know basic stroke rehabilitation principles. If you are a new therapist or coming from a different specialty, the workshop moves fast. I attended a course where they spent roughly forty-five minutes covering upper extremity spasticity management implications for constraint compliance and I left realizing I had missed maybe fifteen percent of what was said because the instructor assumed we all knew the Bobath concepts being referenced. I recommended the clinic cover the prerequisite reading list before anyone attended the live session. That saved us from looking lost in front of our attending physicians.
The actual enrollment process is straightforward in theory. Identify a recognized provider, register, attend the full contact hours, complete any required post-course assessment, and submit documentation to whichever credentialing body you need. In practice, the bottleneck is usually the case study requirement. Most programs want you to submit two to three documented patient cases showing proper device fitting, dose progression, and outcome measurement. This is where things get tricky because not all cases are created equal. I ran into this when a colleague submitted a case where the patient's constraint compliance was below seventy percent due to unaddressed sensory neglect on the constrained side. The reviewer rejected it outright because the documentation didn't show any modification to the restraint strategy or any attempt to address the barrier. Compliance rates below eighty percent essentially invalidate the CIMT protocol according to the published literature, so a case with poor compliance but no documented problem-solving gets flagged. We ended up redoing three cases with detailed rationales for the interventions we adjusted. Took about six hours total but it made the difference between approval and a request for resubmission.
Get the Full Details
What the training actually covers and what it leaves out
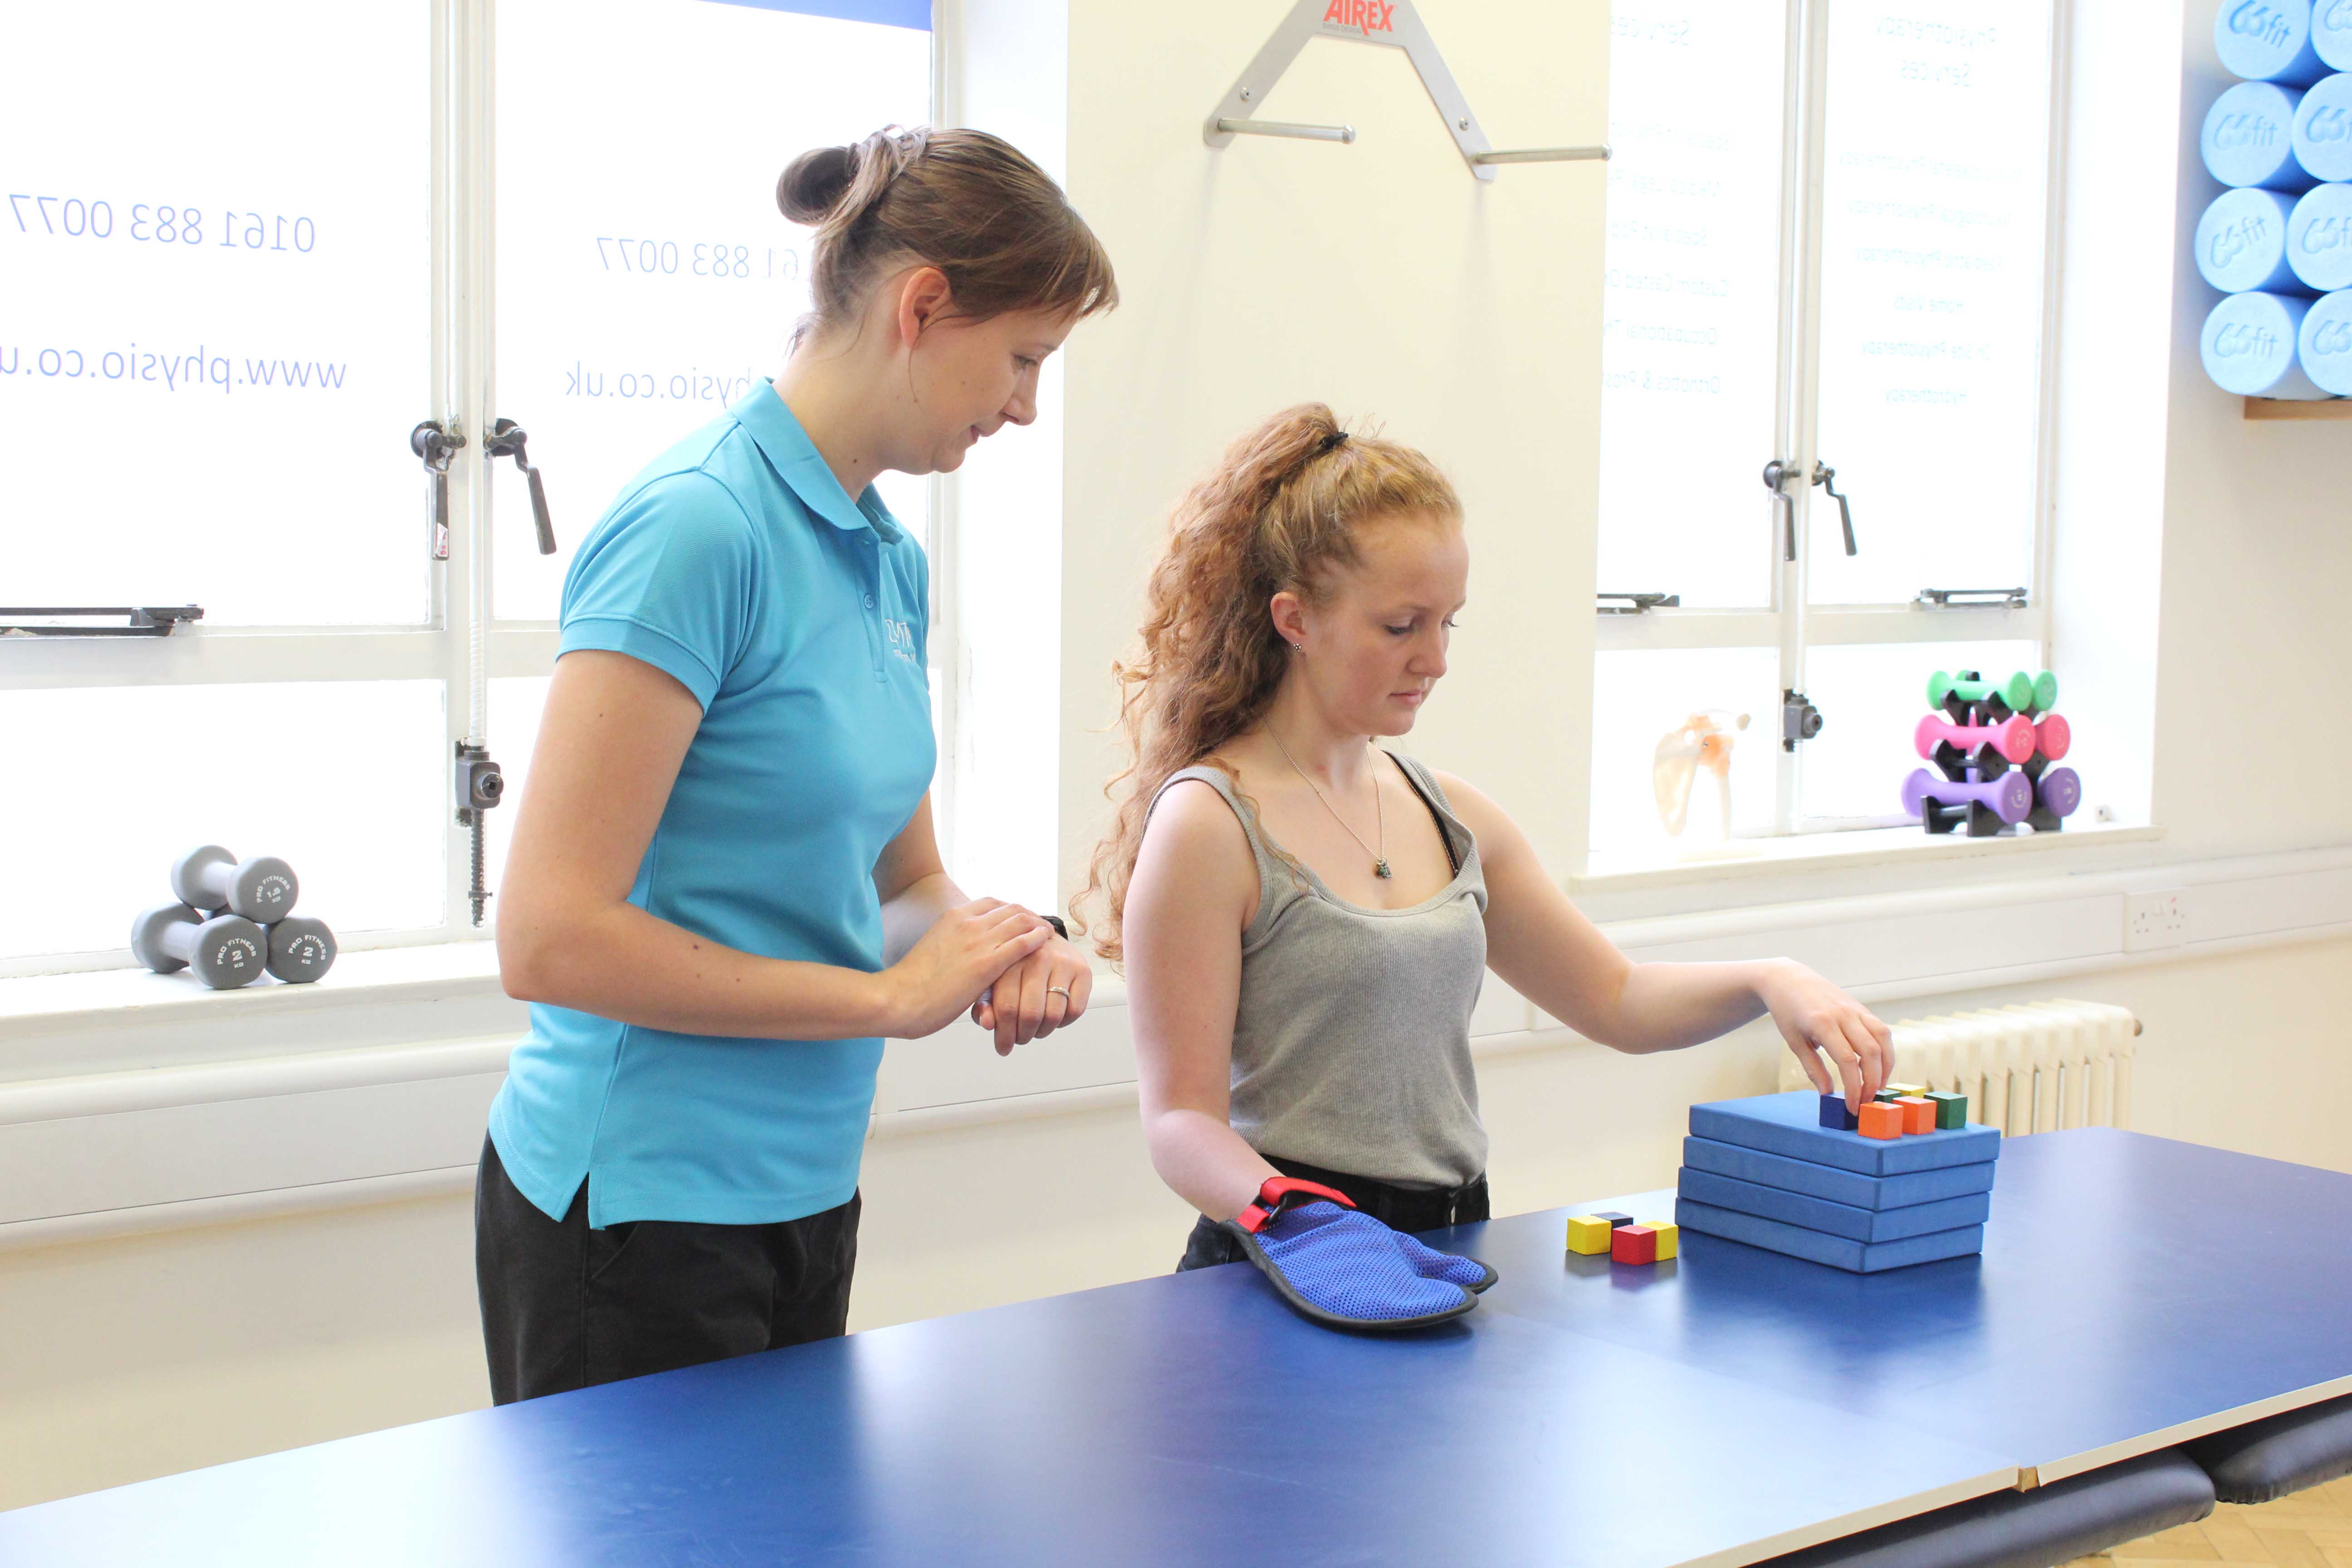
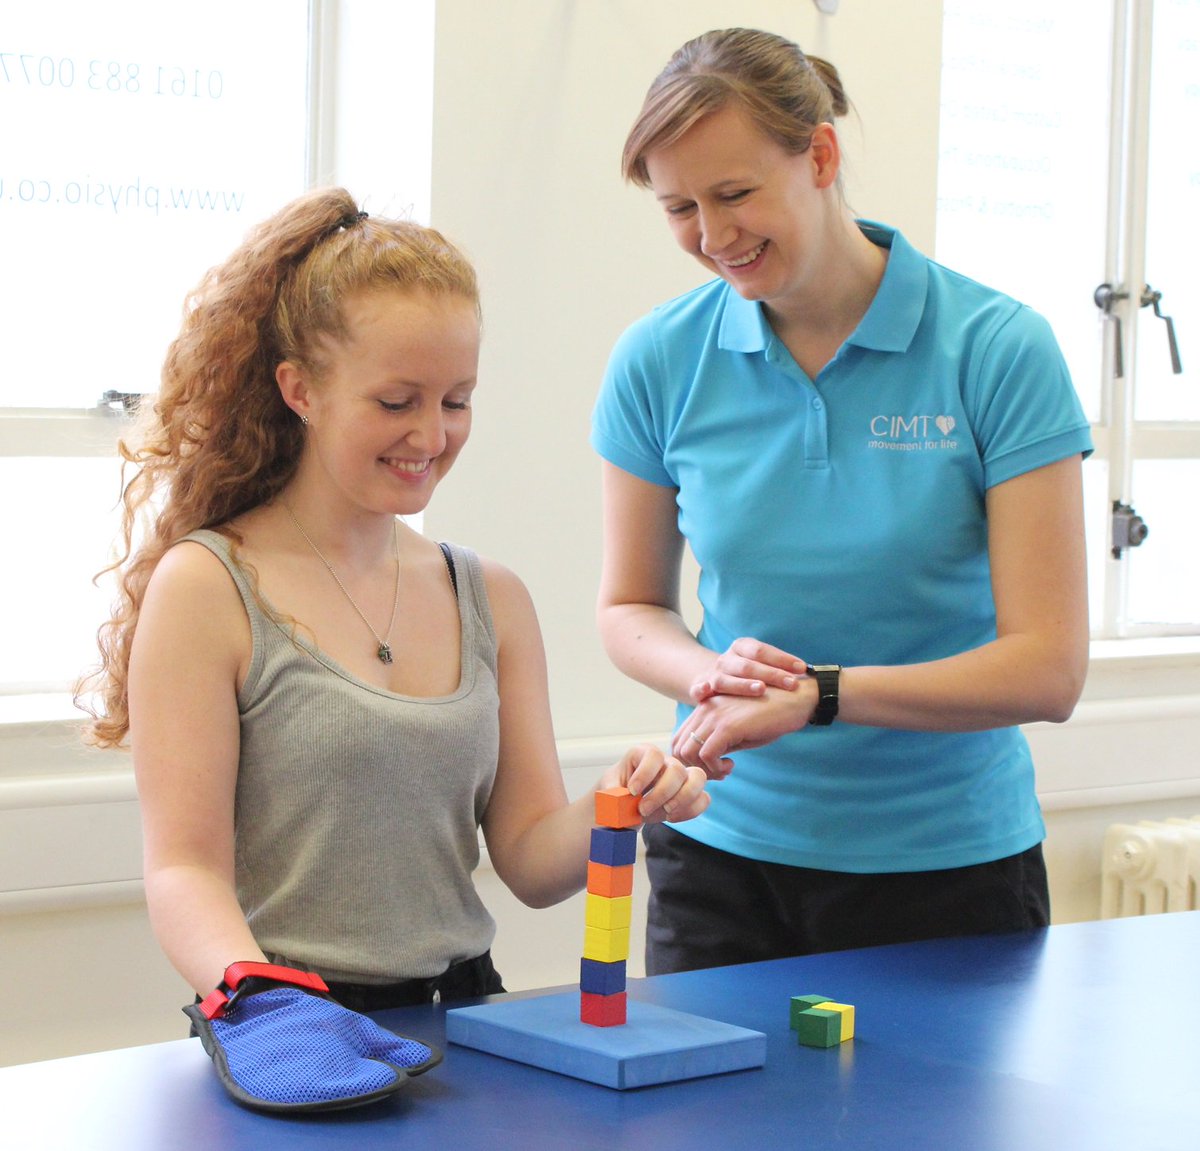
A proper CIMT program teaches you to calculate dosage using the constraint-wearing hours multiplied by the focused practice hours. The typical protocol calls for six to eight hours of daily constraint use over two to three weeks. You learn to select the right restraint device — and this is more nuanced than it sounds. A simple sock or mitten works for some patients. A purpose-built arm cast or commercial restraint device is needed for others. The choice depends on the patient's cognitive status, ability to understand the rationale, and level of cooperation. You also learn the shaper technique, which is the graduated transition from full constraint to more natural use of the affected limb. This is where a lot of practitioners cut corners because it requires additional clinical decision-making. I've seen therapists skip the shaping phase entirely and just remove the constraint after the treatment period ends. That's not CIMT. That's just arm restraint with therapy exercises, and the evidence base doesn't support it. Outcome measurement is another area where consistency matters. The WMFT and ARAT are the standard tools but they require calibration. Two different therapists can score the same patient differently if they haven't gone through inter-rater reliability training together. The accredited programs usually build in some form of video scoring exercise, but the quality varies. I found that watching the instructional videos twice and practicing scoring on recorded sessions from our own clinic beforehand made a noticeable difference in my inter-rater agreement with colleagues.
One thing most programs don't adequately address is the psychological component. Patients, particularly those with significant stroke deficits, can become deeply frustrated or even depressed when you constrain their good arm. Compliance drops not because of physical barriers but because of emotional resistance. The better trainers build in screening questions for depression and anxiety and provide scripts for patient education. The ones that don't leave you guessing on day three when your patient says they'd rather not wear the constraint anymore.
Where this approach breaks down
CIMT has a narrow evidence window. It works best for patients who have some baseline wrist and finger extension — typically at least grade 3 or better on manual muscle testing. If a patient has severe proximal weakness without distal function, the protocol produces minimal transfer effects. Several studies have looked at modified CIMT protocols for these patients but the results are mixed and the evidence level drops significantly. Don't advertise this as a solution for moderate to severe hemiparesis. It isn't. Insurance reimbursement is another practical limitation. Not all payers cover CIMT as a distinct procedure code. Some fold it into general neurological rehabilitation and reimburse at a lower rate. Others require prior authorization with specific documentation that goes beyond what the certification program teaches you. My clinic spent approximately three weeks figuring out our local Medicare Administrative Contractor's documentation requirements before we could confidently bill for CIMT episodes. That time cost us two potential patients. The time commitment is also a real constraint that the certification materials sometimes minimize. A full CIMT course requires eight to twelve hours of supervised clinical practice, not counting the workshop time. For a busy outpatient therapist, finding that block of time is genuinely difficult. Many of us end up spreading it across several months, which reduces knowledge retention between modules.

There is also the issue of equipment costs. Proper restraint devices range from twenty dollars for basic fabric options to several hundred dollars for commercial systems. Outcome measurement tools require certification in their administration. If your clinic is outfitting multiple therapists, the startup cost is non-trivial and few certification programs include it in the tuition. The credential itself expires. Most issuing bodies require continuing education credits or recertification every two to three years. This isn't unique to CIMT but it is something to factor into your professional development timeline and budget.
Practical next steps
Start by determining which credential matters for your situation. If you need it for hospital privileging, check which providers that hospital's credentials committee recognizes. If you need it for insurance credentialing, check the payer directories. If you're doing this for personal skill development, pick the program with the strongest clinical practicum component regardless of the issuing organization's prestige. Before enrolling, verify that the program covers outcome measurement tool certification as part of the curriculum. Separate certification for the WMFT and ARAT can add significant cost and time if it's not included. Also ask about the case review process — whether it's handled during the workshop or asynchronously afterward, and what happens if your submitted cases don't meet criteria the first time. Build the post-certification plan before you start the course. Identify the patients in your current caseload who would be appropriate candidates. Get the equipment ordered. Schedule the prerequisite reading. The gap between finishing the certification and actually implementing CIMT in your clinic is where most people lose momentum. Keep the pipeline moving while the material is fresh.



