Working with Context in OT: A Practical Guide
Understanding Contextual Factors Occupational Therapy
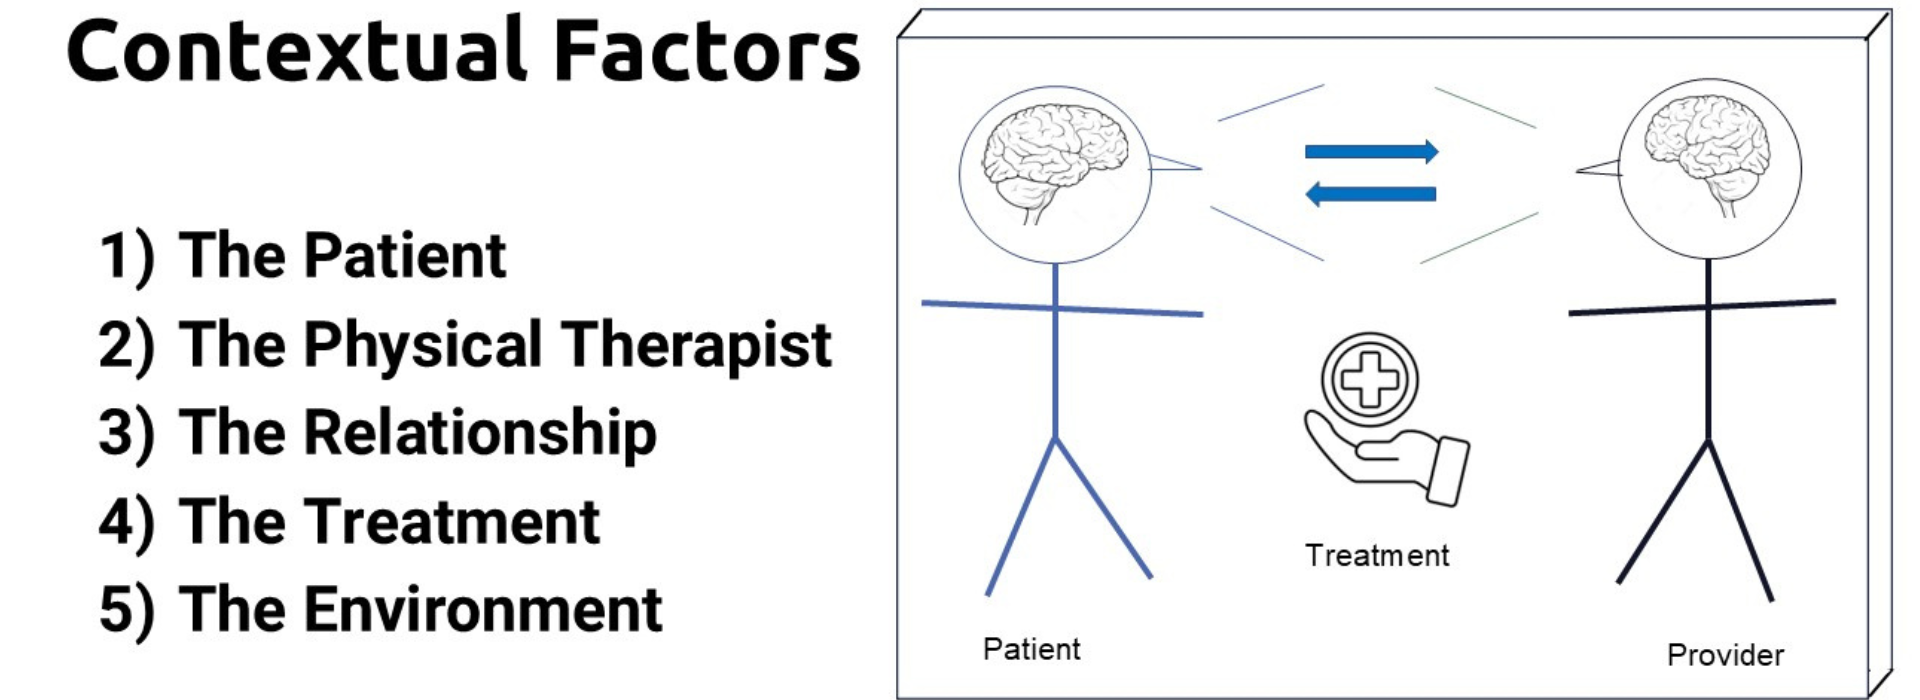
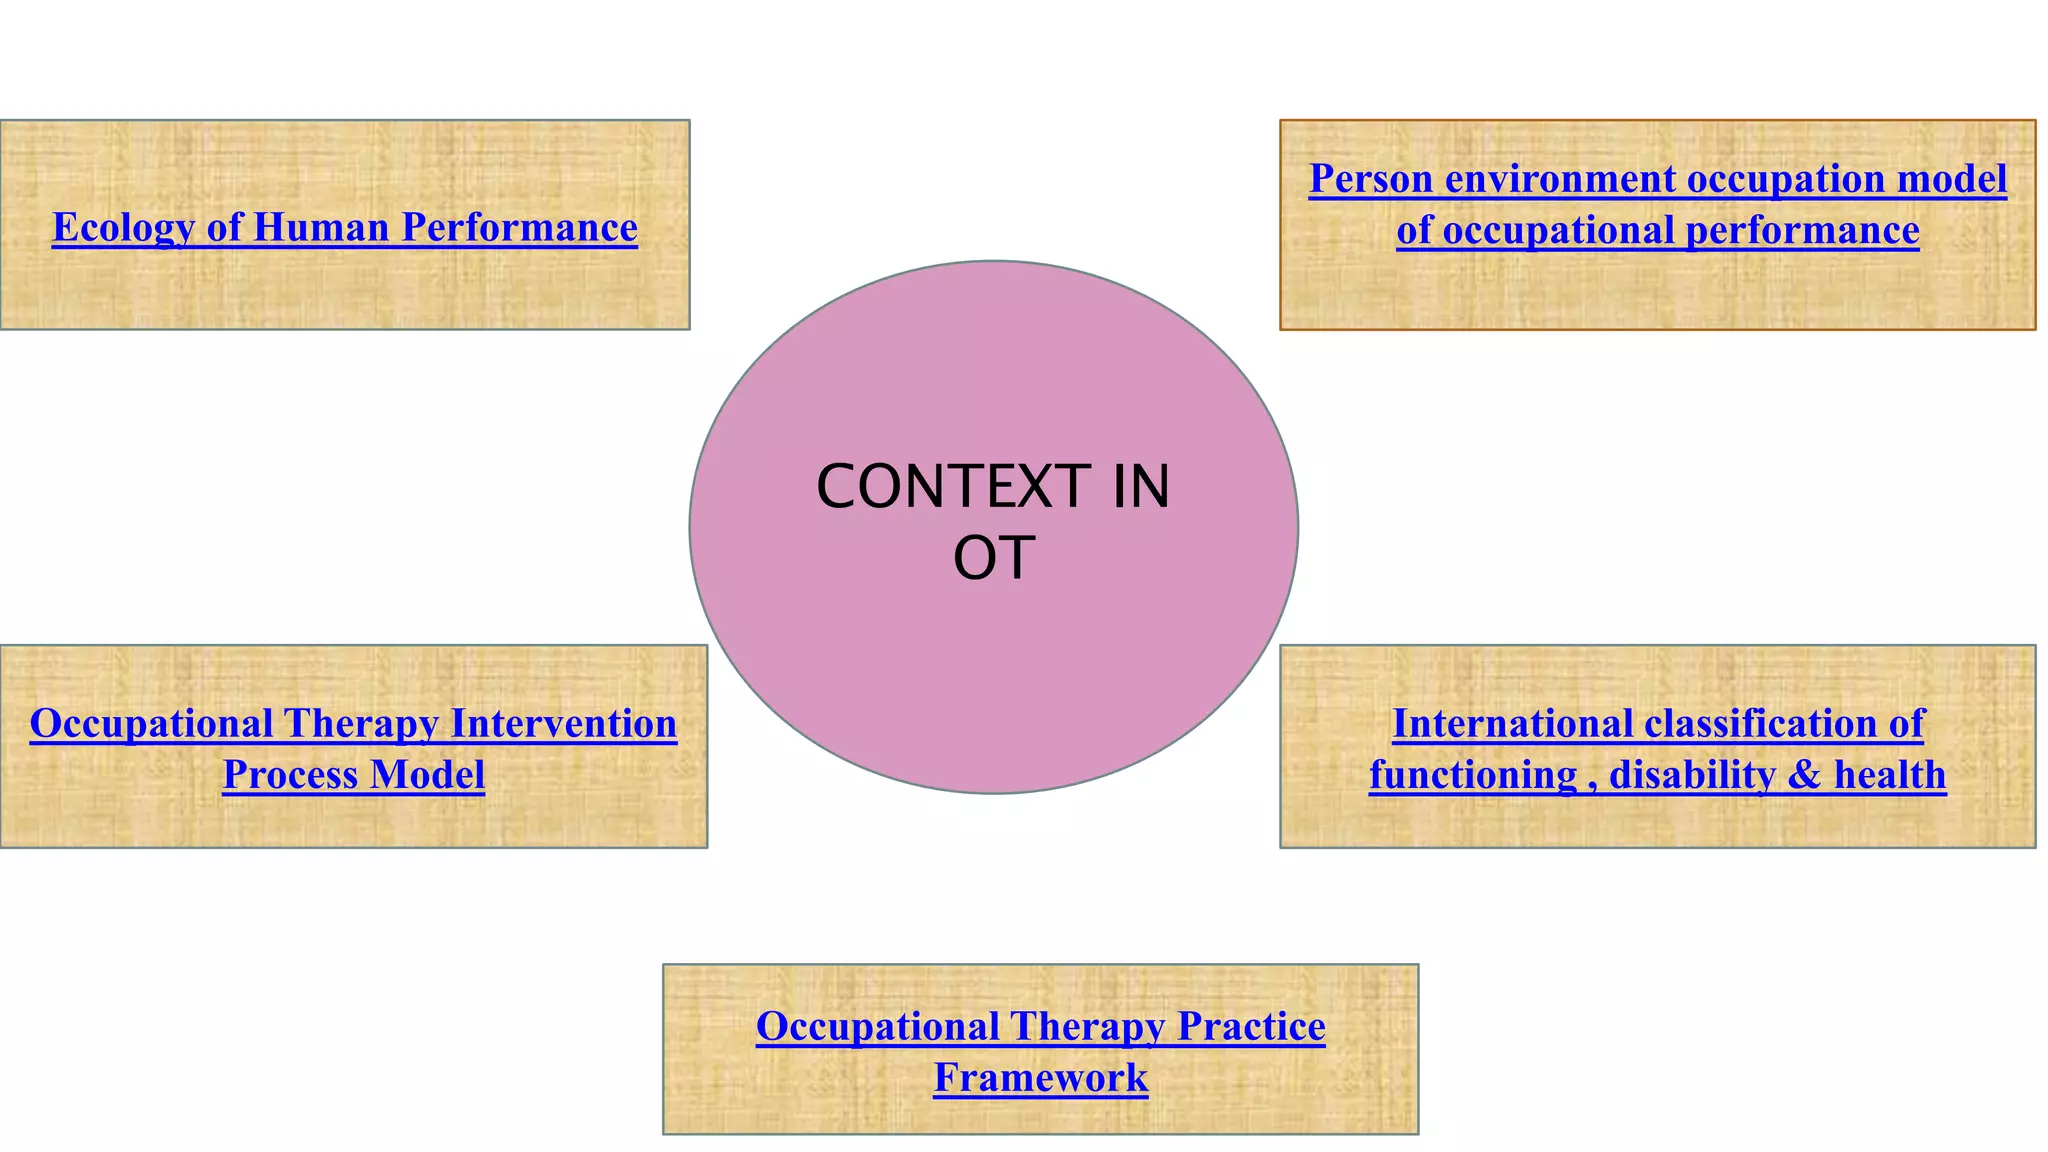
Contextual factors in occupational therapy are the background conditions that shape how a person engages with daily activities. They fall into two buckets under the ICF framework: environmental factors like your physical space, social support, assistive technology, and policy barriers, and personal factors like your age, habits, coping styles, and life experience. The framework sounds clean on paper but in practice it's the thing that makes or breaks a treatment plan. I've seen therapists nail the clinical reasoning on every measurable outcome and still miss because they treated the home environment as a checkbox rather than a living system. One of my cases sticks out. A mid-sixty patient with a stroke was making excellent progress in clinic. Grip strength, ROM, balance — all tracking well. We set up a simulated kitchen and she could navigate it fine. Then I got on a home visit to assess her actual kitchen and found the issue wasn't motor control at all. Her cabinets had been refaced with touch-latch doors years ago, which meant zero visual feedback on whether they were open or closed. She'd walk to the cabinet, find the handle where it used to be, feel nothing, assume it was closed, and give up. That cost us another three weeks of intervention before I caught it. The workaround was straightforward — I had her swap back to lever handles for about forty dollars each — but it never would've shown up in a standard evaluation. Here's the part most people don't tell you about contextual factors: they're not just background noise. They actively construct the problem you're treating. A patient's "fine motor deficit" might actually be an issue with lighting in their workspace. What looks like poor compliance with a home exercise program might just be that the exercises were prescribed for a routine they no longer have after a job change. The ICF model forces you to map these connections, and the mapping is where the work actually happens.
When I sit down with a new client I start with the Contextual Factors Assessment — not the standardized versions that come in the ICF core sets, though those have value, but a pragmatic version I built over years of practice. It covers housing type, room layout, household members and their roles, daily rhythm and schedule, cultural and language considerations, transportation access, financial constraints that affect equipment choices, and any existing barriers from local policies or insurance coverage. I don't need to check every box every time. Some contexts are obvious from the referral. What I do always is ask about the patient's actual day, hour by hour, for a typical week. That's where the misfits between their abilities and their environment show up. The real challenge with this approach is that contextual factors are unstable. They change. A patient moves, gets a new caregiver, loses a source of income, or their symptoms fluctuate with weather or medication. If you write your intervention plan around a snapshot of someone's life and that snapshot expires in six weeks, your plan is useless. I keep context notes on a rolling log inside the chart and I revisit them at every session, not just the initial assessment. It adds maybe ten minutes per visit but it prevents you from prescribing interventions that no longer fit.
The Assessment Process in Practice
There isn't a single validated tool that captures contextual factors the way there is for things like grip strength or range of motion. That's by design, honestly, because context is messy and any instrument trying to pin it down will miss the pieces that matter. The closest you'll get are the ICF core sets for specific conditions — stroke, spinal cord injury, rheumatoid arthritis — and even those leave a lot of room for clinical judgment. I use a combination of the Canadian Occupational Performance Measure for activity context and a semi-structured interview guide I developed. The COPM gives you a ranked list of what the patient actually cares about, which immediately filters out the noise. You then probe the environmental and personal factors around each top-ranked occupation. If the patient says cooking is a problem, you don't ask about kitchen features in the abstract. You ask about the last time they cooked, what happened, what they were trying to do, who was around, what time of day it was. The context reveals itself through the story. I should be clear about the limitations here. This method is slow. A thorough contextual assessment takes me roughly 45 to 60 minutes for a new adult client, sometimes longer if language barriers or cognitive concerns require an interpreter or a caregiver interview. For pediatric cases with school and home contexts it can run 75 to 90 minutes. If you're in a high-volume outpatient setting with fifteen-minute slots, you're not going to do this well unless you're willing to split it across visits, which means you lose the coherence of the picture until you've seen the patient three or four times.
Get the Full Details

Another downside: contextual factors are easy to underrate when you're being measured on clinical outcomes. Insurance reviewers and utilization managers want to see quantifiable progress, and "improved environmental modification" doesn't look as clean on a dashboard as "increased shoulder flexion by twenty degrees." I've had plans pushed back because the documented goals leaned too heavily on contextual changes rather than impairment-level outcomes. The workaround is to translate contextual interventions into functional outcome language wherever possible. Instead of "modified home environment," write "enabled independent meal preparation through kitchen adaptation, measured by COPM performance score improvement from 4 to 8."
Intervention Strategies That Actually Work
Once you've mapped the context, the intervention options fall into four categories. Environmental modification, which is the most common and usually the highest impact. Activity adaptation, which means changing how the task is done rather than changing the environment. Capacity building, which is the traditional therapeutic work of improving the person's abilities. And role renegotiation, which sounds fancy but just means figuring out who does what when the patient can't do it alone anymore. Environmental modification is where most of my wins have been. A wheelchair user can't reach the light switch because the ceiling fan pull chain is now within their reach but the actual switch is too high after a renovation. A patient with Parkinson's tremor can't button shirts but can manage magnetic closures if you replace the existing hardware. A home health patient on a fixed income can't afford a shower chair but a community grant program covered it after I filed the right paperwork. These are small things that compound. A single visit where I address the real environmental barriers tends to produce more functional gain than three visits of strengthening exercises in a controlled clinic setting. Activity adaptation follows a similar logic. The key insight most therapists miss is that adaptation isn't just about making tasks easier. It's about matching the task demands to the available context. I once worked with a patient who wanted to return to woodworking. His arthritis made power tools impossible, so we adapted the approach entirely. He switched to hand tools, modified his workbench height, and used jigs he could operate with one hand. The output wasn't identical to what he used to produce, but it was viable. The intervention wasn't about restoring his old capacity, it was about rebuilding a working relationship with the activity under his actual constraints.
Capacity building is the traditional territory — strengthening, retraining, sensory integration, whatever the diagnosis calls for. Don't skip it, but don't assume it's the primary lever. In my experience, capacity work produces the most reliable results when the context already supports it. If a patient has the strength to do their exercises but no space to do them, no time because of a second job, and no motivation because they don't see the point, the exercises themselves aren't the bottleneck. Fix the context first, then layer in capacity work. Role renegotiation is the one most therapists are uncomfortable with. It means talking to families, employers, schools, or caregivers about shifting expectations. A mother with MS can't lift her toddler anymore. That doesn't get fixed by strengthening the mother. It gets fixed by redistributing lifting tasks within the household and finding adaptive equipment for what remains. I've had pushback from family members who interpret this as "giving up" rather than "adapting." The conversation usually goes better if you frame it around the patient's valued roles, not the lost functions. People respond differently when you're protecting what matters to them instead of replacing what they can't do.
Documentation and Measuring Outcomes
Documentation for contextual factor work doesn't have to be elaborate. I use a simple structure: the identified contextual factors, the intervention applied, the patient's response, and the measurable outcome change. The outcome part is where people struggle. There's no standard metric for "better environment," so I default to the COPM when possible, the ADL independence scales when appropriate, and direct observation notes when neither fits. Progress notes should read like a narrative of change, not a list of services rendered. A note that helps with authorization and review looks like this: "Patient reported inability to prepare own meals due to inability to open food containers with left hand and difficulty reaching refrigerator shelf at current height. Provided adaptive can opener and installed shelf reducer on lower refrigerator shelf. Patient demonstrated independent meal preparation of simple items post-modification. COPM performance score improved from 3 to 7." That tells a story, shows the context, documents the intervention, and ties it to a measure. It also survives a peer review without requiring a defense of the clinical reasoning. The risk with contextual factor documentation is that it can look subjective. Without measurable anchors, reviewers may flag it as insufficient. The anchor doesn't have to be clinical. It can be task completion time, frequency of independent performance, or even patient-reported confidence. Whatever you choose, make it consistent so you can track change across sessions.
Contextual Factors Occupational Therapy: When It Falls Short
This approach doesn't work everywhere. It depends on therapist time, patient engagement, and access to the actual context. If you're doing telehealth only and the patient won't share video of their living space, your contextual assessment is going to be shallow. If the patient has severe cognitive impairment that prevents meaningful interview, you need a caregiver or collateral source, and if none is available, you're working blind on the personal factors side. Acute inpatient settings often don't allow enough time for the kind of environmental analysis that makes this framework useful, and the contextual factors there are dominated by medical instability rather than daily occupation. When the context is the main barrier and you can't modify it — a locked facility, an inaccessible building, a family situation you can't change — the framework still applies but your intervention options narrow. In those cases the best move is usually role renegotiation combined with advocacy. Document the barrier clearly. Refer to social work or case management if you haven't already. Push for policy-level changes when possible. The ICF model includes these structural barriers for a reason. If you want a starting point for the assessment, the ICF core sets are freely available through the WHO website and they give you a structured checklist for the major disability categories. The Canadian Occupational Performance Measure requires certification but many programs offer short workshops. My own semi-structured interview guide isn't published anywhere — I built it from trial and error over several years — but the structure is simple enough that you can reconstruct it from the ICF domains if you spend thirty minutes mapping them to interview questions.