Understanding When Estrogen Should Not Be Used
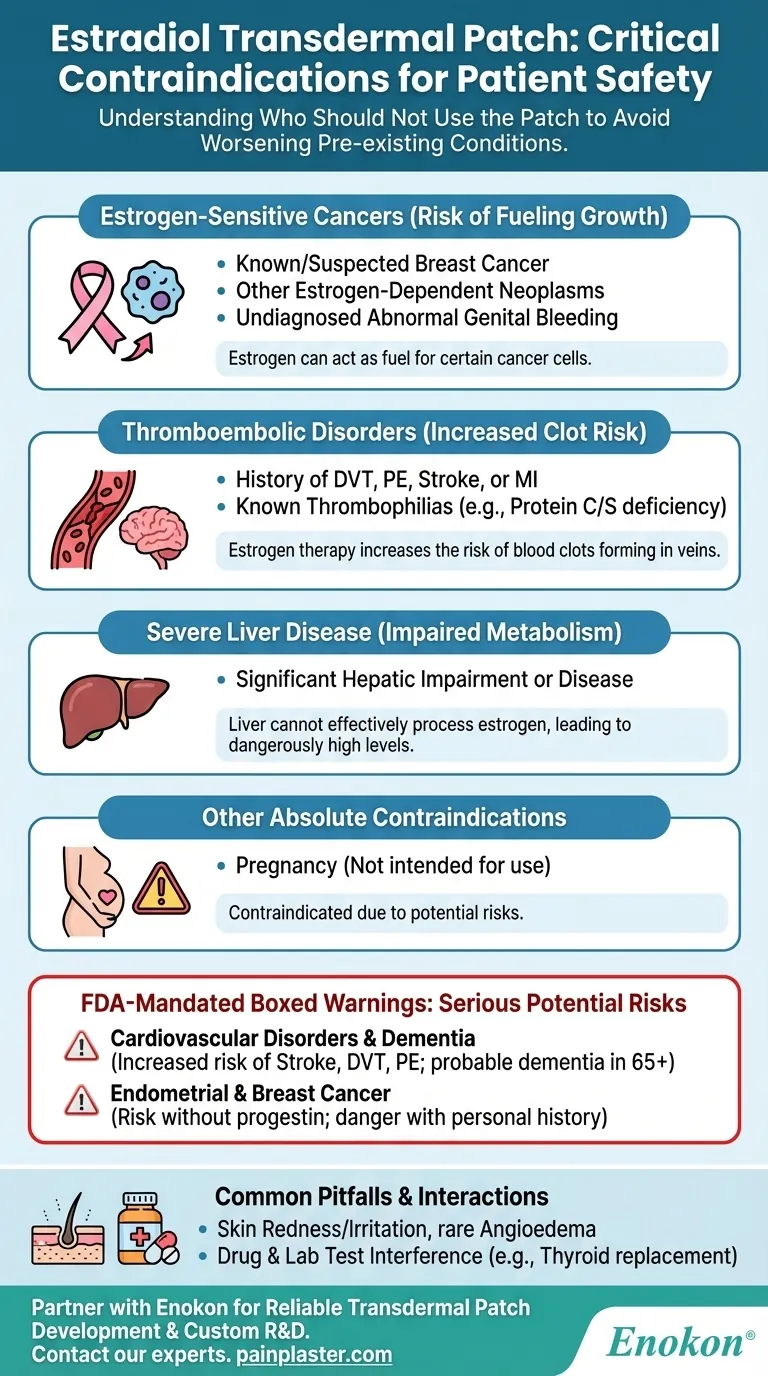
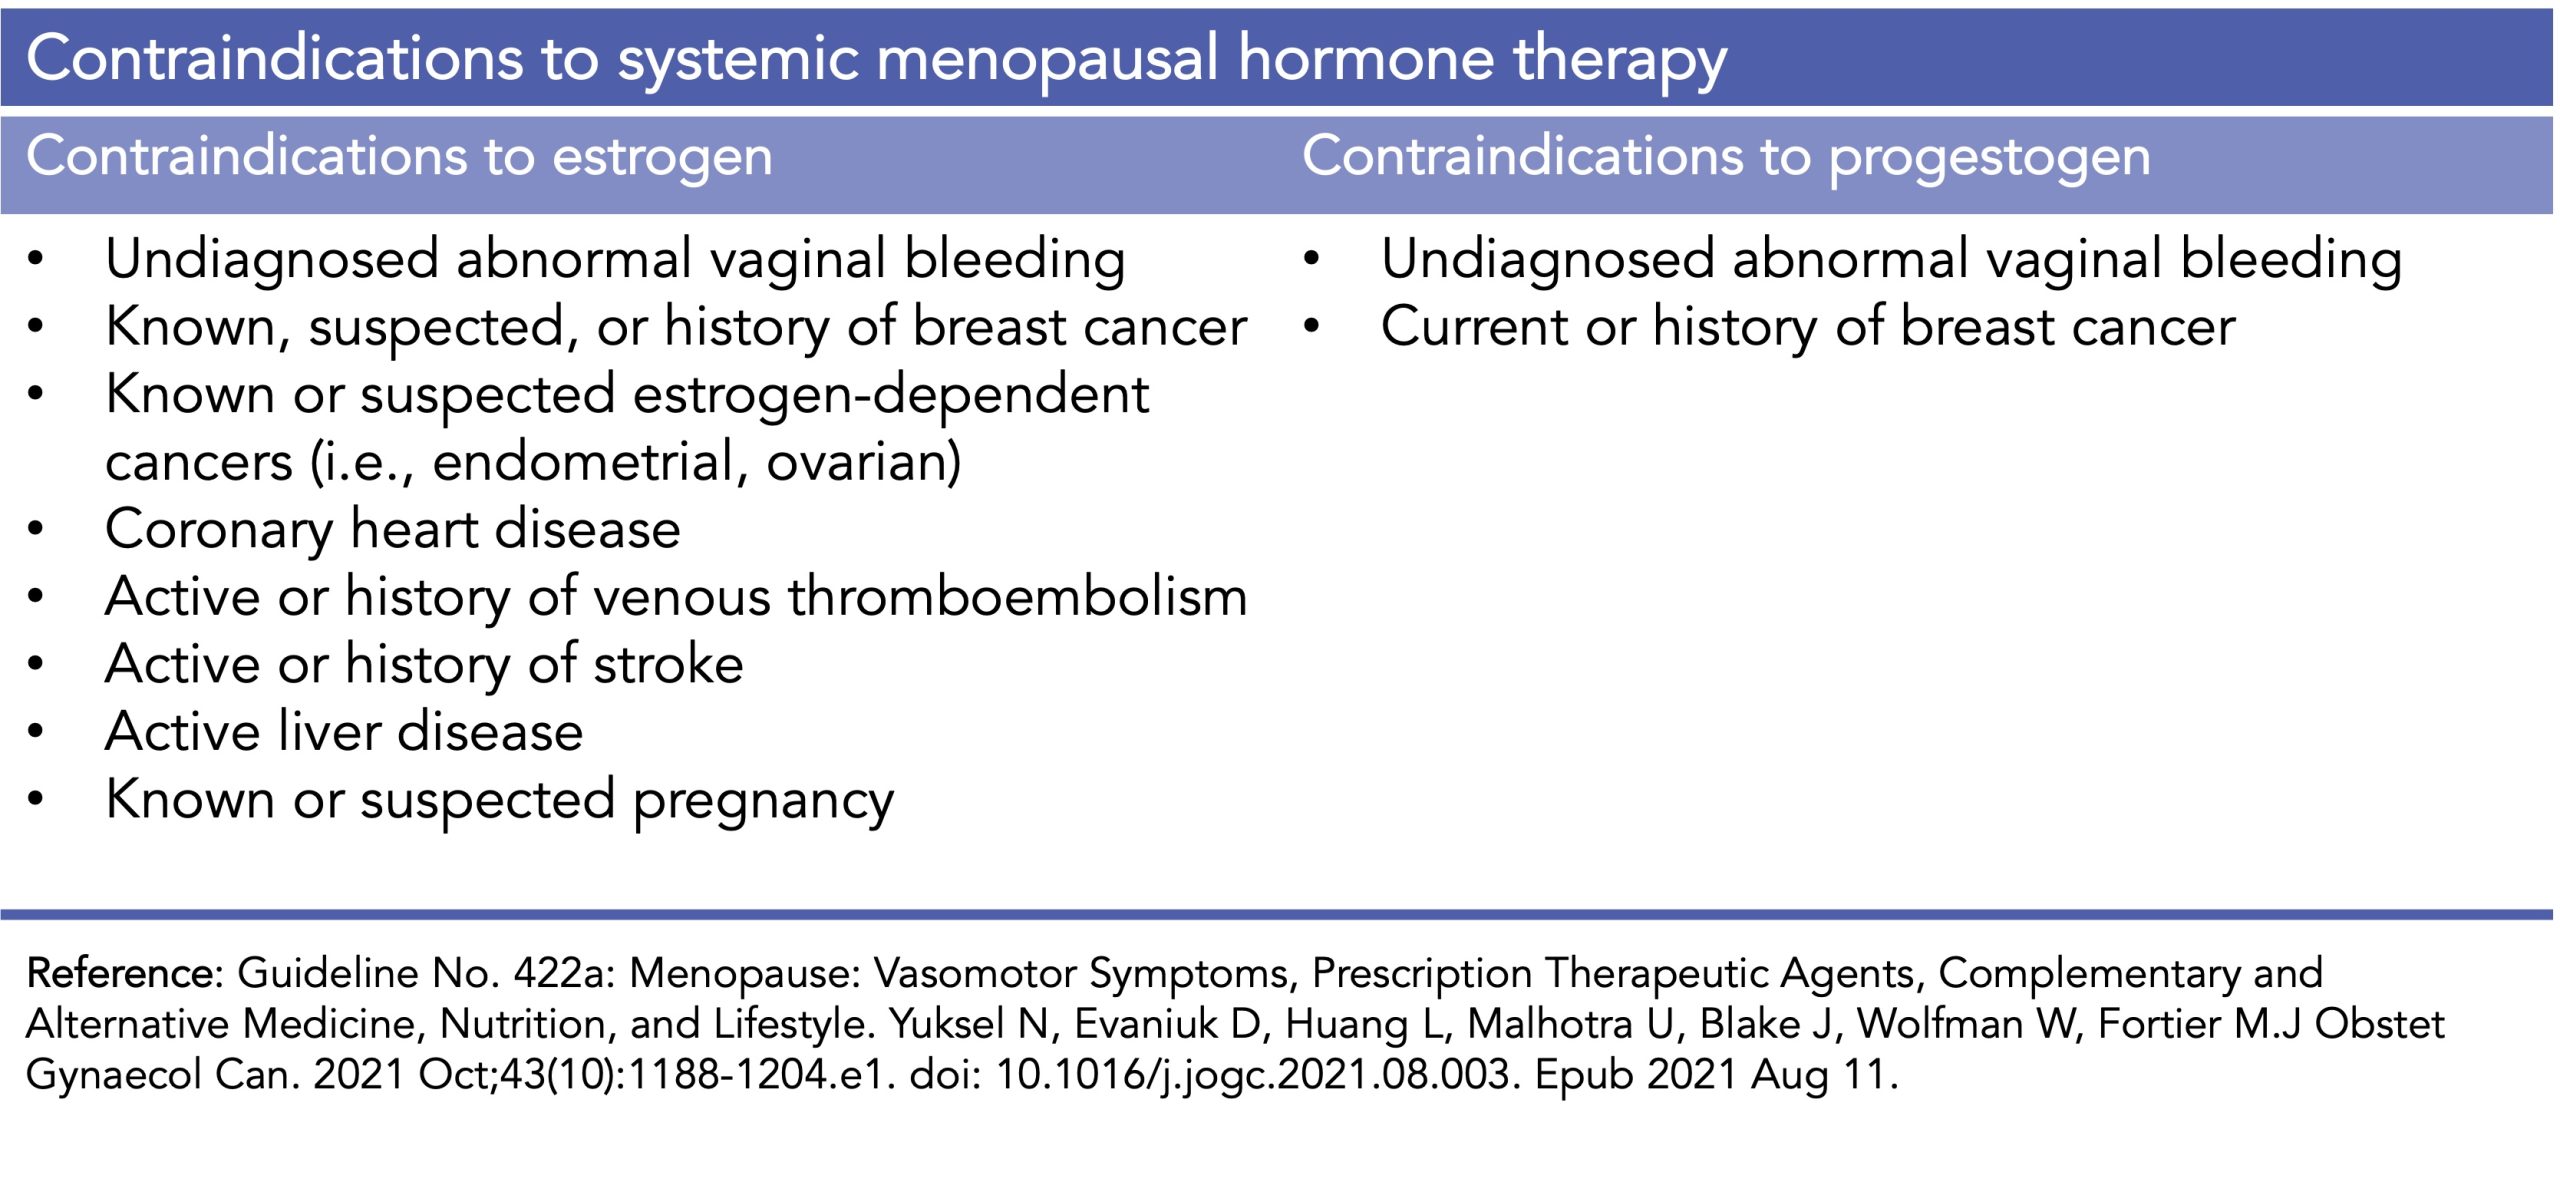
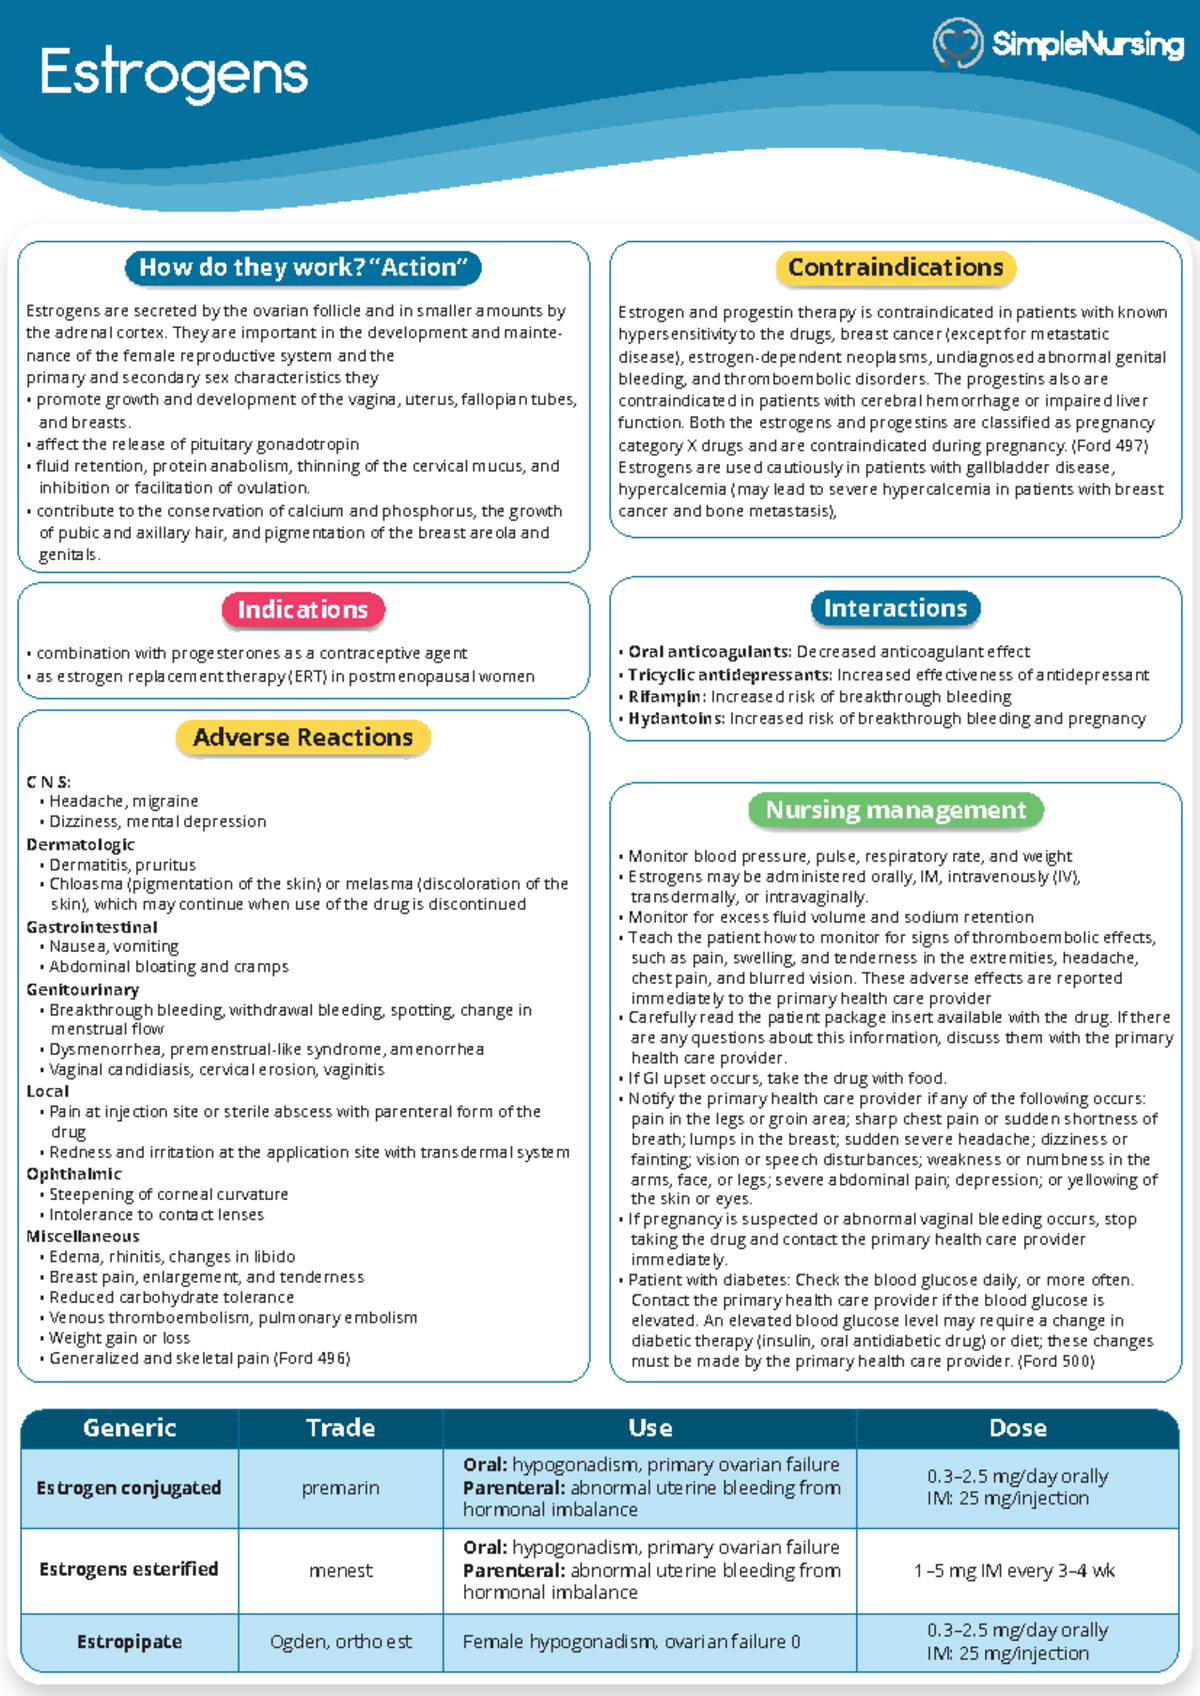
Estrogen therapy is one of those treatments that sounds straightforward on paper but requires serious caution in practice. The contraindications are not arbitrary lists pulled from a textbook. They exist because certain patient profiles consistently produce bad outcomes when estrogen is pushed into them. The absolute contraindications fall into predictable buckets. History of venous thromboembolism tops the list. I have seen this play out repeatedly. A woman in her late forties starts hormone replacement without a thorough personal and family history review. Three weeks later she is in the ER with a pulmonary embolism. The standard transdermal route would have lowered her risk, but it still would not have made it zero. There is no safe way to administer systemic estrogen to someone who has already proven they clot abnormally.
Contraindications For Estrogen Therapy
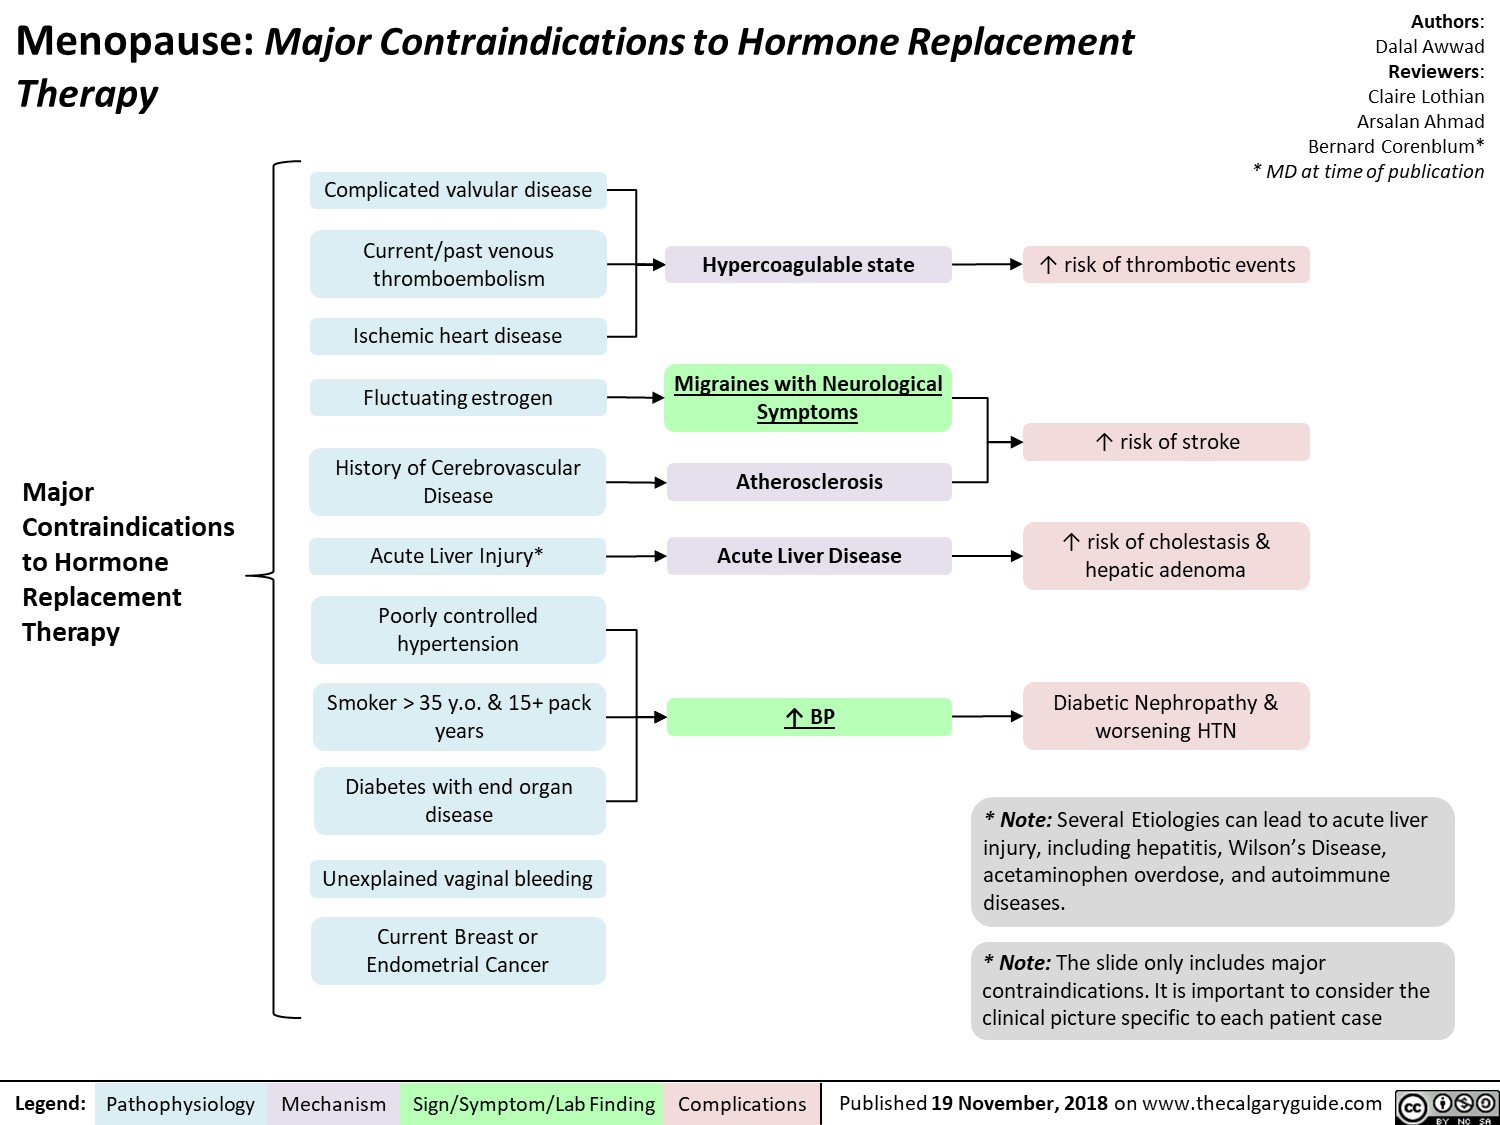
Known or suspected breast cancer is the next major category. Estrogen can stimulate hormone receptor-positive tumor growth. I ran into a case where a patient started hormone therapy before a mammogram was completed. A small lesion was found six months later. It turned out to be stage one ER-positive breast cancer. The estrogen had likely accelerated its development. Even decades of experience does not make that easier to stomach. Unexplained vaginal bleeding always gets flagged. It is not a contraindication itself, but it is a signal that something needs investigating before any hormonal intervention begins. Skipping that step is how you miss endometrial pathology. Active or recent arterial thrombotic disease counts as a hard stop. Stroke, myocardial infarction, unstable angina. Estrogen can worsen the coagulable state that underlies these conditions. A patient who has had a stroke at age fifty-two should not be starting conjugated equine estrogens for hot flashes.
Hepatic impairment is another area where clinicians sometimes get sloppy. Liver disease, especially cholestatic jaundice, can worsen with oral estrogen because of first-pass metabolism. I worked with a physician who prescribed oral micronized estradiol to a patient with moderate cirrhosis. Liver enzymes spiked within weeks. Switching to a transdermal patch avoided the hepatic first-pass effect entirely and stabilized her labs. This is one of those practical workarounds that does not get emphasized enough in guidelines.
Get the Full Details

Relative Contraindications and the Gray Zones
Not every contraindication is absolute. Migraine with aura comes up often. The original FDA label on combined oral contraceptives carried a black box warning for this exact scenario, and the mechanism is the same for hormone therapy. The risk of ischemic stroke increases, but the baseline risk for a woman in her early fifties is still low. When the clinical situation warrants estrogen and the migraine profile is manageable, some specialists will proceed with close monitoring. I have seen this done carefully with transdermal estradiol and cyclic progesterone, with neurological follow-up. It is not common practice, but it exists in the literature and in specialized clinics. gallbladder disease is a relative contraindication rather than an absolute one. Estrogen increases biliary cholesterol saturation. Oral formulations carry a higher risk of symptomatic cholelithiasis compared to transdermal routes. If a patient has a history of gallstones, switching to a patch or gel reduces the stimulus to the liver's cholesterol secretion pathway. The underlying gallbladder condition does not change, but the added pharmacologic pressure drops significantly. Hypertriglyceridemia deserves mention because it is frequently overlooked. Estrogen raises triglyceride levels by increasing VLDL production. In patients with baseline triglycerides above five hundred milligrams per deciliter, this can push them into pancreatitis territory. I encountered a case where a patient's triglycerides went from four hundred twenty to over nine hundred after starting oral estrogen. The workaround was switching to a low-dose transdermal preparation and adding a fibrate. The estrogen dose needed to be reduced to around twenty-five micrograms of estradiol daily to maintain symptom control without destabilizing her lipid profile.
Practical Screening Protocol
Before initiating any estrogen therapy, the following assessments should be in place: A complete personal and family history focused on thromboembolic events, cardiovascular disease, and breast or endometrial cancer. First-degree relatives with early-onset breast cancer change the risk-benefit calculation considerably. Baseline blood work should include liver function tests, fasting lipid panel, and a fasting glucose or HbA1c. These take about fifteen minutes to draw and provide information that directly affects which estrogen formulation is appropriate.
A breast exam and age-appropriate mammography. A pelvic exam with endometrial assessment if the patient has a uterus and presents with any irregular bleeding. Transvaginal ultrasound or endometrial biopsy may be necessary depending on findings. Blood pressure measurement. Uncontrolled hypertension is a relative contraindication that is sometimes missed until after therapy has started.
What the Guidelines Leave Out
Major guidelines cover the well-known contraindications adequately. What tends to get glossed over is the interaction between estrogen and certain medications. Aromatase inhibitors, tamoxifen, and even some anticonvulsants can alter estrogen metabolism in ways that make standard dosing unreliable. Patients on enzyme-inducing antiepileptics like carbamazepine or phenytoin metabolize estrogen faster, which means standard doses may not achieve therapeutic levels but the prothrombotic risk remains unchanged. I once managed a patient on long-term lamotrigine who developed breakthrough bleeding on a standard estradiol regimen. Increasing the dose did not solve the problem because her CYP enzyme induction meant the half-life was drastically shortened. The solution was splitting the dose and monitoring levels, which is not a protocol most general practitioners are set up to handle. Another frequently underestimated factor is body mass index. Higher BMI is associated with increased baseline risk of venous thromboembolism, and estrogen adds to that risk in an additive rather than purely synergistic pattern. The data here is nuanced. Some studies suggest that transdermal estrogen in obese patients carries a lower thrombotic risk than oral estrogen, while others find no significant difference. The practical takeaway is that obesity alone should not preclude estrogen therapy, but it should prompt a more careful discussion about route of administration and closer monitoring. Estrogen therapy has clear boundaries. Knowing where they are prevents harm. The contraindications for estrogen therapy exist for reasons that are mostly clinical and occasionally statistical. The exceptions are real but narrow. When in doubt, the route of administration matters more than most prescribers realize. Transdermal estrogen generally presents a lower thrombotic risk than oral estrogen across nearly all patient populations, and this difference is large enough to change decisions in borderline cases. That is the single most practical piece of information most clinicians need.