Let's talk about when you should not use a vest therapy system
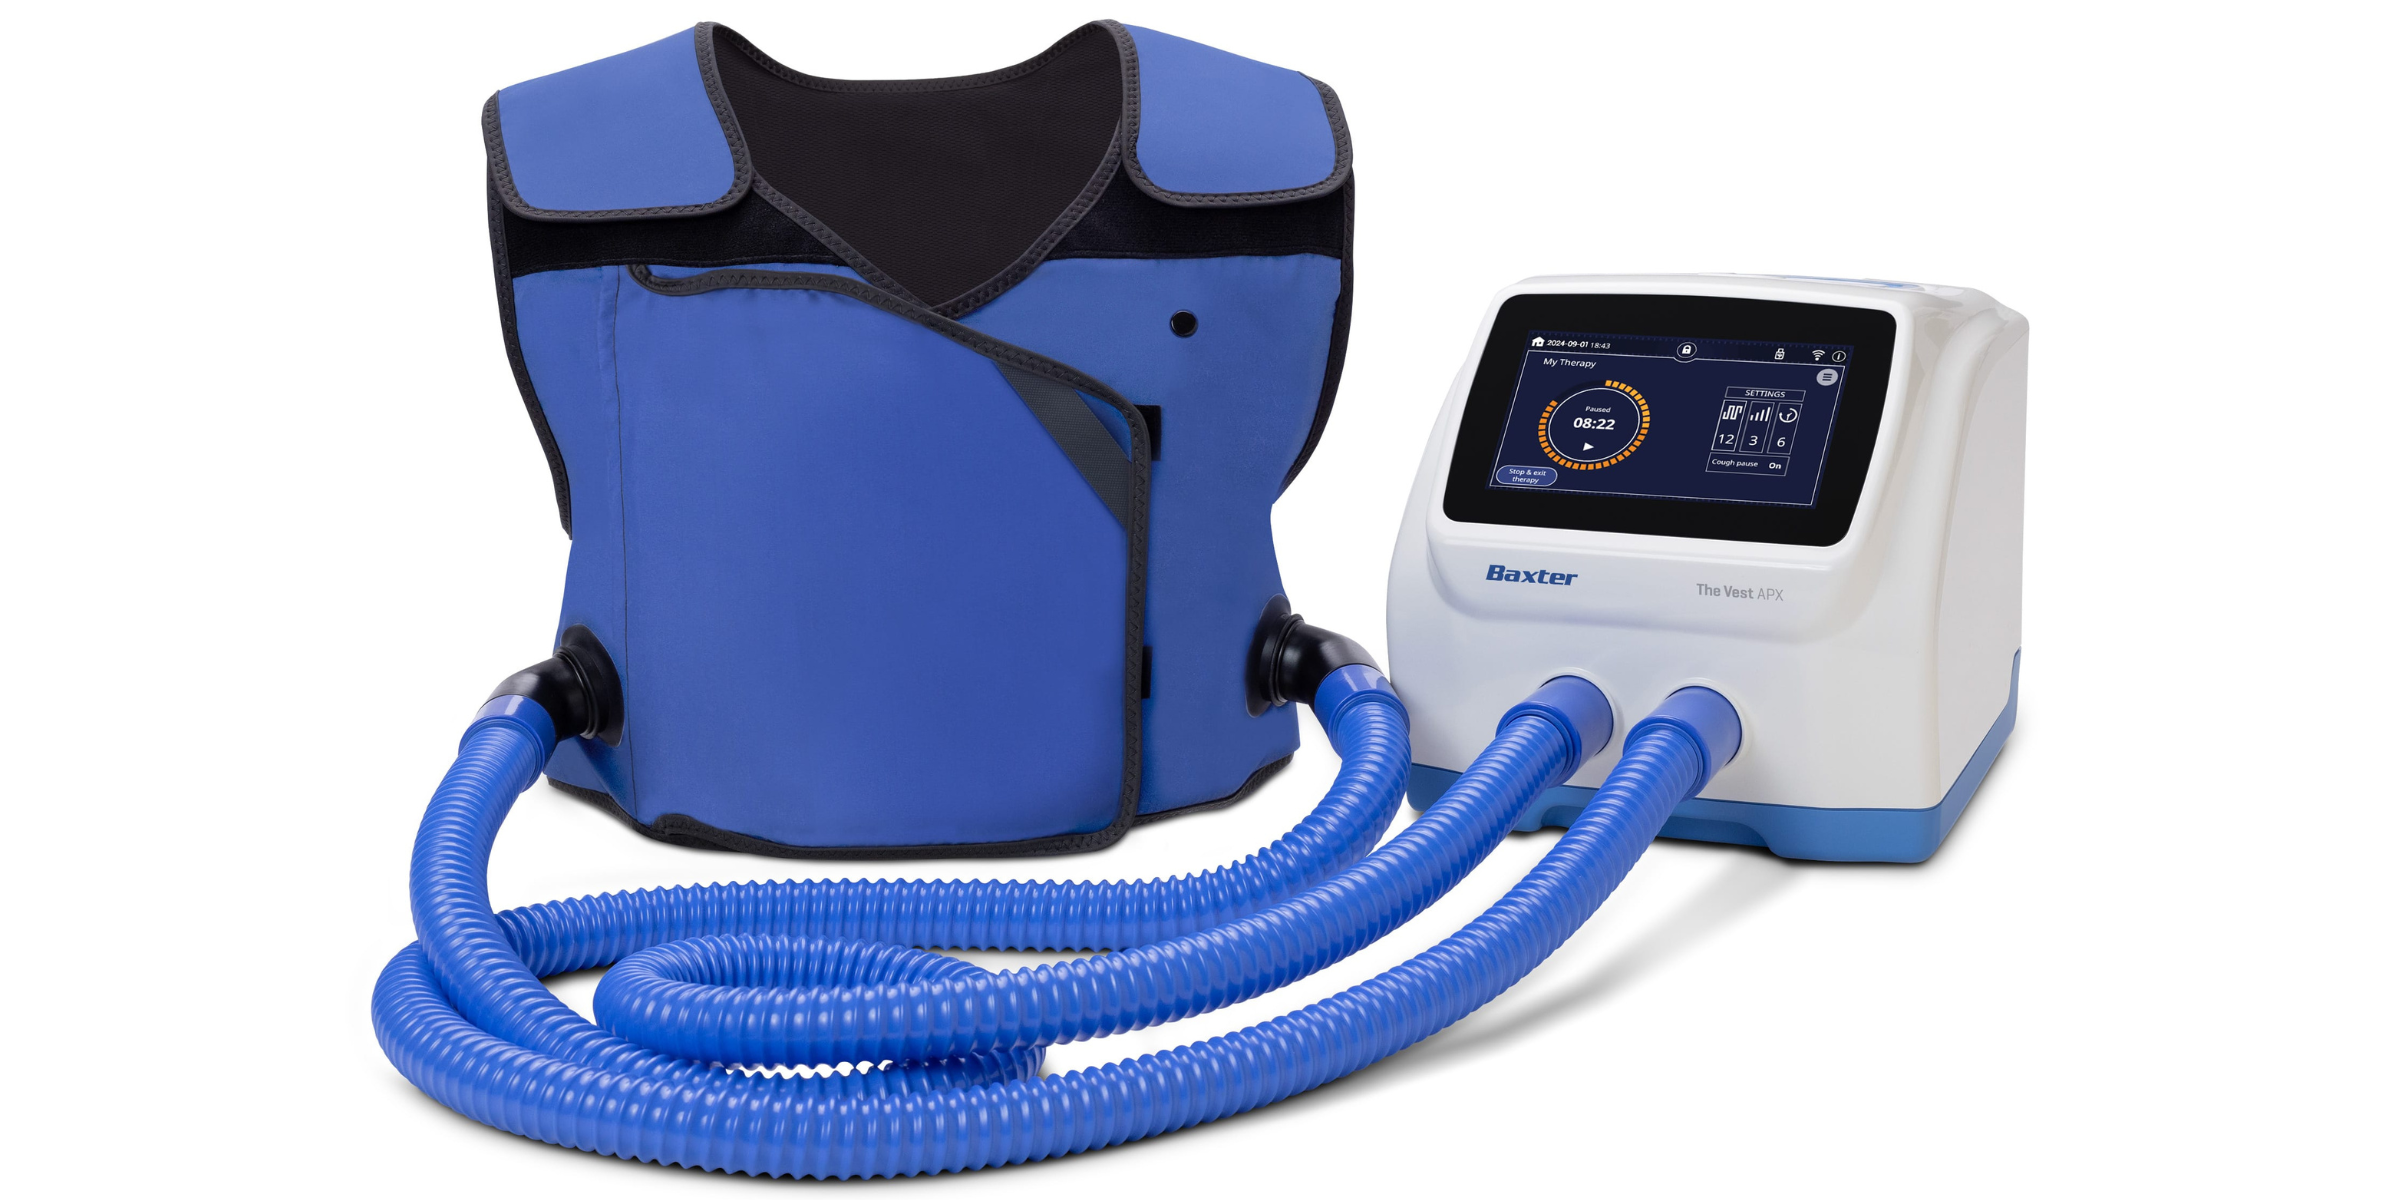
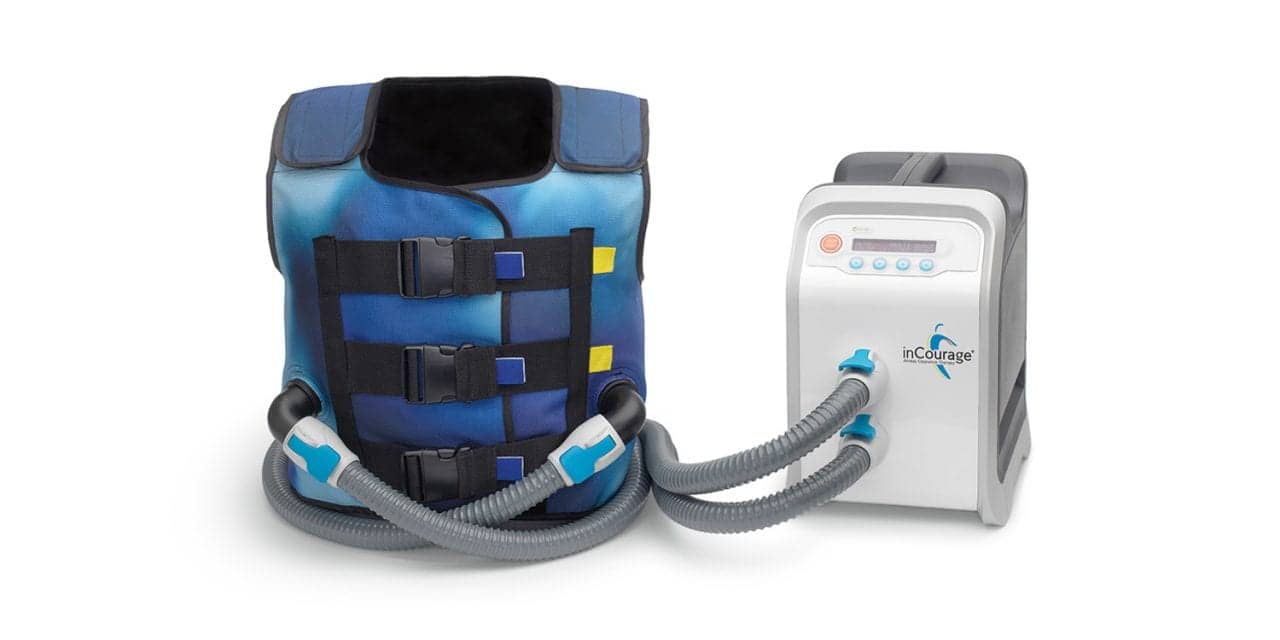
Vest therapy is high-frequency chest wall oscillation. A tight vest inflates and deflates in sequence to create vibrations that loosen secretions from the airway walls. It works well for people with cystic fibrosis, bronchiectasis, and some neuromuscular conditions. But it is not a universal tool and using it on the wrong patient can cause real harm. I spent years adjusting these programs in clinical settings and on home care calls. The contraindications are not always obvious from the package insert. The absolute contraindications are relatively straightforward. Pneumothorax is the big one. Positive pressure changes and physical vibration on a lung that has already collapsed will worsen it. I had a case where a CF patient with a known small bulla was started on vest therapy at a standard pressure. Within twenty minutes he was tachycardic and desaturating. The CT scan showed a new pneumothorax. We discontinued immediately and consulted pulmonology. This is why baseline imaging matters before you start. Unstable fractures of the ribs or sternum are another hard stop. The oscillation transmits force through the chest wall. A healing fracture under repeated vibration will not knit properly. I once saw a patient with undiagnosed osteopenia develop microfractures after three weeks of daily vest sessions at moderate pressure. Bone density screening should be part of the initial workup for anyone over fifty starting this therapy long-term.
Recent facial or nasal surgery is often overlooked. The vibrations travel through the thoracic cage and up into the upper airway structures. I've seen post-op patients develop epistaxis and surgical site dehiscence because nobody connected the two. Hold off for at least two weeks after any ENT procedure.
Relative Contraindications and When to Proceed with Caution
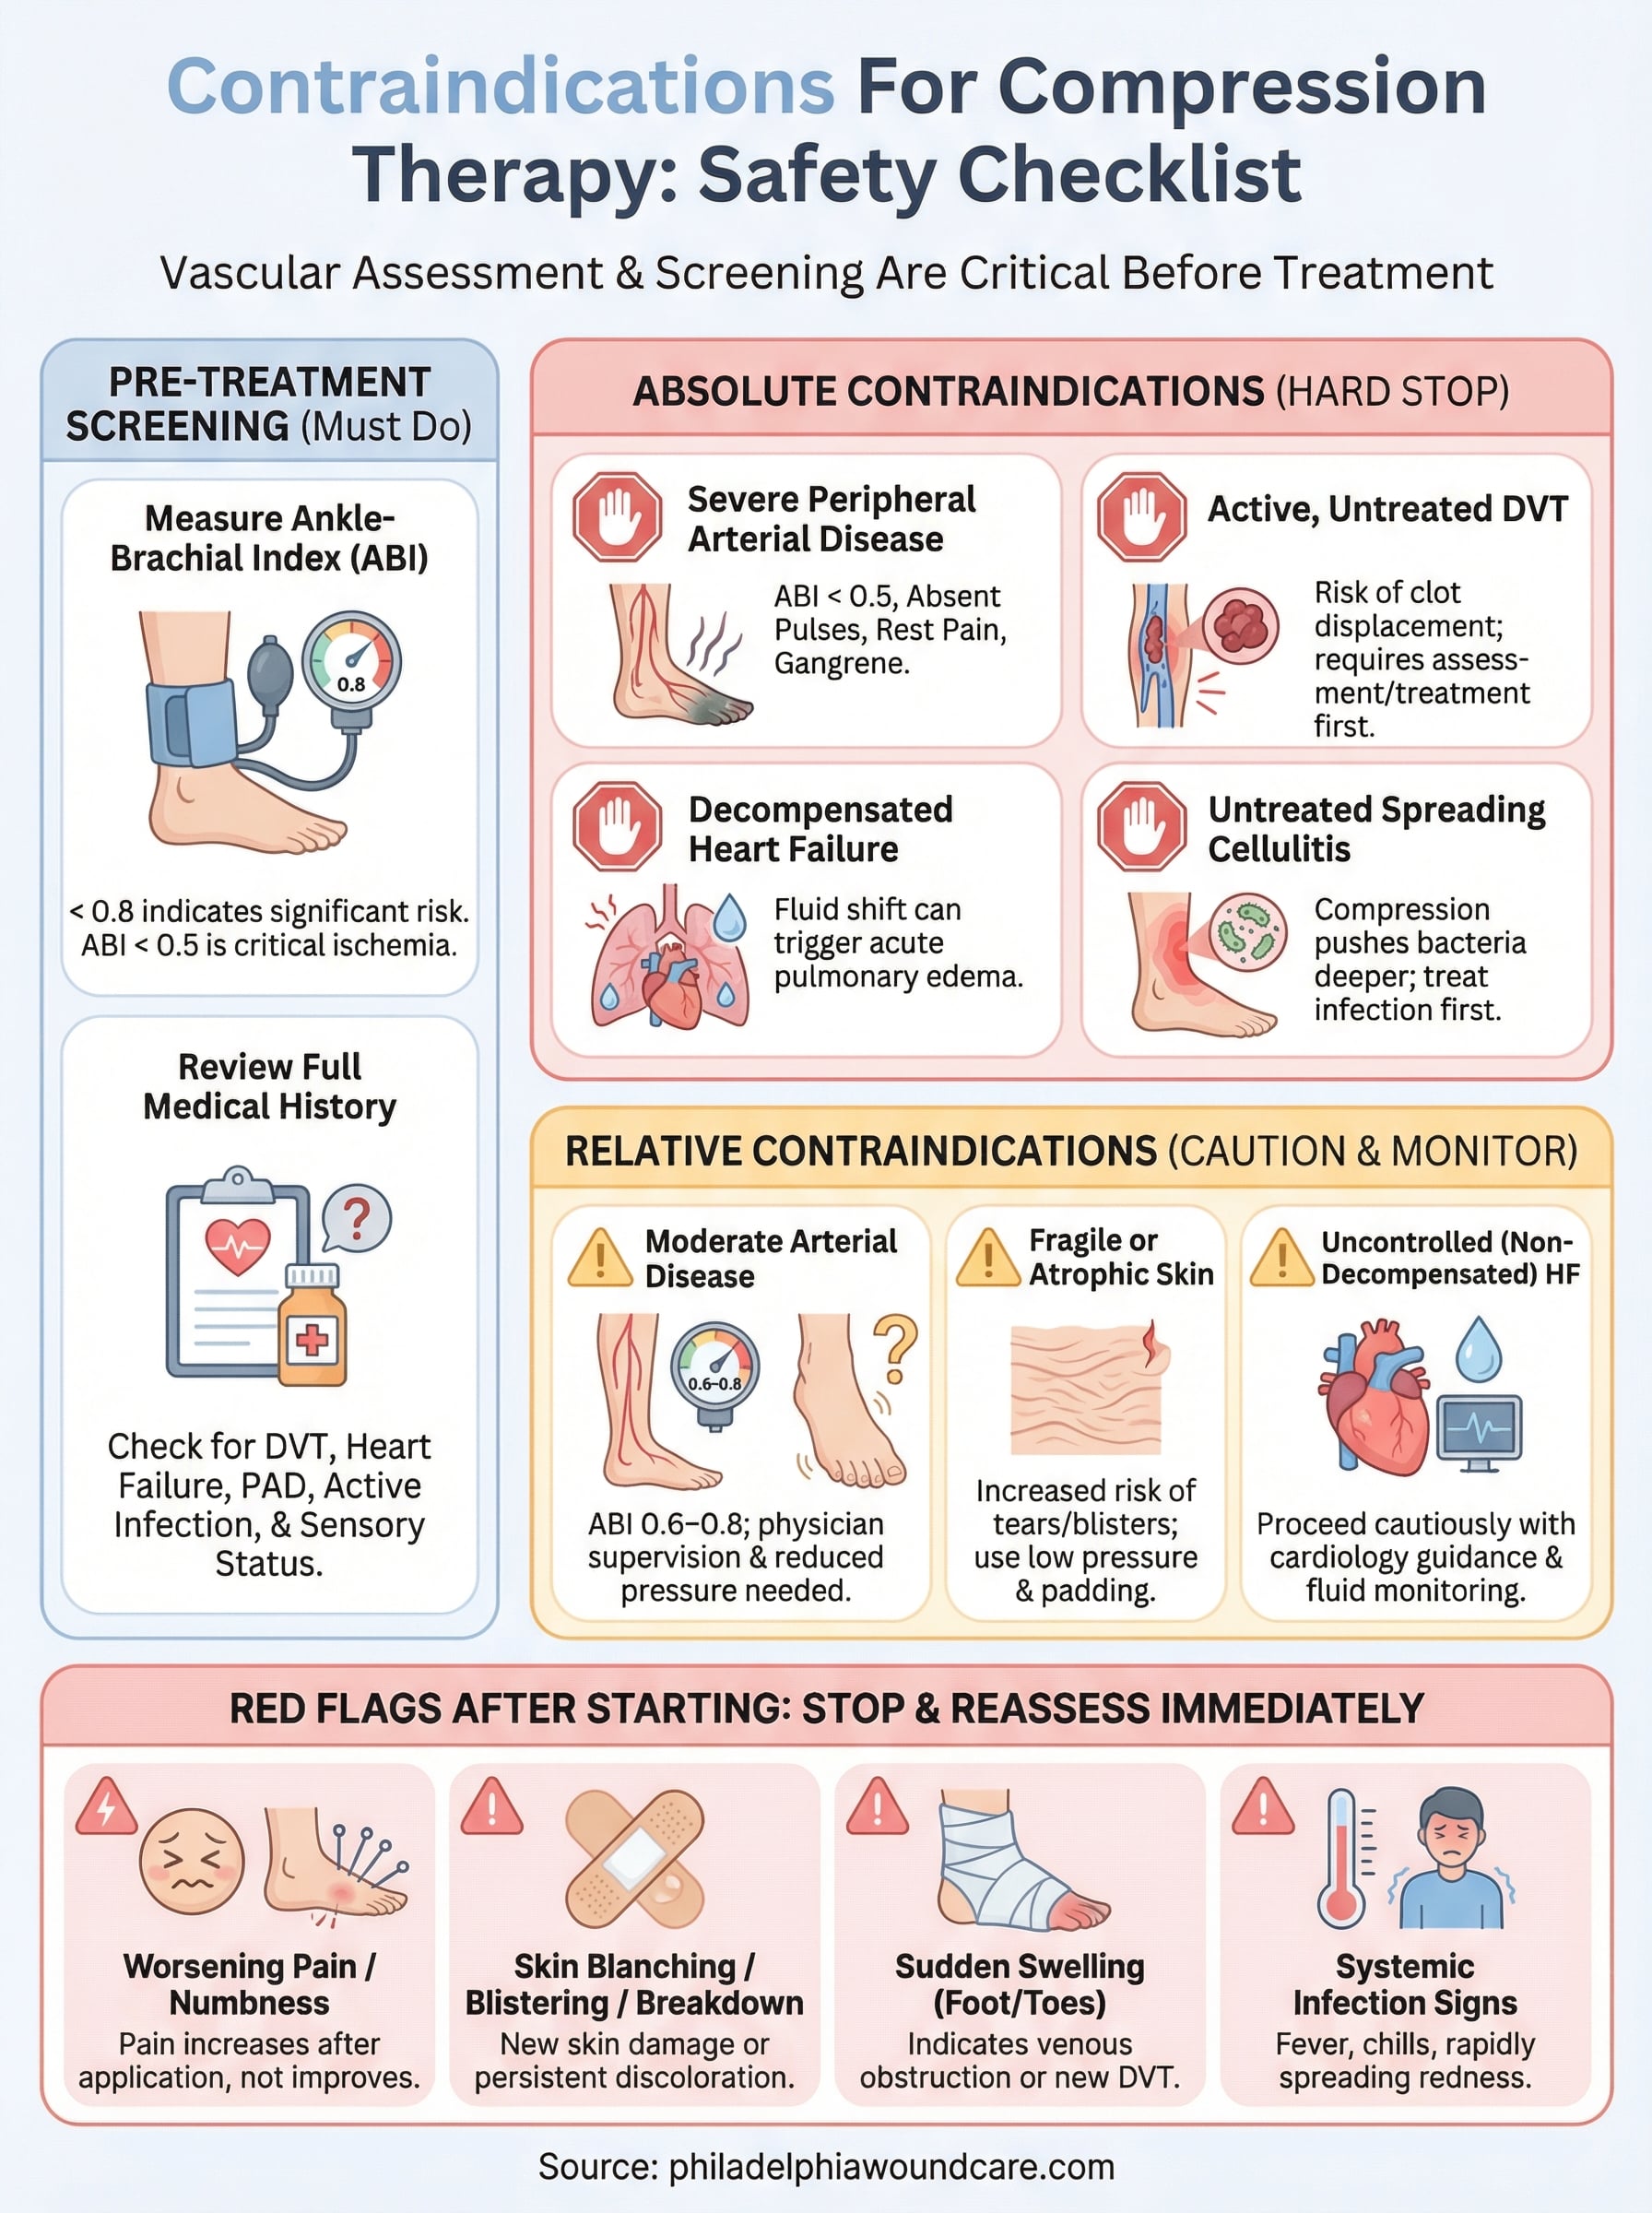
Not everything is a hard no. Some conditions require modified protocols. Gastroesophageal reflux disease is one. The compression on the abdomen can push gastric contents upward. I recommend running the vest with the patient in a semi-upright position and avoiding sessions within two hours of eating. One of my patients had silent reflux that worsened significantly. We adjusted the timing and added a PPI. His secretion clearance improved without the GI complaints. Heart failure with reduced ejection fraction needs careful monitoring. The thoracic compression affects venous return and can transiently alter hemodynamics. I check blood pressure and heart rate before and after sessions. If there is a drop in systolic pressure greater than twenty millimeters of mercury, I reduce the pressure setting by fifty percent and shorten the session to ten minutes. Most patients tolerate this fine. A few do not, and those patients need cardiology clearance before continuing. Pregnancy is a gray area. The literature is thin. I generally avoid vest therapy during the first trimester unless the respiratory benefit clearly outweighs the theoretical risk. After the first trimester, it may be used with modifications. The vest should not compress the abdomen. A pediatric vest on an adult torso sometimes works for this. I always get OB clearance on file.
Get the Full Details

Increased intracranial pressure is rare but serious. The Valsalva-like effect from chest compression can raise ICP. Any patient with a history of head trauma, brain tumor, or recent neurosurgery should be evaluated by neurology before starting. I once worked with a patient who had a Chiari malformation. We tried vest therapy and within five minutes she had a severe occipital headache and visual changes. We stopped. An MRI showed tonsillar herniation progression. This patient ended up on an airway clearance mattress instead.
Technical Pitfalls That Mimic Contraindications
Sometimes the problem is not the patient but the equipment setup. Improper vest fit is the most common error. A vest that is too loose creates dead zones where no oscillation reaches the lung tissue. A vest that is too tight restricts chest expansion to the point where the patient cannot breathe adequately. The pressure should be set so that you can slide two fingers under the vest at the sternum. If you cannot, it is too tight. If you can slide five or more, it is too loose. Incorrect pressure settings cause problems too. The standard starting range is fifteen to twenty-five centimeters of water. Patients with thick chest walls or significant obesity often need higher pressures, sometimes up to thirty-five cmH2O. Patients with emphysema and hyperinflated lungs need lower pressures, often ten to fifteen cmH2O. I start everyone at fifteen and titrate based on secretion mobility and patient tolerance. It usually takes three to five sessions to find the right setting. Session duration matters more than people think. The recommended twenty to forty minutes per session is a guideline, not a rule. Some patients clear their secretions in fifteen minutes. Others need the full forty. I judge by auscultation before and after, not by the clock. If lung sounds improve and the patient is expectorating productive sputum, we stop. Running longer just causes fatigue and skin breakdown without additional benefit.
What to Do When Vest Therapy Is Not an Option
If a patient has multiple contraindications, there are alternatives. High-frequency oscillatory ventilation through an endotracheal tube works for hospitalized patients who cannot tolerate external vest therapy. Postural drainage and percussion remain valid for patients with limited secretion loads. Acupeitris devices and flutter valves provide targeted airway clearance without whole-chest oscillation. Airway clearance mattresses use low-frequency oscillation through a mattress surface and can work for patients who cannot wear a vest due to skin integrity issues or recent surgery. I also recommend humidification therapy as an adjunct or alternative in mild cases. Thinning the secretions with heated humidification reduces the need for aggressive mechanical clearance. One of my patients with severe osteoporosis and multiple rib fractures managed his CF with humidification and directed cough techniques alone. He avoided the vest entirely and maintained reasonable lung function for four years before transitioning to other therapies. The bottom line is that vest therapy is effective when indicated and properly applied. The contraindications are real and sometimes subtle. Take the time to screen properly, monitor closely during the first few sessions, and have an alternative plan ready. The patients who benefit most are the ones who get the right therapy at the right intensity for the right duration.