What This Training Actually Covers After You Get Your Initial Certification
Most pharmacy support staff finish their initial controlled substance training and think they're done. They get a certificate, file it away, and move on to the next task. That's when things get dangerous. The DEA doesn't require you to prove you learned it once. They require you to demonstrate ongoing competence. Part 2 of any decent Controlled Substance Training For Pharmacy Support Part 2 curriculum deals with everything that happens after the initial classroom session. It covers the maintenance phase, the audit prep phase, and the "what do I do when something smells wrong but I can't quite prove it" phase. Here's something nobody puts in the brochure. Most pharmacy technicians and support staff handle controlled substance inventory logs without really understanding what auditors look for. They think if the numbers add up at the end of the shift, they're fine. They're not. The DEA and state boards care about patterns. A missing four-count of oxycodone tablets sounds like a rounding error to most people. To an auditor, it's a flag if it happens every third Tuesday for six months running. I've seen a chain pharmacy get hit with a consent decree because their audit trail showed that pattern clearly, and nobody had bothered to connect the dots. The workaround I ended up using involved creating a simple spreadsheet that tracked discrepancies by date, shift, and specific drug. After three months, the pattern was impossible to miss. We reported it internally before anyone outside could find it. That report became part of our documentation showing proactive compliance. It mattered more than you'd expect during the actual inspection.
Inventory Counts That Actually Work Under Real Conditions
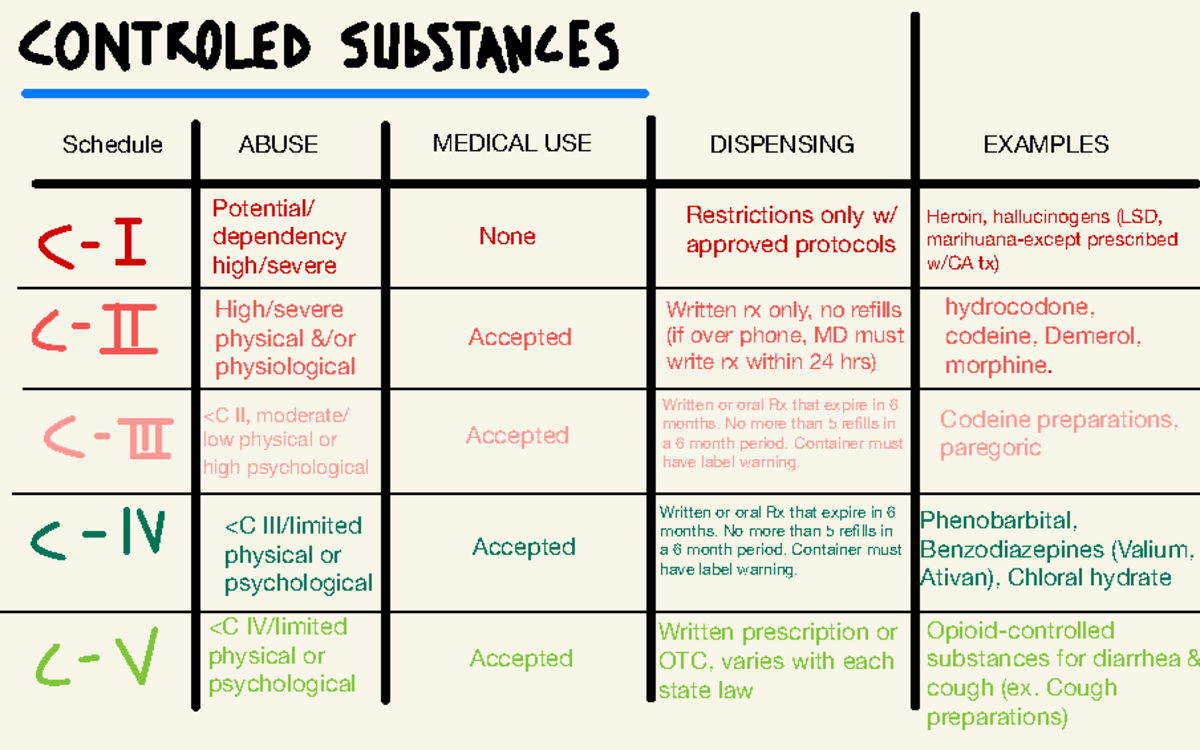
The textbook says you need a physical inventory of all Schedule II substances at least every two years. That's the legal minimum. The reality is you should be doing them quarterly at minimum, and monthly for high-volume Schedule IIs. Here's why. I worked at a pharmacy where the quarterly count discrepancy was always small - two pills here, one bottle there. Management treated it as normal shrinkage. When we switched to monthly counts, we found those "normal" discrepancies added up to over sixty missing controlled substance pills per year across just three medications. That's not shrinkage. That's a control failure. The counter-intuitive part is that more frequent counts don't necessarily mean more work. Once you set up a rotating schedule where each tech counts a different category each month, the actual time commitment drops significantly. You're counting smaller batches more often instead of facing a massive once-a-year counting event. I reduced my two-hour inventory nights to roughly twenty minutes of actual counting work per month, spread across four shifts.
Practical Steps for Implementing Better Controls
Start by mapping out exactly which Schedule II drugs your pharmacy carries and their relative theft risk. Oxycontin, fentanyl patches, and hydromorphone are always going to be higher risk than tramadol or certain compounded preparations. Put your highest-risk items on monthly counts and everything else on a rotating quarterly schedule. Build this into your pharmacy's SOP document and get it signed by the pharmacist in charge. That signature matters more legally than the content of the SOP itself, and I learned that the hard way after a state board inquiry where they asked for proof of implemented procedures and we had the procedures written down but never formally adopted. Another thing that catches people off guard is the disposal documentation requirement. When you destroy controlled substances, even in small quantities, you need proper documentation. Many pharmacies use an inventory management system that auto-generates the required forms. Some smaller operations still use paper. Either way works if it's complete. The problem arises when someone disposes of a partial container and records it as a single-unit disappearance instead of following the proper destruction protocol. That inconsistency is exactly what raises red flags during audits. I ran into this issue when a new tech joined our team and started recording all destroyed medications as "inventory adjustments" rather than tracking them through the proper destruction process. Our system allowed both entry methods, which was the real problem. The system should have prevented that flexibility. Until systems get better, you have to train people on the specific reason each method exists. The destruction record creates a chain of custody from filling to disposal. The inventory adjustment record does not. When auditors see your numbers balancing through adjustments rather than through documented destructions, they assume the chain of custody is broken.
Get the Full Details

Handling the Uncomfortable Situations
Part 2 training should prepare you for moments when something doesn't add up and you're not sure whether to escalate it. The truth is most pharmacy support staff never encounter serious diversion. But when you do, you need to know the right path. Document everything immediately. Date, time, who was on shift, what medication, what the discrepancy is. Don't investigate yourself. Don't try to figure out who took the pills. Your job is to report the anomaly through the proper chain of command, ideally in writing, and let the pharmacist in charge handle the investigation. There's a downside to building robust inventory controls and reporting structures, and I should mention it. It takes time and patience. Some pharmacy owners see it as overhead that eats into margins. They push back on monthly counts, they resist comprehensive documentation, they want to keep the simple system that the textbook describes as the minimum. You can't control that pressure. What you can control is maintaining your own records accurately and raising concerns through proper channels before they become problems. A well-documented pharmacy with solid tracking procedures is defensible regardless of what happens. A pharmacy with minimal documentation and a missing shipment is not. The other practical limitation is that no tracking system catches everything. Human error will always exist. A pill counted wrong during a rush period, a quantity entered incorrectly in the computer, a partial refill recorded against the wrong patient. These happen. The value of thorough training isn't in eliminating errors entirely. It's in catching them early enough that they don't accumulate into patterns that look intentional. That's the difference between an administrative mistake and a compliance violation, and it's measured in how quickly you notice and report deviations.
If you're looking for resources to build out your training program beyond the initial certification requirements, the DEA's own resources at dea.gov are surprisingly accessible. They have diversion control division forms, guidance documents, and the registration database where you can verify your pharmacy's standing. State boards usually have their own specific requirements layered on top, so cross-reference those. What works in Texas doesn't always translate to California or Florida, and the differences are usually in the reporting frequency and the specific form numbers rather than the underlying principles.