Understanding How Nursing Unit Conversions Actually Work in Practice
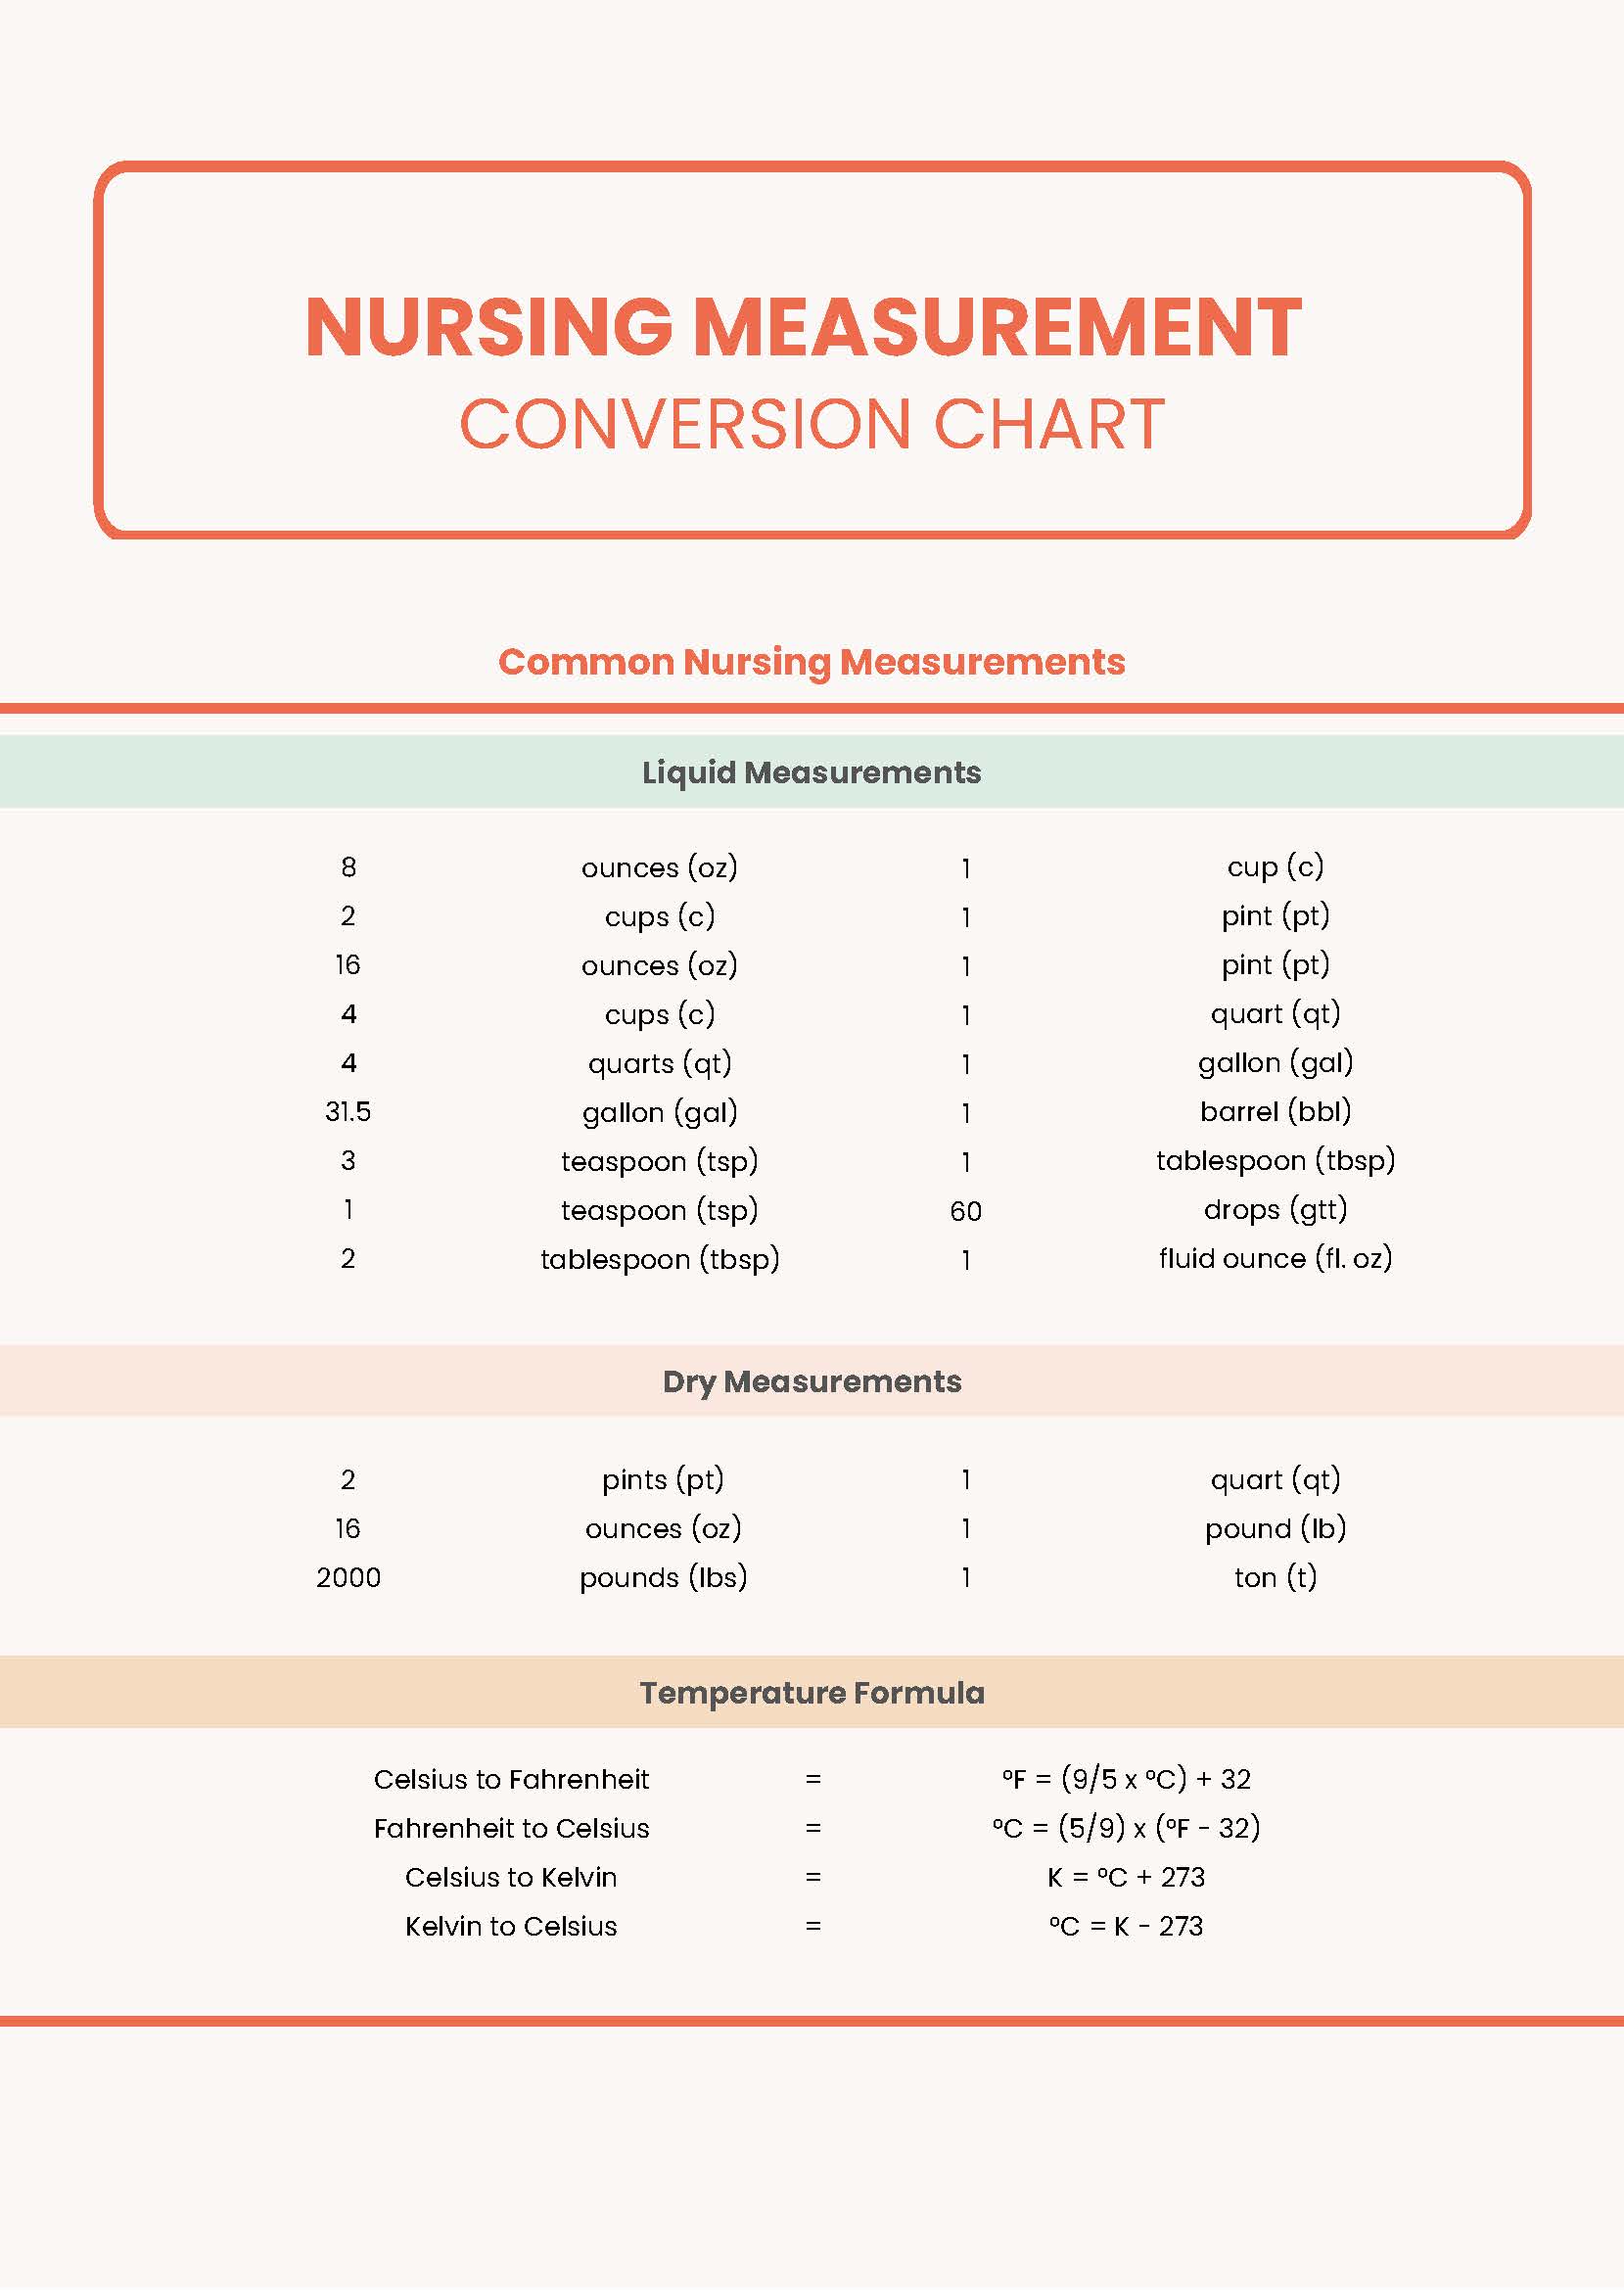
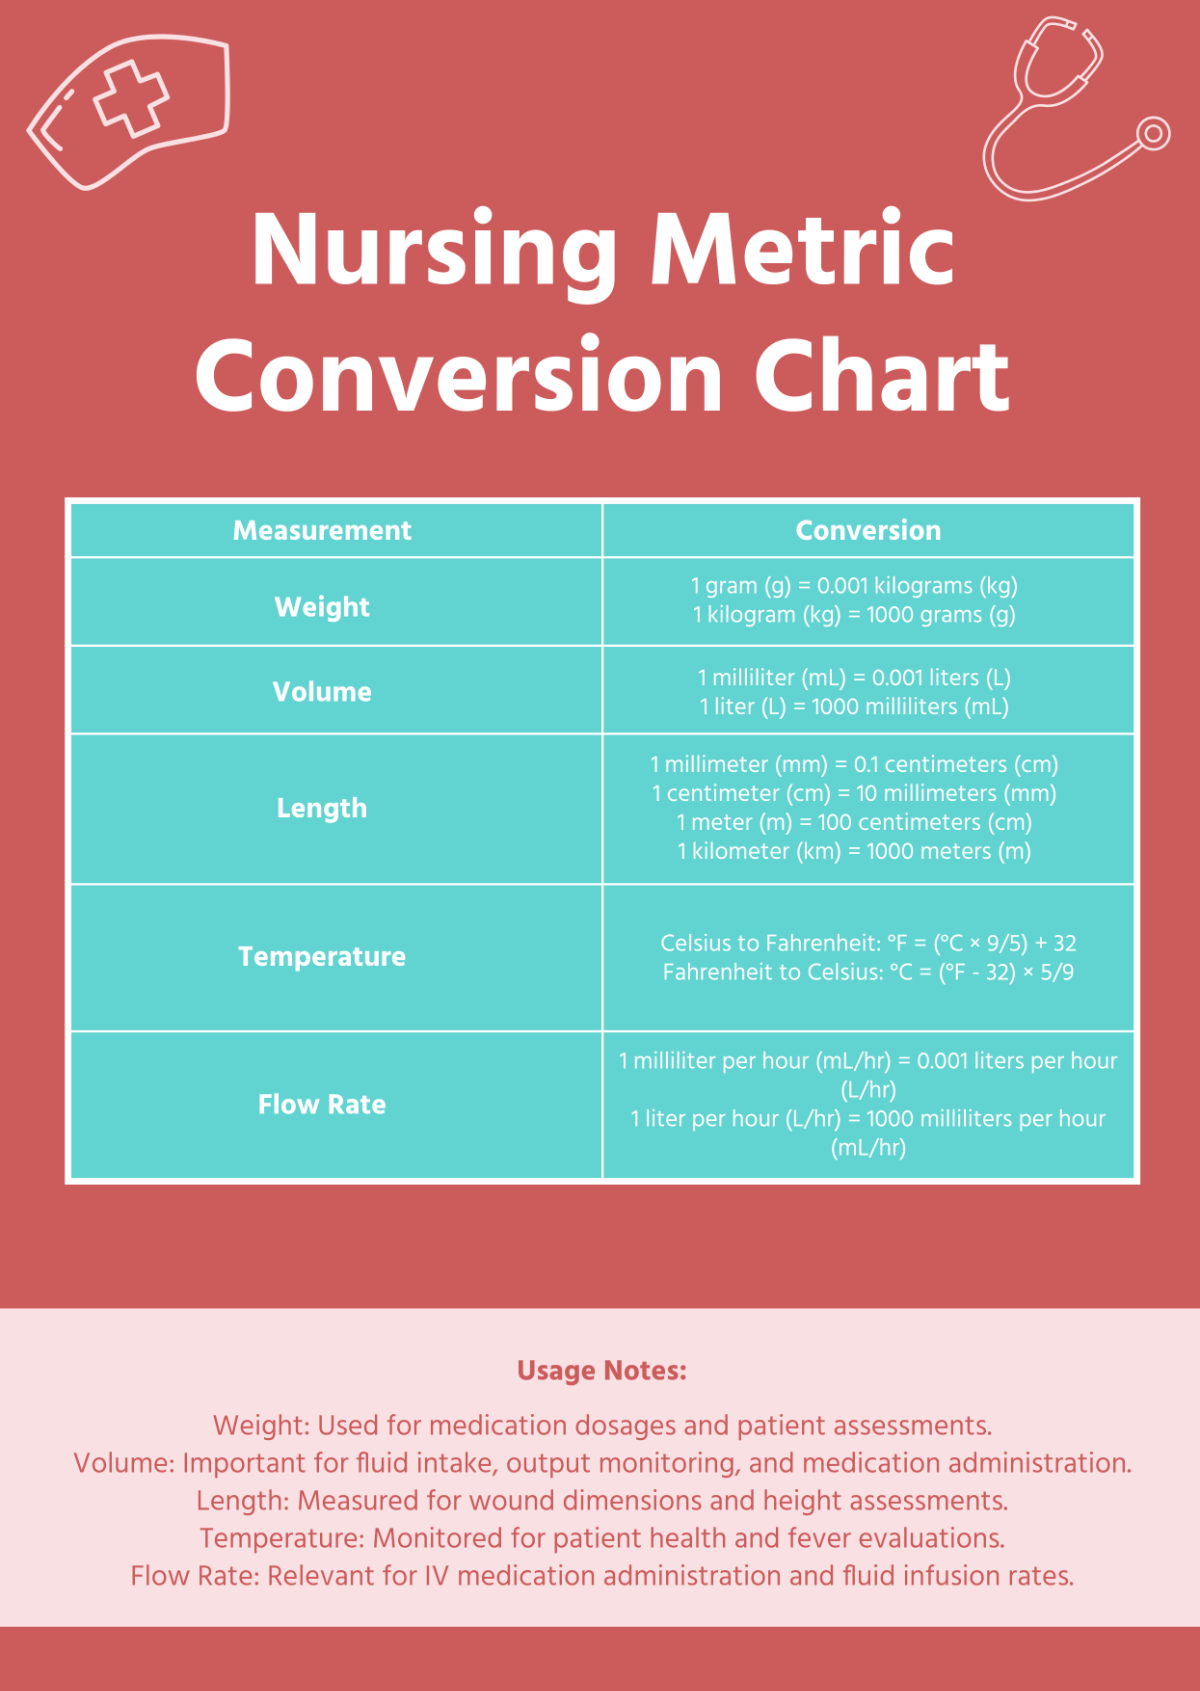
I spent years doing fluid calculations in the ICU and still ran into the occasional mess when residents were calling at 3 AM for a weight-based drip adjustment. The core issue isn't that conversion is hard, it's that most people treat it like arithmetic when it's really about unit awareness and dimensional analysis. Let me walk through how this works without the fluff. A Conversion Table For Nursing is really just a structured reference for translating between common medical measurement systems. We're talking about things like converting kilograms to pounds for pediatric dosing, milligrams to micrograms for drug titrations, or fluid ounces to milliliters for intake tracking. The table itself is trivial to find. The challenge is using it correctly under pressure.
What You'll Find in a Standard Conversion Table For Nursing
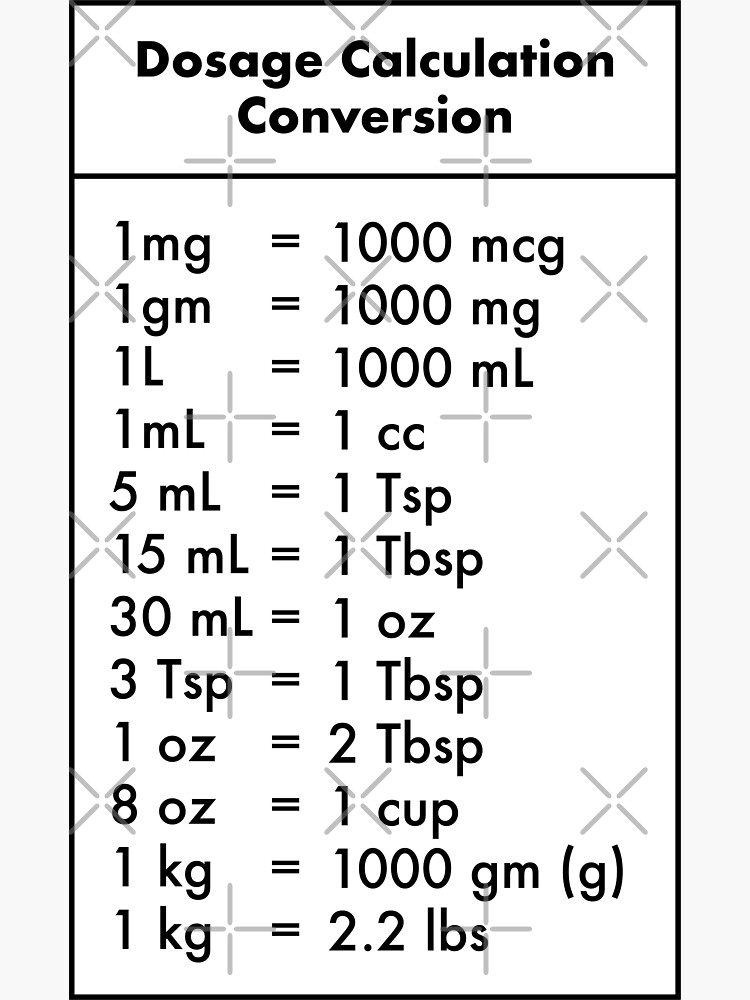
Weight conversions: 1 kilogram equals 2.20462 pounds. In practice, rounding to 2.2 is standard across virtually every hospital formulary. I've seen people round to 2 and get burned on narrow-therapeutic-index drugs. Don't do that. Conversely, carrying four decimal places through a calculation is pointless when your scale reads in whole pounds. Volume conversions: 1 fluid ounce is 29.5735 milliliters, but nursing practice uses 30 mL as the standard approximation. Again, this is intentional. A difference of 0.5 mL per dose won't move the needle clinically, but it adds up if you're tracking 24-hour output through a Foley. That's where the tiny rounding error becomes relevant. Drug unit conversions: This is where things get tricky fast. Milligrams to micrograms is a factor of 1,000. Micrograms to milligrams is division by 1,000. One zero off by a decimal place and you're administering a hundred-fold overdose. I once watched a new grad catch a 500 mcg dose being written as 500 mg on a verbal order readback. They asked me to verify. The order said 500 micrograms. The med pass system auto-filled milligrams. A simple double-check protocol saved a serious error that night.
Temperature: Celsius to Fahrenheit is (C × 9/5) + 32. I still see people approximate with C × 2 + 30. It works for rough triage but falls apart at the extremes. A fever of 39°C is 102.2°F, not 108°F. The approximation method would flag a septic patient as already in dangerous hyperthermia territory.
Get the Full Details
How to Actually Use These Conversions Without Second-Guessing Yourself
The dimensional analysis method is what I recommend. Write out the units you have and the units you need, then stack conversion factors so unwanted units cancel. Here's a real example: you need to convert a patient's weight from 165 pounds to kilograms for a vancomycin dose calculation. Set it up as 165 lbs × (1 kg / 2.2 lbs). The pounds cancel, leaving you with 75 kg. Three seconds, zero calculator needed. When you're converting between drug concentrations, like figuring out how many milliliters to administer from a vial labeled 250 mg per 5 mL when the order is for 100 mg, dimensional analysis keeps you honest. Write 100 mg × (5 mL / 250 mg). The milligrams cancel. You get 2 mL. If you skip writing it out and just divide in your head, that's when arithmetic mistakes creep in. I keep a laminated reference card at my workstation that lists the most common conversions. Not because I can't do them, but because under high cognitive load, even experts make mechanical errors. The card is a sanity check, not a crutch. I've watched experienced nurses freeze up during code situations precisely because they were mentally juggling conversions instead of focusing on the intervention.
One thing most online tables don't warn you about: some conversions depend on the substance. Density matters. A milliliter of water weighs one gram, but a milliliter of oil weighs less, and a milliliter of mercury weighs more. This comes up in compounding and in parenteral nutrition calculations where specific gravity adjustments are required. If your conversion table assumes everything is water-weight, you'll get wrong answers for anything else.
Where Conversion Tables Fail and What to Do Instead
The biggest limitation I've encountered is that printed tables don't account for patient-specific variables. A standard pediatric dose table might give you a range based on weight brackets, but it won't factor in renal function, liver status, or concurrent medications. I dealt with a situation where a standard conversion table suggested a dose that would have been toxic for a child with CrCl of 30 mL/min. The table had no column for renal dosing because it's not a pure conversion problem anymore. Electronic health record systems handle conversions better than paper tables for routine calculations, but they're not infallible. I've seen CPOE systems auto-convert units incorrectly when the order entry dropdown was set to the wrong base unit. The system assumed the prescriber entered milligrams when they'd actually typed micrograms. The conversion then propagated a tenfold error. Never trust the auto-conversion without verifying against the original order and clinical intent. For complex or high-stakes conversions, I recommend a two-person verification process. This is especially important for pediatric dosing, chemotherapy calculations, and anticoagulant weight-based infusions. The time investment is small relative to the risk. One extra set of eyes catches more errors than any table ever could.
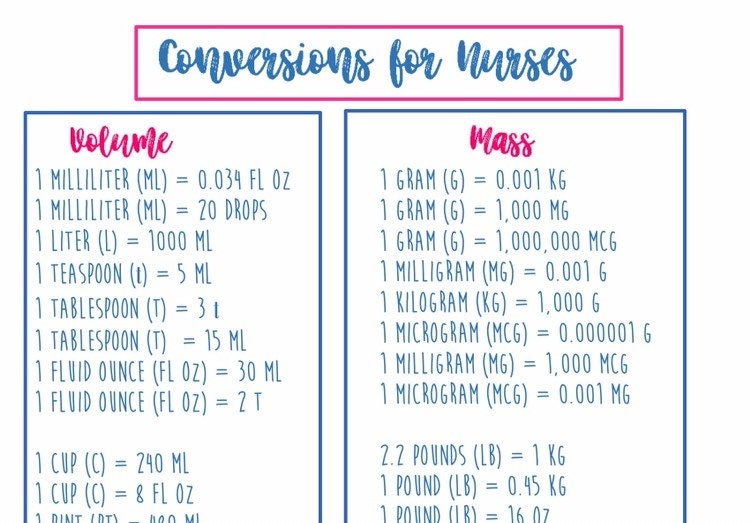
The other practical issue is that conversion tables vary by institution. Some hospitals round differently. Some use avoirdupois ounces, some use fluid ounces. Some pharmacy departments work in metric exclusively while nursing stations still reference imperial for patient education materials. Knowing which standard your facility follows matters more than memorizing a generic table. Ask your charge nurse or pharmacist which conversion standards are official at your site. If you're looking for a reliable reference, most hospital formularies include conversion tables in their dosing guidelines section. The CDC publishes freely available nursing reference materials online. Drug manufacturers include conversion information in their package inserts. There's no single universal table because clinical practice adapts conversions to context. That's actually a feature, not a bug, though it does mean you should always cross-reference with your institution's approved materials before applying a general table to patient care.