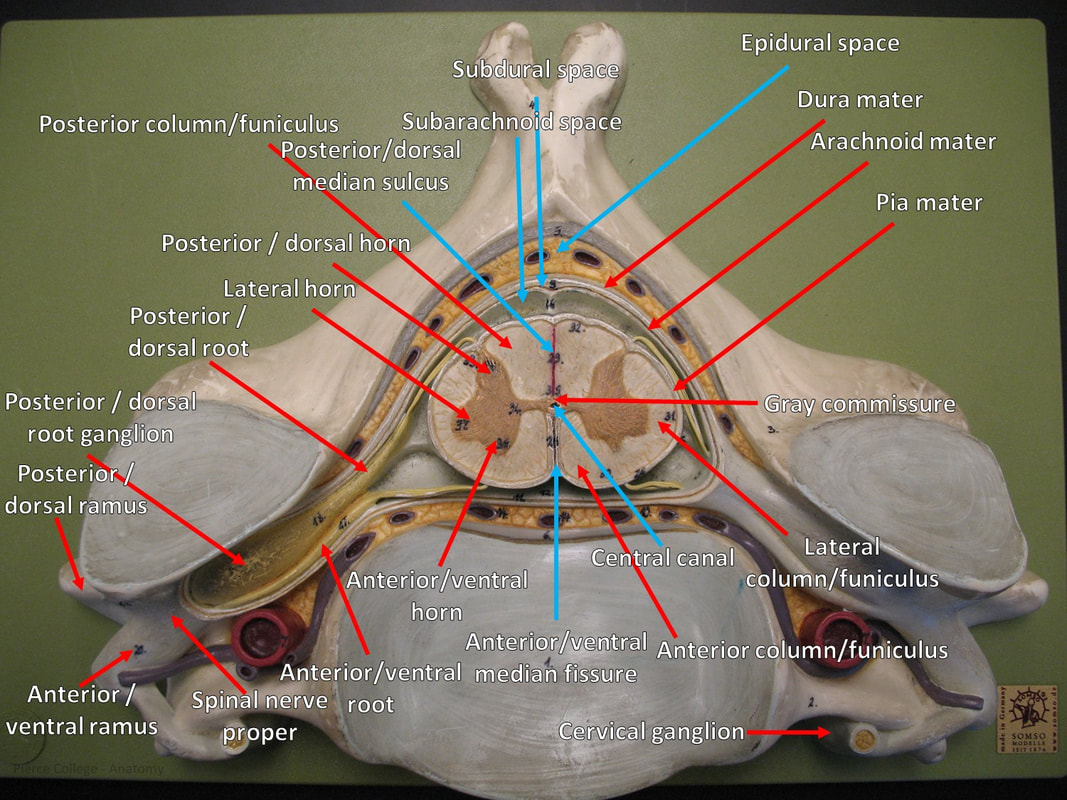
Why a Labeled Cord Anatomy Model Actually Matters
I was building a surgical rehearsal model for a laminectomy case last year when I realized something most people skip over: the labels on an anatomical model aren't decoration. They're the difference between someone seeing a spine quickly and understanding the relationships between structures. A properly labeled cord anatomy model lets a resident, a patient, or a surgical team get oriented in seconds rather than minutes of pointing and guessing. A labeled cord anatomy model is a 3D representation of the spinal column and its surrounding structures, with key anatomical features identified through color coding, numbers, or embedded tags. The cord itself — the spinal cord proper — runs centrally through the vertebral canal, and around it are structures like the lamina, transverse processes, pedicles, nerve roots, ligaments, and the epidural space. Each of these gets a distinct visual marker in a labeled version. What separates a decent labeled model from an excellent one isn't the base geometry. It's the clarity of the labels. I've seen models where the numbering system required a separate legend card and a magnifying glass because the fonts were too small to read once the model was printed. That's useless in a teaching environment where you're flipping through it between patients.
How I Build One From Scratch
I don't buy these off the shelf anymore. The commercial options are either too generic or wildly overpriced for what you get. Instead, I work from DICOM data — a CT or MRI scan — and run it through a segmentation pipeline. Here's the workflow I use: I start with the raw DICOM series. It usually comes from a standard clinical CT myelogram or a high-resolution non-contrast spine CT. The resolution matters. If your slice thickness is greater than 1.5mm, you're going to lose detail on the nerve roots and the delicate ligamentous structures. I usually resample to about 0.5mm isotropic voxels before segmentation. From there, I use a combination of thresholding and region-growing in 3D Slicer or Mimics to isolate the bony vertebrae, the thecal sac, the cord, and the exiting nerve roots. The bone segments out cleanly with a Hounsfield threshold around 200 to 2500 HU. The soft tissue structures — the cord, dural sac, ligaments — need a different approach. I use adaptive region growing with seed points placed manually. It takes longer, but the results are significantly better than automatic segmentation for the neural elements.
Once I have the separate STL files for each structure, I bring them into Blender. This is where the labeling happens. I assign distinct materials and colors to each anatomical structure. The vertebral bodies get a natural bone tone. The spinal cord itself is a pale pink. The nerve roots at each level are a bright yellow because they stand out against the surrounding structures. The ligamentum flavum gets a translucent red. The epidural fat is a soft yellow-tan. These color choices aren't arbitrary — they follow conventions that surgeons and radiologists already recognize.
Get the Full Details

The Labeling System I Actually Use
Numbers alone don't work. A model with numbers but no context forces the viewer to keep a reference key nearby, which breaks engagement. What I do instead is combine three systems: First, I use color coding as the primary identifier. Anyone looking at the model can distinguish the cord from the nerve roots without reading a single label. Second, I place small engraved text directly on or near each structure. For the vertebrae, I engrave the level — C5, T7, L2. For the nerve roots, I add a tiny tag at the exit point indicating the level. Third, I create a separate reference plate that sits beside the model with a complete legend. This plate is informational, not essential for basic orientation. The engraved text needs to be deep enough to survive handling but not so deep that it weakens the print. On a resin print, I engrave at about 0.5mm depth with a font size of no smaller than 1.5mm. Anything smaller becomes illegible after the first few printings.
A Specific Problem I Encountered and How I Fixed It
Last spring, a neurosurgeon asked me to build a labeled model of a C1-C2 region with a basilar invagination. The pathology involved upward migration of the dens into the foramen magnum with compression of the lower brainstem and upper cervical cord. Standard segmentation failed here because the bony structures and the compressed cord had nearly identical Hounsfield values in that region. The automatic threshold couldn't separate them. What I ended up doing was switching to a manual segmentation approach in 3D Slicer. I loaded the CT data and went slice by slice through the craniocervical junction, tracing the boundaries between the bone and the neural tissue by hand. It took about four hours for a region that spans roughly thirty slices. The result was a clean separation of the compressed cord from the encroaching bone. The surgeon was able to use the model to plan the decompression approach, and we ended up using it as a briefing tool with the anesthesia team the night before surgery. The workaround for this kind of problem isn't better software — it's patience with manual segmentation. No auto-segmentation tool handles pathological anatomy well. When normal anatomical boundaries break down due to disease, you fall back to trace-by-trace delineation. It's slower, but it's the only reliable method for complex cases.
Printing Considerations That Nobody Talks About
The filament or resin you choose determines how long your labels stay readable. PLA prints fine and is cheap, but it yellows under UV exposure and becomes brittle after six months of shelf life. If this model is going on a desk in a clinic where sunlight hits it, PLA will degrade noticeably within a year. ABS or PETG handles UV better and won't become brittle as quickly. For the highest detail — especially the engraved text and small nerve root structures — I recommend resin printing. A 4K or higher resolution LCD resin printer will capture nerve root structures that are less than 1mm in diameter. FDM printers simply cannot resolve that level of detail reliably. I've tried both approaches on the same model. The FDM version rendered the C8 nerve root as a blob. The resin version showed the root clearly with its proper taper and trajectory. The scale of the model also affects label readability. A 1:1 scale model is roughly the size of an actual spine section. At that scale, text under 2mm becomes nearly impossible to read. I usually create models at about 1.5 to 2 times anatomical scale. This gives the labels room to breathe and makes the smaller structures like nerve roots more visible without distorting the anatomy significantly.

Common Mistakes That Ruin a Labeled Model
The biggest mistake I see is over-labeling. Someone will try to tag every single muscle, ligament, and fascial plane. The result is visual noise. A spine model used for surgical planning doesn't need the longissimus capitis labeled. It needs the vertebrae, the cord, the nerve roots, the pedicles, and the critical ligaments. Keep the label count under fifteen for a functional model. Every label beyond that competes for attention and reduces overall comprehension. Another frequent error is inconsistent color coding across models. If your cord is pink in one model and green in another, the viewer has to relearn the system each time. Establish a consistent palette and stick with it. Pink for the cord, white or cream for bone, yellow for nerve roots, red for vascular structures, blue for the thecal sac. Once you establish these conventions, they transfer across every model you produce.
When a Labeled Model Won't Help and What to Do Instead
A 3D printed labeled model has real limitations. It cannot show dynamic relationships. You can't flex the model to see how the lamina moves relative to the cord during extension. It cannot display internal pathology like a syrinx or intramedullary tumor with the same clarity as a cross-sectional imaging study. For those purposes, the model adds confusion rather than clarity because it presents a static, surface-only view of a problem that is fundamentally internal and dynamic. When the clinical question involves the relationship between a tumor and the cord parenchyma, or the extent of cord compression across multiple segments in 3D space, a labeled physical model is the wrong tool. In those cases, a navigable 3D volume rendered on screen — something you can rotate, slice, and adjust opacity for — provides far more information. The physical model excels at teaching gross anatomical relationships and surgical approach planning. It fails when the pathology is internal to the cord or when dynamic spatial relationships matter. For educational use with students or patients, a labeled cord anatomy model remains one of the most effective communication tools available. The tactile nature of holding a physical representation of someone's own anatomy changes how people process information. I've watched patients understand their diagnosis in minutes with a labeled model when they'd been confused for months by 2D CT slices. The model makes abstract radiological findings concrete. That's the real value proposition, not the labels themselves.
Practical Download and Source Options
If you're looking for base models to modify rather than building from DICOM data, several sources exist. The Visible Human Project offers segmented anatomical data that can be adapted for spinal regions. The National Library of Medicine maintains several freely available 3D anatomy datasets. For commercially available labeled spine models, companies like Anatomical Model Store and 3D Systems offer pre-labeled variants, though you'll pay a premium for customization options. Most of these come with standard color coding but limited flexibility in label placement and font choices. The most practical approach if you work with this regularly is investing time in learning 3D Slicer and Blender. Both are free. The learning curve is real — expect two to three weeks of daily practice before you can produce a publishable model — but once you're past that threshold, you can generate labeled cord anatomy models in a few hours rather than waiting days for a commercial product. I keep a library of segmentation presets for common spinal levels. A cervical protocol, a thoracic protocol, a lumbar protocol. Each one contains the threshold values and region-growing parameters I've found to work reliably for that region. Setting up these presets takes initial effort but reduces subsequent model builds to roughly an hour from scan to labeled printable model. That's something most people don't realize is possible with free software.