How I Actually Do a Spinal Cord Assessment in the Field
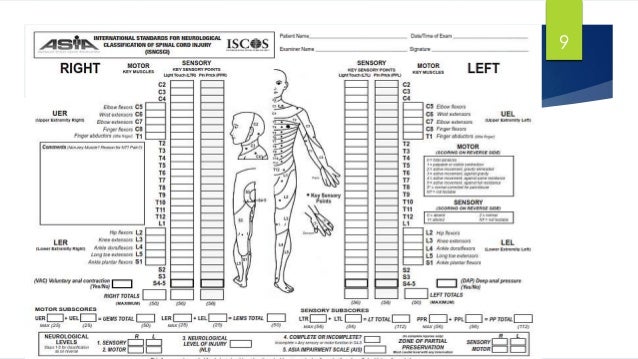
I'm writing this because the ASIA exam feels totally different on paper than it does at 2 AM in a trauma bay with a patient who's confused, in pain, and possibly under sedation. The Cord Injury Assessment framework is straightforward until you actually apply it to a real person. I've done hundreds of these, and there are things the guideline doesn't tell you. The International Standards for Neurological Classification of Spinal Cord Injury (ISNCSCI) remains the gold standard. It evaluates sensory function across 28 dermatomes and motor function across 10 key myotomes. That's it. The system is simple by design. But the execution is where things fall apart if you're not paying attention. First, confirm the patient is hemodynamically stable and any potential cervical spine clearance criteria have been met. I've seen assessors skip this step in high-acuity environments and then realize mid-exam that moving the patient risks further injury. Document it. Get imaging reviewed before you begin a formal neurological exam if you suspect an unstable fracture.
The Assessment Sequence That Actually Works
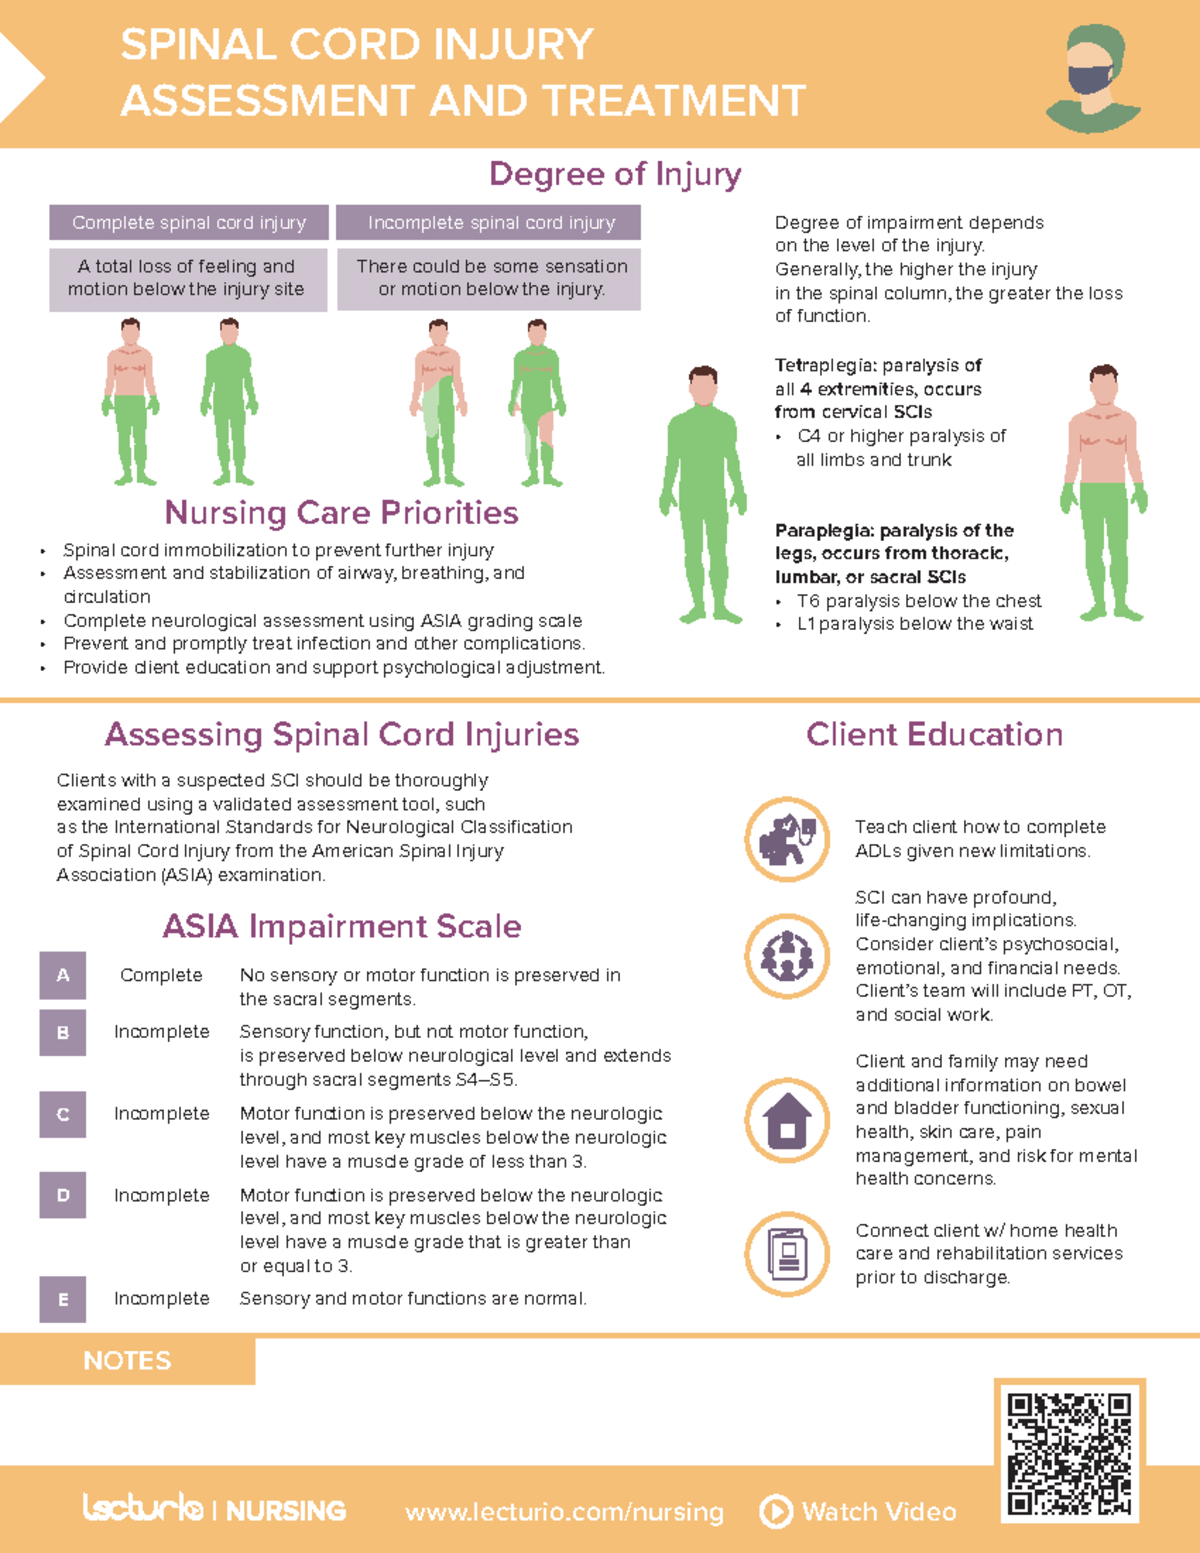
Start with sensory. Light touch and pinprick separately for each dermatome, going from sacral upward. Use a neurotip or a gentle pinch for pinprick. Light touch with a wisp of cotton. Don't rush this part. I've caught missed sacral sparing cases because the examiner didn't actually test the perianal region — a common error. If a patient appears to have no sensation below a certain level but has intact perianal sensation, that's a complete sensory examination, not a failure to examine properly. Next, motor testing. Five muscle groups on each side: C5 (elbow flexors), C6 (wrist extensors), C7 (elbow extensors), C8 (finger flexors), T1 (finger abductors), L2 (hip flexors), L3 (knee extensors), L4 (ankle dorsif lexors), L5 (long toe extensors), S1 (ankle plantar flexors). Grade each from 0 to 5 using the standard MRC scale. A patient who can't cooperate due to sedation or intubation gets a notation of N.A. (not assessable) for those muscles. Don't guess. Writing N.A. is honest and accurate. After sensory and motor, determine the neurological level of injury and the ASIA Impairment Scale grade. AIS A through E. Here's where the nuance comes in. An AIS A classification means complete injury — no motor or sensory function preserved in the sacral segments S4-S5. But here's the catch: spinal shock can make any injury look complete initially. I've had patients graded AIS A on admission who walked out of the hospital as AIS D because the true injury was only revealed after spinal shock resolved over 48 to 72 hours.
A Real Problem I've Encountered
Last year I was consulting on a high-speed MVC case. Adult male, T8 fracture-dislocation, initial ASIA exam showed no motor or sensory function below T8. We called it a complete injury and started rehab planning accordingly. Forty-eight hours later, he flinched to light touch around the inguinal region and showed a trace of contraction in the iliopsoas. Spinal shock had masked the deficit. We corrected the AIS grade from A to E at that level — which means the injury was much more complex than the initial exam suggested, possibly an anterior cord syndrome with partial sparing that wasn't evident during the shock phase. The workaround? Serial reassessment. I now document a preliminary ASIA score at the initial exam and explicitly note "pending resolution of spinal shock." Repeat the full Cord Injury Assessment within 24 to 48 hours minimum, and again at 72 hours if spinal shock is suspected. This single habit has prevented at least three wrong-prognosis calls in the past year alone.
Get the Full Details

Things the Guidelines Don't Emphasize Enough
Spinal shock is not a diagnosis you skip. It lasts anywhere from one day to four weeks, sometimes longer. During this period, all reflexes below the level of injury are depressed or absent. A patient in spinal shock may not demonstrate the bulbocavernosus reflex, and you cannot determine true completeness until it resolves. The return of the bulbocavernosus reflex is the clinical marker that spinal shock is ending — but even then, a follow-up exam is warranted within a few days to capture the full picture. Pediatric assessments are another trap. The ASIA exam was validated on adults. Kids don't always cooperate the same way. A 6-year-old with a cervical injury may not reliably report pinprick sensation or follow commands for muscle testing. In those cases, rely more heavily on observable responses, parental report of baseline function, and serial clinical observations. I use the Pediatric ISNCSCI when available, but it still has gaps, particularly for non-verbal children.
Common Mistakes I See Repeatedly
Examiners often test the wrong dermatome for a given nerve root. The dermatomal map is well-documented, but C6 is the thumb, not the entire hand. L4 is the medial malleolus, not the whole lower leg. Getting these wrong throws off the entire level determination. I carry a laminated dermatome/myotome reference on my phone now because I'd rather look it up than trust my memory under pressure. Another frequent error: not testing the key sensory points bilaterally. Left and right matter. A patient might have asymmetric deficits that change the classification entirely. I've seen AIS B misclassified as AIS C because someone only tested one side and assumed symmetry. Pre-existing conditions also interfere. Peripheral neuropathy from diabetes, prior radiculopathy, arthritis limiting range of motion — these all confound the motor exam. Document them. Note when a myotome can't be fairly assessed due to an orthopedic limitation rather than a neurological one. This distinction matters for legal and insurance purposes, and it matters for treatment planning.
What the ASIA Exam Misses
The standard assessment does not capture autonomic dysfunction. Autonomic dysreflexia in lesions above T6 is a life-threatening emergency that the ISNCSCI doesn't evaluate. Blood pressure monitoring is essential and separate from the motor-sensory exam. I add a vitals and symptom check to every assessment: blood pressure trends, heart rate, presence of headache, flushing, or nasal congestion in patients with high thoracic or cervical injuries. Missing this can be fatal, and it's not part of the formal scoring system. Bladder and bowel function assessment is also outside the scope of the standard exam. It should be done, but it's usually handled by nursing or urology teams independently. Make sure you know the results and document them in your record. A patient with a seemingly stable motor exam might have a neurogenic bladder that changes the entire care trajectory.

Downloadable Resources
The ISNCSCI form is publicly available on the ASIA website and can be downloaded as a PDF. I use the standard form with a personal addendum sheet that includes sections for spinal shock documentation, pre-existing conditions, serial assessment dates, and autonomic symptoms. This custom form has cut my charting time in half compared to starting from scratch each session. The ASIA form alone is free to download; my addendum template isn't published but can be built in under ten minutes if you work with these regularly. Here's the blunt truth: the ASIA exam is only as good as the examiner and the patient's ability to participate. If a patient is intubated and sedated, if they have bilateral upper extremity fractures, if they're too agitated to cooperate — the exam is unreliable. In these situations, MRI findings, CT myelography, and clinical judgment fill the gaps. Don't force a classification you can't justify. Document why you can't complete the exam and schedule a follow-up when the patient's condition improves. This happens more often than you'd think in acute trauma settings. Serial reassessment remains the single most important practice in spinal cord injury evaluation. One exam tells you almost nothing reliable about long-term outcome. The trend across three to five exams over the first two weeks tells you far more. I schedule mine at admission, 48 hours, 72 hours, and then weekly until stabilization. Each one refines the picture.
The field keeps moving forward too. Emerging tools like somatosensory evoked potentials and quantitative sensory testing add data points the standard exam doesn't capture. They're not replacements yet, but they're supplements worth knowing about. If your facility has access to them, use them alongside the ISNCSCI rather than instead of it.
Bottom Line
A Cord Injury Assessment done well requires patience, attention to detail, and the humility to admit when you can't get a clean answer on the first try. The system works when you follow it. It fails when you rush it or ignore what the patient is actually telling you. Serial exams, documented caveats, and awareness of the exam's blind spots will serve you better than memorizing the scoring tables alone.