How to actually use a Core Surgical Training Self Assessment without wasting your time
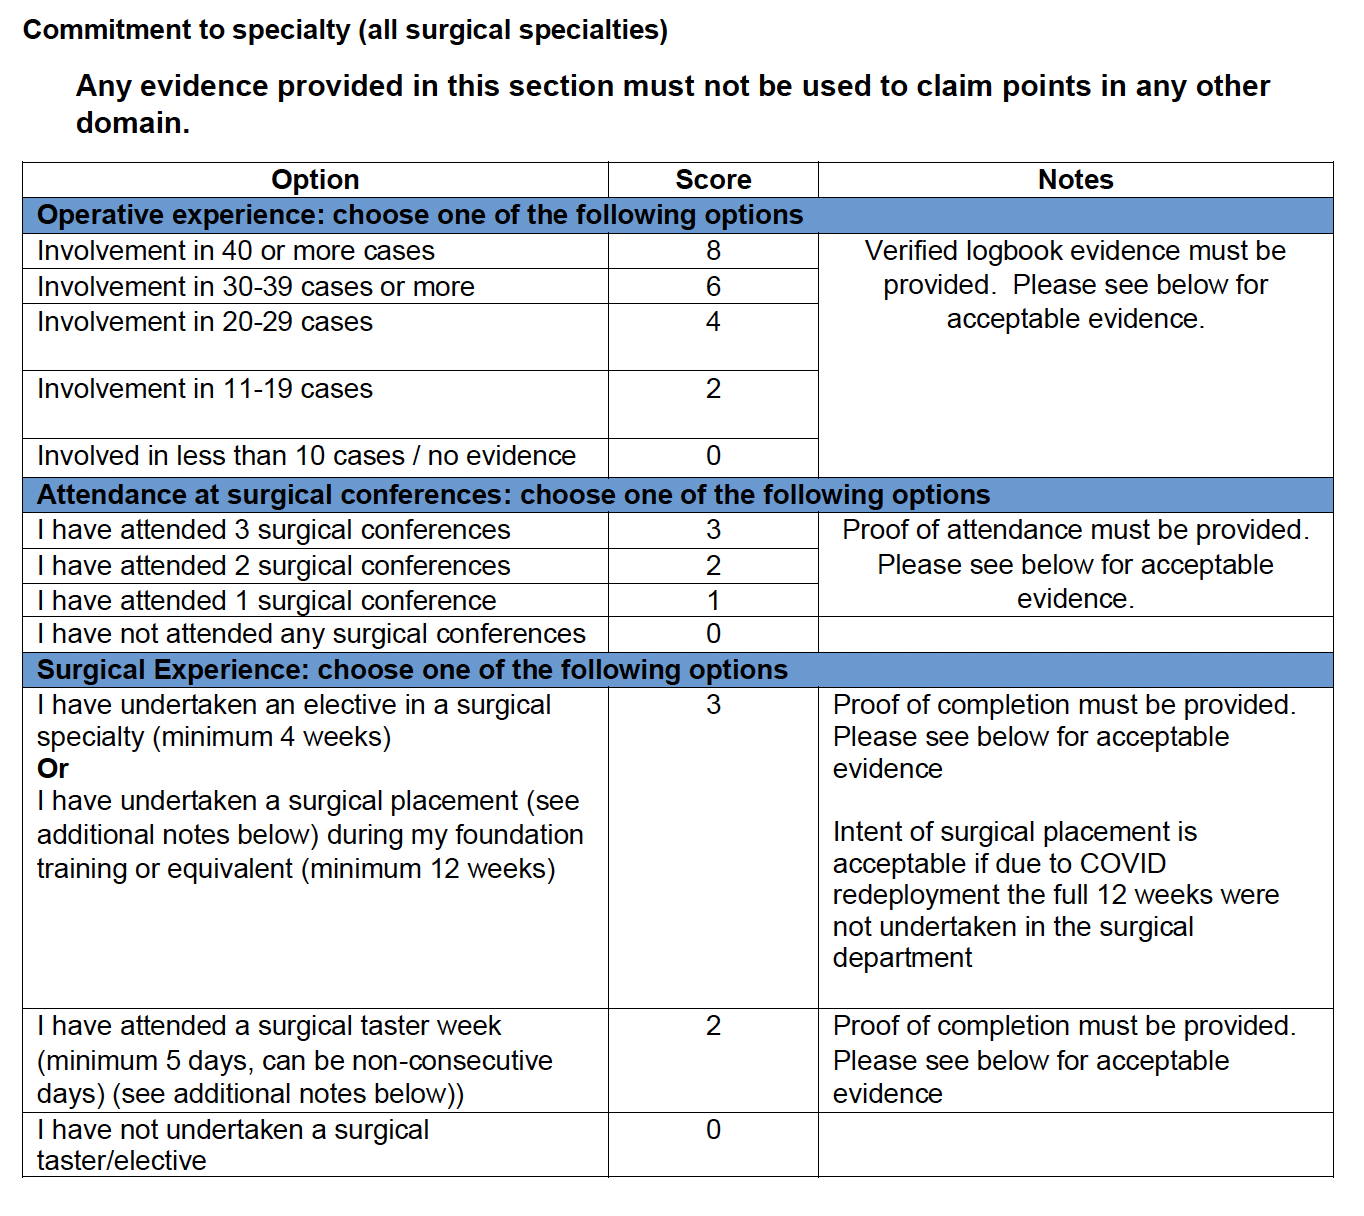
The Core Surgical Training Self Assessment is one of those documents that sounds impressive on paper but ends up being either barely useful or surprisingly actionable depending on how you approach it. I have spent more years than I care to count watching foundation doctors and surgical trainees stumble through these because nobody really explains what they are for or how to engage with them properly. The system wants you to reflect on your clinical performance across a set of competencies, but the real value comes from treating it as a working tool rather than a box-ticking exercise you panic about the week before your portfolio review. A self assessment in the CST context is a structured reflection on your progression through the first two years of core surgical training. You are expected to evaluate yourself against the curriculum competencies set out by the relevant surgical college, covering areas like operative skills, medical knowledge, professional behaviour, and clinical decision-making. The tricky part is that the curriculum does not give you a simple pass or fail grade. It asks you to demonstrate that you have reached thresholds of competence across multiple domains, and your own honest appraisal is the starting point before a supervisor or trainer signs off on anything. I learned this the hard way during my second year when I submitted a self assessment that was essentially a list of procedures I had observed rather than participated in. My supervisor pushed it back immediately. She flagged that observation alone does not satisfy the competence requirements for several curriculum elements, and that my reflection lacked any evidence of independent clinical reasoning or post-operative decision making. That feedback forced me to restructure the entire document around specific cases where I had managed patients independently, documented the rationale, and then reflected on what went well and what I would adjust next time. It took me another three weeks to redo properly, but the supervisor sign off went through cleanly the second time.
The practical workflow most people get wrong
Here is how the process normally works and where it usually falls apart. You begin by reviewing the curriculum competencies for CST. Not skimming them. Reading them carefully enough to understand the difference between demonstrating knowledge at a core level and applying it under supervision. Then you go through your portfolio and identify cases, procedures, and clinical scenarios that map onto each competency. This mapping step is the one most people skip because it feels tedious, but it is also the step that separates a coherent self assessment from a scattered collection of generic statements. After mapping, you write reflective accounts for each domain. Reflection in this context does not mean summarising what happened. It means analysing your performance against the expected standard, identifying gaps, and stating what you will do differently. A typical account that actually satisfies a trainer looks something like this in practice: you describe a case where you took primary responsibility for a patient with an acute surgical abdomen, explain how you formed a differential diagnosis, justified your management plan, and then honestly assess where your judgment was sound and where you hesitated or asked for help too late. That kind of entry takes roughly twenty to thirty minutes to write well if you have your clinical notes nearby. Guess what happens if you try to produce twelve of them the night before your review. You produce garbage, and your trainer knows it immediately.
Where the self assessment framework has real limitations
I need to be straightforward about this because so many people present the CST self assessment as if it is a comprehensive evaluation tool. It is not. The biggest limitation is that it is entirely dependent on the quality of entries you have been making throughout your training. If you have not been documenting cases, procedures, and reflective notes in real time, the self assessment becomes an exercise in fabrication or vague generalisation. That is not a flaw in the concept itself. It is a flaw in how trainees treat their portfolios over the eighteen to twenty-four months leading up to submission. Another limitation that rarely gets discussed is the subjectivity inherent in asking someone to rate their own competence. Humans are systematically poor at calibrating their own abilities in clinical settings. There was a period when I confidently rated myself as competent in several procedural skills based on self perception alone, only to have a consultant observe me during an emergency laparotomy and immediately point out that my knot tying under time pressure was unreliable and my tissue handling was too aggressive. That uncomfortable conversation completely reshaped my self assessment for the remaining domains. Self assessment works best when you deliberately test your own assumptions against objective clinical feedback rather than assuming your internal gauge is accurate. A third problem area is the curriculum's granularity. Some competencies are described in ways that make it difficult to demonstrate them in certain training environments. If you are in a department with limited exposure to certain surgical specialties or procedures, you might struggle to find relevant cases for every single curriculum element. The workaround I used was to submit alternative evidence where the curriculum explicitly allowed it, such as simulation-based competencies or cross-specialty clinical scenarios, and to document clearly why a particular surgical exposure was not available in my rotation. Trainers generally accept this if you are transparent about it and show that you pursued reasonable alternatives.
Get the Full Details

Building the actual document step by step
Start with the curriculum document. Download the latest version from the appropriate surgical college website. I usually recommend the Royal College of Surgeons versions since they are the most commonly referenced. Print it out or open it in a separate window while you work. Do not rely on memory for what the competencies actually say because your supervisor will notice any mismatches. Next, pull your logbook data. Most training programmes use a digital portfolio system, and your log of procedures, observations, and clinical encounters should already be there. Export it if possible. Having a clean dataset makes the mapping phase significantly faster. When I export my logbook entries, I usually get around four hundred to six hundred cases per year depending on rotation, which gives you plenty of material to draw from if you organise it properly. Then create a mapping table. Columns for competency number, competency description, case reference, your reflective summary, and evidence type. This spreadsheet becomes the backbone of your self assessment. It is far easier to write reflectively when you can see exactly which cases support which competencies rather than trying to hold everything in your head. I spend about an hour on this mapping stage, and it usually saves me several hours of rewriting later.
After mapping, draft each reflective account. Aim for clarity over complexity. A good entry answers four questions without being prompted: what did I do, what was the clinical context, what does the standard require, and where do I stand against that standard. Keep the tone measured. Avoid language that sounds like you are trying to sell yourself. Superlatives like exceptional or outstanding will raise eyebrows unless you have objective evidence to back them up. Moderate language with specific examples carries more credibility. Finally, review and request preliminary feedback. Before you submit anything formally, send drafts to your educational supervisor or a trusted senior colleague. Give them two weeks minimum for this step. Rushed feedback is worse than no feedback because it tends to miss structural problems. I once submitted a self assessment without external review and missed a major gap in my professionalism domain. A colleague reading it spotted it immediately because she noticed I had no entries relating to interprofessional communication or patient safety incidents, which is a conspicuous omission. That one review catch saved me from a potentially damaging review meeting.
A realistic timeline and what to expect
If you start early, the entire Core Surgical Training Self Assessment process takes roughly four to six weeks of part-time work, maybe eight to ten hours per week depending on how thoroughly you document throughout training. If you start late, it stretches to eight to ten weeks and involves considerably more stress and lower quality output. The difference comes down to whether you are writing from a habit of ongoing reflection or attempting to reconstruct months of experience retroactively. Most trainers expect your self assessment to accompany supporting evidence. This usually means signed workplace-based assessments, procedure logs, multi-source feedback summaries, and possibly teaching or quality improvement project documentation. The self assessment itself is the narrative thread that ties those pieces together. Without the supporting evidence, it reads as opinion. Without the narrative, the evidence reads as a data dump.

When this approach simply does not work
I should note that the self assessment framework can break down completely in certain situations. If you have had a prolonged period of training interruption due to illness, parental leave, or other extended absences, your portfolio may not contain sufficient material to fill the required competencies credibly. In those cases, the self assessment cannot be fabricated into usefulness. The appropriate response is to discuss with your training programme director about alternative evidence pathways or deferred submission. There is also the scenario where your training environment has significant variability in supervision quality. If your supervisors are inconsistent in signing off assessments or providing feedback, your self assessment will lack the verification layer that gives it weight, and you should flag this proactively rather than letting it appear as though you simply have no evidence. The self assessment is a self assessment, which means it is inherently subjective by design. Its value depends entirely on your willingness to be critical rather than promotional, your commitment to contemporaneous documentation, and your understanding of what the curriculum actually expects. Treat it like a clinical document rather than a personal statement, and the process becomes manageable. Treat it like a performance review you are trying to win, and you will likely produce something that falls apart under scrutiny.