Working With Coronal Sections Of The Brain
The coronal cut of brain imaging runs front-to-back, slicing you into anterior and posterior portions. It's one of the three standard anatomical planes radiologists and neuroscientists use daily. You see it constantly in MRI scans, histology slices from post-mortem dissections, and surgical planning software. Most people learning neuroanatomy get stuck on memorizing which structures appear where on each plane. That's fine if you're studying for a test. But when you're actually looking at real data, the practical details matter more than the textbook definitions. I spent years working with ex-vivo brain samples and in-vivo MRI, and I can tell you straight: coronal sections are simultaneously the most intuitive and the most frustrating plane to work with. They're intuitive because they map to how we naturally think about left and right hemisphere structures. They're frustrating because minor head positioning errors throw off your entire stack of slices within a few millimeters.
What You Actually Need To Know About The Coronal Cut Of Brain
A coronal plane is perpendicular to both the sagittal and axial planes. In neuroimaging, it's typically defined relative to the anterior commissure and posterior commissure (the AC-PC line). If you're doing manual slice acquisition rather than relying on automated reconstruction software, you need to orient your cuts perpendicular to that AC-PC line, not just parallel to the canthomeatal line like some old scanners defaulted to. That alone will save you from significant angular distortion in the temporal lobes and brainstem regions. Here's a practical problem I ran into recently that most guides don't address: when you're doing high-resolution ex-vivo histological sectioning at something like 50 micrometers per slice, even a half-degree tilt in your embedding orientation propagates into noticeable misalignment across a full coronal stack of 200 or 300 sections. I had a dataset where the hippocampus appeared to shift laterally by nearly two millimeters from the first slice to the last. It wasn't a biological effect. It was pure mechanical drift in my freezing microtome. What worked was regenerating a template from the middle slices first, then using iterative registration to warp the early and late slices back into alignment rather than trying to fix it at the embedding stage. You catch it too late once the block is already cut. In vivo, the situation is different but equally annoying. Head motion during a coronal-fMRI run can introduce slice-to-slice artifacts that look like activation. I've seen people misinterpret motion-correlated signal changes as genuine BOLD response in the medial temporal lobe. Motion correction software handles the gross translation, but the residual within-volume movement between successive coronal slices is still a real problem if you're doing event-related designs with sub-second TRs.
The Technical Setup
For MRI acquisition, a standard coronal protocol typically uses a slice thickness between 3 and 4 millimeters for clinical work, or 1 to 2 millimeters for research-grade structural scans. You're looking at FOV sizes around 220 to 240 millimeters depending on the scanner manufacturer. TE and TR values vary by sequence type, but a typical T1-weighted MPRAGE runs roughly 1900ms TR, 2.3ms TE, and a 9-degree flip angle on a 3T system. If you're working in CT rather than MRI, the coronal reformats are post-acquisition anyway. You scan axially and then reconstruct coronally. The quality depends entirely on your isotropic voxel size. You want 0.5mm or better if you plan to do multiplanar reconstructions without stair-step artifacts. Anything thicker and the coronal view starts looking jagged, especially around the orbits and the petrous ridges. For histology, the fixation protocol matters more than the cutting technique itself. Perfusion-fixed brains held in 4% PFA for at least 48 hours at 4 degrees Celsius maintain enough structural integrity for clean coronal sections. Under-fixed tissue tears at the corpus callosum and the hippocampal formation every time. Over-fixed tissue becomes brittle and fragments. Both scenarios waste days of work.
Get the Full Details

Common Structural Landmarks You'll See
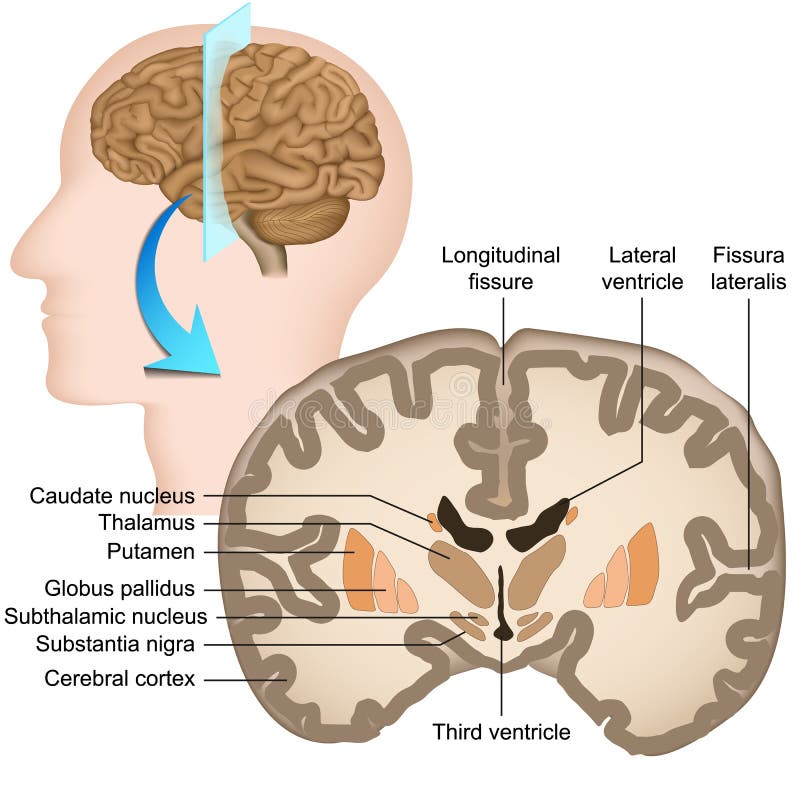
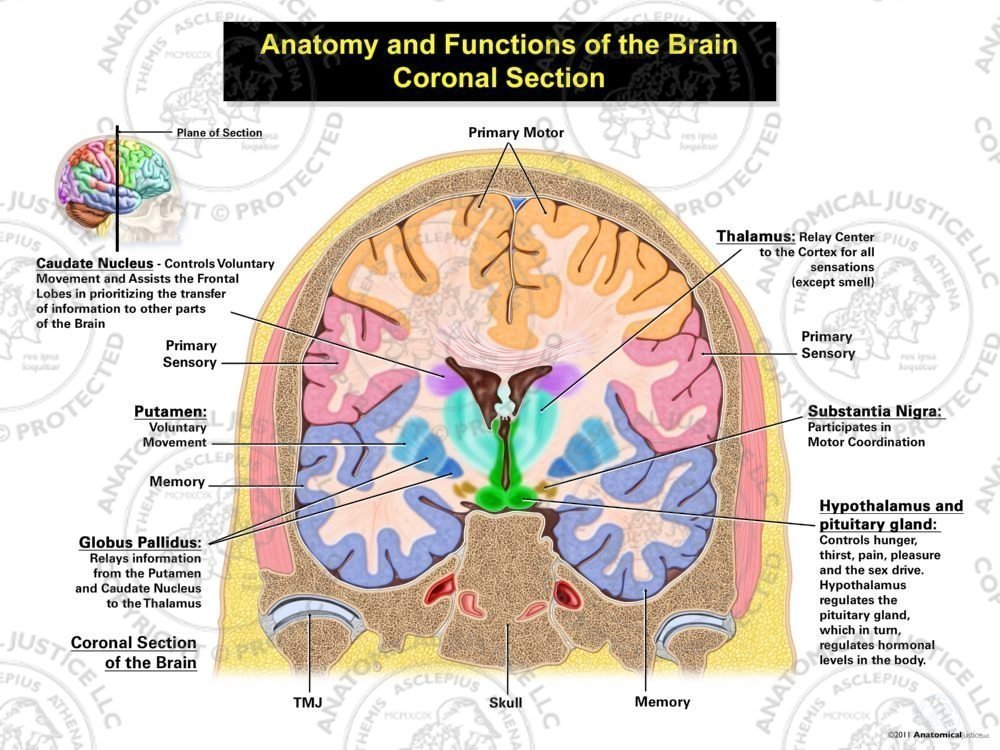
Cutting coronally through the brain gives you a particular view of deep structures that axial slices obscure. The lateral ventricles appear as distinct C-shaped or comma-shaped cavities. The caudate nucleus hugs the lateral wall. The putamen and globus pallidus sit lateral to the internal capsule, which appears as a bright V or Y shape on T2-weighted images due to the myelinated fibers running through it. The thalamus occupies the central region flanking the third ventricle. The hippocampus is where coronal sections really earn their keep. Axial views compress it into a thin ribbon that's easy to miss. In coronal, you can actually distinguish the head, body, and tail. You can see the dentate gyrus curling inside. This is also where you identify the Cornu Ammonis subfields if your resolution allows it. Clinical raters use coronal slices specifically to measure hippocampal volume for temporal lobe epilepsy workups. The amygdala sits anterior to the hippocampal head, roughly at the level where the temporal horn of the lateral ventricle is still visible. On coronal sections it looks like a small almond-shaped cluster deep in the temporal pole. Size variability here is enormous between individuals, which is why volumetric analysis requires careful boundary definition rather than relying on automated segmentation tools without manual oversight.
Pitfalls That Wreck Your Data
The biggest mistake I see people make is assuming coronal slices are symmetric left and right. They're not. Even in a perfectly healthy brain, you'll see asymmetry in the planum temporale, the Hippocampus often runs slightly longer on the left, and the Sylvian fissure angles differently on each side. Treating asymmetry as an error and trying to average it out is how you lose the signal you actually care about. Another issue is partial volume effect. At 3mm slice thickness with 1mm gap, you're missing roughly a third of the tissue between slices. For cortical thickness measurements this is catastrophic. For gross anatomy it's fine. Know which regime you're in before you interpret the data. Modern sequential acquisition with no gap helps, but you still get signal loss at the slice edges from RF pulse profile limitations. For people doing manual tracing or segmentation, coordinate systems matter more than you'd expect. MNI space, Talairach space, and native space all place the same anatomical landmark in different coordinates. I've had to re-register entire datasets because someone exported coordinates in Talairach but the atlas they were comparing against was in MNI. The difference isn't trivial around the temporal and frontal poles.
And if you're working with pathological specimens, coronal cuts through tumor tissue or atrophy patterns can be misleading if you don't account for tissue deformation. Resection cavities, edema, and mass effect shift surrounding anatomy. What looks like a abnormal signal in a distant structure might just be displacement from the primary lesion. Always compare to the contralateral side first before calling anything abnormal.
Where This Method Falls Short
Coronal sections are not ideal for visualizing long-range white matter tracts. If you need to trace connections from frontal to occipital cortex, you're better off with diffusion tensor imaging and tractography rather than relying on sequential coronal slices. The tracts run either parallel or oblique to the cutting plane, which means they appear as tiny cross-sections scattered across dozens of slices rather than continuous pathways. You can reconstruct them, but it's tedious and error-prone. For functional localization, the coronal plane alone is insufficient. You need to combine it with axial and sagittal views to pinpoint activity. A BOLD signal change in a coronal slice could be in the precentral gyrus, the supplementary motor area, or the cingulate cortex depending on the exact anterior-posterior position. Tri-planar viewing isn't optional, it's necessary. Automated segmentation tools like FreeSurfer and FSL's FIRST do a decent job extracting subcortical structures from coronal-space data, but they struggle with the hippocampus and amygdala in aging populations or in cases with mild atrophy. I've seen segmentation errors of 15 to 20 percent in those regions compared to manual tracing by trained raters. If you're doing clinical research where hippocampal volume is your primary outcome measure, budget time for manual verification regardless of what the software outputs.
Getting Started Practically
If you're new to interpreting coronal brain sections, start with the Allen Brain Atlas or the Neuroanatomy Atlas from the University of Michigan. They have high-quality reference images organized by stereotaxic coordinate, so you can match what you're seeing in your own scans to a known template. Don't try to learn from random internet images. The lighting, contrast, and orientation vary wildly between sources, and that creates confusion faster than anything else. For your own imaging work, always acquire a localizer scan first. A quick low-resolution coronal and sagittal scan before your main sequence tells you exactly where your head is positioned and lets you align the prescan planes properly. Skipping this step and just starting your high-res acquisition is how you end up with the cerebellum cut off at the bottom of every slice and no useful data above the foramen magnum. Save your raw data in DICOM format and keep your acquisition parameters documented. I can't count the number of times I've come back to an old dataset months later and couldn't remember whether it was T1 or T2 weighting, what the slice thickness was, or whether there was a gap between slices. The DICOM headers contain all of this, but only if you actually preserve the files instead of converting everything to NIfTI and deleting the originals.
The coronal cut of brain remains one of the most practically useful ways to visualize neuroanatomy. It's not the most glamorous plane, and it has well-known limitations, but it's the one you'll reach for most often once you get past the initial learning curve. Focus on understanding the landmarks, watch for motion and alignment artifacts, and verify what your automated tools are actually doing before you trust their output.