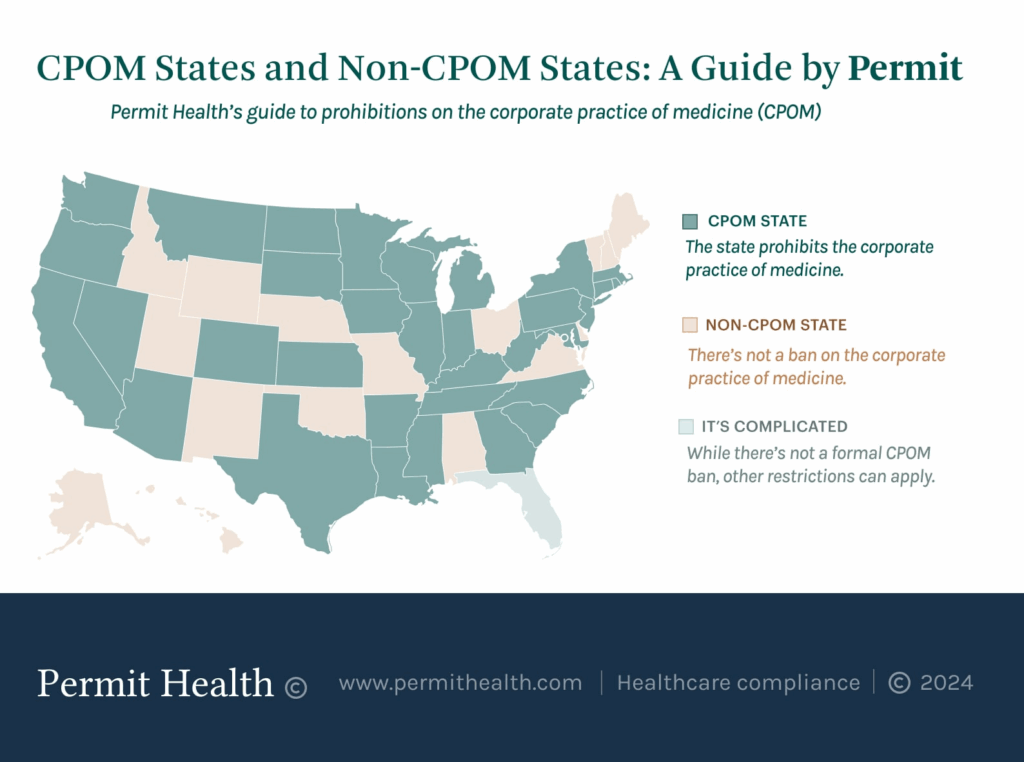
Why You Shouldn't Trust a Generic CPOM Chart
I spent about three weeks last year building out a Corporate Practice Of Medicine 50 State Survey for a client launching an AMP (Alternative Practice Model) in Texas. They had already bought a pre-made template online for $400. By day two, they were on the phone with me because their Nevada entity was getting slammed by the state board for "corporate interference" in a medical direction clause that the cheap survey listed as "permissible." It wasn't. The survey got Nevada wrong, and more importantly, it missed the regulatory nuance that actually matters on the ground. That's the problem with these surveys. Most are lazy compilations scraped from statutes without the case law, advisory opinions, or enforcement history. A state might say CPOM doesn't apply to physician-owned LLCs on its face, but the actual test comes from a 2018 Board of Medical Examiners opinion that nobody thought to include. You end up structuring an entity around a rule that doesn't reflect reality.
Corporate Practice Of Medicine 50 State Survey
Here's how I actually build these, and what you need to verify before you rely on any version of one. Start with the statute. Every state has something. Some call it CPOM, some call it the unauthorized practice of medicine statute, some codify it through their professional corporation laws, and a few don't have it written down at all but enforce it anyway through board discipline. Florida is one of those. Their statute is narrow on paper but the board has taken action against management companies for things that technically look fine if you only read the code. I learned that the hard way in 2022 when a client of mine had a perfectly compliant management services agreement that still drew a cease-and-desist because the wording around "clinical supervision" triggered a board interpretation we'd never seen before. The workaround was clean once we understood the actual concern. The board wasn't objecting to the corporate structure at all. They were objecting to the specific language in the MSA that gave the management company signing authority over clinical scheduling protocols. We rewrote that single section, moved scheduling decisions to a physician advisory committee with documented voting records, and the board dropped it within sixty days. The entity structure was fine. The contract language was the problem. A survey wouldn't have caught that because it's not in any statute or regulation. It's pure enforcement posture.
So here's the actual method: First, I pull every state's relevant statute and any attorney general opinions that touch on corporate practice restrictions. That takes me to the second step, which is checking recent board actions and consent orders from the past five years. This is where you find the gap between what the law says and what the regulators actually care about. I cross-reference those findings against the model structures—PC, AMP, AMA, IPA, professional LLC—and flag which combinations are safe, which are gray, and which are dead on arrival in each jurisdiction. The output isn't a simple chart. It's a matrix that shows permitted structures, prohibited arrangements, required physician ownership percentages, and any pending legislative changes that could shift the ground beneath an existing setup. I include citation to the specific statute, relevant case law or board opinion, and a practical risk rating based on enforcement frequency.
Get the Full Details

Now, the uncomfortable part. A CPOM survey will never be fully reliable on its own. Here's why. Regulators change their minds without changing the law. I've seen states where a clear precedent existed for ten years and then suddenly a new board composition started enforcing a stricter interpretation with zero statutory basis. There's no public notice period. You just get a surprise audit or a complaint. Any survey is a snapshot of enforcement posture at a point in time, and that poster decays fast. Second, many states have carve-outs that are narrow and technical. Texas allows professional entities through its Professional Entity Act, but the carve-out only covers entities where all owners are licensed professionals in the same discipline. Throw an investor into the mix even at one percent, and you're outside the protection. Some states let you structure around CPOM entirely through intermediary entities like management service organizations, but the MSCA (Management Services Contract Act) requirements are state-specific and deeply detailed. Get one requirement wrong and the whole arrangement collapses.
Third, and this is the part most surveys completely ignore: federal and local layers. Even if a state permits your structure, you still need to clear Medicare billing rules, state Medicaid programs, hospital credentialing bylaws, and insurance network agreements. A structure that looks clean on the CPOM side can get revoked at the payer level because the plan sponsor's medical policy committee doesn't recognize the arrangement. I had a client in Illinois whose AMP was legally sound under state law but got denied participation in two major commercial networks because the payer couldn't reconcile the ownership structure with their fraud and abuse screening questionnaire. They ended up restructuring the holding company and lost four months of revenue while the change propagated through every contract. If you're serious about this, here's what I'd recommend instead of buying a pre-made survey. Start by identifying your target states and the specific business model you're pursuing. Then get a baseline reading from the state medical board website and the bar association's healthcare section. Most states publish FAQs or advisory opinions that are more current than any statute. From there, hire someone who actually practices in those states to review the structure you're planning. The cost is real, but it's nowhere near the cost of reorganizing after you've already incorporated, signed leases, and onboarded providers. The surveys out there will save you time on initial research. They'll point you to the right statutes. But they are not a substitute for actual legal review of your specific operational model. That's the difference between knowing the rule and knowing how the rule gets applied when someone actually tries to use it.
I've been doing this long enough to stop trusting charts and start trusting process. The process is messy, it's slow, and it requires actual human judgment at every step. But it's the only way to avoid the kind of mistake that turns a $400 survey into a six-figure compliance problem.