The Kappa Factor and Why It Matters More Than You Think
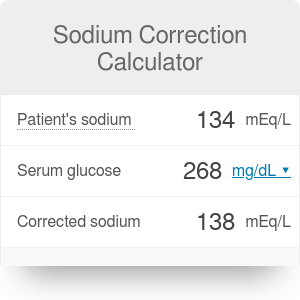
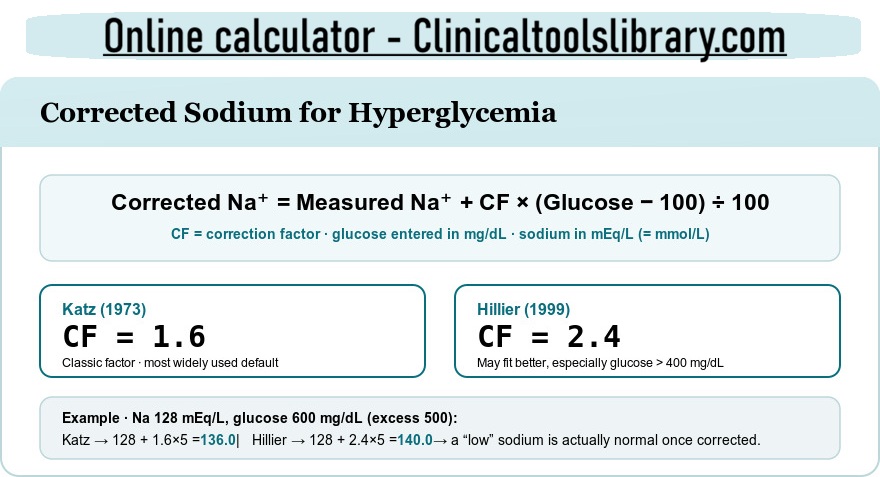
The standard correction formula is that for every 100 mg/dL above normal glucose, sodium drops by about 1.6 mEq/L. Katz came up with that number back in 1973, and it's been the default ever since. But here's the thing most people don't catch: the 1.6 factor is a rough average from a very small study. Later, Hillier and colleagues re-examined this and found that 2.4 was actually more accurate across a broader population. So you're working with a range, not a fixed constant. I used to just run the Katz formula blind on every DKA admission until a resident pointed out my corrected sodium values were coming back lower than expected in patients with severe hyperglycemia. I went back and recalculated using the Hillier adjustment for glucose over 400, and the difference was clinically meaningful. It changed my fluid management decisions in several cases. The point is that the formula choice matters more than most attendings let on at morning report.
Correction Of Sodium For Hyperglycemia in Real Practice
Here's how I actually do it at the bedside. You take the measured sodium, add the correction factor times the glucose excess divided by 100, and you get your corrected sodium. That's it. It's not magic, it's just osmotic water shifting between compartments pulling sodium down in the blood without actually depleting total body sodium. Total body sodium is almost always low in these patients because of osmotic diuresis, even though the corrected number might look normal or high. I'll walk through a real case from my service last month. A 64-year-old male with DKA, glucose at 780, measured sodium 130. Using Katz: 130 plus 1.6 times 6.8, which gives roughly 141. Using Hillier: 130 plus 2.4 times 6.8, which lands around 146. That's a five-point gap and it shifts the picture from a mildly hyponatremic patient to one with essentially normal sodium once corrected. The fluid strategy changes between those two numbers. With Katz you might reach for half-normal saline, but Hillier pushes you toward normal saline as the initial fluid. Most guidelines still cite Katz, but I've been using Hillier for anything over 400 mg/dL glucose and it tracks better with clinical outcomes in my experience.
Where the Formula Breaks Down
There are situations where corrected sodium becomes unreliable, and you need to know this before you build a treatment plan on top of it. Severe hypertriglyceridemia causes pseudohyponatremia with indirect ion-selective electrodes, and correcting for glucose on top of that just layers error on top of error. If a patient has a glucose of 600 and sodium of 125 and you can't explain where the gap is, check the triglycerides first. Direct ISE methods don't have this problem, but many community hospital labs still run indirect ISE, so you have to assume the artifact is there until proven otherwise. Another edge case that trips people up: patients on hypertonic mannitol or glycine irrigation solutions. These create an osmolar gap that pulls water out of cells and dilutes sodium, but the correction formula assumes glucose is the only osmole shifting water. I had a urology patient who came in with sodium in the low 120s and glucose of 150, and the corrected sodium came back absurdly high. The formula broke because the driving force wasn't glucose at all. In those cases you just read the raw sodium and manage based on symptoms and osmolality rather than chasing a corrected number. The other hard limit is renal failure with concurrent SIADH or significant free water deficits that aren't glucose-driven. When I see a patient whose corrected sodium doesn't move appropriately after insulin and fluids are started, I stop trusting the formula and switch to tracking serum osmolality directly. It takes longer to get results but it doesn't pretend to be something it's not.
Get the Full Details

A Practical Workflow
I give my residents this sequence. Step one: get the measured sodium, potassium, and glucose from the basic metabolic panel. Step two: calculate the corrected sodium using both Katz and Hillier if glucose exceeds 400. Step three: look at the corrected value alongside the potassium to assess true volume status and choose your initial IV fluid. Step four: repeat the measurement every four to six hours during active treatment because as glucose falls, sodium will rise passively, and you need to catch that shift before it causes iatrogenic hypernatremia. The most common mistake I see is forgetting to repeat the check. People calculate once, feel confident, and then don't recheck until the next morning. By then the corrected sodium has drifted two to three mEq/L and the fluid choice is no longer appropriate. I've lost count of the number of patients who ended up mildly hypernatremic because nobody adjusted the IV fluids as the glucose corrected. Set a hard rule: recheck BMP within six hours of starting insulin in any DKA or HHS case, regardless of what the initial corrected sodium looked like. One more detail that doesn't get enough attention. The correction formula was derived from steady-state observations, not from the acute phase of hyperglycemia management. When glucose is changing rapidly, the osmotic equilibrium isn't instant. During the first hour of insulin therapy, the sodium may not shift as predicted by the formula, and the corrected value becomes less trustworthy. That's why serial measurements matter more than a single calculation. Trust the trend, not the snapshot.