How to Actually Get External Anatomical Labels Right
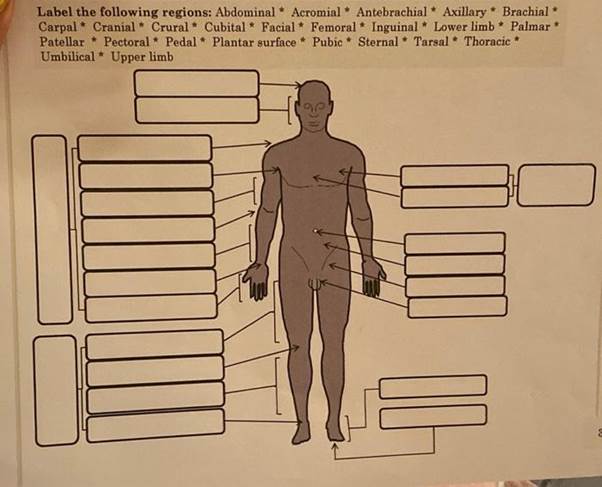
I have seen more students lose points on practical exams because they labeled the antecubital fossa as simply the "arm" than any other single mistake. It is not a tricky subject by nature, but it demands precision that most people do not approach with enough seriousness. Getting the terminology straight matters because a mislabeled region can cascade into misunderstanding clinical instructions, imaging reports, and procedural documentation. The first thing you need to do is ignore the textbook diagrams that try to be comprehensive and instead work from a single, clean reference at a time. Start with the standard anatomical position — standing upright, arms at the sides, palms facing forward. Every external region you label assumes this position as the baseline. If the figure you are working from is in a different position, your labels will drift and you will not even notice it happening until you are halfway through the exercise. I spent a week teaching a group of nursing students how to label the upper limb regions, and I stopped counting the number of times someone put "axillary" where "brachial" should go. The axilla is the armpit. The brachium is the anterior or posterior compartment of the upper arm between the shoulder and elbow. These are not synonyms. Mixing them up in a clinical context means someone might document the wrong site for an injection or a lesion assessment.
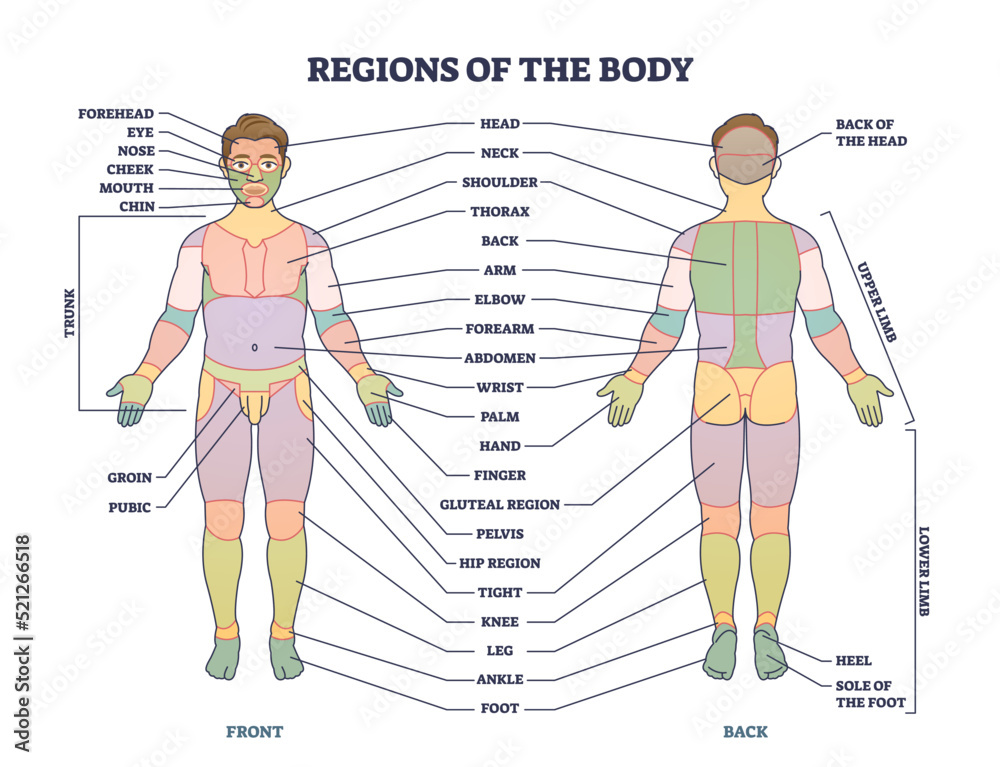
Here is the breakdown most people actually need when they sit down to do this, starting from the top and moving down: Head and Neck: Frontal region (forehead), orbital region (around the eye), nasal region (nose), oral region (mouth), mental region (chin), cervical region (neck). The cervical region itself has subdivisions — anterior, lateral, and posterior — and on an external labeling exercise you need to know which side of the neck you are pointing at. Upper Extremity: Acromial region (shoulder tip), brachial region (upper arm), antecubital region (anterior elbow fossa), olecrational region (posterior elbow point), forearm divided into radial (lateral) and ulnar (medial) regions, carpals (wrist), palmar (palm), and digital (fingers).
Trunk: Thoracic (chest), sternal (breastbone area), abdominal subdivided into epigastric, umbilical, hypogastric, and lumbar regions, and the gluteal region (buttock). People consistently forget the inguinal region — the groin area — which sits right above the thigh and is clinically important for hernia assessment. Lower Extremity: Femoral (thigh), patellar (kneecap), popliteal (back of the knee), crural or tibial (shin area), fibular (lateral lower leg), malleolar (ankle), plantar (sole of foot), and digital (toes). When I was learning this myself, I used a simple technique that still works: trace the outline of a body on paper and label each region by writing the term over the area and drawing a line to the name. Do it freehand without tracing a diagram underneath. This forces your brain to locate the region spatially rather than just matching words to pictures. I did this for about two hours over three days and went from taking twenty minutes per labeling exercise to under four minutes with full accuracy.
Get the Full Details
One counter-intuitive thing about external anatomy labeling is that you do not need to memorize every single regional name. What you actually need is the relationship map between regions. If you know the antecubital region sits between the brachial and antebrachial (forearm) regions, you can reconstruct the rest of the diagram on the fly. Exams and clinical scenarios test spatial relationships far more often than they test rote recall of isolated terms. Another thing beginners miss: directional terms matter more than regional names in practical labeling. If a question asks you to label structures relative to one another, knowing that the patellar region is anterior to the popliteal region and medial to the fibular region is worth more than memorizing that the popliteal region exists at all. I saw a student once spend thirty seconds searching for the term "popliteal" on a practice exam when the question really just wanted "posterior knee." The answer was right there in plain language. That is a common test design pattern. There is a practical shortcut that is not widely discussed. When labeling external anatomy for real-world use — clinical notes, patient communication, procedural documentation — many of the informal regional terms get compressed into shorthand that is universally understood. "Antecubital" becomes "AC," "popliteal" stays "pop," "inguinal" stays "ingu." This shorthand is not appropriate for formal written work but it is what you will hear in actual clinical settings. Knowing both the full term and its colloquial equivalent prevents confusion when you are listening to a clinician give handoff instructions.
Now, the honest limitations. Labeling external anatomy correctly has a real bottleneck: many reference images are drawn in a way that makes regions ambiguous. A diagram of the torso might shade the flank region so lightly that it looks like empty space, or the inguinal crease might be missing entirely, making it impossible to distinguish the abdominal wall from the thigh. I encountered this problem while preparing teaching materials and found that the workaround was to overlay a transparent grid on the diagram, then label based on bony landmarks rather than surface shading. The iliac crest, the pubic symphysis, and the inguinal ligament form the boundaries you need. Surface color and shading are unreliable. Bone landmarks are not. Another limitation worth stating plainly: external labeling alone does not translate to internal understanding. You can label every external region of the torso perfectly and still confuse the anatomical layers beneath. The abdominal wall has four muscle layers — external oblique, internal oblique, transversus abdominis, and rectus abdominis — and none of those are visible on external labeling exercises. This is not a flaw in the labeling method. It is a reminder that external anatomy is a foundation, not the complete structure. If you are looking for a resource to practice with, the OpenStax Anatomy and Physiology textbook has a free online labeling module that covers the major external regions with interactive drag-and-drop exercises. It is not perfect — the lower limb diagrams are a bit simplified — but it is free and accurate enough for foundational work. For a more comprehensive set of labeled diagrams, Gray's Anatomy for Students has a digital atlas section that includes surface anatomy overlays, though the subscription access varies by institution.
The most effective practice routine I have found for this is ten minutes of active labeling per day over five consecutive days. It sounds minimal but it works because spaced repetition beats cramming for spatial terminology. Your brain needs time to wire the regional names to their positions, and ten focused minutes a day is enough to build that mapping without burning out. Two-hour sessions once a week produce worse retention and more labeling errors under time pressure. I also want to flag a specific edge-case that comes up repeatedly. When labeling the lower abdomen, the difference between the hypogastric (pubic) region and the inguinal region is subtle on some diagrams but critical in clinical documentation. The hypogastric region sits directly above the pubic bone. The inguinal region sits just above and slightly lateral to it, where the abdominal wall meets the thigh. I had a student who labeled the inguinal region as hypogastric on a practical exam and lost six points across three separate questions because the grader applied the error consistently. Do not conflate these two on any assessment. External anatomy labeling is not difficult, but it requires a methodical approach that most people skip. Start with the standard position. Learn the regional relationships, not just the names. Use bone landmarks when diagrams are ambiguous. Practice in short, daily sessions. And pay attention to the regions that look similar but are clinically distinct — the inguinal and hypogastric, the axillary and brachial, the patellar and popliteal. Those are where the marks get lost.