Getting a Cost Benefit Analysis Actually Right in Healthcare
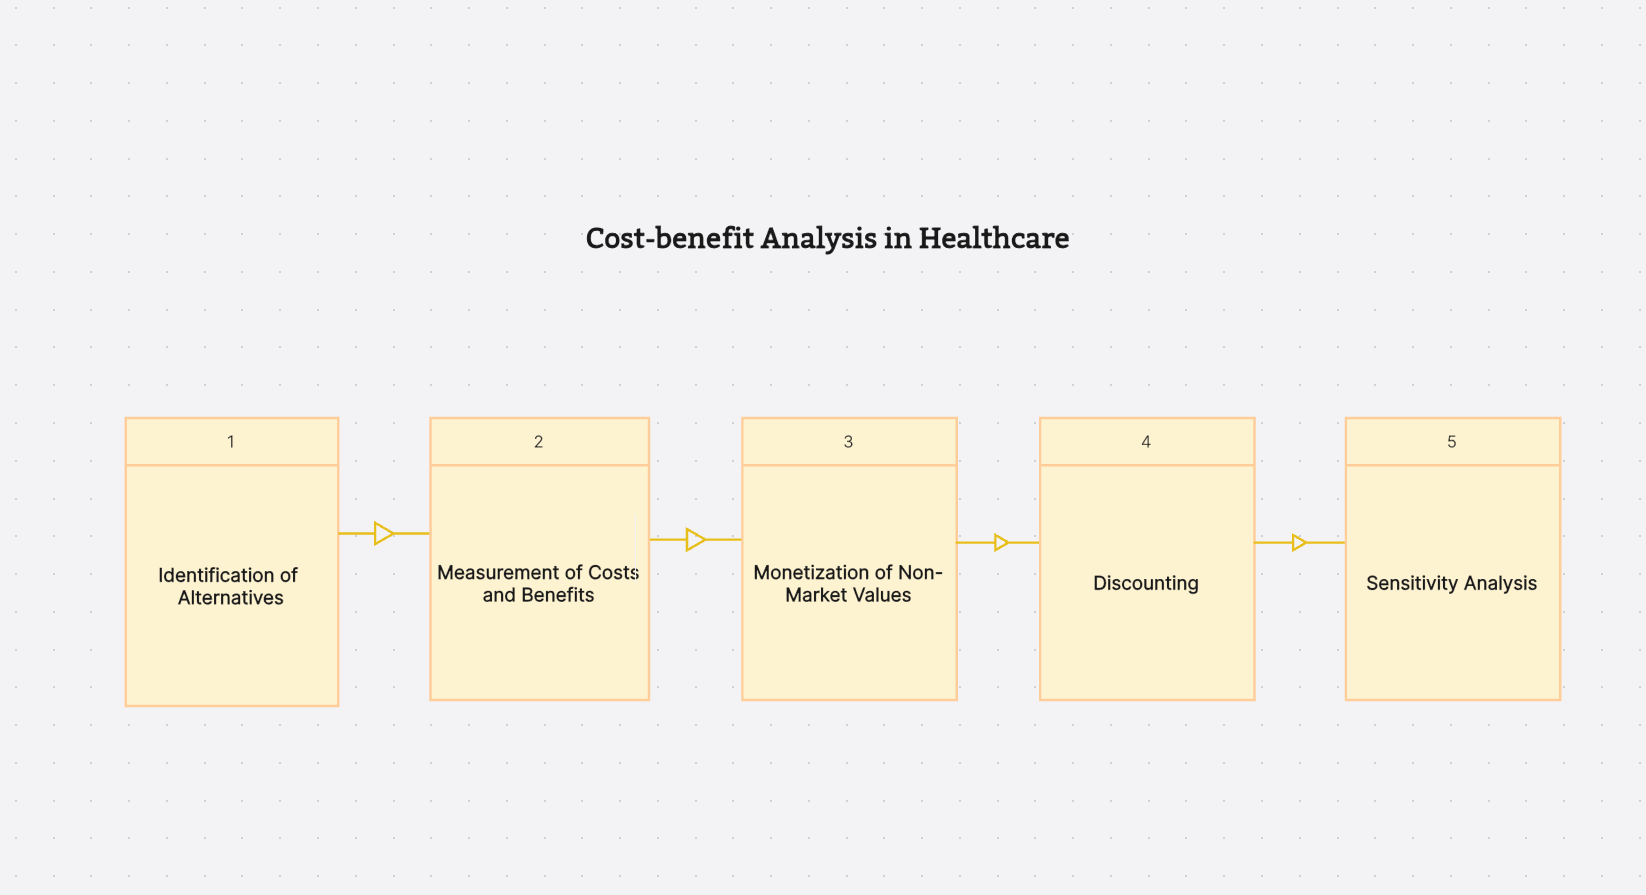
A lot of people think a Cost Benefit Analysis is just a spreadsheet with fancy formulas. It isn't. The actual work starts before you open Excel, usually in a conference room where someone asks you to assign a dollar value to a human life, and the whole exercise falls apart because nobody gave you clear parameters upfront. I've seen three hospital systems waste six months each building models that got thrown out in the final review simply because the underlying assumptions weren't documented, or were buried in appendices nobody read. The method itself is straightforward in theory: you identify every cost and every benefit associated with a healthcare intervention, assign monetary values to them, discount future cash flows to present value, and compare the net result against your decision threshold. The hard part is everything that happens between those words. You need to decide whether you're taking a payer perspective, a provider perspective, or a societal perspective, because each one will produce dramatically different numbers for the same program. A telehealth expansion might look like a clear win from a payer's angle—lower reimbursement costs, reduced travel—but from a clinic's view, it requires infrastructure investment that won't show returns for years. You also have to pick a time horizon. Three years? Ten? Twenty? In oncology drug evaluations, the difference between a five-year and ten-year horizon can flip a positive net benefit into a negative one, or vice versa, because the long-term survival gains just don't materialize on the shorter timeline. The standard approach uses a 3 to 5 percent annual discount rate for costs and benefits, which aligns with most government guidelines, but some health economists argue for lower rates when dealing with chronic conditions where benefits accrue far into the future.
Building the Actual Model
Start by listing every cost category. Direct medical costs include the intervention itself, follow-up visits, lab work, complications, and adverse events. Direct non-medical costs cover patient transportation, caregiver time, and lost wages. Indirect costs are the harder ones to pin down—productivity losses from morbidity and mortality, often calculated using the human capital approach or friction cost method. Benefits get trickier because they aren't always monetary. Quality-adjusted life years, or QALYs, are the standard metric, but converting a QALY into a dollar figure requires a willingness-to-pay threshold, which varies wildly between countries and even between insurance plans within the same country. Here's something most beginners miss: sensitivity analysis isn't optional. Running a single point estimate gives you a number, not a decision. You need to at minimum run one-way and multi-way sensitivity analyses across your key variables—drug price, adherence rates, complication probabilities, discount rates—and ideally a probabilistic sensitivity analysis using Monte Carlo simulation if your data supports it. This tells you how much uncertainty is really built into your conclusion. Without it, stakeholders will pick apart the one number you gave them and assume you ignored every possible variable.
A Real Cost Benefit Analysis Example Health Care
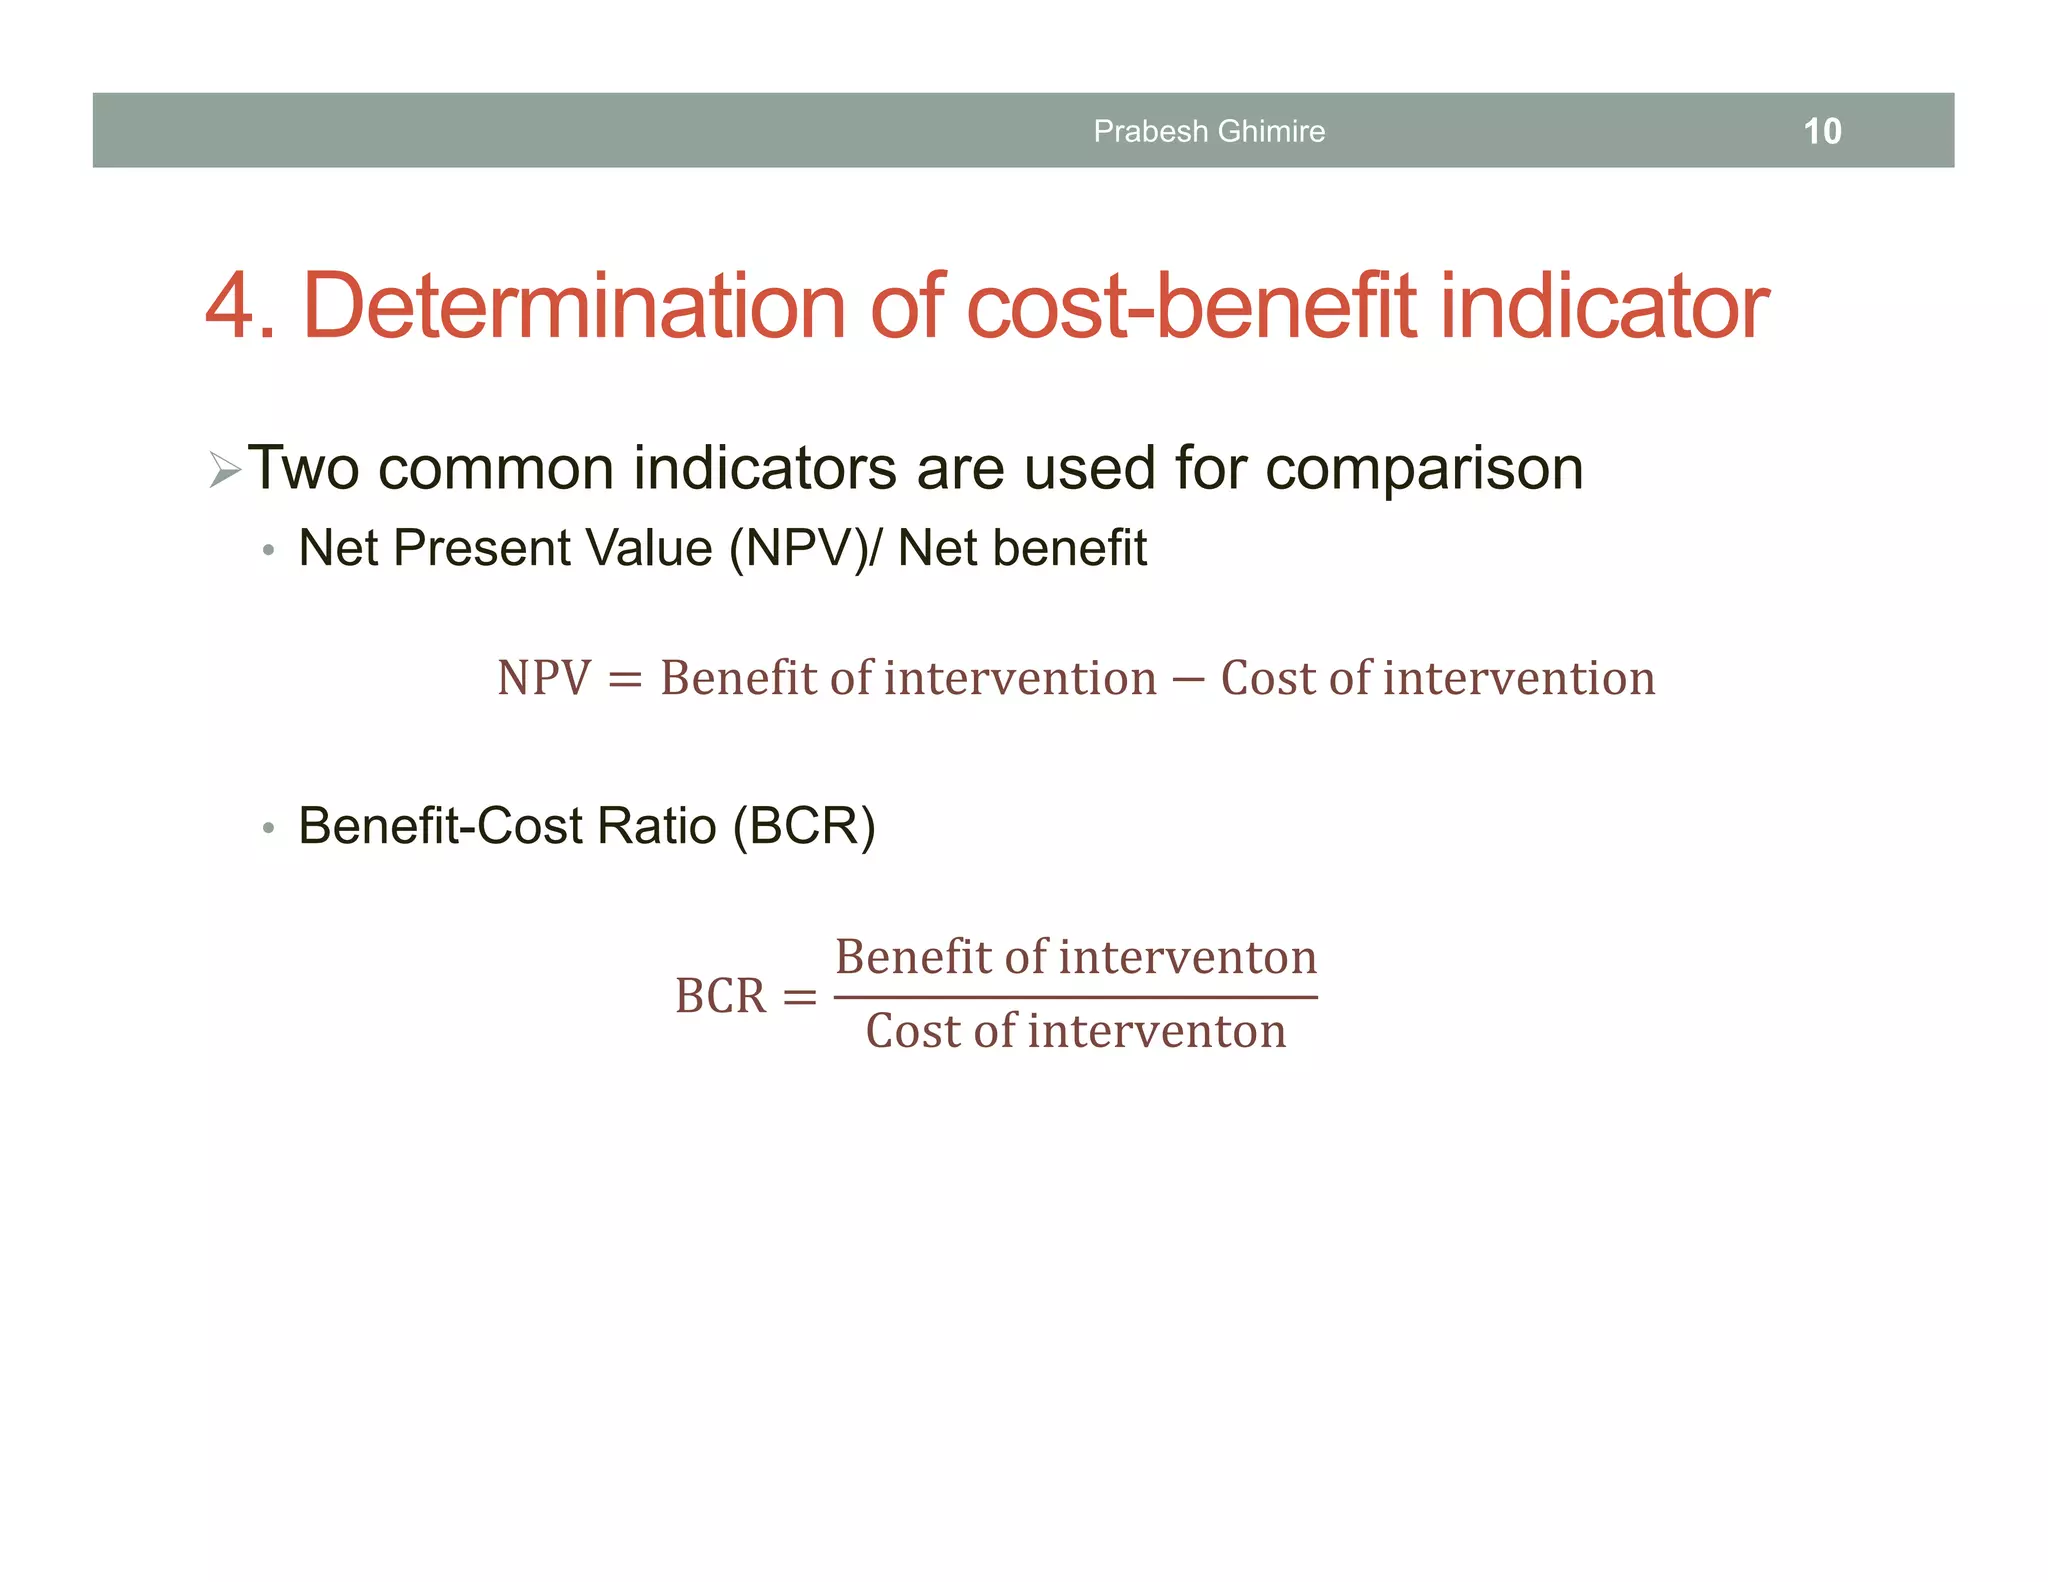
Last year I worked through a Cost Benefit Analysis Example Health Care involving a community-based diabetes prevention program targeting high-risk adults in a rural county. The intervention included biweekly nutrition counseling, subsidized physical activity sessions, and quarterly HbA1c monitoring over a three-year period. Total program cost came to approximately $420 per participant annually, totaling $1,260 per person over the study period. The benefits side was where things got complicated. We projected a 28 percent reduction in incident diabetes cases among participants based on published literature from the Diabetes Prevention Program trial. Each averted diabetes case was valued at roughly $17,400 in direct medical costs over ten years, using Medicare cost data as our baseline. When we discounted future benefits back to present value at 3.5 percent, the net benefit per participant came out to about $1,840 after accounting for the full three-year program cost. The benefit-cost ratio landed at 2.3 to 1. The edge case hit us during the third quarter when we realized our initial model hadn't accounted for transport barriers. Rural participants averaged 47 miles round-trip to the counseling sessions, and attendance dropped to 34 percent once we factored in the actual travel time and vehicle costs. We had to go back and rebuild the model with a two-track approach: one track for participants who received remote counseling via telehealth and another for those attending in person with transportation subsidies. The revised model showed a benefit-cost ratio of 1.9 to 1, still positive but meaningfully different from our original estimate. That adjustment alone changed whether the program cleared the funding board's threshold. I learned that you should never trust your first pass, especially in rural populations where logistics eat into effectiveness faster than you expect.
Get the Full Details
Common Pitfalls That Waste Your Time
Double-counting is the most frequent error. If you include reduced hospitalization costs as a benefit and also count avoided emergency department visits separately, you're likely counting the same event twice. Cross-reference every line item against your data source before you finalize the model. Another common mistake is ignoring opportunity costs—the resources spent on this program could have been deployed elsewhere, and that alternative use has value too. Budget constrained health systems especially need this calculation, though it's routinely omitted from published analyses. There's also the problem of extrapolating from clinical trial data to real-world settings. Trial populations are highly selected, adherence is monitored and enforced, and dropout rates are tracked meticulously. In the field, those same interventions typically show 40 to 60 percent of the efficacy reported in trials. If your model uses trial-level effectiveness without applying a real-world adjustment factor, your benefit projections will be inflated enough to mislead decision-makers. I apply a 50 percent scaling factor to efficacy data from RCTs as a default, which is conservative but defensible.
When This Method Breaks Down Completely
Cost Benefit Analysis works reasonably well for interventions with measurable outcomes and clear cost structures. It performs poorly for preventive programs with long latency periods, mental health interventions where quality-of-life gains are hard to monetize, and rare disease treatments where patient populations are too small for reliable cost estimation. In those cases, cost-effectiveness analysis using incremental cost-per-QALY ratios tends to be more transparent and less prone to manipulation through arbitrary valuation choices. You can stretch a benefit-cost ratio to support almost any conclusion if you're willing to adjust the willingness-to-pay threshold or the discount rate enough. A cost-effectiveness framework makes those assumptions more visible and harder to hide. Another scenario where CBA fails is when equity considerations matter more than aggregate efficiency. A program might show a positive net benefit overall while disproportionately excluding low-income or minority populations. The numbers look good and the recommendation is clear, but the distributional consequences are ignored entirely. If your organization cares about health disparities, pair your CBA with a distributive impact analysis rather than relying on the headline number alone.