Why Most Counselor Training Programs Get It Wrong
The first thing you will notice in almost any introductory course is that theories are taught as competing philosophies. CBT vs. psychodynamic vs. humanistic. Pick your side, learn the pillars, write the exam. That is not how practice works. In real sessions, you are pulling from whatever tool happens to address the immediate problem, and sometimes that means using micro-techniques from three different frameworks in a single hour. I spent several years running training groups for early-career clinicians. The people who struggled were rarely the ones who could not recite theory. They were the ones who treated theory as a costume they put on for each client. You show up as a pure CBT practitioner, force every intervention through cognitive restructuring, and the client who needs validation and relational safety just leaves. I saw it happen repeatedly.
Counseling Theories Essential Concepts And Applications
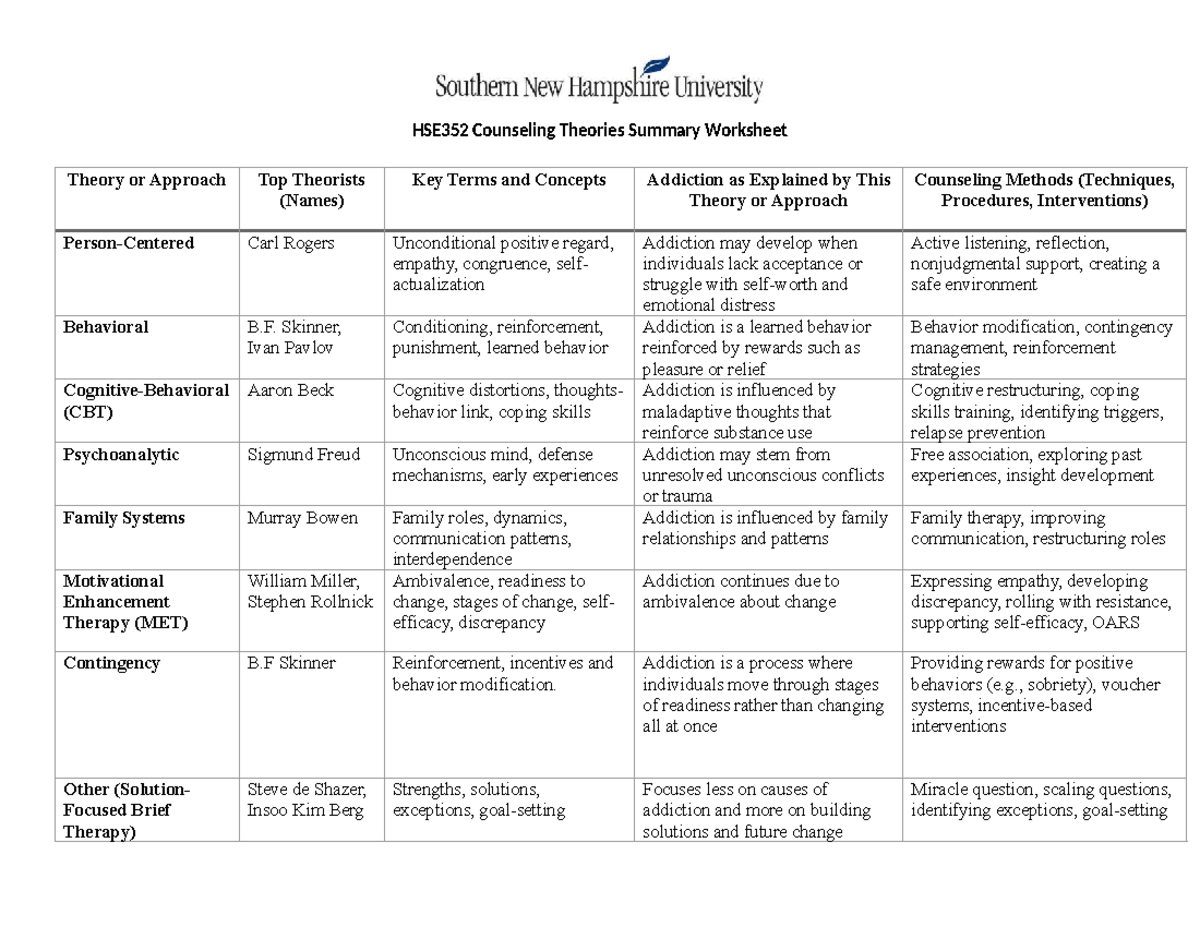
Here is the practical breakdown of what actually matters when you are sitting across from someone and trying to make sense of their presenting problem. Psychodynamic theory is not just about childhood and unconscious conflict. The essential concept you need is transference and countertransference as real-time data. When a client responds to you in a way that seems disproportionate to what you just said, that is useful information. It often reveals a relational pattern they reproduce outside the room. I had a client in my early clinical years who became subtly hostile every time I suggested a small behavioral change. It took me three sessions to realize I was triggering a pattern where authority figures in her life dismissed her autonomy. Once I named that dynamic explicitly, the resistance dropped and we made actual progress. The theory alone would not have caught that. Noticing it required combining psychodynamic awareness with active process commentary. Cognitive Behavioral Theory is frequently misunderstood as a structured worksheet exercise. The core mechanism is the cognitive model: events do not cause emotions, interpretations of events do. That sounds academic until you watch someone spiral through anxiety because they interpreted a neutral email as confirmation they are about to be fired. CBT gives you the scaffold to help them test that interpretation. But here is the part most textbooks skip: CBT fails when the client's thoughts are not distorted but genuinely situationally appropriate. A client in an abusive relationship having catastrophic predictions about their partner's reaction is not having a cognitive distortion. Running behavioral experiments on that is dangerous and counterproductive. In those cases, grounding the work in trauma-informed or systemic frameworks matters more than restructuring.
Humanistic and person-centered approaches are routinely dismissed by programs as too vague to teach. That is an inaccurate assessment. The essential concept is unconditional positive regard paired with empathic reflection. In practice, this means resisting the urge to fix, interpret, or redirect. You let the client lead and trust that the therapeutic relationship itself is the intervention. The counter-intuitive part: this approach is not easier than directive methods. It requires genuine self-awareness from the therapist because every impulse to give advice or reframe has to be consciously set aside. I learned this the hard way with a client who kept circling back to the same career decision. My instinct was to give them a decision-making framework. Instead, I stayed with the ambiguity and reflected the underlying fear of making the wrong choice. Four sessions later, they had already resolved it on their own. Staying present was harder than solving it for them, but it was also more effective. Systemic and family therapies shift the unit of analysis from the individual to the relational network. The essential concept is circular causality. Problems are not caused by one person or one event. They are maintained by interaction patterns. A teenager acting out is often expressing family tension that cannot be spoken directly. The symptom serves a function. Recognizing this changes everything about how you approach treatment. You stop asking what is broken inside the individual and start mapping the relational loops. I worked with a family where the father's anger and the daughter's withdrawal were locking into a pattern that reinforced both. We did not treat the daughter in isolation. We intervened with the interaction pattern itself. The daughter's symptoms improved within six sessions once the family dynamic shifted. Solution-Focused Brief Therapy operates on the assumption that solving the problem does not require understanding its origin. The essential techniques are the miracle question, scaling questions, and exception-finding. If you ask a client what would be different if the problem disappeared, you get a concrete vision. If you ask them to rate their current state on a scale of one to ten, you get measurable progress tracking. If you ask when the problem was less severe, you get evidence they already have resources. This is not lightweight work. The discipline required to stay future-focused and resource-oriented without falling back into problem-talk is real. I initially underestimated SFBT because it felt too simple. Then I worked with a client who had exhausted every insight-oriented approach and was stuck in chronic problem narration. Eight sessions of SFBT broke a two-year impasse. The simplicity was the intervention.
Get the Full Details

Existential therapy deals with the conditions of human existence: freedom, responsibility, isolation, and mortality. The essential concept is that anxiety is not always pathological. It can be a signal that a client is confronting a meaningful choice they have been avoiding. When someone is grappling with purpose, authenticity, or the finiteness of life, standard symptom-reduction models fall short. The work is helping them tolerate uncertainty and make authentic commitments despite it. This is not a technique you apply. It is a stance you hold. You sit with the enormity of the question rather than rushing to fill it with coping strategies. The most common pitfall in applying these theories is treating them as mutually exclusive categories rather than lenses. A skilled practitioner moves between them fluidly. You might use a CBT technique to help a client challenge a specific automatic thought, then switch to a person-centered stance when they surface deeper relational material, then bring in a systemic perspective when family dynamics maintain the problem. Theories are maps, not territories. The territory is the person sitting in front of you. Another pitfall is over-intellectualizing. Learning theory is valuable. Applying it requires dropping the manual and listening. I have watched trained clinicians miss obvious material because they were too busy identifying which theoretical framework fit the client's presentation. The client's words matter more than the taxonomy. Theory should serve the clinical moment, not replace attention to it.
Practical application also depends on population and setting. In a brief workplace EAP model, you are not going to run long-term psychodynamic work. You need focused, solution-oriented interventions. In private practice with clients seeking depth work, a purely directive approach will feel thin. Matching theory to context is part of the skill set. It is not about having a favorite model. It is about having enough flexibility to use the right model for the right person at the right time. If you want to build competence, the most efficient path is this: pick two or three theories and study them deeply enough to apply them poorly before you try to apply them well. Deep study of one or two models teaches you more than surface familiarity with ten. Then supervise your application. Theory knowledge without supervised practice is theoretical knowledge. It does not translate into clinical skill until you have had feedback on your failures. I learned more from three hours of supervision pointing out my misapplications than I did from three semesters of coursework. There is no single correct theoretical orientation. The field has moved past the debate about which model is best. The evidence supports factors that are common across models: the therapeutic alliance, empathy, goal consensus, and cultural adaptation. Theoretical orientation matters for technique selection and case conceptualization, but it does not determine outcomes by itself. A competent therapist is someone who understands multiple frameworks well enough to use them purposefully and knows when none of them fit what is happening in the room.