
What the Cover Uncover Test Actually Measures
It tells you whether someone has a latent or manifest misalignment of the eyes. That is it. The test is called a Cover Uncover Eye Test because you literally cover one eye, watch what the other eye does, then uncover it and observe again. The movement (or lack of movement) reveals whether the uncovered eye was doing the fixing work the whole time. I ran this test hundreds of times during residency. The technique is straightforward but the interpretation trips people up. Let me walk through it without the textbook padding.
How to Perform the Cover Uncover Eye Test Step by Step
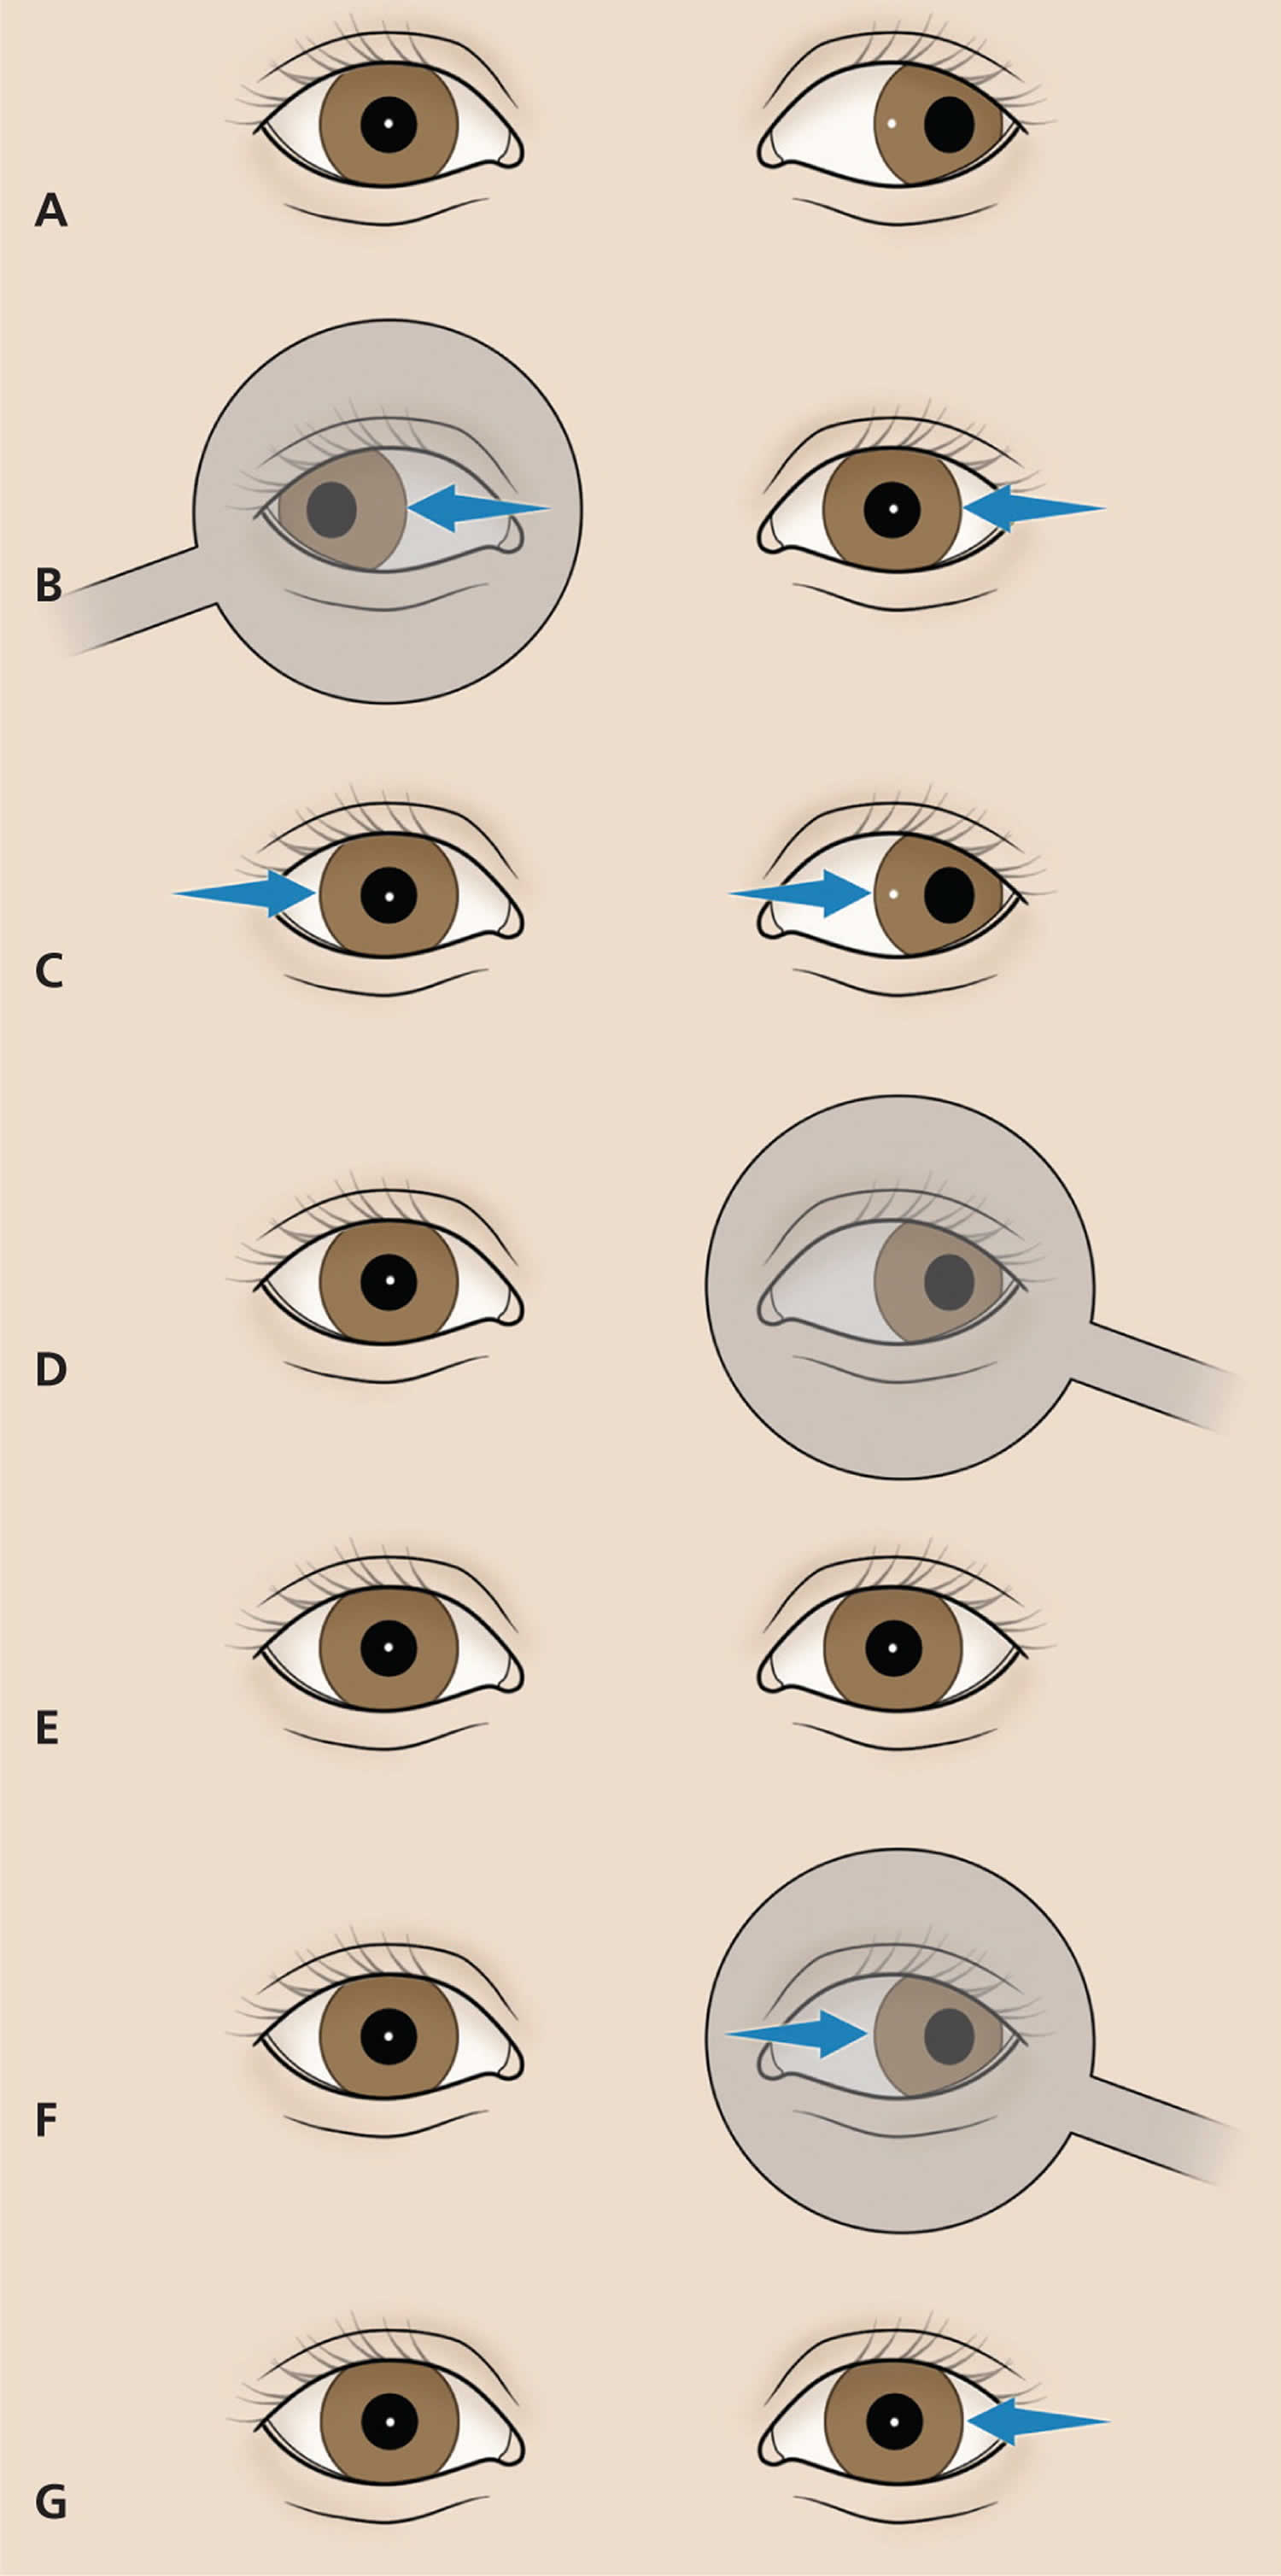
Get the patient sitting comfortably about 33 centimeters from a near target, or six meters away for distance testing. Have them wear their refractive correction if they have it — uncorrected vision changes the baseline and you will misread the deviation. Make sure the room lights are adequate but not glaring into their eyes. Stand where the patient can see your face or a target. Ask them to fixate on something small — a coin, a printed letter, a toy held by the examiner. Then take an occluder (a plastic paddle, a card, even your palm works in a pinch) and cover one eye completely. Do not press on the eyelid. Pressing distorts the cornea and can artificially induce astigmatism for a moment, which skews the observation. Watch the uncovered eye carefully for three to five seconds. Then quickly uncover that eye and immediately cover the other one. Again, watch the previously covered eye for three to five seconds. Repeat a few times switching eyes. If nothing moves, the eyes are aligned. If something moves, you have a phoria or a tropia depending on which phase the movement happened in.
Reading the Results Correctly
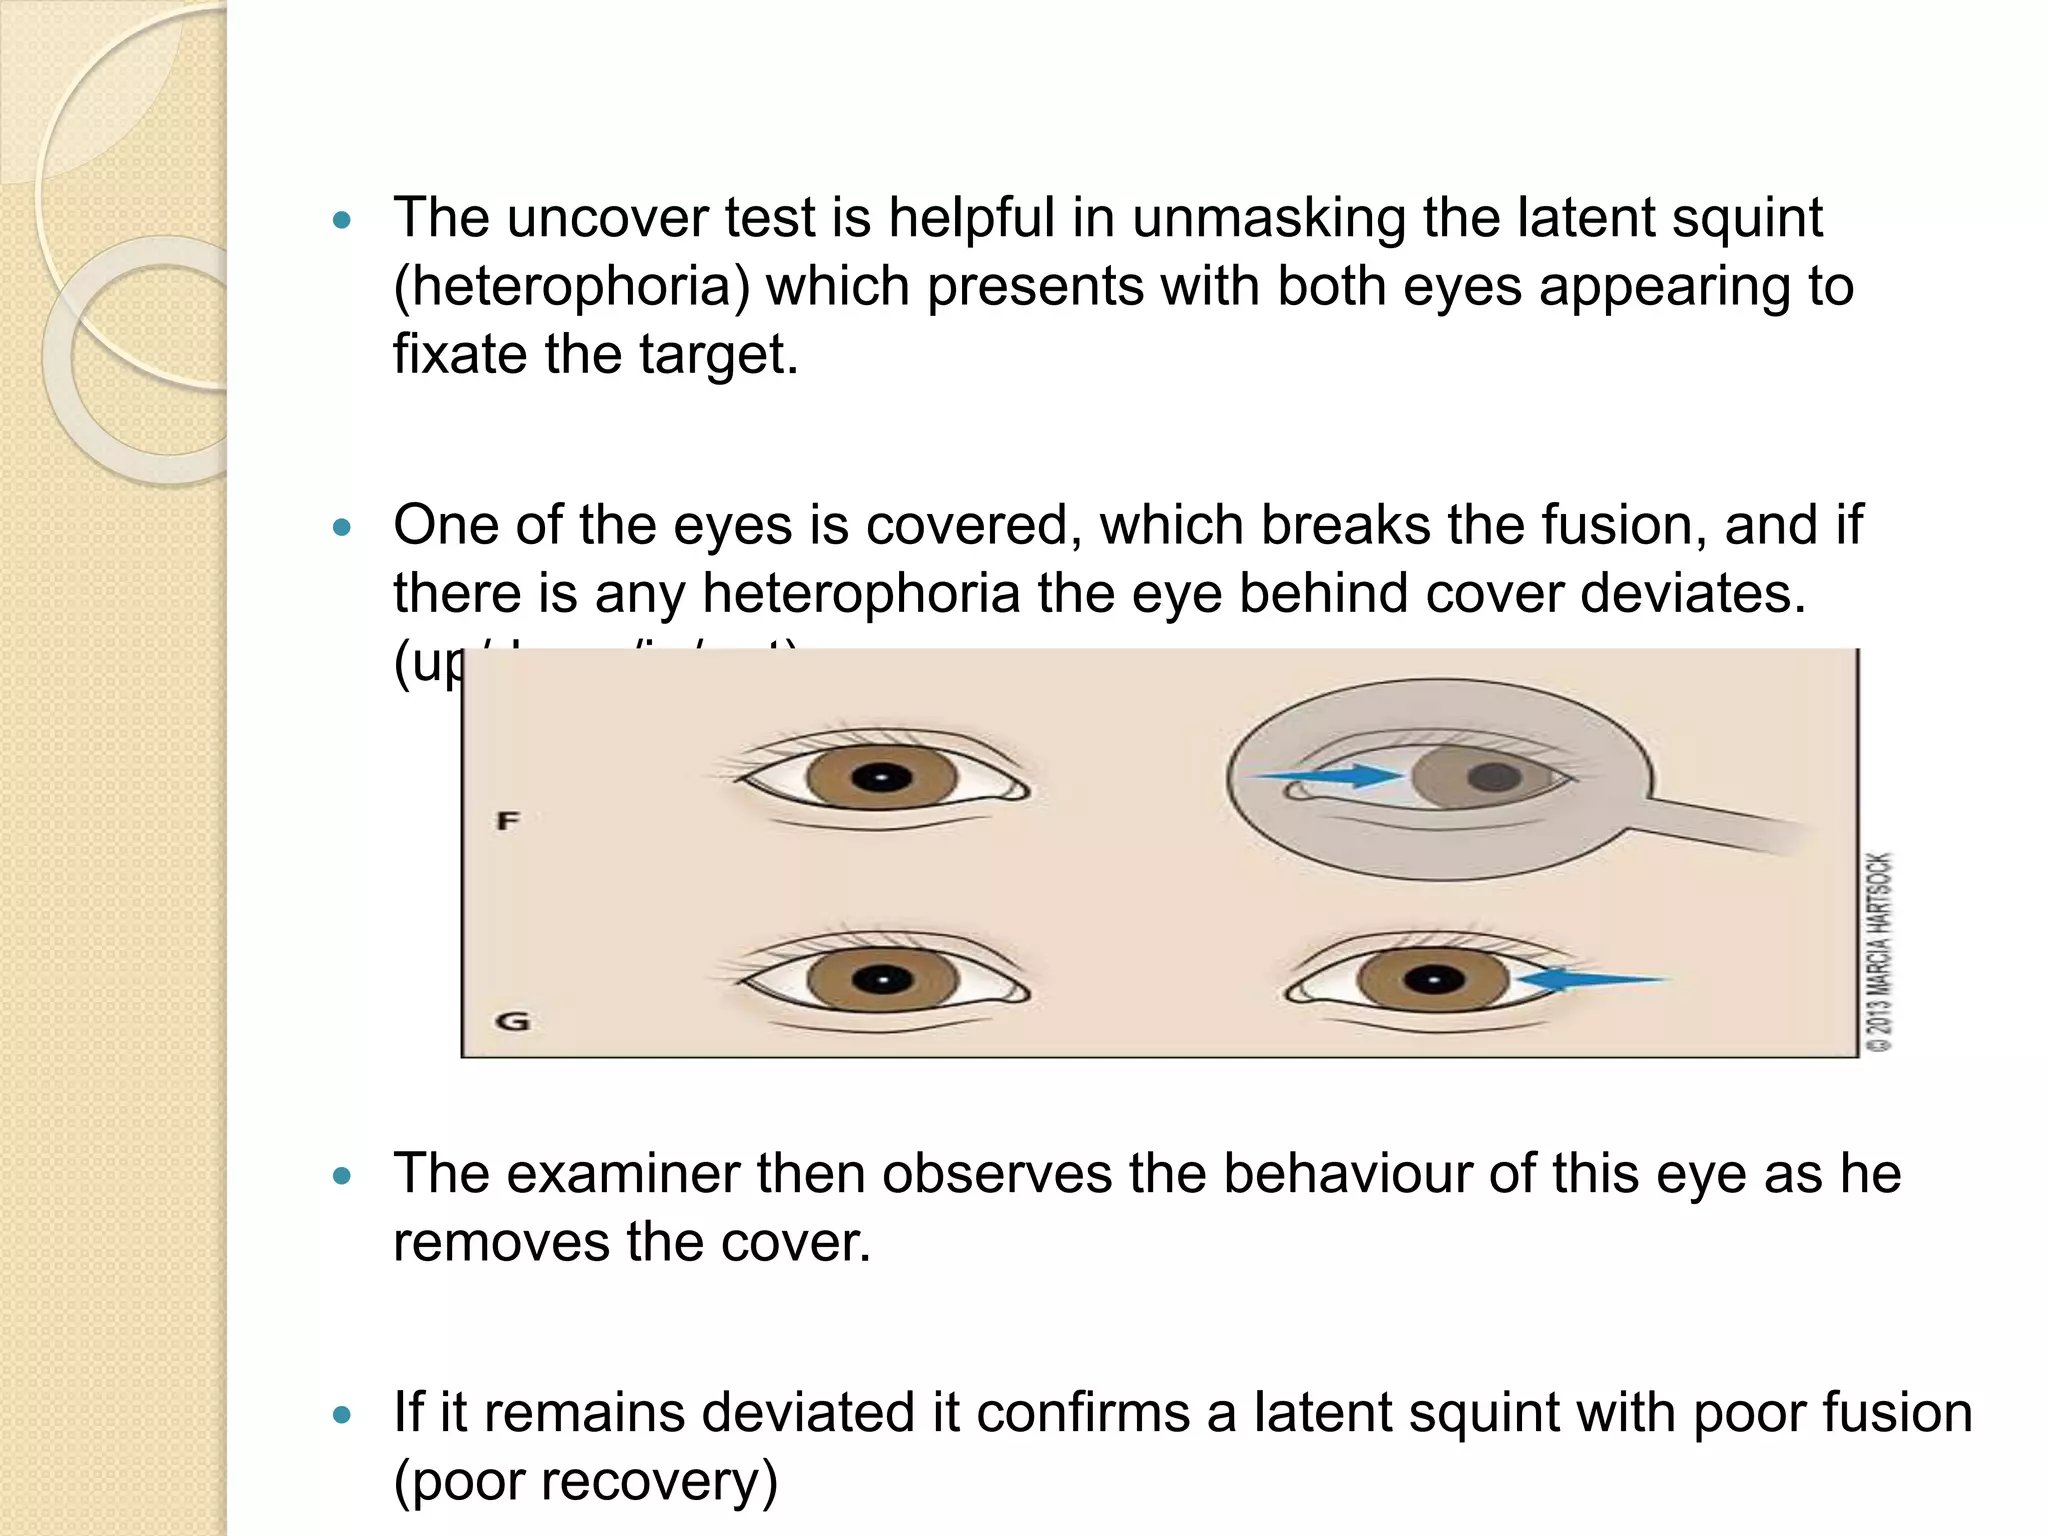
Here is where most people — including some junior residents I worked with — got confused. Pay attention to which phase the movement occurs in: Phase one: Cover test on the fixing eye. The patient is using eye A to look at the target. You cover eye A. If eye B (the one now uncovered) moves to take up fixation, then the patient has a phoria — a latent deviation that only shows when binocular fusion is broken. Eye B was not actually fixed on the target before; it was drifting, held in check by fusion. The moment you cover eye A, fusion releases and eye B saccades to the target. This is the definition of a heterophoria. Phase two: Uncover test. Eye A was covering the deviated eye. You uncover it. If eye A moves from its deviated position back to the target, that confirms the phoria diagnosis. The eye was deviated while covered and corrected itself once binocular vision returned.
Get the Full Details
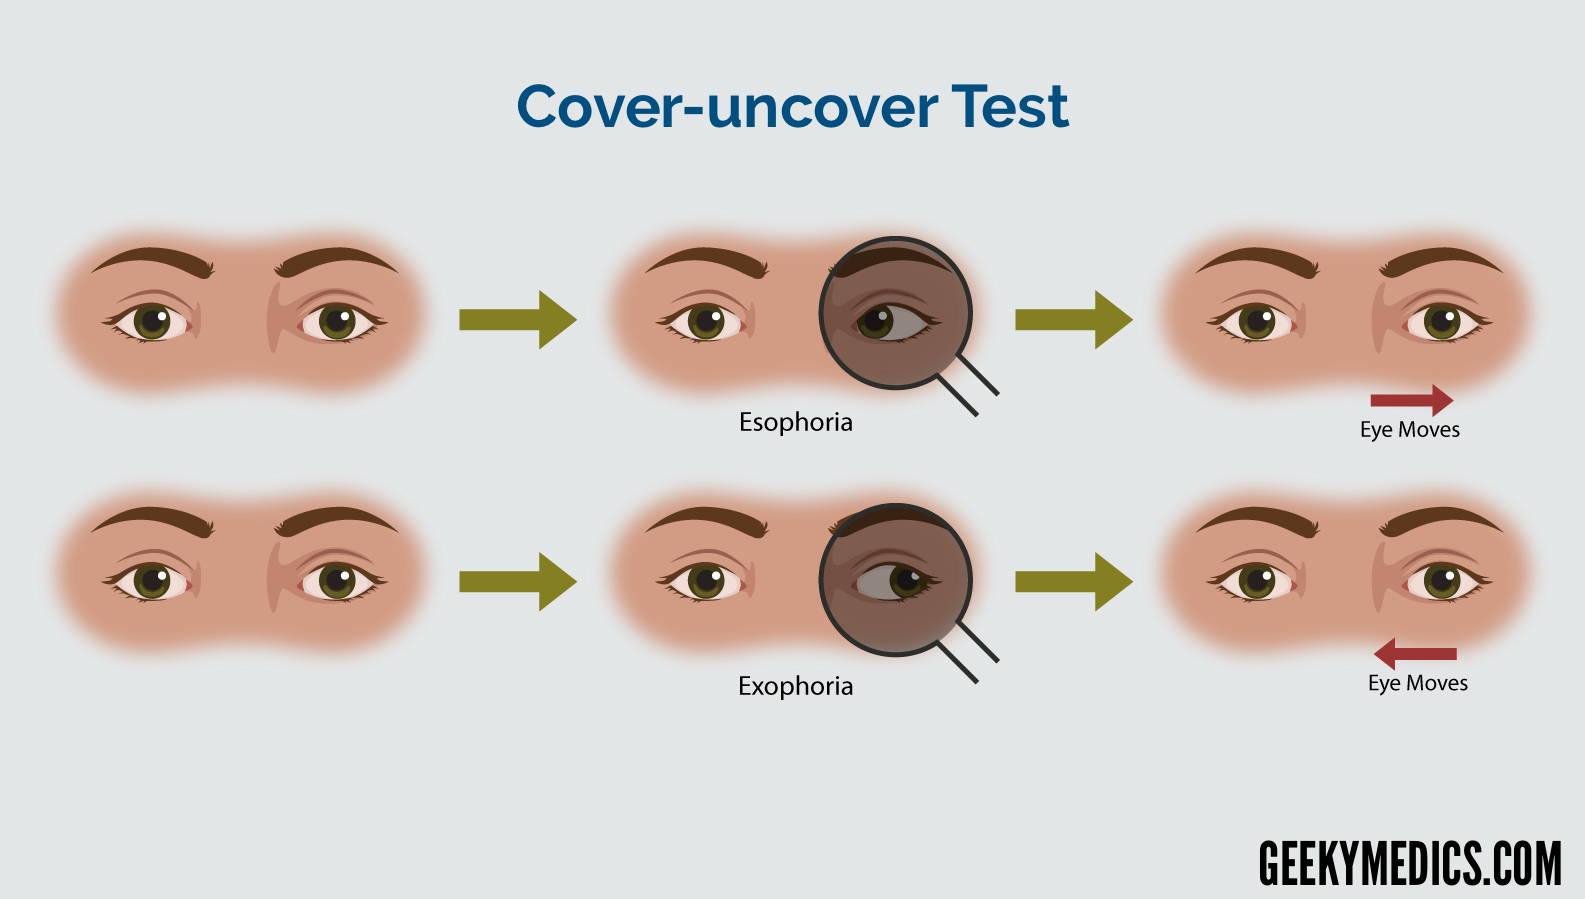
If the uncovered eye does not move when you cover the fixing eye, fusion was already holding it steady. No phoria at that distance and in that gaze position. If the eye does move, note the direction. Outward movement means exophoria. Inward means esophoria. Upward means hyperphoria. Downward means hypophoria. Now the critical distinction: if the eye is already deviated before you even cover anything — meaning the patient is not using both eyes together at all — that is a tropia, not a phoria. The Cover Uncover Eye Test can detect this too. If you cover the fixing eye and the deviated eye stays deviated (does not move to take up fixation), the patient has a manifest misalignment. They are not fusing. This is a tropia.
A Problem I Encountered That the Textbooks Do Not Mention
Suprapapillary nystagmus. I had a patient — mid-twenties, referred for evaluation of intermittent double vision — whose eyes appeared perfectly aligned on the Cover Uncover test. No movement. No deviation. I cleared them. Three weeks later they came back because the double vision was getting worse. The issue was that the patient had a subtle upbeat nystagmus that only manifested when one eye was occluded. When both eyes were open, fusion suppressed it. When I covered one eye, the uncovered eye would drift upward in a very slow, almost imperceptible beat. The nystagmus was so fine I missed it on the first pass. I went back and did the test again with a red glass over one eye. The red image jumped — there it was. Suppressed upbeat nystagmus revealed only under monocular conditions. The workaround was simple but it required me to slow down the test. Instead of the standard three-second observation window, I held the cover for eight to ten seconds and watched for a slow upward drift that would then correct with a fast beats — classic upbeat nystagmus pattern. I also added a prism break test afterward, which confirmed the fusion reserve was abnormal. The patient ended up having a subtle brainstem lesion that was missed on the initial imaging because the standard exam had been read as normal. Repeat imaging with contrast found it.
Lesson: the Cover Uncover Eye Test is sensitive to your observation window. Three seconds is standard. Eight seconds catches things three seconds misses.

Common Pitfalls That Lead to Wrong Readings
Pitfall one: testing with the wrong target distance. Esophorias are far more common at near. If you only test at distance, you will miss a near esophoria. Conversely, exophorias are more common at near. Test both distances. A full orthoptic exam includes the Cover Uncover test at 6m and at 33cm, in primary gaze and in all nine positions of gaze. Pitfall two: not checking for suppression. If a patient has a large tropia, the deviated eye may be suppressed. The Cover Uncover test will show no movement of the deviated eye when you uncover it because the patient is not using it. You might incorrectly call this "no deviation present." But the real issue is suppression — the brain is actively ignoring that eye. A Worth four-dot test or the alternate cover test with a red lens will reveal this much more clearly. Pitfall three: confusing the alternate cover test with the Cover Uncover test. They are related but not identical. The Cover Uncover test uses one eye at a time without alternating rapidly. The alternate cover test — where you switch the occluder back and forth quickly — breaks fusion more aggressively and reveals larger deviations. If you only do the Cover Uncover test, you may miss a significant phoria because the fusion mechanism has time to re-establish between covers. Use the alternate cover test as a screening follow-up whenever the Cover Uncover test is ambiguous or normal but clinical suspicion remains high.
Pitfall four: not noting the direction and magnitude. Writing "esophoria present" on a chart is not enough. You need to specify the distance (near or far), the gaze position (primary, left, right, up, down), and the prism diopter magnitude if you are using prisms to measure it. A 15-prism-diopter esophoria at near is clinically significant. A 3-prism-diopter esophoria in primary gaze is basically normal — everyone has a small amount of physiological phoria.
Advanced Nuance: Convergence Insufficiency and the Cover Test
Convergence insufficiency is the most common binocular vision disorder in adults. The Cover Uncover Eye Test alone will not diagnose it. But it is part of the workup. After you establish the phoria status at near, you measure the near point of convergence (NPC) using a convergence ramp or an ophthalmoscope handle brought toward the nose. You also measure the accommodative convergence to accommodation ratio (AC/A) if you have the equipment. A patient with convergence insufficiency will typically show an exophoria at near that increases in magnitude as you hold the cover longer. The fusional vergence reserves — measured with prismatic break points — will be reduced. The treatment is not always glasses. Vision therapy has solid evidence for convergence insufficiency. Patching one eye is sometimes used diagnostically but it is not a treatment for this condition.
When the Test Is Not Useful
The Cover Uncover test requires the patient to be able to fixate. If the patient has significant visual impairment — say, less than 20/200 in one or both eyes — you cannot reliably perform it. The eye may be deviated simply because it cannot see the target well enough to align. In that case, you do a penlight corneal reflex test (Hirschberg test) instead. It is less precise but it works regardless of visual acuity. Similarly, if the patient has nystagmus, the test becomes unreliable. The constant movement makes it difficult to distinguish a true phoria from the baseline nystagmic beat. I have seen this with congenital nystagmus — the Cover Uncover test gave confusing results because the eyes were always moving. In those cases, I relied on the Hirschberg test and orbital imaging rather than trying to force a phoria measurement. Infants and non-verbal toddlers are another population where the test is challenging. You can do a modified version by observing the eyes while the child looks at a toy, then placing an occluder over one eye and watching for movement in the other. But the results are far less reliable. For young children, the corneal light reflex and the ability to fixate and follow are more useful screening tools.
A Note on the Alternate Cover Test as a Companion
I mentioned the alternate cover test earlier but I want to emphasize it. The alternate cover test is the workhorse. You cover one eye, then the other, then the other, in rapid succession. This thoroughly breaks fusion. Any deviation that shows up here is a tropia or a phoria that fusion was masking. The Cover Uncover test is more conservative — it tests whether fusion is maintaining alignment under normal binocular conditions. Together they give you a complete picture. In practice, I run the Cover Uncover first to assess the baseline, then the alternate cover to unmask any latent deviation, then the fixation swap test (covering each eye in turn and watching for a saccade to fix) to differentiate tropia from phoria. That sequence takes about two minutes and covers the essential diagnostic ground.
Measuring the Deviation With Prisms
Once you have identified a phoria or tropia, you quantify it. Place a prism in front of the deviated eye with the base direction opposite to the deviation — base in for exophoria, base out for esophoria, base up for hypertropia, base down for hypotropia. Increase the prism power until the eye no longer moves when you cover the fellow eye. That is the prism neutralization point. Record the value in prism diopters. A 6-prism-diopter esophoria at near is within the normal range for many people. A 12-prism-diopter esophoria is worth investigating. Above 15 prism diopters at near, most orthoptists will recommend some form of intervention — prism glasses, vision therapy, or in persistent cases with a cranial nerve palsy, surgical consultation. The threshold for intervention depends on symptoms, not just the number. A patient with a 10-prism-diopter esophoria who complains of headaches and double vision at near deserves more attention than an asymptomatic patient with a 15-prism-diopter esophoria.
Bottom Line
The Cover Uncover Eye Test is one of the oldest and most fundamental tests in ophthalmology and optometry. It is deceptively simple. The technique requires patience, a long enough observation window, and an understanding of what normal fusion looks like so you can spot when it fails. The most valuable thing you can bring to this test is not the steps themselves — you can read those anywhere — but the habit of slowing down when the result seems too clean. A normal Cover Uncover test in a symptomatic patient is a signal to look harder, not a signal to stop.
