Getting Your Clinic's Documentation Right Without Losing Your Mind
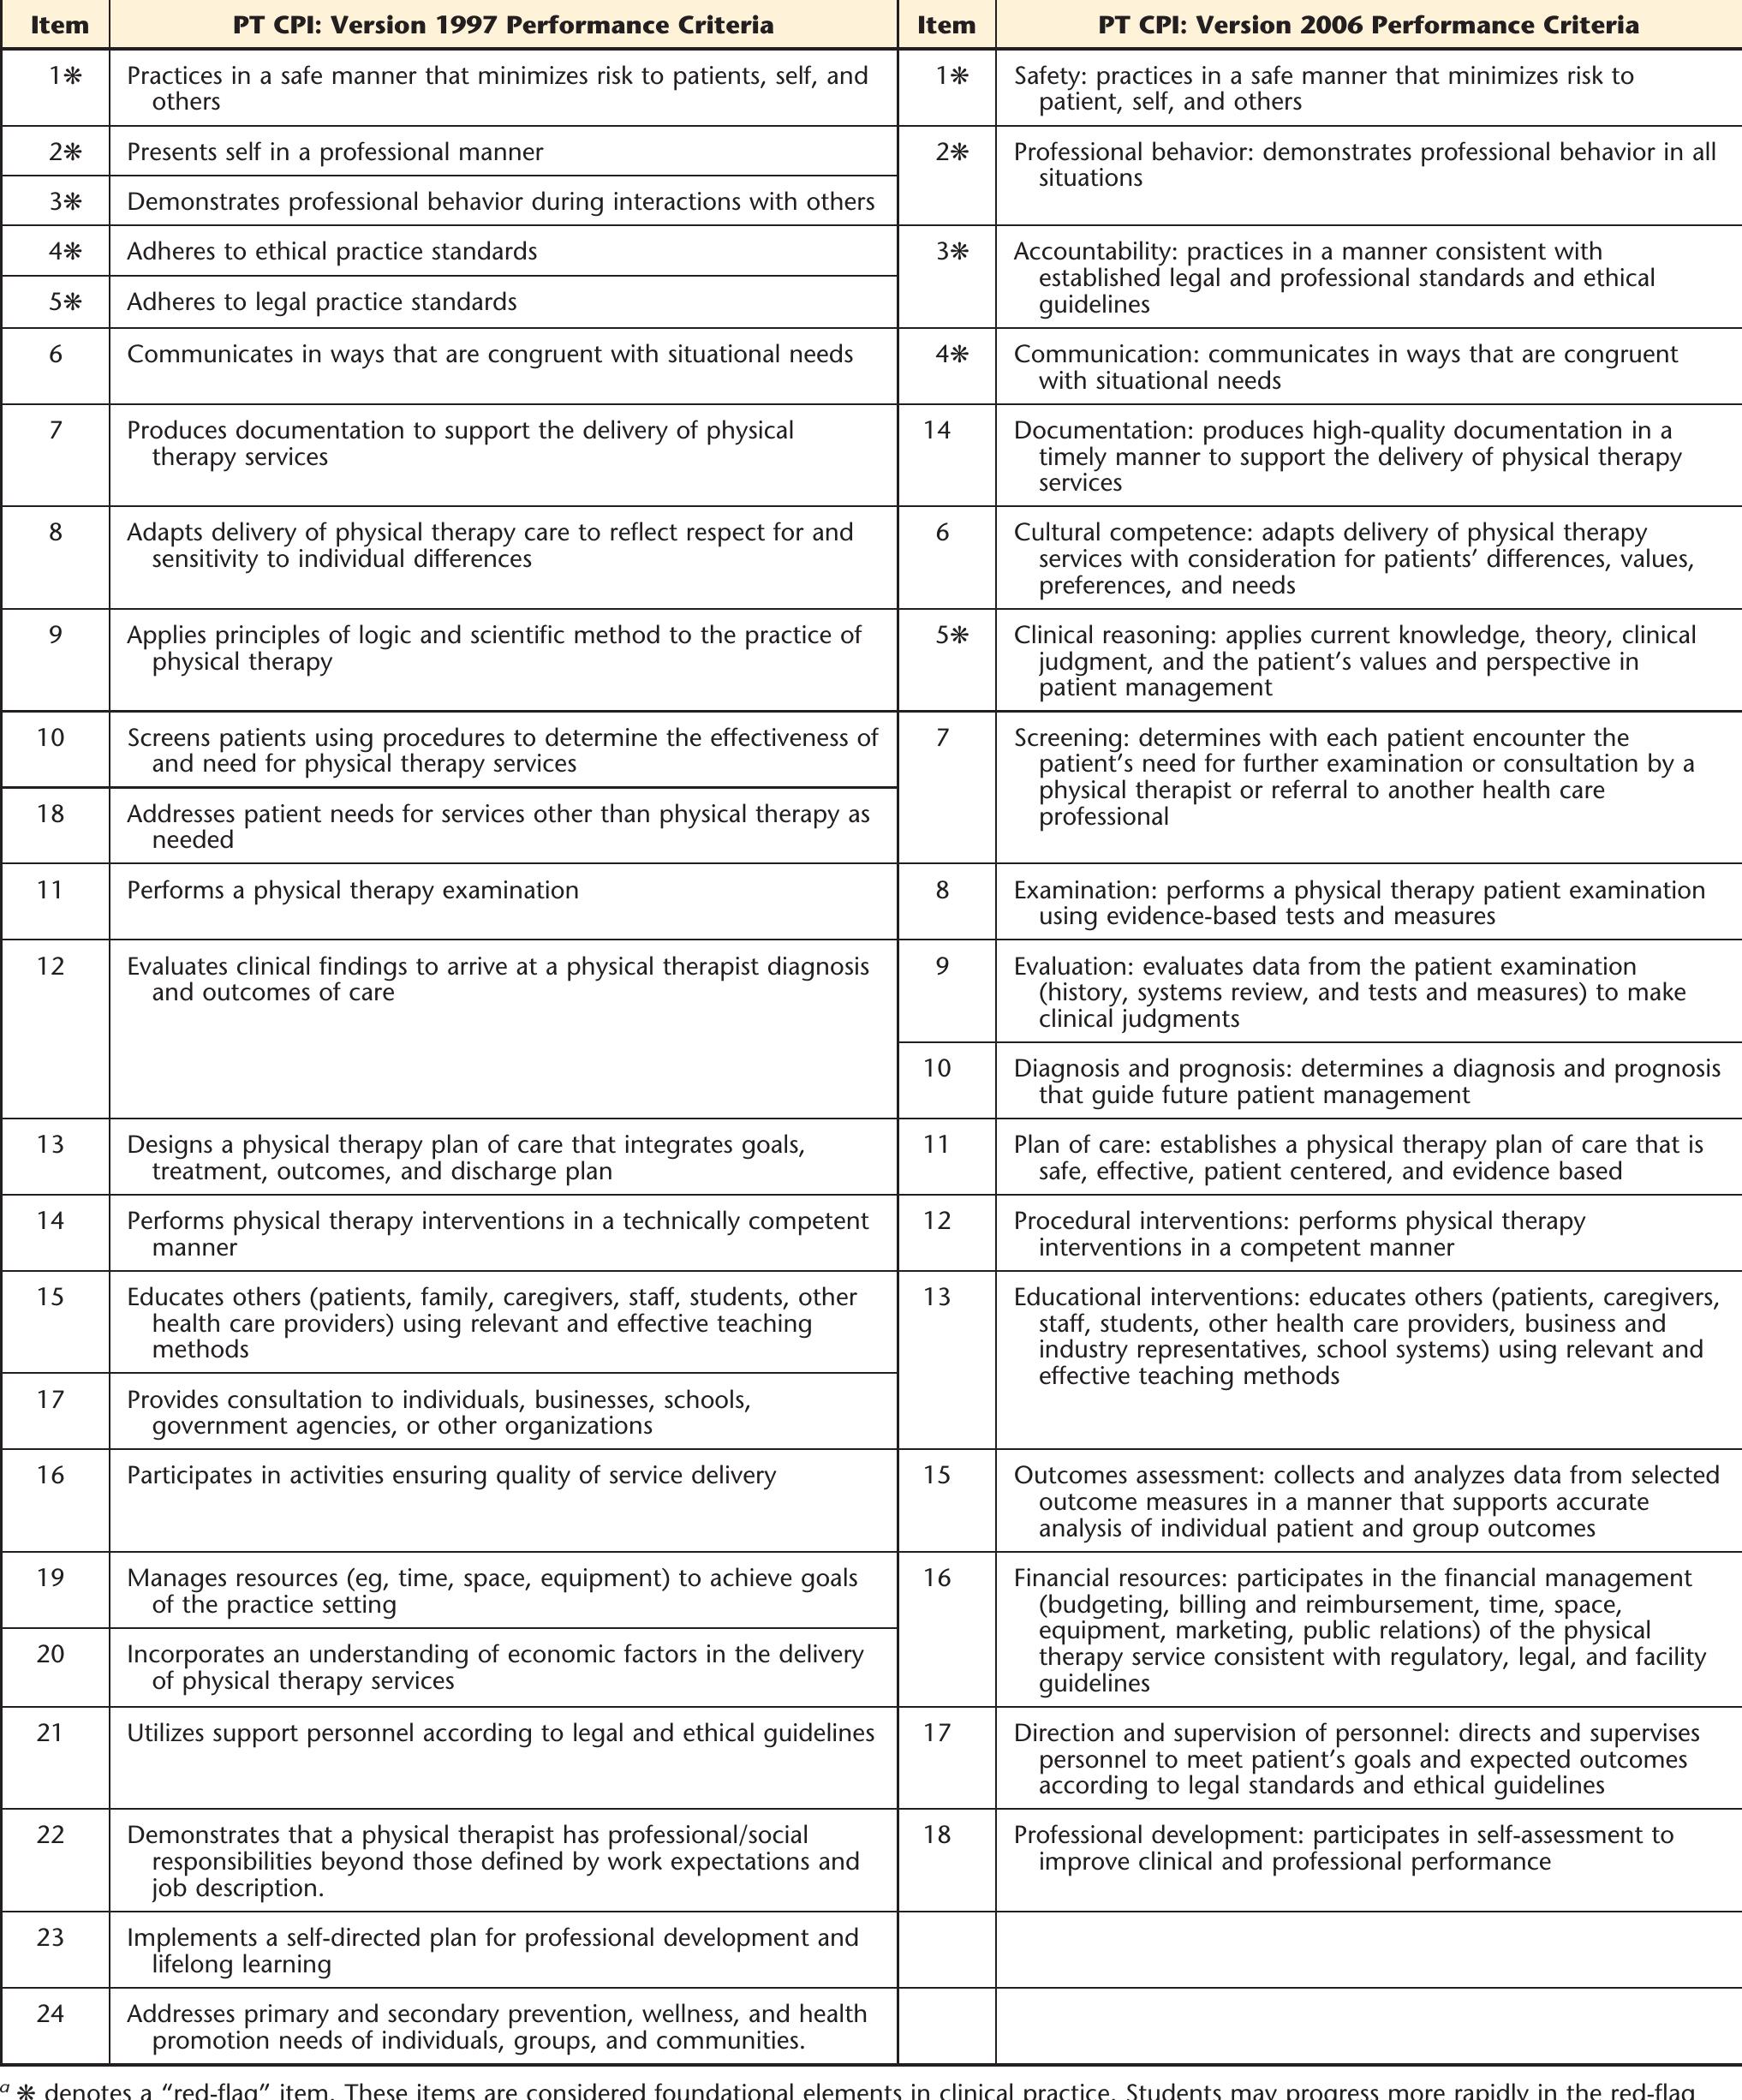
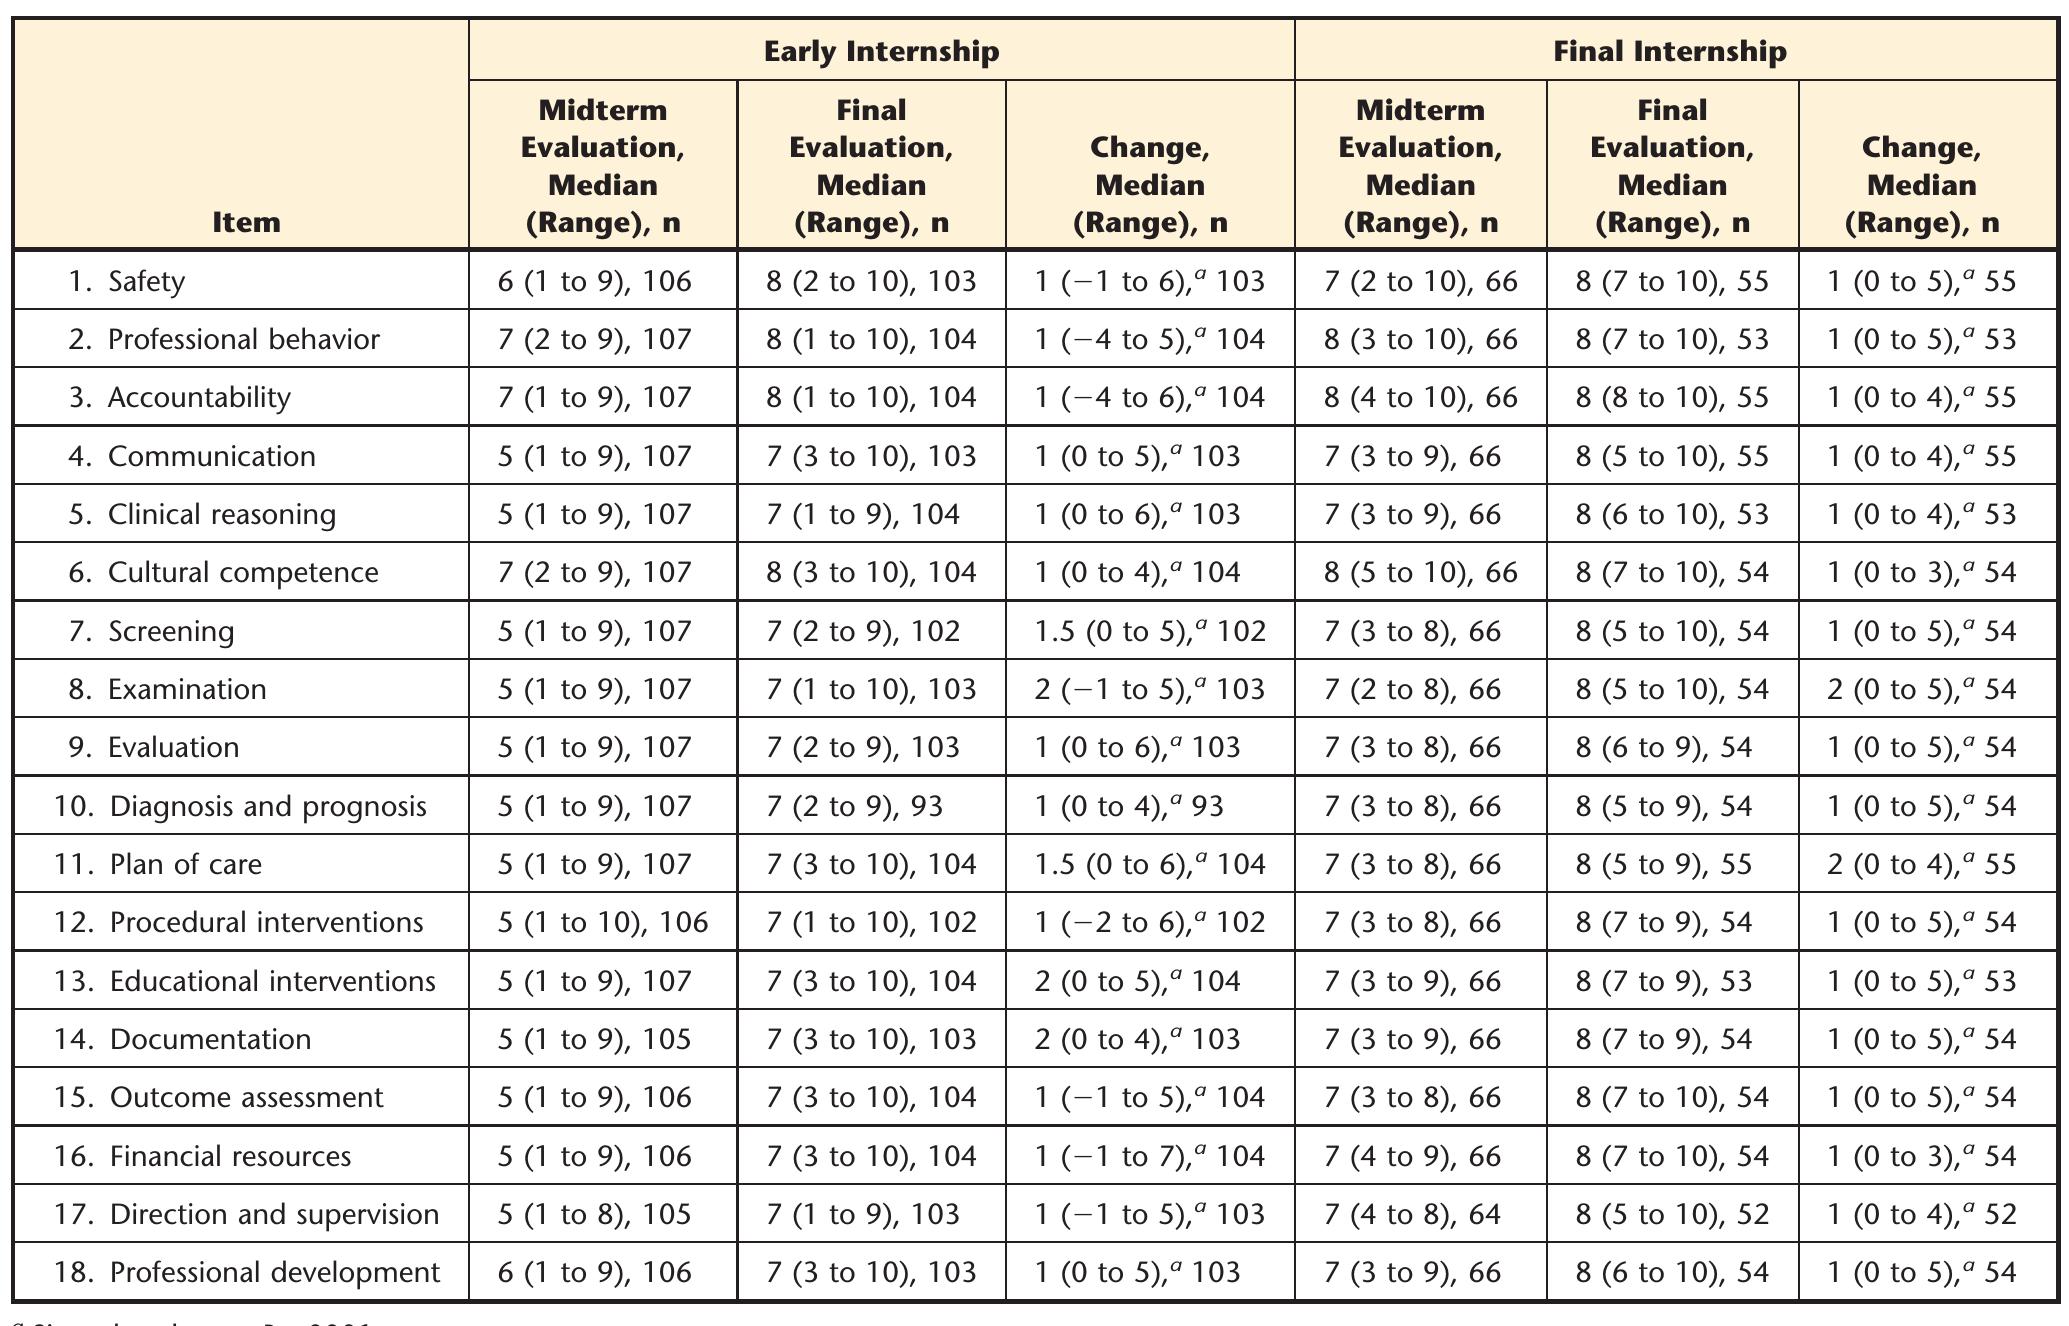
Most physical therapy clinic owners eventually run into the same problem: they hired someone to help with coding and documentation, that person left, and now the new staff has no idea how the practice actually tracks patient compliance and progress. I've been there three times. The term that keeps coming up in our office is Cpi For Physical Therapy, and honestly, it's one of those phrases you hear people use without always knowing exactly what they're talking about. Let me break down what it actually means in practice, because the gap between the textbook definition and the real-world workflow is where most clinics lose money. In my experience, CPI stands for Clinical Performance Index, and it's essentially a structured way of measuring whether a patient is meeting the functional benchmarks set out in their plan of care at each stage of treatment. It's not a government form. It's not a CPT code. It's a tracking methodology that some practices build internally and others license through EHR vendors. The confusion starts because there's no single standardized version, so two clinics can be using completely different CPI frameworks and calling it the same thing. The core idea is straightforward. You take your plan of care goals, assign each one a measurable threshold, and then at regular intervals—usually every five to ten visits—you score the patient's progress against that threshold. A score of 1 means they haven't met it. A score of 3 means they've exceeded it. The average across all goals gives you a composite number that tells you whether the patient is on track, falling behind, or ahead of schedule. That composite is your CPI for that visit block.
Setting Up Cpi For Physical Therapy in Your Practice
I spent about three weeks last year rebuilding our CPI system from scratch after a vendor abandoned their product mid-contract. What I learned should save you most of that pain. Step one: define your goal categories. You need at least three: pain reduction, functional range of motion, and strength or endurance. Don't add more than that in your initial setup. I watched a clinic try to track fourteen different metrics per patient and end up with nobody actually filling them out. The system died in six weeks because the documentation burden was too high for the clinical team. Step two: assign numeric thresholds to each goal. This is where most people get sloppy. Don't use vague language like "improved flexibility." Use numbers. Hamstring tightness measured by passive straight leg raise angle in degrees. Grip strength measured in kilograms. Step-down symmetry measured as a percentage. If you can't put a number on it, it doesn't belong in the CPI system. This rule alone cut our incomplete documentation rates from about forty percent down to under twelve percent.
Step three: determine your scoring cadence. I recommend scoring at visits five, ten, and fifteen, then at discharge. Scoring at every visit sounds thorough but it creates fatigue and inconsistency. Different therapists will score the same patient differently on consecutive visits because they're rushing, or because they're having a good day versus a bad day. Fixed checkpoints force consistency. Step four: integrate it into your existing EHR workflow. This is the step that determines whether your CPI system lives or dies. If it requires opening a separate tab, logging into another portal, or copying data by hand, nobody will use it. I built ours as a single tab inside our notes screen. Therapists open a patient's chart, click CPI, enter the three scores, hit save, and the composite auto-calculates. Four clicks. Takes about thirty seconds. That's the maximum friction you should ever build into this process.
Get the Full Details

The Hidden Problem Nobody Warns You About
Here's something that took me eighteen months to figure out. Most people treat CPI as a clinical tracking tool. It's equally important as a payer communication tool. When a Medicare audit comes through—and they do come through more often than you'd expect—the auditor wants to see that the patient was making measurable progress at each phase of treatment. A properly filled CPI snapshot from visit five is worth more than three pages of narrative documentation in those situations. The counter-intuitive part is that CPI data sometimes helps you discharge patients earlier than you expected. I had a knee replacement patient whose CPI was averaging a 2.8 across three consecutive scoring windows. Our standard protocol called for re-evaluation at that point, but the data showed consistent progress above threshold. We adjusted the plan of care, reduced frequency, and discharged two weeks early. The payer accepted the CPI trail without question. Doing it the old way—with just narrative notes—would have probably required extending the episode by another two weeks to cover liability.
Where the System Fails and What to Do Instead
CPI isn't a silver bullet. It breaks down in a few specific scenarios that you need to plan for before they hit your desk. Patients with fluctuating conditions. Someone with severe osteoarthritis might have good days and bad days that swing their scores by a full point between scoring windows. A single CPI number can look like regression when it's just normal disease variation. My workaround is to add a brief qualitative note at each CPI entry explaining any environmental factors—weather changes, sleep quality, medication adjustments—that might affect the score. It adds ten seconds per entry and saves you from looking negligent during an audit. New therapists who don't know how to calibrate. I had one therapist who scored everything a 2 regardless of actual performance. When we compared CPI scores between therapists for the same diagnosis group, the variance was absurd. The fix was a two-hour calibration session where I had each therapist score the same five standardized patient cases independently, then we compared results and discussed discrepancies. After that session, inter-rater variance dropped by about sixty percent. Do this for every new hire. Don't assume they'll figure it out on their own.
Small practices with limited EHR customization. If you're on a basic EHR package that doesn't allow custom tabs or automated calculations, building a manual CPI system is still possible but it will be slower. I've seen clinics use a simple spreadsheet that auto-calculates composites and prints a one-page summary for each scoring window. It's not elegant. It works. The key is keeping it in the same workflow as your notes so nobody has a reason to skip it.

A Practical Example From One of My Cases
Last fall I had a patient who came in with a rotator cuff repair and a CPI baseline of 1.2 across all three categories. At visit five, the pain score had improved to a 2.5 but the functional score stayed at 1.0 because she wasn't doing her home exercise program consistently. The composite CPI sat at 1.5, which flagged a problem but didn't tell us what the problem was. Looking at the individual scores rather than just the composite was the moment that changed her outcome. We pulled up her home program compliance log, which showed she was completing about thirty percent of assigned exercises. We had a direct conversation about barriers, discovered she didn't have access to the resistance band we'd recommended, and she picked one up the same day. Her next CPI at visit ten showed a functional score of 2.8 and a composite of 2.4. She finished the episode of care two visits early. That single example shows why CPI matters. The composite number alone would have looked acceptable. The breakdown told the real story. If you're only looking at the composite, you're missing half the signal.
What You Should Actually Download and Implement
There's no official CPI software you can buy from a single vendor because the term isn't regulated or standardized. What you should do instead is build your own framework or find a template. I created a basic spreadsheet-based CPI tracker that handles the scoring logic and composite calculation automatically. It's not fancy but it's functional and it costs nothing to set up. If you want something more structured, several EHR vendors offer CPI modules as add-ons. Make sure you understand exactly what you're getting before you sign. Some of these modules are essentially glorified spreadsheets with a pretty interface and they charge monthly subscription fees that add up fast. I learned this the hard way with a vendor who charged us twenty-five dollars per provider per month for a feature that did less than our internal spreadsheet. The most reliable approach I've found is to build the system yourself using tools you already have access to. Your EHR likely supports custom fields or templates. Excel or Google Sheets works fine for smaller practices. The technology is not the problem. The problem is establishing the discipline to use it consistently, and that has nothing to do with which platform you choose.
The Bottom Line Without the Fluff
Cpi For Physical Therapy is a documentation and tracking method that, when done right, improves clinical outcomes, reduces audit risk, and gives you actual visibility into patient progress instead of guessing. When done poorly, it becomes another checkbox exercise that nobody takes seriously and nobody uses correctly. The difference between those two outcomes is almost entirely about how much thought you put into the design before you start using it, and how consistently you enforce it across your clinical team. Start small. Three categories, four scoring points, one integrated workflow. Get your team comfortable with it. Then expand. Don't try to build the perfect system on day one because the perfect system is the one your staff actually uses every single day, and that only happens through iteration, not upfront planning.