What Actually Happens When You Try To Save Someone
Cpr And Heimlich Maneuver Training sounds simple when you watch the quick videos online, but the real world is messier. You are standing over someone who cannot breathe, your hands are shaking, and the textbook says one thing while your brain is trying to remember three different steps at once. That gap between knowing and doing is exactly why formal training exists. It is not about memorizing a flowchart. It is about building muscle memory so that when adrenaline hits, your body does the right thing before your conscious mind catches up. I went through a certified course back in 2018, and honestly, the part that stuck with me had nothing to do with the theoretical explanations. It was the moment we practiced on the manikin and the instructor said, "You are not pushing hard enough, and you know it." Compression depth for an adult is at least two inches, five times per second minimum rate, and you have to let the chest recoil fully between pushes. On a real person, that means ribs can crack. The manikin gave us audible feedback so we could actually feel what proper depth looked like in real time. Most first-timers are off by a full inch on their first try. You just do not know until someone tells you.
Where To Get Cpr And Heimlich Maneuver Training Near You
The American Heart Association and the Red Cross run certification courses in almost every city. They cost between seventy and one hundred fifty dollars depending on whether it is a basic Heartsaver class or a full BLS for healthcare providers. The certification lasts two years, and renewal is usually faster than the original course. Many community centers and even some employers offer free sessions if you call ahead. Find one that uses updated manikins with feedback technology, not the old ones that just click when you press hard enough. The difference in training quality is noticeable after your second or third practice round. For the Heimlich specifically, you will learn it as part of the choking response module in most CPR courses. There is no separate standalone certification that is widely recognized. The choking protocol overlaps heavily with adult CPR anyway, since both can stem from cardiac compromise. The course will cover infant, child, and adult variations. If you are working in healthcare, BLS covers all of this plus the use of an AED. That extra component matters more than people realize because up to forty percent of choking victims go into cardiac arrest within minutes, and the AED can be the difference between recovery and brain damage.
The Mechanics Behind What You Learn
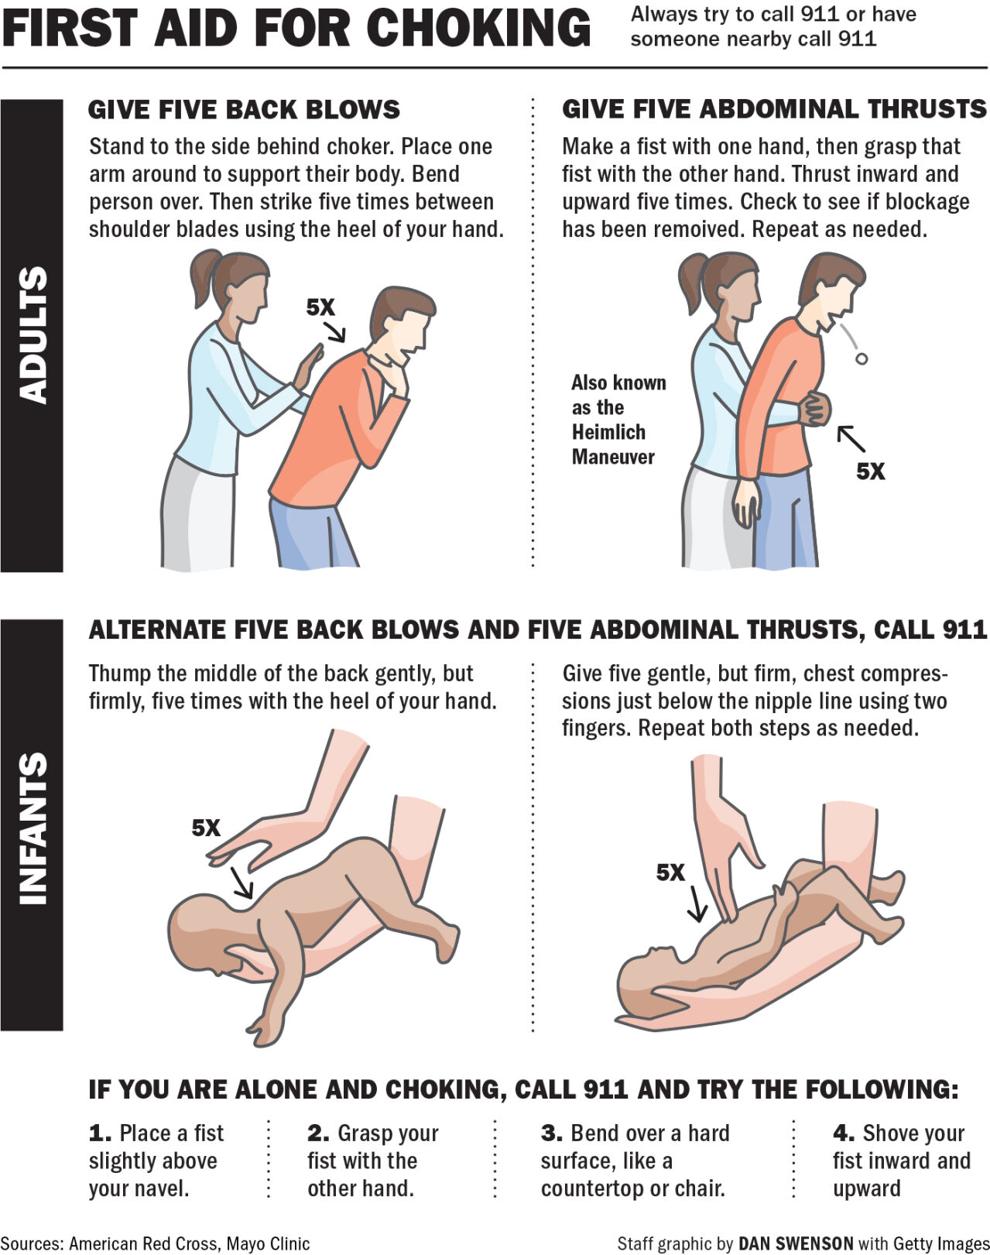
CPR works by manually compressing the heart between the sternum and the spine, pushing blood forward into the brain and vital organs. It is not a perfect substitute for a beating heart, but it moves enough blood to buy time until defibrillation or spontaneous circulation returns. Compression-only CPR, sometimes called hands-only, has become the standard recommendation for untrained bystanders because it removes the hesitation factor of mouth-to-mouth ventilation. The survival rates between conventional and compression-only CPR are statistically similar in the first hours of cardiac arrest, and compression-only is easier to teach at scale. The Heimlich maneuver, or abdominal thrusts, relies on a different mechanism. You position yourself behind the person, make a fist above the navel and below the ribcage, and drive upward and inward sharply. The rapid increase in intra-abdominal pressure forces air up from the lungs, creating an artificial cough that can dislodge the obstruction. It is surprisingly effective for partial blockages where the person can still make some sound or cough. The key detail most people miss is that you do not wait for complete obstruction before acting. If someone is wheezing, grasping their throat, or making high-pitched noises, intervene early. Waiting for silence means waiting until they lose consciousness, and then you switch to CPR instead.
Get the Full Details

Edge Cases That Textbooks Do Not Cover Well
During my training, we did a scenario with an obese patient on the manikin, and the instructor told us to place our hands lower than the standard navel landmark, right around the lower sternum. On a real person with significant abdominal mass, the standard hand placement may not generate enough upward force to create the pressure spike needed. You wrap your arms around the chest instead and perform chest thrusts rather than abdominal thrusts. This applies to pregnant individuals as well, and honestly, I have seen far more confusion about this than any other part of the course. A lot of people still instinctively reach for the abdomen because that is what the videos show, and that can fail in these populations. Another thing they do not emphasize enough is self-Heimlich. If you are alone and choking, you can thrust your own abdomen against the back of a chair, a countertop edge, or even your own fist. It is not as clean as having a second person do it, but it works. I learned this from a paramedic who told me about a call where a restaurant patron saved himself using the corner of a table. The paramedic arrived to find him conscious, coughing, and embarrassed. That story got more attention in the class than any of the scripted scenarios.
Limitations You Need To Accept
CPR has a steep attrition curve. Even with perfect technique, manual compressions only achieve about thirty percent of normal cardiac output. That means you are buying minutes, not hours. Every minute without defibrillation reduces survival probability by roughly ten percent. After ten minutes of untreated cardiac arrest, the chance of meaningful neurological recovery drops below five percent regardless of how good your compressions are. The training will make you competent, but competence alone does not guarantee a positive outcome. You need an AED within range and minimal delay between collapse and first shock. The Heimlich maneuver is not risk-free either. Improper force or incorrect positioning can cause internal organ damage, rib fractures, or splenic injury. I have read case reports of diaphragmatic rupture following repeated abdominal thrusts in elderly patients with fragile tissue. The maneuver should never be attempted on someone who is already unconscious, coughing effectively, or showing signs of partial airway patency. Those people are moving enough air on their own, and aggressive intervention can push the obstruction deeper or cause trauma. The rule of thumb is clear symptoms only: inability to speak, inability to cough, blue or gray lips, and loss of consciousness within seconds. Infant choking is a completely separate protocol from adult. You do not perform abdominal thrusts on infants under one year. Instead, you use back slaps and chest thrusts with the infant positioned face-down along your forearm. The force required is minimal, and the thoracic cavity is compressible enough that gentle but firm thrusts work. One mistake here, like applying adult-level force or using the wrong position, can cause serious injury. This is why the in-person skills check matters. Watching a video will not teach you how much pressure is appropriate for a six-month-old.
What To Expect On The Day Of Training
Plan for two to four hours depending on the course level. You will watch demonstrations, practice compressions on a manikin, use an AED trainer, and perform choking relief on another manikin or partner. Some centers require you to demonstrate proficiency on each skill before receiving certification. Do not skip the hands-on portion because of embarrassment. The instructors have seen everyone from people who overcompress to those who barely touch the chest, and they do not judge. The only person you are holding back is yourself if you stay quiet. Take notes on the compression rate. The metronome beat of one hundred to one hundred beats per minute is something you can internalize by singing "Stayin' Alive" by the Bee Gees, which the AHA officially recommends as a timing aid. But the real metric is depth and full recoil. Rate is secondary to quality. When you are tired during extended compressions, your depth drops before your rate does, and that is when perfusion fails. Rotate with another rescuer every two minutes if possible, even in a real setting if another trained person is available.
A Few Things That Will Surprise You
First, most cardiac arrests happen at home, not in public. The average emergency response time in many urban areas is eight to twelve minutes, and in rural areas it can exceed twenty. That means your spouse, your child, or your coworker is statistically more likely to be the first responder than a paramedic. Training is not about preparing for a rare event. It is about being prepared for the event that happens in your own kitchen. Second, the AED is designed to be used by laypersons. It talks you through every step, analyzes the rhythm automatically, and will not deliver a shock unless it detects a shockable rhythm like ventricular fibrillation or pulseless ventricular tachycardia. You cannot accidentally shock someone who does not need it. The device makes that call, not you. The biggest barrier is psychological, not technical. People hesitate because they think they might do something wrong. They will not. Third, after any successful Heimlich maneuver or CPR episode, the person still needs medical evaluation. Abdominal thrusts can cause delayed internal bleeding. Chest compressions frequently fracture ribs, and while rib fractures are survivable and expected in good CPR, they require imaging to rule out lung puncture or organ damage. Do not assume the person is fine because they are breathing again. Get them to a hospital regardless.