Getting Cpt Code 97530 Occupational Therapy Right on Claims
Cpt Code 97530 Occupational Therapy covers therapeutic activities designed to improve gross/fine motor skills, endurance, range of motion, and functional performance. It is not a catch-all code, and that distinction is where most claims run into problems. The code specifically targets activities like balance training, balance board work, proprioceptive tasks, and upper body coordination drills that are directly tied to measurable functional goals. If the activity could be described as exercise in a general fitness sense, it probably does not qualify. The way I handle this code starts with how the session is documented from the first minute. I need to see what the patient was actually doing, the resistance level or complexity introduced, and how it maps back to a written goal. Here is a concrete example that tripped me up recently. A provider billed 97530 for a patient using a therapy ball for seated core work. The documentation said "improve core stability and balance." The payer denied it, pointing out that the activity lacked specificity about the functional carryover. I rewrote the note to specify that the patient performed unilateral weight shifts on the ball while reaching toward targets, with the explicit goal of improving the ability to transfer from chair to wheelchair safely. That revision got the claim paid on resubmission. The key detail that most people miss is the difference between 97530 and 97110. Both involve movement. The distinguishing factor is functional application. 97110 is aerobic or conditioning activity, and 97530 is therapeutic activity with a direct functional goal. A balance board drill for a stroke patient working on weight-bearing tolerance is 97530. A balance board drill as part of a general conditioning circuit without a specific functional outcome attached leans toward 97110, and you should verify what your particular payer considers acceptable there. Some carriers are stricter about this than others.
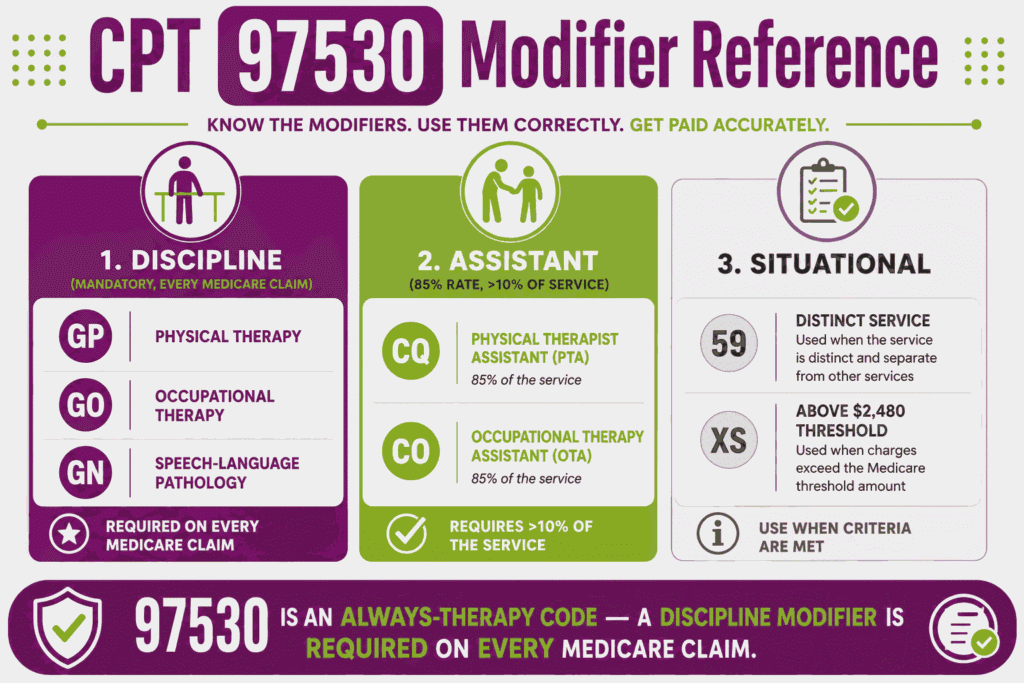
Another thing that causes friction is unit counting. The standard billing rule is 15 minutes per unit of 97530, counted in 15-minute increments. But the time you bill must align with the actual face-to-face therapeutic activity. If a patient spends eight minutes on balance board work and then twelve minutes on a different treatment modality, you bill one unit of 97530. You do not round up to two units. Rounding up is one of the most common audit triggers in occupational therapy billing, and it is entirely avoidable. I also want to address modifier usage because this is where claims get unnecessarily complicated. When 97530 is provided on both the left and right sides of the body during the same session, modifier 50 or the RT/LT modifiers apply depending on your payer's preference. Some commercial payers require 50. Medicare and many Medicaid programs prefer the side-specific modifiers. If you are billing a multi-site practice, standardize your modifier policy across all locations to reduce variation and the subsequent denials that come from inconsistent formatting. There is a practical limitation to 97530 that nobody likes to talk about. It requires close supervision or direct one-on-one contact for at least half the encounter to meet Medicare guidelines. If you are running a group session where the therapist is monitoring multiple patients simultaneously, 97530 may not be the appropriate code for that time block. In those situations, 97188, the group therapeutic activities code, exists specifically for that scenario. Using 97530 in a group setting and getting caught by an audit is a real risk, and it happens more often than you would expect given how convenient the code feels to bill.
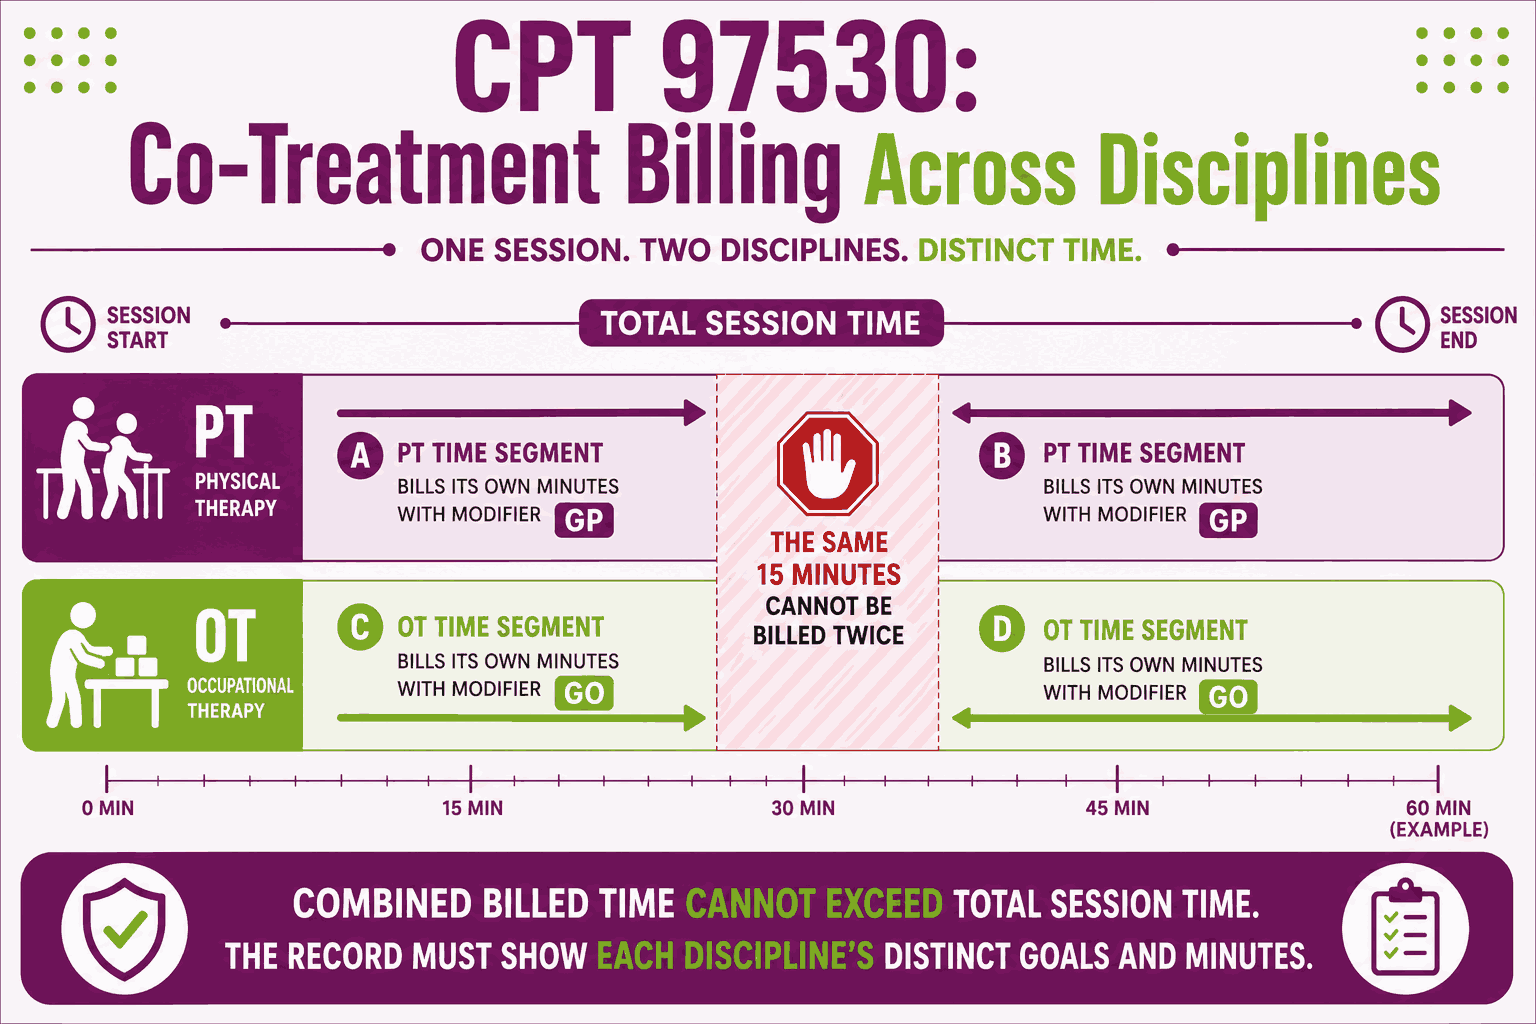
For documentation, keep a simple but consistent template in your electronic health record. I use a format that captures the activity, the complexity or resistance level, the functional goal it addresses, and the patient's response during the session. "Patient performed weight shifts on wobble disc with visual feedback to improve weight-bearing symmetry for transfers; required minimal cueing; reported decreased hesitation compared to previous session." That level of detail gives the auditor exactly what they need and protects you when a review comes months after the service date. The other counter-intuitive point is that 97530 cannot be billed alongside certain other codes in ways that seem logical but are actually restricted. For instance, pairing 97530 with 97140 (manual therapy) in the same time block is fine as long as you document separate minutes for each and the activities are distinct. But stacking 97530 with another therapeutic activity code for the same body area within the same 15-minute window can raise red flags. The payer may question whether the patient was actually performing two separate therapeutic activities simultaneously. Split the minutes clearly in the documentation and use different goal references for each code. If you are looking for a downloadable reference sheet that covers 97530 documentation requirements, common payer-specific modifiers, and the Medicare supervision guidelines, the CMS.gov website has the most current official guidance. The American Occupational Therapy Association also publishes clinical practice resources that include coding recommendations. Neither of those is a quick download, but they are the most reliable sources available and they get updated regularly when code set changes happen.
Get the Full Details

The bottom line is that 97530 is straightforward when you understand its boundaries. It covers therapeutic activities with clear functional goals, requires direct contact documentation, and demands accurate unit accounting. The denials almost always come from vague documentation, incorrect unit rounding, or applying the code to group settings where it does not belong. Fix those three things and the code works cleanly.