What Cpt Code Ct Guided Renal Biopsy Actually Covers
The CPT code for a CT guided renal biopsy is 50300. That is the only code you need to know for the procedural billing side. It describes the complete act of image guidance plus the actual tissue sampling through the percutaneous approach. Some people try to bundle needle passes separately. You cannot do that. The code includes all imaging guidance and needle trajectory adjustments during that single session. I have seen coders pair 50300 with 76942 or 77002. Those are wrong. Those are standalone imaging codes. When you are billing CT guidance as part of a biopsy, the guidance is already inside 50300. Double billing it is how audits start.
How Cpt Code Ct Guided Renal Biopsy Is Used in Practice
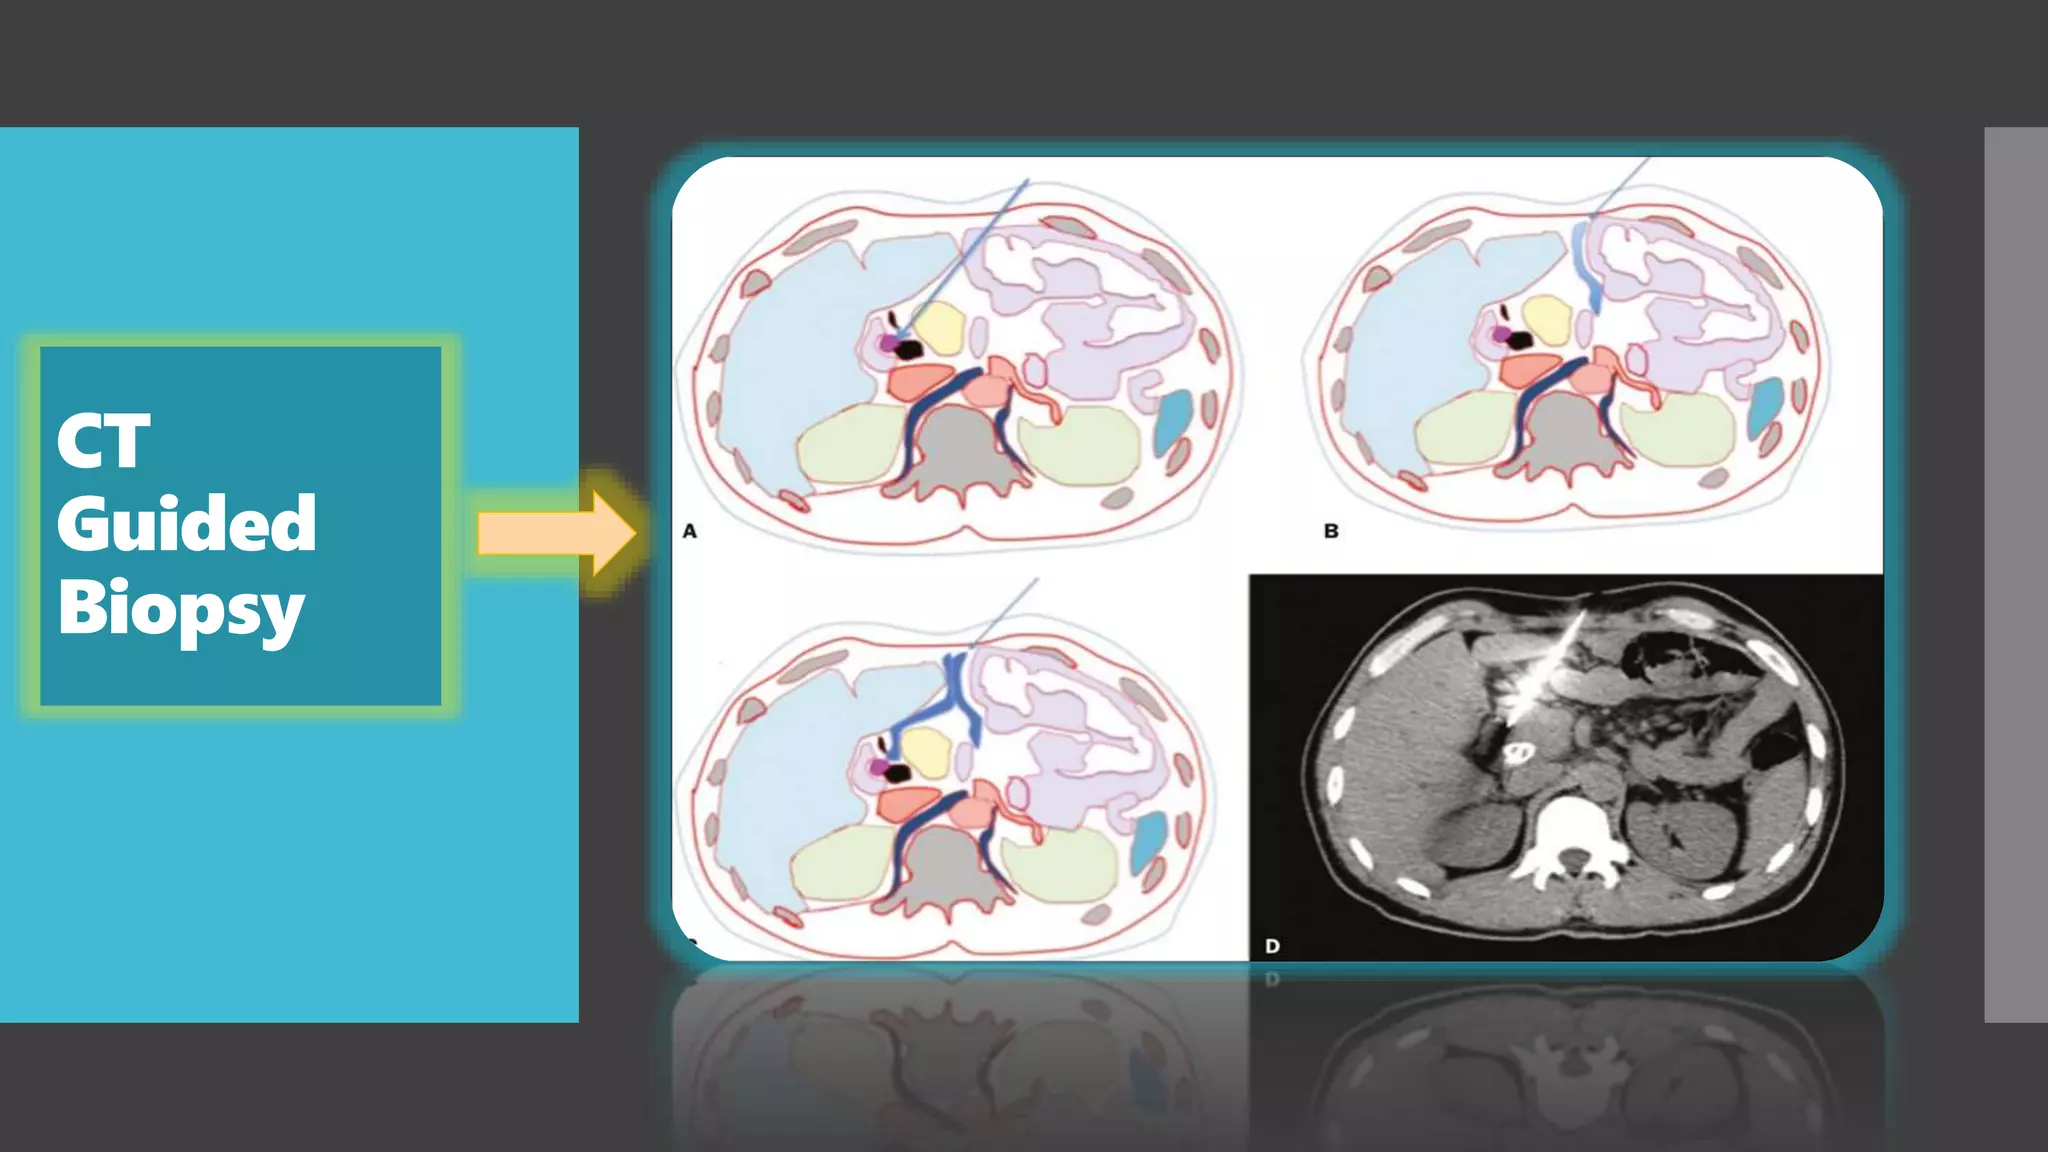
Here is how the workflow actually looks from a coding standpoint. The patient comes in, gets positioned on the CT table, localizing scans happen first, then the radiologist marks the skin entry point, numbs the area, advances the core needle through the flank, takes the sample, and confirms hemostasis. That entire sequence maps to one line: 50300. No add-on codes. No separate guidance code. Just 50300 once. What trips people up is the distinction between CT guidance and fluoroscopic guidance. If the procedure is done under fluoro instead of CT, the code changes entirely. There is no specific CPT code for a renal biopsy under fluoroscopy in the same way. You would look at the surgical codes for the biopsy itself plus any applicable imaging add-ons depending on the payer. But for CT guided specifically, 50300 is clean and complete. I ran into a case last year where a physician performed a CT guided biopsy but switched to ultrasound mid-procedure because the kidney migrated off the CT field of view. The documentation only noted CT guidance. The coder billed 50300. The claim got denied because the ultrasound use was never documented. The fix was straightforward but tedious: the radiologist had to amend the operative report to reflect the hybrid guidance approach. We ended up still billing 50300 since CT was the primary modality, but the documentation had to match exactly what happened. That kind of gap costs you weeks in denial management.
Common Billing Pitfalls
There are a handful of patterns that show up repeatedly. The biggest one involves laterality. 50300 does not have a built-in laterality modifier like some surgical codes do. When you biopsy a left kidney, you do not append -LT. When you biopsy both kidneys in the same session, which happens rarely but does occur, some payers expect two units or modifier 50. Most commercial payers and Medicare will allow two units with no modifier if the note supports bilateral sampling. Read your local coverage determination before you guess here. Another frequent error is confusing this with needle localization codes. 50300 is a biopsy code, not a localization code. If someone places a fiducial marker or a localization wire before the biopsy, that is a completely different code set and usually falls under breast or stereotactic guidance, which does not apply here. Do not layer unrelated codes onto 50300 just because something else happened in the room during the procedure. Contraindications and refusal to biopsy matter more than you might think. If the physician evaluates the kidney via CT, decides the lesion is not safe to sample due to coagulopathy or positioning, and aborts, you do not bill 50300. You may bill a diagnostic CT code and an E/M code if the evaluation was distinct and documented separately. But the biopsy code requires an actual tissue sample to be obtained. Period.
Get the Full Details
Documentation Requirements That Actually Matter
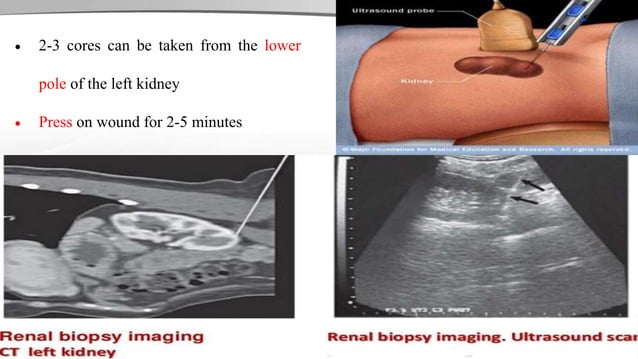
The operative note needs to include four things at minimum. The indication for the biopsy. The imaging modality used for guidance. The specific anatomical target, meaning which kidney and which region of the kidney. And confirmation that tissue was retrieved. If any of those four items is missing, the claim becomes vulnerable to medical review. I learned that the hard way when a payer requested records for a random audit and we could not produce evidence that a specimen was actually obtained because the note only said "biopsy performed" without mentioning the sample. Sedation documentation is another quiet trap. If the patient receives moderate sedation, that requires its own separate coding with time documentation. Many facilities forget to log the start and stop times for the sedation. Without those timestamps, you cannot bill the sedation codes regardless of how much midazolam or fentanyl was administered. Keep a separate sedation flow sheet or ensure the anesthesia record is cross-referenced in the operative note.
When 50300 Is the Wrong Code
Not every CT guided kidney procedure is a 50300. If the intent is drainage rather than tissue sampling, you are looking at a percutaneous nephrostomy or abscess drain code instead. The approach might look identical. The needle goes through the same path. But the purpose changes the entire coding assignment. A CT guided renal abscess drain is not a biopsy. Payors will flag that mismatch immediately. Similarly, if you are doing a biopsy of a renal mass that has already been characterized and you are merely confirming a known diagnosis with a pre-planned approach, the code is still 50300. The coding does not change based on diagnostic certainty. It changes based on whether you are sampling tissue or doing something else entirely. The method defines the code, not the clinical context. One more edge case worth noting. If the physician performs a CT guided renal biopsy and then immediately uses the same access tract for a therapeutic injection, like a bleomycin administration into a cyst, some payers may consider that a separate procedure. Others will bundle it. There is no universal rule. You have to check the specific payer policy. I stopped trying to predict this and just document everything separately and let the payer decide. It saves more time than preemptive bundling decisions that get reversed anyway.
What Cpt Code Ct Guided Renal Biopsy Excludes
The code does not include post-procedure imaging. If you order a CT scan afterward to check for bleeding or retroperitoneal hematoma, that is a separate diagnostic CT code. It may or may not be covered depending on the payer and the clinical indication. Do not assume it is bundled. It is not. Pathology evaluation of the biopsy specimen is also separate. The pathologist's work is coded under the surgical pathology section, typically 88305 or similar depending on complexity. That never goes on the same line as 50300. These are two distinct billing events that happen back to back but belong to different departments. If you need to verify the exact wording of 50300, the CPT manual entry reads: "Percutaneous needle biopsy of renal mass or lesion, image guidance." That is it. Five words in the descriptor and a code that covers everything from patient positioning through specimen retrieval under CT guidance. Anything outside that scope needs its own code. Anything inside that scope is already paid under 50300. There is very little gray area if the documentation is clean.