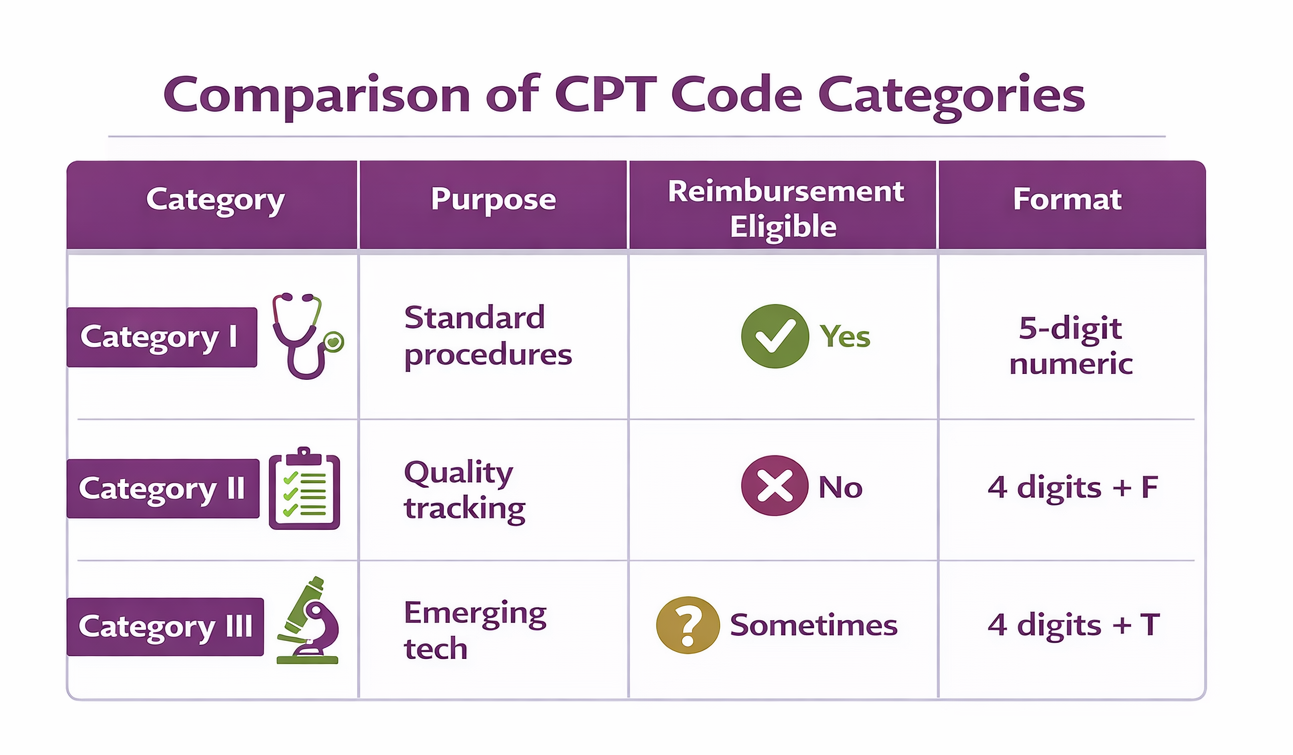
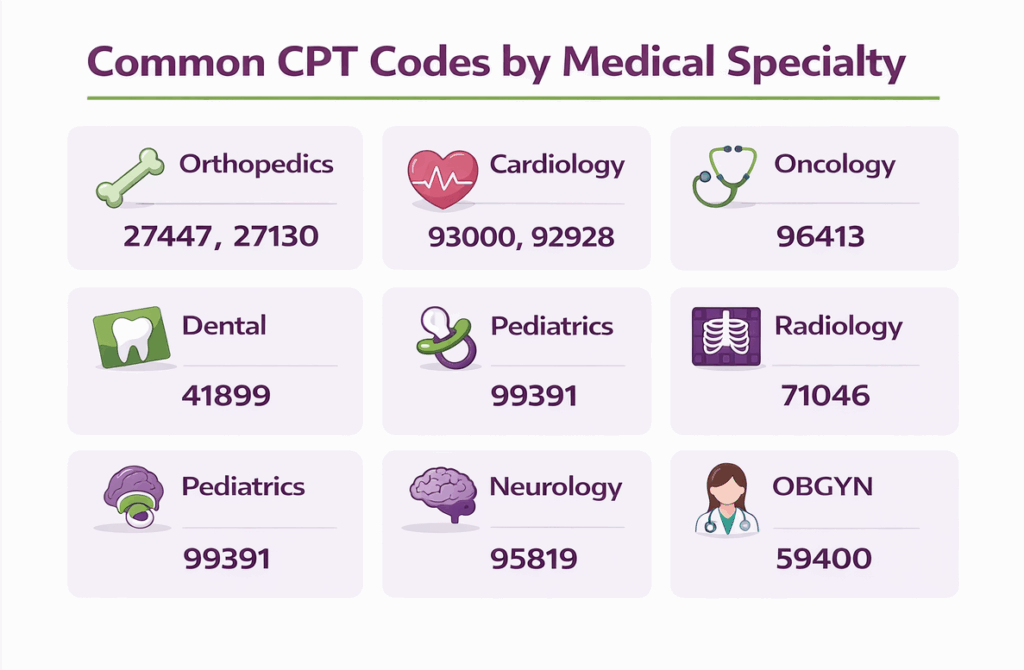
Reading CPT Code Descriptions the Way They Actually Work
Most people treat CPT code descriptions as if they're standalone definitions you can look up and memorize. They aren't. A CPT code description is really just a label attached to a bundle of clinical work, and the description alone will mislead you half the time if you don't know what's hidden underneath it. The American Medical Association maintains these codes, and the descriptions change every year. When you pull up a code like 99213, the description might say "office visit, established patient, straightforward medical decision making." Sounds simple enough. But the actual work involved could include reviewing lab results, prescribing medication adjustments, counseling a patient for twenty minutes, and documenting all of that in a way that meets payer-specific requirements. The description doesn't tell you any of that. That's the first thing beginners get wrong.
Understanding Cpt Code Description in Practice
I spent years doing medical coding for outpatient clinics before moving into consulting, and the thing that cost me the most headaches wasn't the codes themselves. It was the modifiers and the fact that the same code description could mean something totally different depending on who was billing it. Let me give you a concrete example. We had a surgery center that would routinely bill CPT code 29881, which is an arthroscopy of the knee, diagnostic, with synovial biopsy. The description made it sound like a minor procedure. One of our surgeons would do a quick diagnostic scope and grab a biopsy sample if he saw anything interesting. Payers were flagging it constantly because the description didn't reflect the actual time and complexity. The workaround was straightforward once we figured it out. We started adding modifier 59 when the biopsy was a distinct procedural service, and we made sure the operative report explicitly separated the diagnostic scope from the biopsy work. That usually resolved the audits. It didn't help with everyone, though. Here's the counter-intuitive part that nobody really talks about. CPT code descriptions are written for physicians, not coders or billers. The language assumes clinical context that isn't in the description. Take code 76700, an abdominal ultrasound complete. The description says "complete," but the AMA has separate guidance that defines what complete actually means for this code, and it includes documenting specific structures. If your radiologist doesn't mention the IVC or the portal vein in the report, the code description is technically accurate but the code itself may not be billable. The description lies by omission.
Another thing that trips people up is the relationship between CPT descriptions and HCPCS Level II codes. They're not the same system. CPT covers procedures and services. HCPCS Level II covers supplies, durable medical equipment, and services that don't have a CPT equivalent. When a coder tries to match a CPT code description to a HCPCS code, it usually goes poorly. I've seen entire departments waste weeks trying to force-fit descriptions across the two systems. They shouldn't be cross-referenced unless there's an explicit linker in the code set. The biggest bottleneck with CPT code descriptions is that they are not self-contained. You need the accompanying guidelines, appendices, and payer-specific policies to actually use them correctly. The base code book gets you maybe sixty percent of the way there. The other forty percent is scattered across CMS manuals, NCCI edits, and individual payer bulletins. If you're relying solely on the description text, you're working blind for nearly half your cases. There's also the issue of descriptor creep. Over the last several years, the AMA has expanded code descriptions to be more specific, which sounds good but actually creates more confusion. A code that used to cover a broad category now has three more specific versions. The old codes aren't deleted immediately, so you end up with legacy descriptions sitting alongside new ones, and payers often haven't updated their systems to match. I've had to explain to clients that the code description they're looking at in their software is from the 2023 edition while their payer is still processing claims against the 2022 rules. That mismatch causes denials that look like coding errors when they're really just version drift.
Get the Full Details
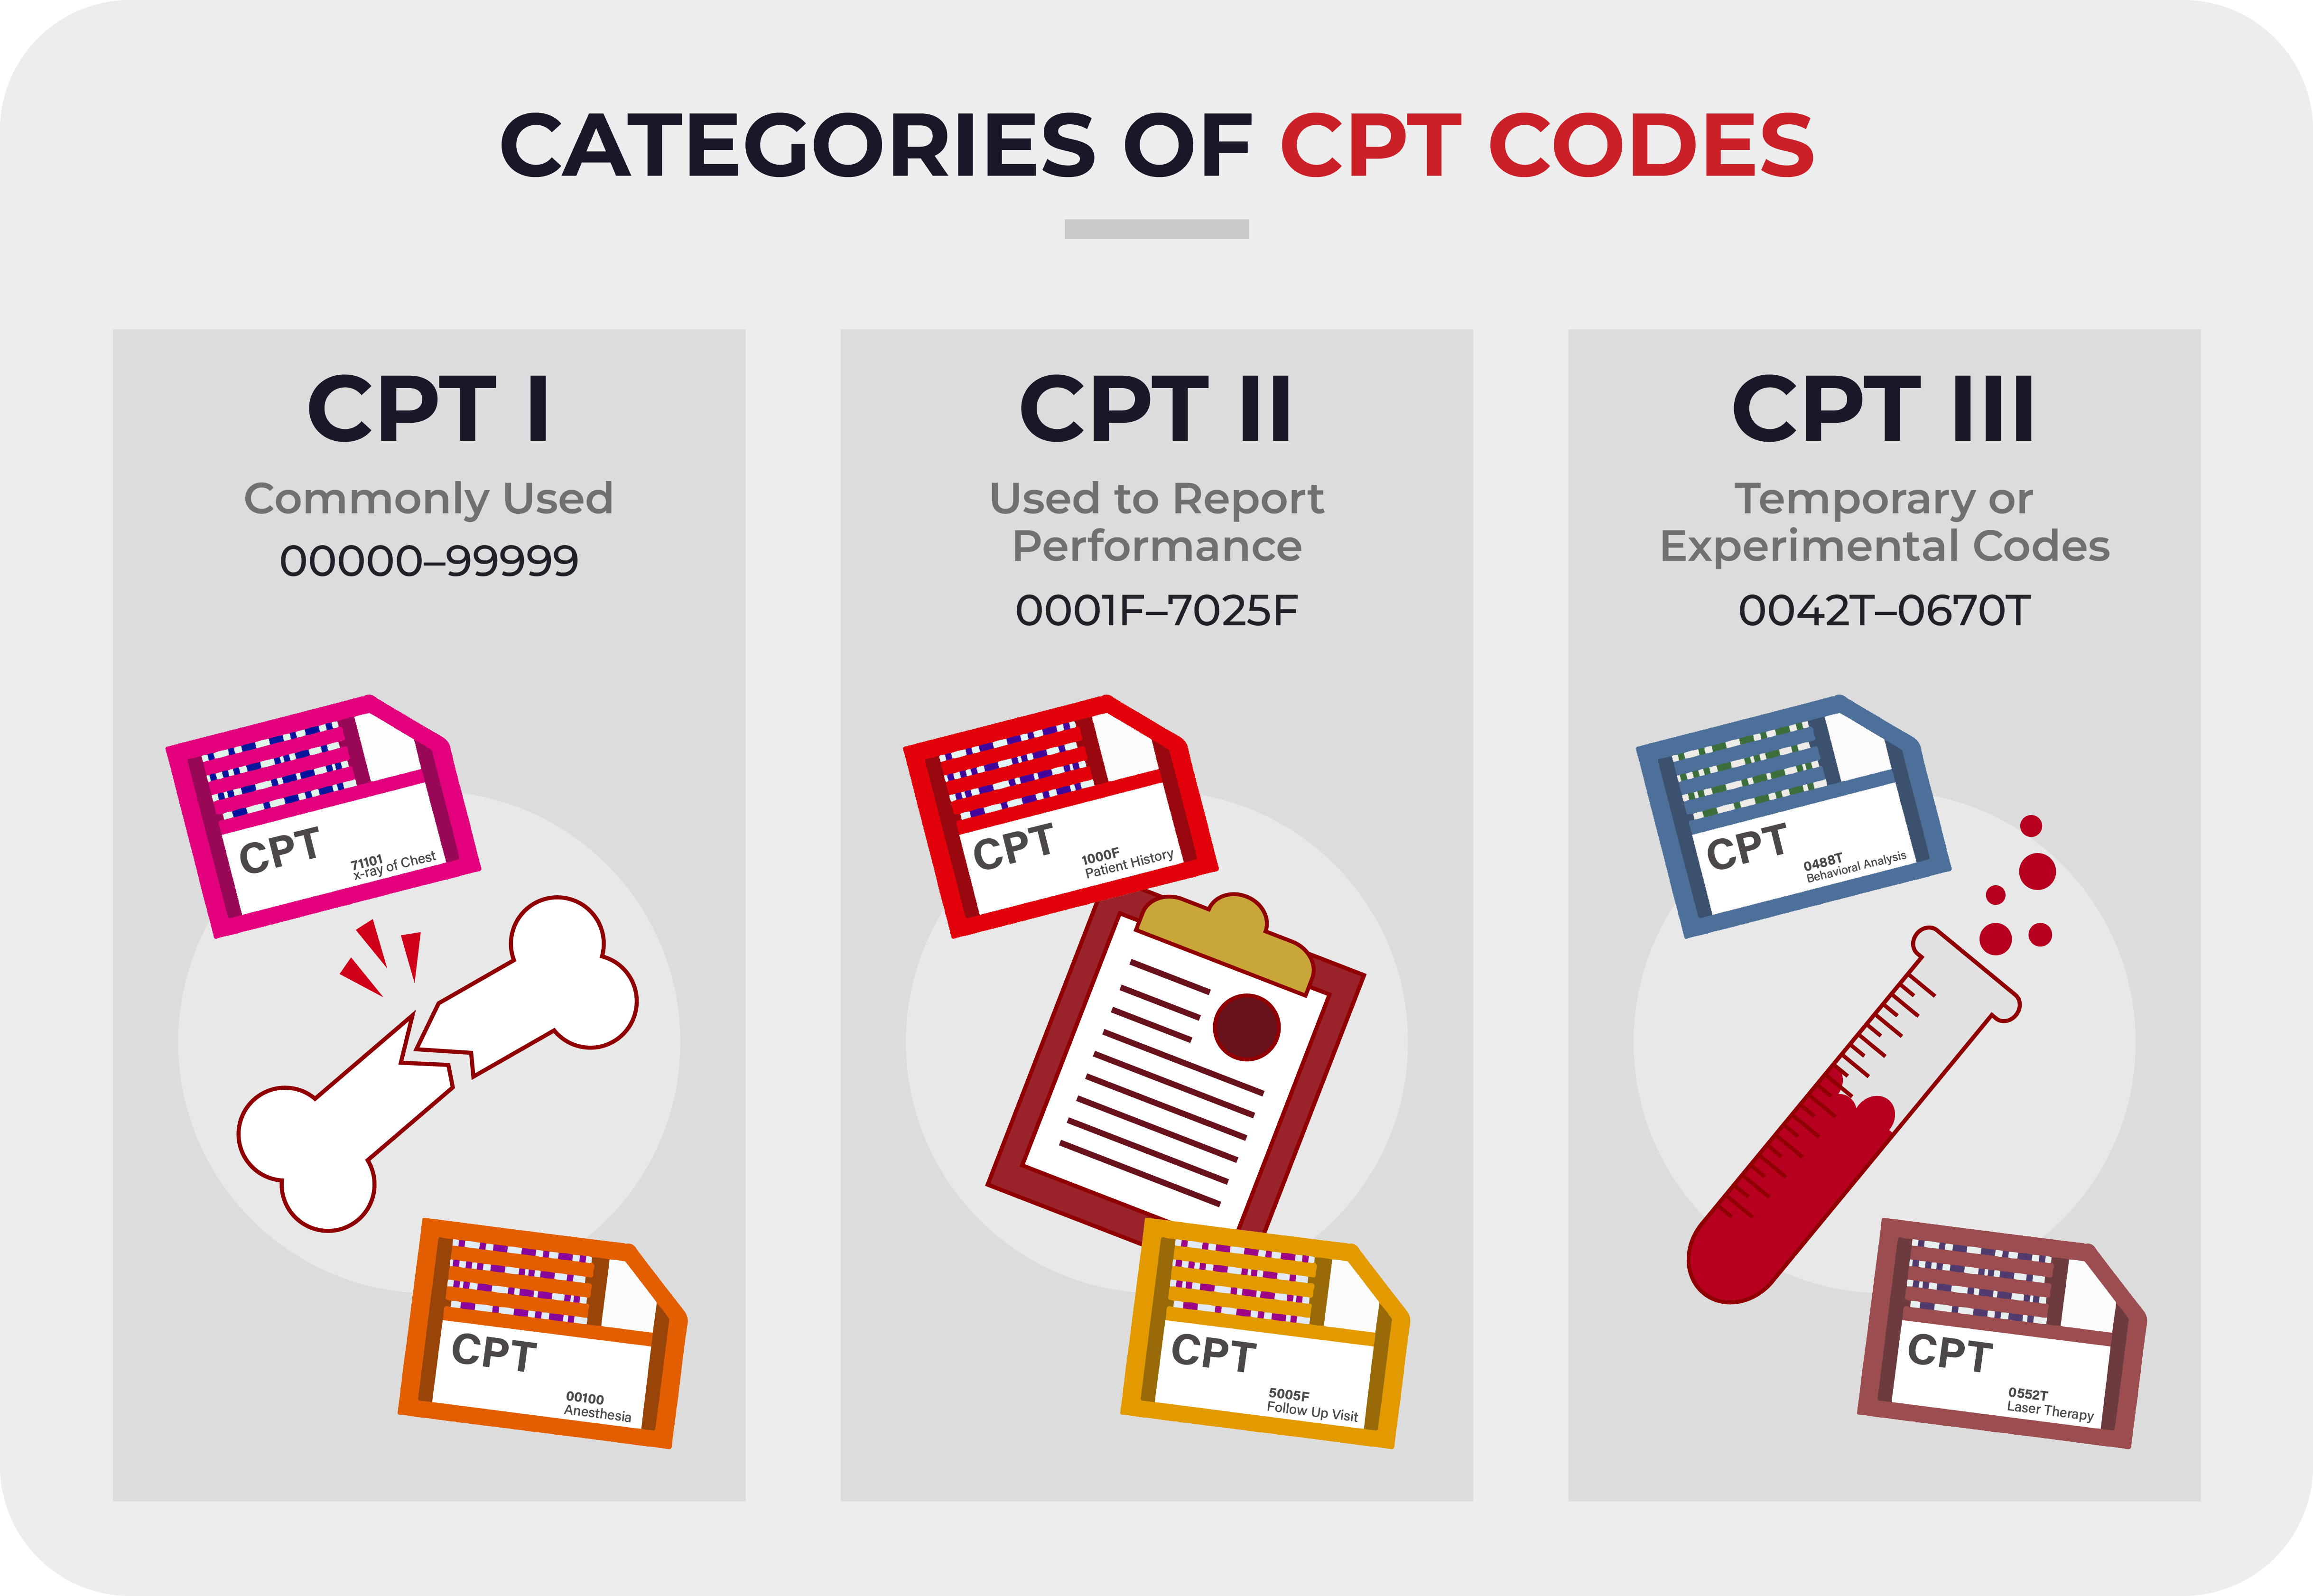
If you're trying to learn how to read these descriptions properly, start with the CPT Professional Edition and work through the guidelines section before you touch any individual code. The guidelines are where the actual rules live, not in the descriptions. Then cross-reference with the NCCI Policy Manual. It's dry reading but it will save you from making mistakes that cost real money. The manual is available free on the CMS website if you search for NCCI edits documentation. One more practical note. When you encounter a code description that feels vague or incomplete, don't guess. Look at the prior year's version. Sometimes the current year's description is tighter because the AMA closed a loophole. Other times they loosened it, and the old description was actually more precise. Checking the annual updates file from the AMA will show you exactly what changed, and that comparison is often more useful than reading the new description straight.