Setting Up the Right Code When They Walk In
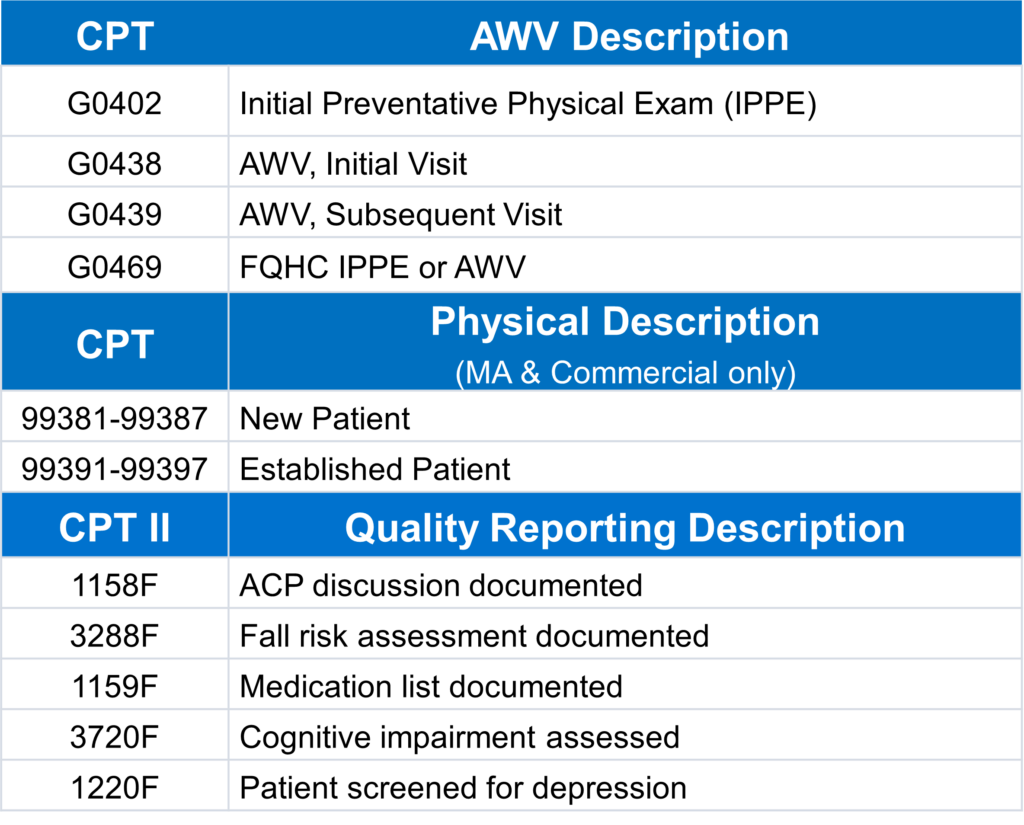
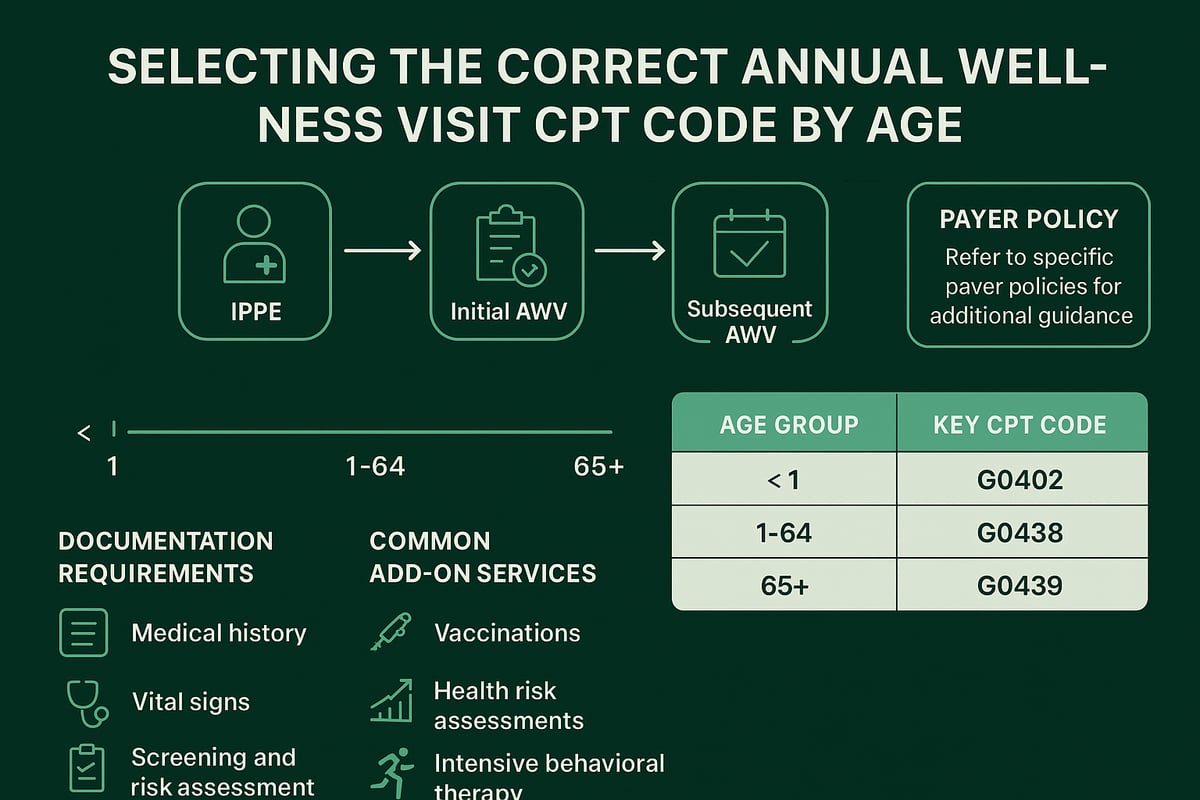
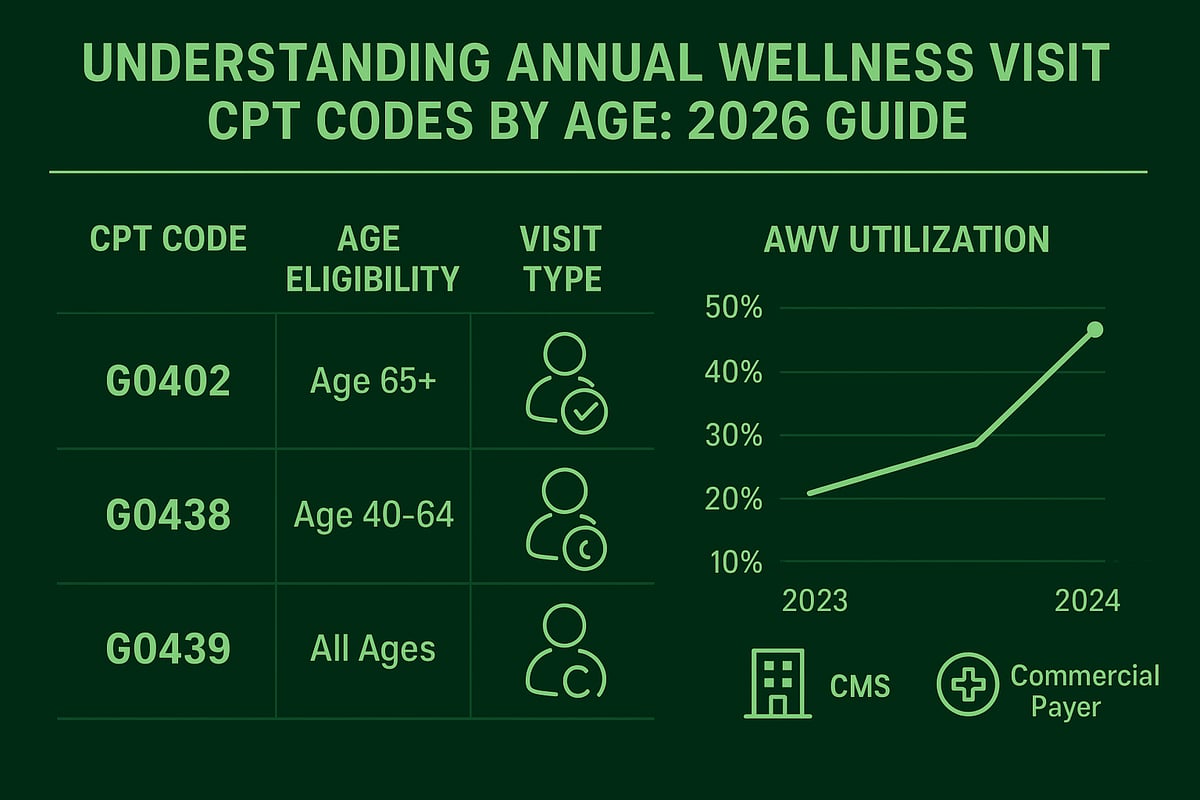
You don't want to waste ten minutes re-checking a code when the room is already holding a patient who's been expecting their exam for six weeks. The straightforward answer is that for a routine annual physical with an established patient, you generally go with the G0439 code if this is a Medicare patient on their annual wellness visit, or the 99212 through 99215 range for established-patient office or other outpatient evaluation and management visits when dealing with commercial insurance or self-pay. That's the surface-level answer. The actual day-to-day reality involves a few wrinkles. The most common confusion people run into is thinking G0439 and the 99212-99215 codes are interchangeable. They are not. G0439 is strictly for Medicare annual wellness visits, which have a defined checklist of required elements. If your Medicare patient is coming in for a true physical -- blood work, vaccinations, a head-to-toe assessment, and some preventive counseling -- G0439 is usually the right call as long as you can document the required elements. If the patient has a complaint, even a minor one, that visit stops being purely preventive and you shift into E/M coding. That's where it gets messy.
Key Details on the Cpt Code For Annual Physical Exam Established Patient
Let me walk through what actually happens when you're running these codes day to day. For a Medicare established patient, G0439 requires a comprehensive health risk assessment, measurements of height, weight, BMI, blood pressure, pulse, and a fall-risk assessment. It also requires review of functional status and potential caregivers, plus a personalized prevention plan. If you miss any of those elements, the claim will either deny or get flagged during audit. I once had a clinic get burned on this because they were documenting the exam but never actually writing out the personalized prevention plan section. Every claim from that quarter got questioned. The fix was straightforward -- we built a template into the EMR that forced the prevention plan to be populated before the visit could be closed out. For commercial or self-pay established patients, the 99212 through 99215 codes rely on medical decision making or total time spent. The 2023 E/M guideline changes removed the requirement to meet a specific MDM table, so you can choose between MDM-based or time-based billing. Most practices I know default to MDM because it is simpler to document and review, but time-based billing can actually give you a higher level when the visit runs long due to counseling or coordination of care. The catch is that you have to document the total time on site, not just face-to-face time, and you have to account for pre- and post-visit work that falls on the same calendar day. Here is something most people do not think about: the Z00.00 diagnosis code. You need this on the claim for an established patient annual exam. If you use it, certain services like lab work may be denied as not medically necessary because the visit is classified as preventive. Some payers will cover preventive labs under the physical, others will not. I dealt with a situation where a patient's stat panel came back as a denied claim because the office used G0439 with only Z00.00 and no additional diagnostic codes, but the payer had a policy that preventive visits do not cover metabolic panels unless ordered for a specific medical reason. The workaround was adding the appropriate ICD-10 code for elevated cholesterol -- Z79.899 -- and resubmitting. That shifted the claim from preventive to medically necessary and it went through.
Practical Setup in the EMR
You will want to build templates that match the two main scenarios. One template for the G0439 Medicare annual wellness visit, and another for the 99212-99215 established-patient physical. Put them in your quick-access bar so your providers are clicking the right one every time. I recommend setting up a default diagnosis of Z00.00 on both templates, then having a second diagnosis slot ready for any conditions that come up during the exam. That way you are not scrambling to add codes after the visit when the billing staff is already chasing you. For time-based billing on 99212-99215, make sure your EMR can capture total time. Some systems only pull from face-to-face encounter notes. If yours does that, you are leaving money on the table for any visit where you spend twelve minutes reviewing labs before the patient comes in and another eight minutes documenting after. That is twenty minutes total, and at the current 2024 conversion factors it can push a 99213 into a 99214 territory depending on your state's fee schedule. Check with your specific payer to confirm their time rules, because some still require the documentation to clearly state the total time rather than just implying it from progress notes.
Get the Full Details

Where This Breaks Down
Annual physical exams are becoming a less reliable revenue stream for many practices. A growing number of commercial payers have dropped coverage for routine physicals entirely, referring patients instead to wellness visits that may not exist in your contract. Before you invest heavily in training staff on physical exam coding, verify what your top five payers actually cover. If you are seeing a pattern of denials for 99212-99215, the problem is likely payer policy, not your coding. Medicare annual wellness visits also have a hard limitation: you can only perform one per 12-month period. If a patient comes in early, you cannot bill G0439 again until the window resets. Some clinics try to bundle a follow-up E/M code onto the same claim, but that requires distinct, separately billable work beyond the wellness visit, and not every payer accepts that approach. In practice, you are better off scheduling the next annual wellness visit at the appropriate interval and handling any interim issues through separate visits. It is cleaner for audits and it avoids the headache of trying to justify a modifier 25 on a preventive visit claim. The bottom line is that coding an annual physical for an established patient is not complicated if you know which path your patient falls under. Medicare gets the G0439 track with its strict documentation requirements. Everyone else mostly rides the 99212-99215 track with the Z00.00 diagnosis and a few condition codes when needed. Build the templates, verify your payer contracts, and stop trying to force a single code to do work it was never designed for.