Getting the CPT Code For Gynecological Exam Right on Your First Try
Most people grab code 99202 through 99215 for a gynecological exam without thinking about it. That works sometimes, but it is rarely the most accurate choice and often leaves money on the table or triggers an audit flag. The reality is that gynecological encounters sit in a weird middle ground between a comprehensive preventive visit and a problem-focused office visit, and the coding depends entirely on what actually happened during the encounter. I want to talk about how to pick the right code, when to layer on modifiers, and where most billing departments get tripped up. I have spent years fixing claims that came back with denials because someone slapped a 99213 on a visit that was clearly a well-woman exam, or missed a modifier that would have made the whole thing clean.
The Cpt Code For Gynecological Exam: What It Actually Is
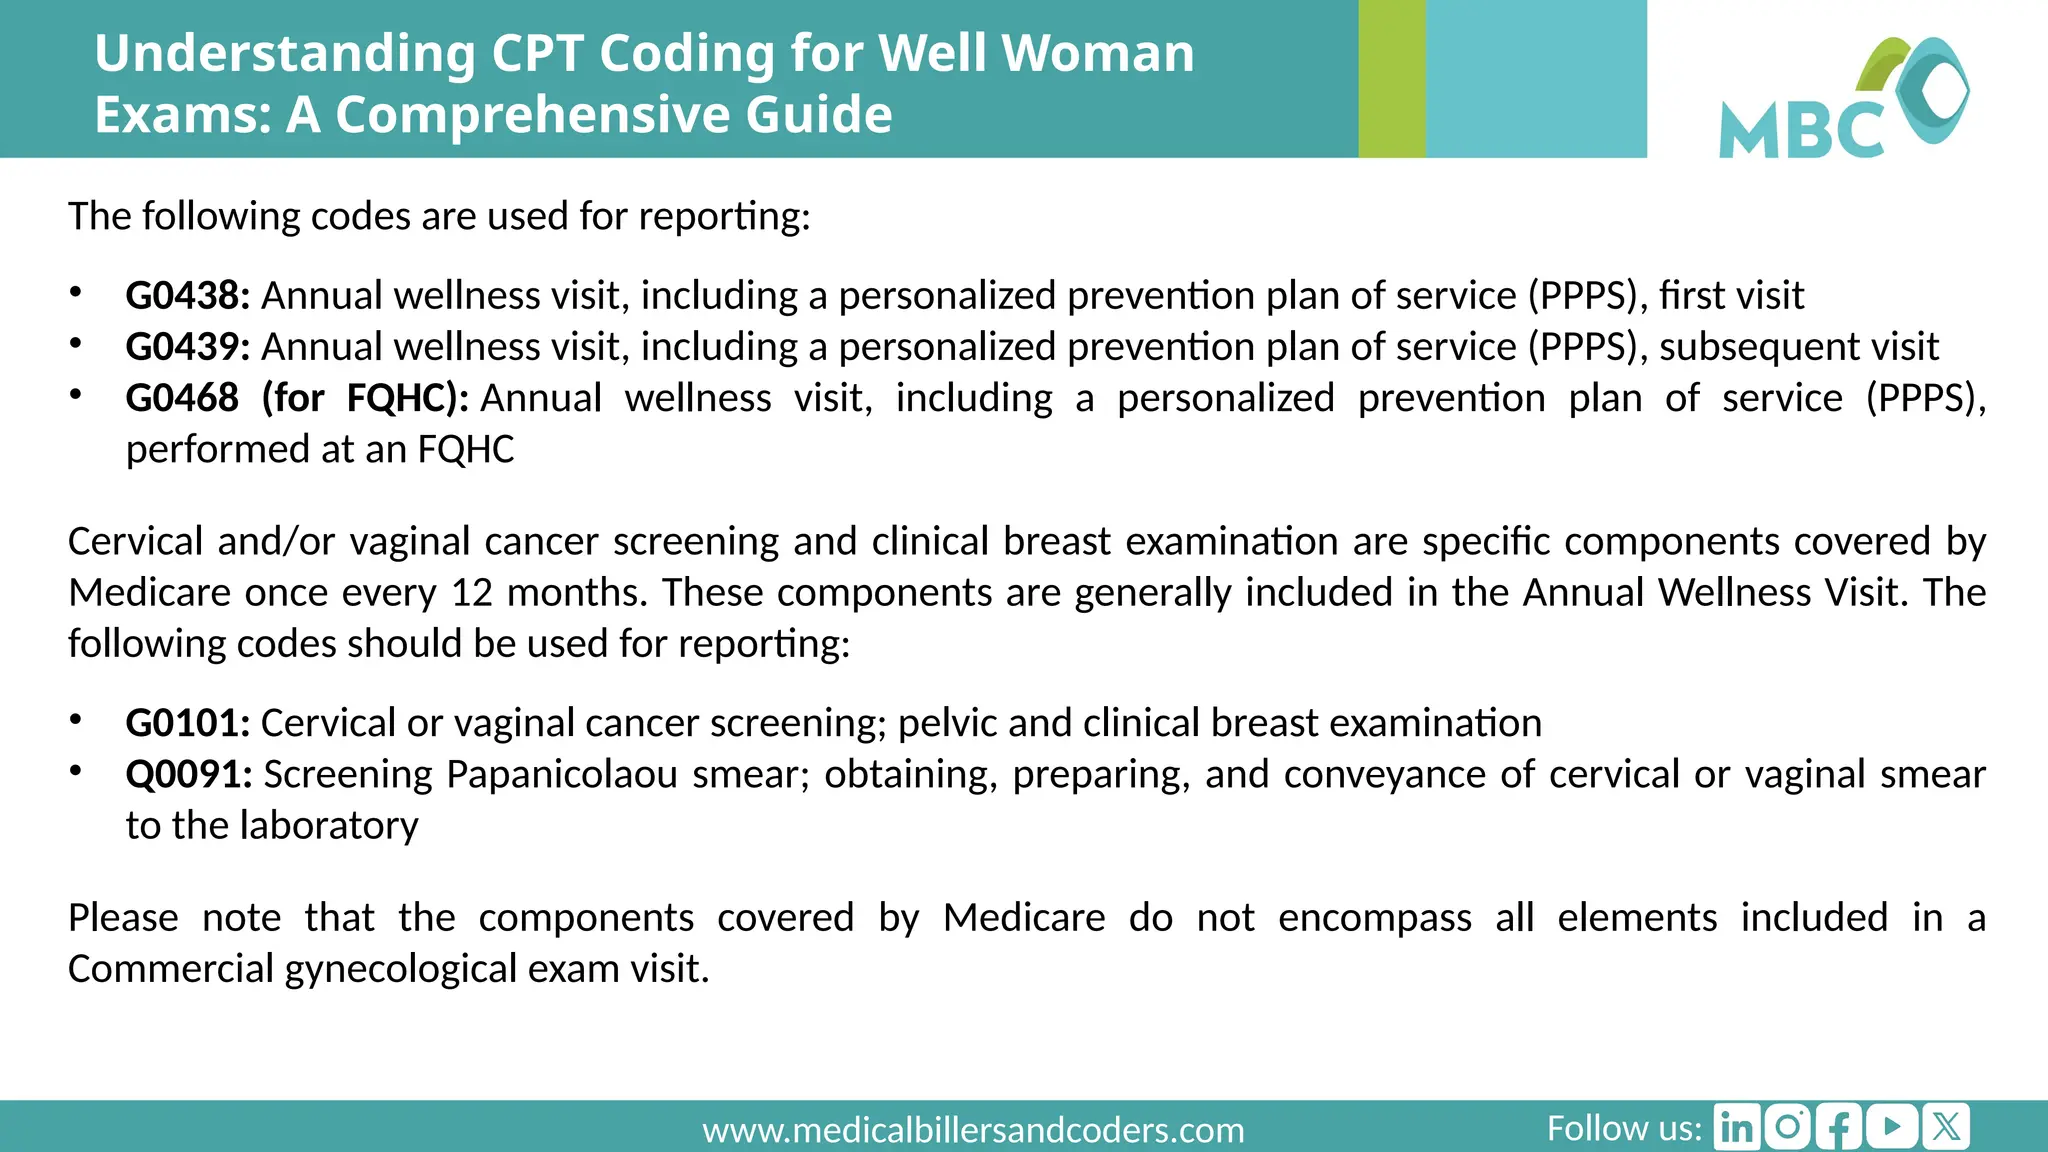
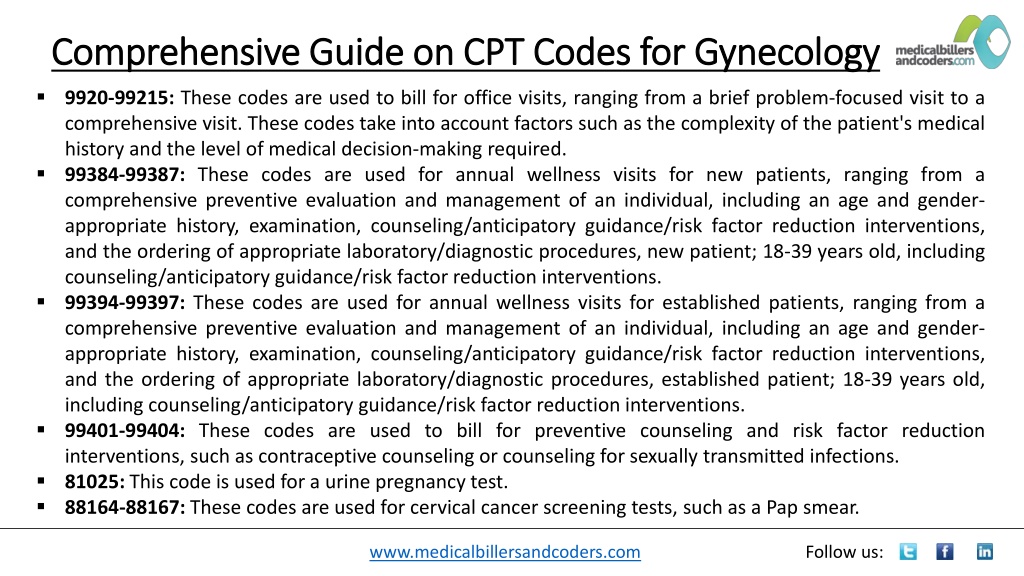
There is no single CPT code called "gynecological exam." That is the first thing to understand. What you are really looking at is a combination of codes depending on the type of visit. The main paths are: Preventive medicine codes (99381-99397 for new patients, 99201-99215 are evaluation and management codes used when the visit is problem-focused). The gynecological component of a preventive visit is handled within the E/M code you select based on medical decision making or time. Gynecological diagnostic codes — if the patient is there for a specific issue like abnormal bleeding, pelvic pain, or post-menopausal spotting, you use the standard E/M codes (99202-99215 for new patients, 99212-99215 for established). The pelvic exam becomes part of the medical decision making, not a separate billable procedure unless you are doing something additional like an endometrial biopsy.
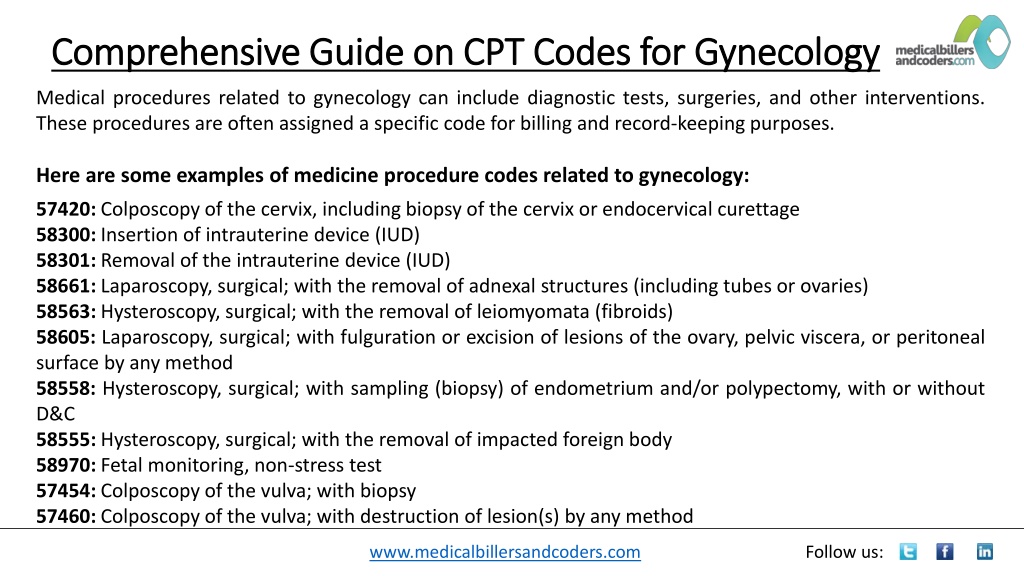
Procedure codes if you perform something beyond the exam. A Pap smear is 88108 or 88150 depending on the method. A colposcopy is 57452-57461. An endometrial biopsy is 58120. These stack on top of the E/M code with a modifier -25 when appropriate. I remember one claim from about three years ago where a provider did a comprehensive gynecological exam, ordered a Pap smear, and also performed a LEEP procedure all in one visit. The billing staff put 99214 with code 58154 and completely forgot the -25 modifier on the E/M. The payer rejected it outright. Added the modifier, resubmitted, got paid within two weeks. That is the kind of thing that eats into your revenue cycle if you are not tracking it.
Get the Full Details

How to Determine Which Code to Use
The decision tree is simpler than people make it. Start by asking whether the visit is preventive or diagnostic. If the patient is coming in for her annual well-woman visit with no active complaints, you are looking at preventive medicine codes or the Z-code pathway with G0402/G0438-99214 depending on Medicare versus commercial payer rules. If she is there because of a symptom or abnormal finding, you go E/M with the appropriate level based on documentation requirements. The documentation itself is where most of the problems show up. For a preventive visit at the higher levels, you need to document a thorough or comprehensive history, a comprehensive examination, and moderate to high complexity medical decision making or the appropriate time threshold. I have seen providers write "pelvic exam normal" and think that satisfies the comprehensive exam requirement. It does not. You need to document each organ system or body area examined. For a gynecological preventive exam that means at minimum documenting breast, abdomen, and pelvic findings with specific observations, not just a single word. For diagnostic E/M visits, the same documentation rules apply but the context shifts. A 99214 requires a detailed history, detailed exam, or moderate complexity MDM. The pelvic exam counts toward the exam component, but again, specificity matters. If you are billing a 99214 and the only pelvic exam note says "speculum exam performed, no lesions noted," that is going to look thin under audit review. Document the visual inspection findings, any discharge noted, cervical appearance, uterine size and position, adnexal findings. Even brief specific findings are better than a generic statement.
Here is a counter-intuitive point that most people miss: the grade of the gynecological exam does not automatically determine the E/M level. A thorough pelvic exam can accompany a straightforward MDM if the visit is short and the problem is minor. Conversely, a limited bimanual exam can sit under a 99214 if the medical decision making is complex due to abnormal lab results, medication changes, or coordination with specialists. The E/M level is driven by MDM or time, not by how extensive the physical exam happens to be. I have watched coders downgrade a legitimate 99214 to a 99213 simply because the pelvic exam was quick, and that is just incorrect under current guidelines.
Modifiers and Bundling Issues
Modifiers are where the coding gets tricky with gynecological visits. The -25 modifier on an E/M code signals a separately identifiable service on the same day as a procedure. If a patient comes in for a well-woman exam and you decide to also perform an endometrial biopsy because of abnormal bleeding you discovered, you would bill the preventive E/M with modifier -25 plus 58120. Without the -25, the payer will bundle the E/M into the procedure and deny it. This is one of the most common denial reasons in gynecology practice. Another modifier worth knowing is -59 when you are performing two distinct procedural services on the same day that are not typically billed together. For example, if you do a colposcopy (57452) and also a cervical biopsy (57450), some payers require -59 on the biopsy to indicate it was a separate anatomical site or distinct procedural approach. Not all payers recognize -59 for this scenario though. Some want you to use -XS (distinct procedural service) or have their own specific pairing rules. You need to check your payer policies individually rather than assuming one modifier works everywhere. Bundling is also an issue with vaccine administration. If you give a HPV vaccine during a gynecological visit, that is 90656 or 90662 with modifier 9920x or 9921x and you can typically bill both. But some commercial payers have bundling rules that require the -25 on the E/M if the vaccine was administered as part of a preventive visit. Again, payer-specific. The general rule for Medicare is that preventive visits include routine immunizations without a separate E/M, but if you address a separate problem during the same visit, the -25 applies.
Workarounds From Actual Practice
One specific problem I dealt with involved a patient who had a screening pelvic ultrasound ordered as part of her annual exam. The ultrasound was normal. The provider billed 76856 with the preventive E/M code. The payer denied the E/m saying it was not separately identifiable from the ultrasound. The fix was to document a distinct problem in the medical decision making — in this case, the provider had also evaluated chronic lower abdominal pain that was unrelated to the ultrasound indication. Adding that symptom to the MDM and attaching the -25 resolved the denial. The ultrasound and the E/M were on different clinical tracks, and the documentation needed to reflect that clearly. Another common workaround involves Medicare Part B well-woman visits. Under current rules, the annual preventive visit includes a pelvic exam, clinical breast exam, and counseling, billed with G0402 for the initial visit and G0438 for subsequent visits. You cannot separately bill an E/M code on top of this unless there is a significant separately identifiable service with the -25 modifier. I have seen practices accidentally bill 99213 alongside G0402 and get denied every time. The workaround is to build any problem-focused work into the preventive visit documentation rather than trying to layer on a separate E/M, unless the problem is genuinely distinct and warrants its own service. Some limitations to be aware of: the preventive visit codes do not cover the cost of the Pap smear or HPV co-testing. Those are billed separately with 88108/88150 and 88150 respectively, and they have specific coverage rules under the ACA that vary by payer. Also, telehealth gynecological exams are still very limited. You cannot remotely perform a pelvic exam, so telehealth encounters for gynecological concerns generally fall under problem-focused E/M codes with the appropriate telehealth modifiers (95 or GT depending on the payer), but they will be lower level because the exam component is restricted to patient-reported findings and visual inspection through the camera.
If you are setting up a new gynecology practice, the single most practical step is to create a documentation template that forces the specific findings I mentioned above. Generic templates that just have checkboxes for "breast normal" and "pelvis normal" will produce claims that look weak under any scrutiny. Include fields for cervical appearance, vaginal mucosa, uterine size and mobility, adnexal masses or tenderness, and any discharge characteristics. When the template forces specificity, the coding follows naturally and the audit defense writes itself.