Writing Cpt Code For Hormone Replacement Therapy Claims: What Actually Works
The Cpt Code For Hormone Replacement Therapy Coding Landscape
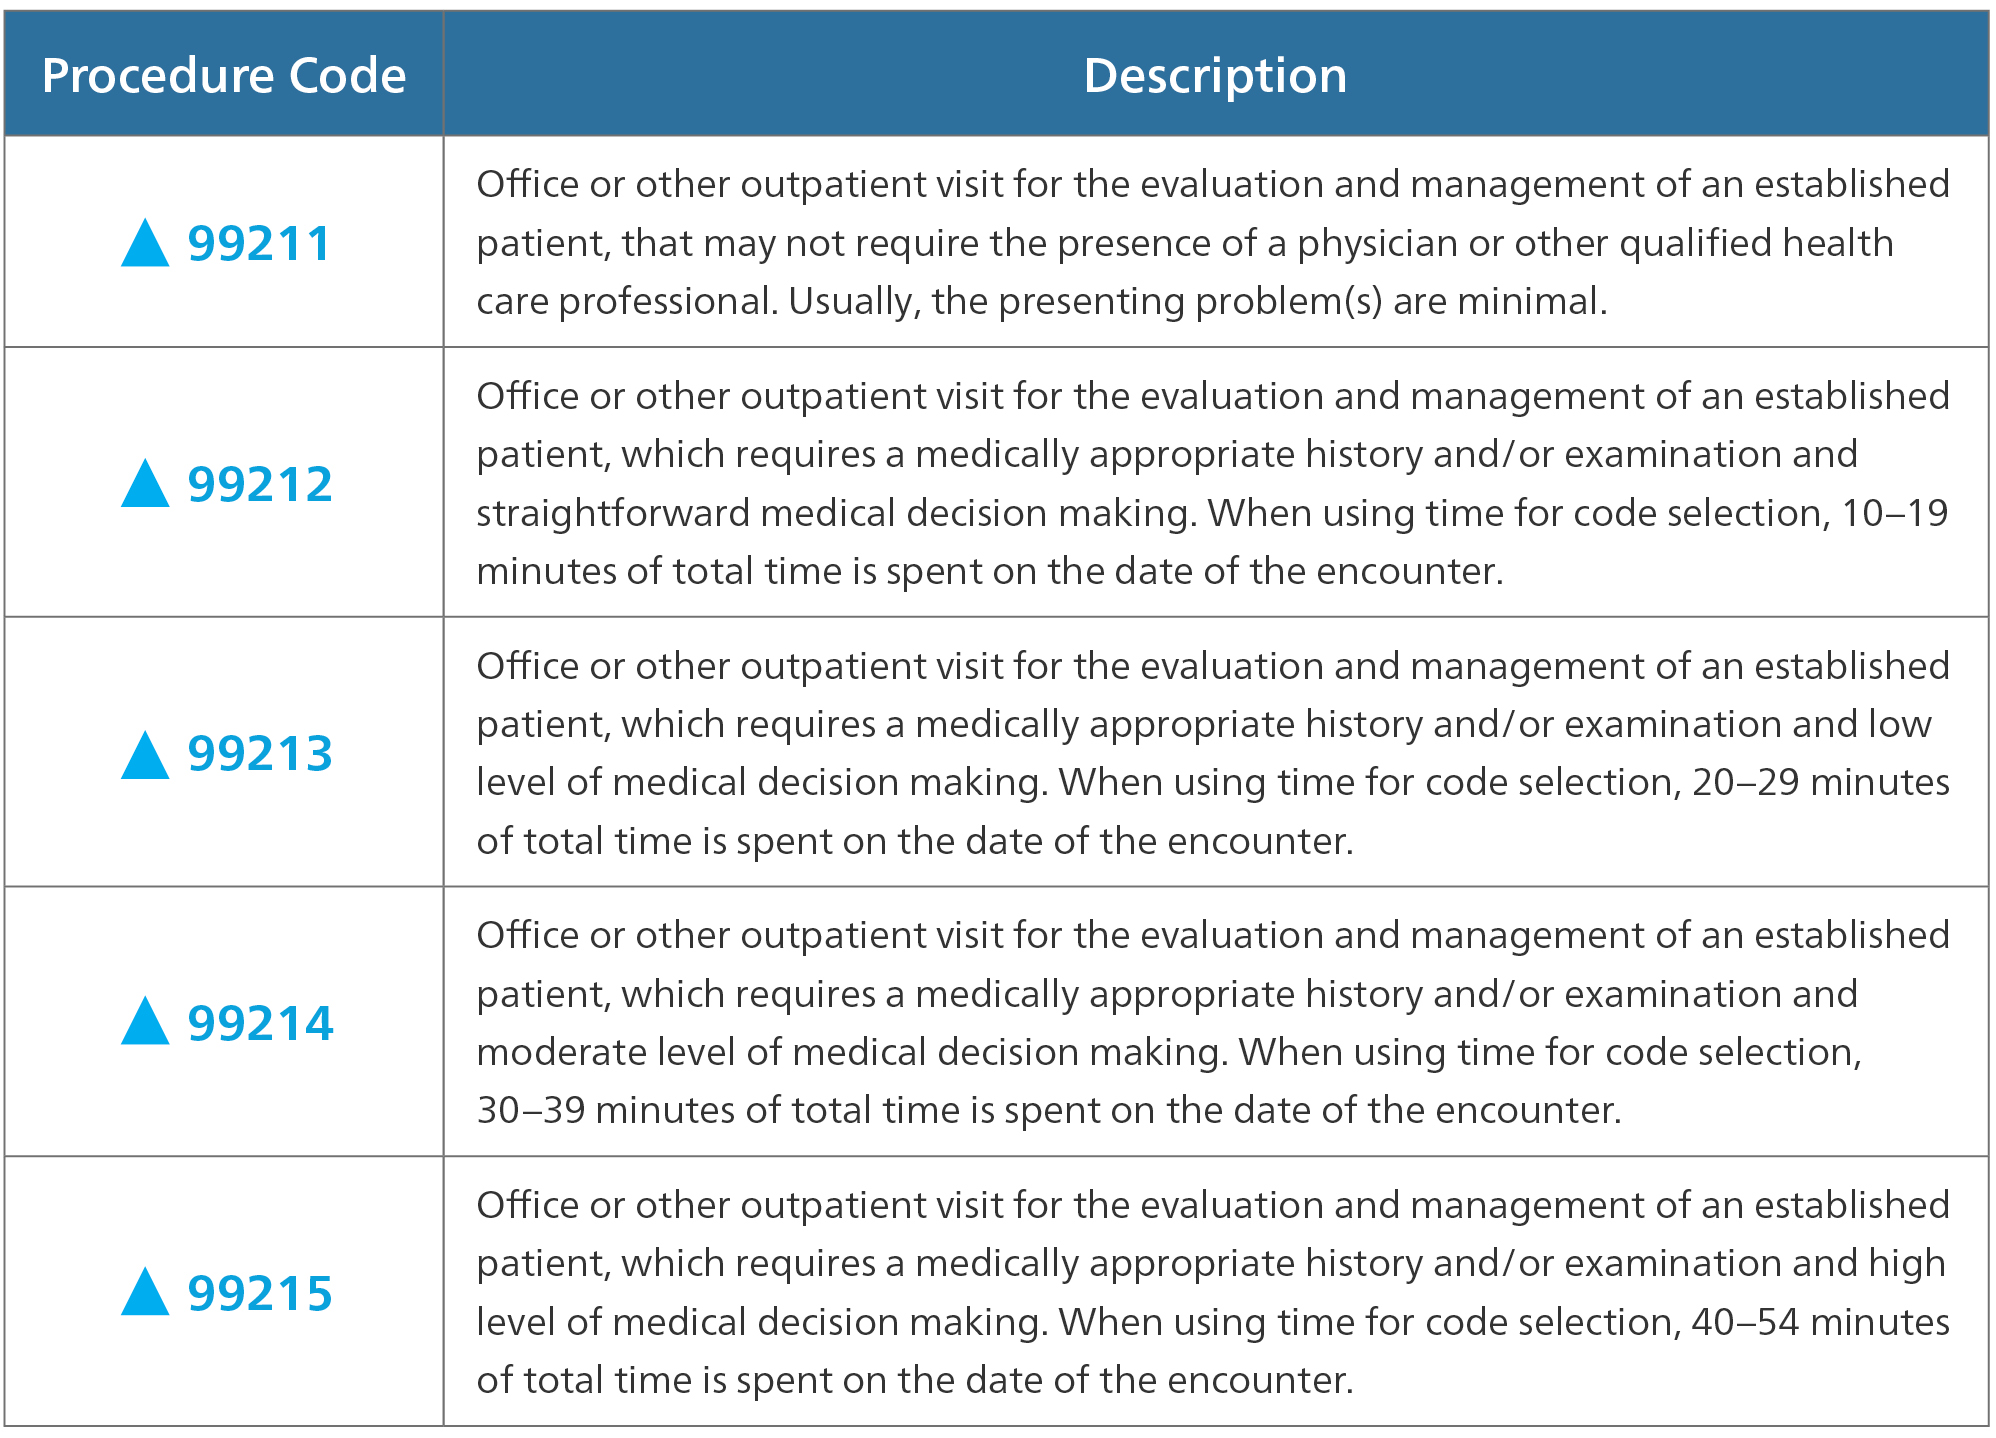
Most people ask for a single CPT code for HRT. That is the first problem. Hormone replacement therapy spans multiple encounter types, different services, and several diagnosis-dependent modifiers. There is no one-size code. The codes you pick depend on what the patient actually received during the visit. The core CPT codes you will encounter for HRT services are 92004 and 92005 for initial or subsequent physician evaluations, 97802 through 97803 for medical nutrition therapy when diet counseling is part of the plan, and 96372 for therapeutic injection administration if you are delivering a medication like a progestin injection in the office. Lab work such as estradiol, testosterone, LH, FSH, and thyroid panels run under the CPT lab series, typically 84712 for estradiol and 84401 for testosterone. These are the ones I see on claim forms the most. Here is how the process feels in practice. You see a patient presenting with menopausal symptoms. The visit is comprehensive. You document a detailed history, a physical exam focused on endocrine findings, and medical decision-making that involves interpreting baseline labs, discussing risk-benefit of systemic estrogen versus topical options, and coordinating with the patient's cardiology team because of their personal history of thromboembolism. You bill 92004. That code captures the evaluation and management work. Then you add the lab codes separately. They go on the same claim line as a companion code, not bundled. You also append modifier 25 if the E/M service was significant and separately identifiable from any minor procedure performed that same day. Claim denials pile up fast when you forget that modifier.
I had a case last year where a clinic billed 92005 without documentation supporting a subsequent visit criteria. The payer reversed it and requested the full chart. The record showed they had seen the patient only three weeks prior for an acute issue unrelated to HRT, so the payer classified it as an initial encounter, not subsequent. Reclassifying to 92004 changed the reimbursement by nearly forty percent on that claim. The lesson is that subsequent versus initial matters more than most coders realize, and the difference between the two codes is not just time. It is the relationship continuity and prior management documentation.
What Beginners Miss About HRT Coding
Beginners treat HRT coding as if it is purely about the medication. It is not. The coding is about the service, the documentation, and the diagnosis linkage. If you are prescribing transdermal estradiol and the patient returns for a follow-up with a lab draw, you still need a valid E/M code or a separate procedure code for the lab draw itself. Insurance payers want to see that the evaluation drove the prescription change. Without that link, the claim looks like a refill-only visit, and many plans deny those entirely under their chronic disease management exclusions. Another nuance is the interaction between ICD-10 codes and CPT selection. Menopausal hormone therapy claims require a valid diagnosis code to justify medical necessity. Z79.3 is the hormone replacement therapy status code, but that alone does not pay. You need to pair it with symptoms like R48.2 for dyspareunia, N95.1 for postmenopausal bleeding, or E03.9 for hypothyroidism if thyroid replacement is part of the regimen. I have seen entire HRT services denied because the provider submitted only Z79.3 without a symptomatic diagnosis. The payer sees a maintenance code and assumes no active treatment. There is also a common misconception about 97802 and 97803. Those are medical nutrition therapy codes, not HRT-specific codes. They apply when a registered dietitian or qualified provider delivers nutrition intervention as part of the hormonal management plan, and they require separate qualifying documentation. Mixing them into an HRT claim without distinct time-based notes will trigger an audit flag. I once worked through a scenario where a practice tried to bundle nutrition counseling into an HRT visit to boost reimbursement. The auditor caught it because the time logs did not match the billing pattern. The practice ended up with a repayment demand and a compliance review.
Get the Full Details

The Practical Workflow I Use
When I code an HRT claim now, I follow a strict sequence. First, I confirm the encounter type: initial, subsequent, or follow-up. Second, I verify the diagnosis codes align with the service. Third, I check whether any procedures occurred alongside the evaluation, because that triggers modifier work. Fourth, I document the medical decision-making at a level that supports the chosen E/M code. Fifth, I submit the claim with all companion codes clearly separated on distinct lines. This workflow takes about twelve minutes per claim when the chart is clean. It takes longer when the EHR has poor documentation structure. If you are setting this up for a new practice, start with a small claim set. Run ten HRT-related submissions through your clearinghouse and track the rejection reasons. You will learn more from those rejections than from reading any coding manual. The typical rejection reasons I see are modifier misuse, insufficient diagnosis linkage, and unbundled service reporting. Fix those three and your clean claim rate jumps to somewhere between ninety-three and ninety-six percent.
Limitations and When This Approach Fails
This coding strategy assumes you have access to standard CPT and ICD-10 databases and that your payer participates in Medicare or standard commercial networks. It does not work well for cash-pay concierge models where coding conventions are relaxed. In those cases, the administrative overhead of strict coding often exceeds the reimbursement benefit. If your practice is primarily cash-based, you may find it simpler to use a flat-visit fee structure instead of piecing together CPT codes for every service. Another limitation is the variability among payers. Some commercial plans require pre-authorization for certain hormone therapies, particularly biologics or compounded formulations. Compounded HRT products do not have their own CPT codes. You must use an unlisted code or a generic drug administration code, and many payers reject those outright without prior authorization documentation. I have lost claims on compounded estradiol prescriptions because the coder assumed the unlisted code would suffice. It did not. The payer asked for a written medical necessity letter and a formulary exception request. By the time I gathered those, the appeal window had closed. Lab codes are another area where expectations diverge from reality. Some payers bundle certain hormone panels under a global package or require specific lab-to-procedure linkage. If you order a full reproductive hormone panel and the payer considers it an umbrella service, you might only be reimbursed for one primary lab code rather than each individual test. Check your payer's bundling rules before you start submitting. It saves you from chasing adjustments months later.
Resources and Tools
For anyone needing reference material, the AMA CPT Professional Edition remains the standard source, though it requires a subscription. Free alternatives include the CMS Medicare Benefits Policy Manual, which outlines coverage rules for hormonal therapy services, and the ICD-10-CM Index for diagnosis coding guidance. Commercial coding software like 3M CodeFinder or Optum EncoderPro will flag modifier issues and bundling conflicts in real time. Those tools reduce the manual review time significantly, though they are not infallible. I still cross-check anything that involves a new or changed code annually. There is no downloadable file that contains a complete, ready-to-use CPT code for hormone replacement therapy because the code depends on the specific service rendered. What you can download are payer-specific policy documents from Medicare Administrative Contractors and state Medicaid portals. Those documents list covered services, required modifiers, and authorization protocols. I keep a folder of current MAC policies for the regions my patients typically receive care from. Updating those quarterly prevents the most common surprise denials.