Understanding the CPT Coding Landscape for Suprascapular Nerve Release
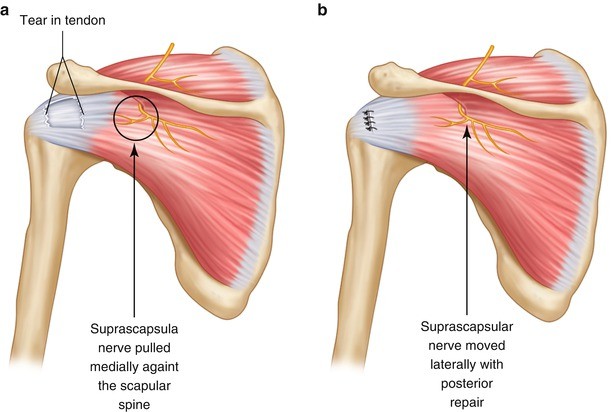
The suprascapular nerve release falls under a handful of CPT codes, and the right one depends entirely on the surgical approach, the anatomic site, and what else you do during the same operation. Most coders and surgeons default to 64408 or 23400 without thinking through the nuances, which is why denials happen. Let me walk through what each code actually covers and where people get tripped up. 64408 - Injection or infusion, anesthetic agent (including corticosteroid), supra-scapular nerve; diagnostic or therapeutic. This is really a nerve block code, not a release code per se, but it's frequently used alongside the surgical procedure for post-op pain management and often gets overlooked when bundling considerations come into play. 64410 - Neuroplasty and/or relocation of suprascapular nerve. This is the open surgical decompression code most surgeons reach for when doing a traditional open release at the suprascapular notch or spinoglenoid notch. It covers neurolysis of the nerve itself.
23400 - Arthroscopic supraspinatus tenodesis; biceps tendon, extra-capsular. Wait, that doesn't sound right for a nerve release. Actually, looking closer, 23400 is arthroscopic release of coracoacromial ligament. That's a completely different procedure. The relevant arthroscopic code for suprascapular nerve release is 23420 - Arthroscopic, shoulder, decompression of subacromial space with acromioplasty and coracoacromial ligament release, with or without biceps tendon tenotomy or release. 23430 - Arthroscopic, shoulder, decompression of subacromial space; with resection of distal clavicle. Again, not directly a nerve release. The code specifically describing arthroscopic suprascapular nerve release at the spinoglenoid notch is 23440 - Arthroscopic, shoulder, decompression of spinoglenoid notch. So the main players are 64410 for open neuroplasty and 23440 for arthroscopic spinoglenoid notch decompression. If you're doing an open release at the suprascapular notch specifically, 64410 is your anchor code.
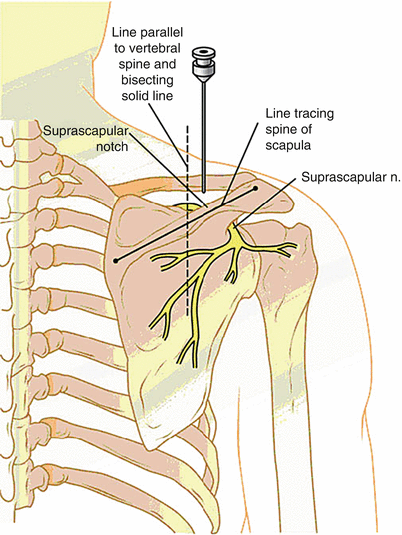
There's also a nuanced discussion around 64505 - Injection, anesthetic agent, supra-scapular nerve block, diagnostic or therapeutic. Some surgeons perform this intra-operatively before the release. It's separately billable in many cases but pokers around NCCI edits will test this depending on your payer.
Get the Full Details
How This Actually Plays Out in the OR and on the Claim
Here's the thing nobody tells you: the anatomic site determines the code more than the approach. A suprascapular nerve release at the suprascapular notch uses 64410 regardless of whether it's open or endoscopic-assisted. A release at the spinoglenoid notch, especially if done arthroscopically, points toward 23440. But if you do an open spinoglenoid release, you still go with 64410 because that code doesn't specify the approach—it specifies the nerve and the procedure type (neuroplasty). I ran into a case last year where a surgeon was doing a combined suprascapular and axillary nerve release for brachial plexus traction injury. The coder billed two separate 64410s with a modifier 50. That claim got denied because 64410 is a unilateral code and the bilateral modifier 50 is appropriate, but the real issue was that the axillary nerve release falls under a different code range entirely (64412 for axillary nerve). So the correct billing was 64410 with modifier 50 and 64412 for the axillary portion. The denial wasn't about laterality—it was about using the wrong code for the axillary nerve neuroplasty. Took three appeals to get it sorted and we ended up providing operative notes documenting both nerve releases explicitly. Another practical point: if you're releasing the superior transverse scapular ligament to decompress the nerve at the suprascapular notch, some payers consider this part of the neuroplasty already described in 64410 and won't allow an additional code for ligament release. Others want to see it documented separately. Check your local coverage determination.
Modifiers and Bundling Pitfalls
Bilateral procedures: use modifier 50. straightforward enough, but make sure both sides were operated on during the same operative session. If they're staged procedures on different days, modifier 50 doesn't apply—you'd bill each side separately on its respective date of service. Modifier 51 (multiple procedures) comes into play if you're doing the nerve release alongside another procedure on the same side. The primary procedure gets billed without a modifier; subsequent procedures get 51 appended. The reimbursement reduction for the secondary procedure is typically around 50% depending on the payer's MPFS calculation. NCCI edits are your biggest enemy here. The Neurosurgery and Orthopedics edit tables will show which codes bundle into which. 64410 appears in multiple bundling relationships. For example, some E/M codes on the same day may be bundled unless you have a significant, separately identifiable E/M service (modifier 25). Document that E/M clearly—just writing "post-operative visit" isn't going to cut it.
If you're also performing a tendon repair or release during the same session, that changes the coding entirely. A concurrent rotator cuff repair would push you toward combination coding and potentially make 23440 the more appropriate choice if the arthroscopic approach covers both the decompression and the cuff work.
Documentation Requirements That Actually Matter
The operative report needs to explicitly state which nerve is being addressed and at which anatomic landmark. "Suprascapular nerve release" is not sufficient documentation for many auditors. You need the specific notch identified—the suprascapular notch or the spinoglenoid notch—because that distinction determines the correct code in borderline cases. Document the specific structure being released. Is it the superior transverse scapular ligament? The inferior transverse scapular ligament? Is there neurolysis of the nerve itself, or is it purely decompression of the passage? These details separate a clean claim from a request for additional information. Laterality must be documented. I've seen claims rejected simply because the operative note said "left shoulder procedure" without explicitly documenting left-sided laterality in the impression or the procedure section. It sounds minor but it happens constantly.
What Doesn't Work Well
Unbundle 64410 with 23440 on the same claim for the same side on the same day. Both describe decompression of the suprascapular nerve and most payers will consider them duplicative. Pick the code that best matches your approach and document it thoroughly. If you need to clarify why two codes might be justified, that's a modifier 59 situation, but get ready to fight for it with supporting documentation. Don't assume arthroscopic always means 23440. If your arthroscopic release is primarily addressing the suprascapular notch and you're doing significant open work as well, 64410 may be the better description. The approach matters less than the anatomic target and the nature of the procedure. For diagnostic nerve blocks (64505) performed on the same day as the surgical release, most payers will deny the block as component of the global period or as bundled into the surgical package. Some surgeons still bill it to capture the diagnostic value, but be prepared for prior authorization or appeal requirements. The global period for 64410 is 90 days, which is unusually long for a nerve procedure and will swallow up related E/M visits.
Quick Reference Summary
Open suprascapular nerve release at the suprascapular notch: 64410 Arthroscopic suprascapular nerve release at the spinoglenoid notch: 23440 Open suprascapular nerve release at the spinoglenoid notch: 64410

Diagnostic/therapeutic nerve block: 64505 (often bundled) Bilateral procedures: add modifier 50 Separate distinct procedure on the same day: modifier 59 may apply but expect pushback
Document the notch, the structure released, the nerve targeted, and the laterality explicitly. That will save you more headaches than any coding guideline you read online.