
Well Child Visit Coding: What Actually Happens
Picking the right CPT code for a well child exam is one of those things that sounds simple until your first denial hits. The codes themselves are straightforward — 99201 through 99205 for new patients, 99211 through 99215 for established patients — but the nuances around preventive visit coding, age considerations, and E/M documentation requirements will trip people up every time. I spent three years in a pediatric practice before moving to consulting. The claims denials I saw in that time fell into two buckets: wrong prevention visit coding and insufficient documentation for higher-level E/M. The good news is both are fixable. The bad news is the fix requires actual knowledge, not guessing.
Cpt Code For Well Child Exam
The CPT codes you'll use for well child exams depend on whether the patient is new or established, and whether you're billing a preventive visit under Medicare/Medicaid versus a standard E/M encounter. For privately insured children, the 99201-99205 or 99211-99215 codes are your starting point. Here is the breakdown by patient type: New patient well visit: 99201 (minimum), 99202, 99203, 99204, or 99205 (extensive). These require three key components: history, examination, and medical decision-making. Most standard well visits for new patients land at 99202 or 99203.
Established patient well visit: 99211 through 99215. These follow the same three-component structure. A routine checkup for a known patient typically lands at 99212 or 99213. The difference between the levels comes down to complexity. A 99212 requires a problem-focused history, an expanded problem-focused exam, and straightforward medical decision-making. A 99213 bumps those to detailed history, comprehensive exam, and low-to-moderate MDM. Most preventive visits fall into these two categories for established patients.
Get the Full Details

Preventive Visit vs. E/M: The Denial Trap
This is where I see the most money walk out the door. Preventive visit coding uses G-codes and CPT codes that differ from standard E/M encounters. For Medicare, preventive visits use G0438 and G0439. For Medicaid, it varies by state. For commercial payers, many follow their own rules. The problem arises when you have a well-child visit AND the child presents with an acute issue during the same encounter. If you code only the preventive visit, you are leaving money on the table. If you try to bill an E/M on top without proper modifier usage, you will get denied. The workaround is to use modifier 25 on the E/M code when the two are distinct, separate, and documented separately. Modifier 25 means you performed a significant, separately identifiable E/M service on the same day as another procedure or preventive visit. The documentation has to prove it. I had a case once where a 4-year-old came in for his annual physical and also needed treatment for an ear infection. The provider did both. The coder bundled it as a single preventive visit. The parent's insurance denied it. I pulled the clinical notes, identified that the HPI section clearly separated the ear complaint from the preventive history, confirmed the physician's assessment documented otitis media with distinct treatment plan, and resubmitted with modifier 25 on the E/M code. The claim went through. Two hours of work that a properly trained coder should have caught in the first pass.
Age Matters More Than You Think
New patient well visit codes behave differently based on the child's age. A newborn visit (0-28 days) at 99202 might seem identical to a 3-year-old's visit at the same level, but the content is fundamentally different. Newborn assessments include umbilical cord examination, hip screening, hearing results review, metabolic screening follow-up, and detailed parental counseling about feeding and sleep. These activities take time and they justify the code level. A teenager's well visit at 99214 involves adolescent-specific screening: mental health assessment, substance use screening, sexual health counseling, and sports physical evaluation. This extensive counseling and comprehensive examination can support a higher-level code than the same visit would at age 5. Pay attention to what the documentation actually reflects. If a 16-year-old preventive visit includes 20 minutes of mental health screening and the chart only shows "denies depression," that is not sufficient documentation for 99214. The documentation needs to show the depth of the assessment, not just the conclusion.
Time-Based Coding: When It Works and When It Fails
Some payers allow time-based coding for pediatric preventive visits. If the total office or other outpatient evaluation and management time on the date of the encounter meets or exceeds the threshold for a given level, you can use time instead of the traditional three-component method. For 99213, the threshold is 25-39 minutes. For 99214, it is 40-54 minutes. The catch is that time must include face-to-face time with the patient or family, plus time spent on the date of the encounter reviewing records, ordering labs, and counseling. But some payers only count direct patient contact time. The rules vary enough that you need to check your specific payer's policy before relying on this method. I stopped using time-based coding for pediatric well visits about four years ago. Not because it does not work, but because the administrative overhead of tracking and documenting time accurately across a busy clinic schedule usually consumes more time than the actual coding saves. For solo practitioners who can document everything meticulously, it is viable. For a high-volume practice with 18 well visits per day, it is not practical.

Common Pitfalls That Will Cost You
Using a 99213 code when the documentation only supports 99212. This is the most common upcoding issue I see. The provider writes a brief note during the visit and tries to bill for a more comprehensive encounter than what was documented. Auditors can and will challenge this. Failing to document the preventive nature of the visit. For Medicare and many commercial plans, preventive visit coding requires documentation that the encounter is preventive, not problem-focused. The plan of care section should reflect routine surveillance and anticipatory guidance, not treatment of active conditions. Missing the developmental screening requirement. Many well child visits require standardized developmental screening tools, and certain ages mandate specific screenings like autism screening at 18 and 24 months. If the documentation does not reference the tool used or the results, payers sometimes request additional information before processing payment.
Not using the right preventive visit code for the payer. Medicare uses different codes than Medicaid, and Medicaid uses different codes than commercial payers. Some commercial plans do not recognize the preventive visit codes at all and default to standard E/M. Your billing software should flag payer-specific code sets, but it will not catch everything. Manual verification is still necessary.
A Practical Workflow That Actually Works
Start with the patient's insurance type and verify the code set for that payer before the visit begins. Run the demographic verification in your practice management system. If the answer is unclear, call the payer directly rather than guessing. A five-minute call saves a weeks-long appeal process. Document the visit thoroughly in the electronic health record using the appropriate template. Make sure the history, examination, and medical decision-making sections reflect the actual work performed. Do not copy and paste previous well visit notes and modify them minimally. Auditors flag this immediately. Select the code based on documentation, not on what you think the visit "should" be worth. Then review the claim before submission. Check that the diagnosis codes support the level of service. For well visits, use the appropriate Z-code such as Z00.129 for a routine child health examination without abnormal findings, or Z00.121 for a newborn well check.
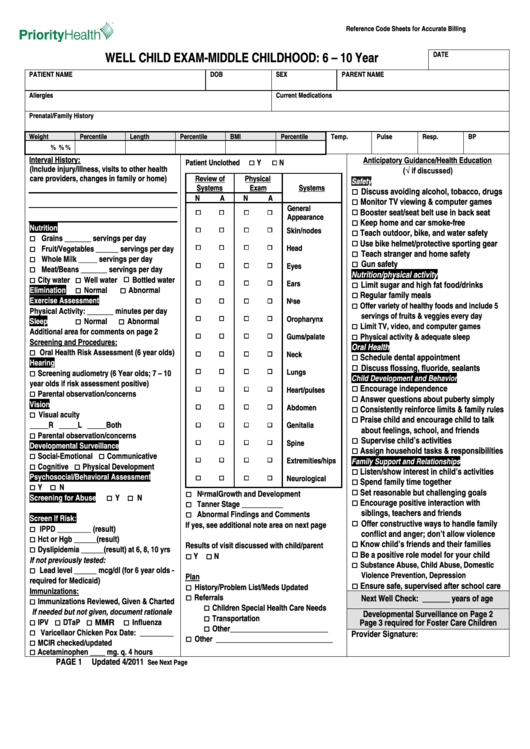
If the visit included a problem beyond the preventive component, document that separately, use modifier 25 if applicable, and ensure the diagnosis codes reflect both the preventive and problem-focused aspects of the encounter.
What I Would Tell Myself Starting Out
The most important thing I learned is that coding accuracy is not about knowing every code by heart. It is about understanding the clinical encounter well enough to map it correctly to the code set. Read the documentation the provider wrote. If it does not support the code you are about to bill, find out why before submitting. The denial will arrive eventually anyway, and then you will spend more time on the appeal than you would have on the initial check. Well child visit coding is not difficult. It is tedious, it is detail-oriented, and it requires constant attention to payer-specific rules. Treat it like the systematic process it is rather than a task to rush through. The claims will pay faster, the denials will drop, and your practice will stop bleeding revenue on preventable errors.


