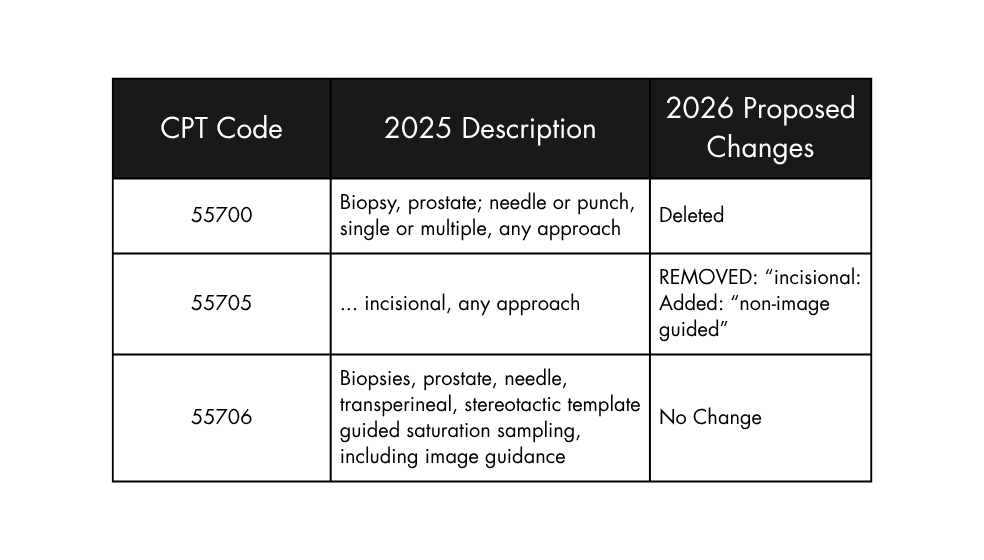
Understanding CPT Codes for Guided Biopsy Procedures
The way CPT codes work for guided biopsies keeps changing, and most people I talk to still get tripped up by the imaging guidance component. When I started in this space around 2008, we were still wrestling with whether the guidance was bundled or separately billable across different imaging modalities. The answer depends on which code you are looking at and what type of biopsy you performed. Let me walk through how this actually plays out in practice. For soft tissue biopsies, you are probably looking at 20203 for a closed needle biopsy, or 20204 if it is an open procedure. Bone biopsies sit at 20220 through 20226 depending on whether you are dealing with vertebral body or non-vertebral sites. Breast biopsies have their own section starting around 19100. The imaging guidance codes are where things get messy. Ultrasound guidance alone is 76942. CT guidance jumps to 77012. Fluoroscopy guidance is 77002. MRI guidance is 73721. I keep running into the same question from billing teams: do you bill the guidance code in addition to the biopsy code, or is it bundled? The answer is it depends on the specific CPT code. Some biopsy codes already include imaging guidance. Others do not. You have to look at each code individually rather than assuming a pattern across all procedures.
Here is what I learned the hard way. I was auditing a clinic that performed breast core needle biopsies with ultrasound guidance. They were billing 19100 plus 76942 on every case. That worked fine for diagnostic biopsies. Then a pathologist called because they had coded a stereotactic breast biopsy using 19101. I checked the code descriptor and found that 19101 already includes imaging guidance as part of the procedure description. Billing 76942 separately on top of that was an overpayment. I had to go back and correct about forty claims from the previous quarter. That cost us more time than I want to admit.
How Imaging Guidance Actually Gets Billed
The tricky part is that some CPT codes bundle imaging guidance while others treat it as a separate component. Let me break down what I see most commonly in the field. For percutaneous needle biopsies of soft tissue using 20203 or 20204, the imaging guidance is separately reportable. So you would code the biopsy plus the appropriate guidance code. For example, 20203 with 76942 for ultrasound guidance, or 20203 with 77012 for CT guidance. The same logic applies to bone biopsies with 20220 through 20226. You add the guidance code on top. Breast procedures are different. Code 19100, which is excision of a breast lesion, does not include guidance. You can bill 76942 with it. Code 19101, stereotactic breast biopsy, includes the guidance. You do not add a separate code. Code 19102, intraoperative ultrasound-guided excision, also bundles the guidance into the procedure itself. Trying to extract a separate guidance code here will trigger an audit flag.
Get the Full Details

Vertebral body biopsies are their own category. Code 20205 is a needle biopsy of a vertebral body using imaging guidance. The code descriptor explicitly states that imaging guidance is included. Billing 77002 or 77012 separately on a 20205 claim is incorrect. I have seen this mistake happen repeatedly because the code number does not intuitively signal that guidance is bundled. The descriptor tells you. Read it every time before you submit.
When Guidance Coding Gets Complicated
There are scenarios where the guidance component requires special attention. One situation I encounter often involves multiple imaging modalities during the same procedure. Let me explain how that plays out. Sometimes a physician starts with ultrasound guidance and then switches to CT guidance mid-procedure. You might think you can bill both guidance codes. That is not how the system works. You report only the primary guidance modality used for the procedure. If ultrasound was used for initial localization and CT guided the actual needle placement, you bill the CT guidance code, not both. Document which modality was used for the definitive guidance component and code accordingly. Another edge case involves concurrent fluoroscopy and ultrasound. I worked with an interventional radiology group that performed thyroid nodules biopsies. They routinely used both fluoroscopy and ultrasound during the same procedure. The question was which guidance code to report. The answer is you bill only one. In that particular case, ultrasound was the primary guidance modality, so they reported 76942. The fluoroscopy was incidental and not separately billable. Having a clear documentation habit of noting which modality served as the primary guidance saves you from guesswork later.
There is also the issue of three-dimensional image guidance, which is code 76497. This is used for CT or MRI based navigation systems. It is not the same as standard CT guidance at 77012. Code 76497 requires a navigation system that creates a three-dimensional representation of the anatomy. Most standard CT guided biopsies do not qualify. I see this code get misapplied fairly often when facilities assume any CT based guidance counts as three-dimensional navigation. It does not. The distinction matters for audit purposes.

Common Pitfalls I See Across Practices
Let me share a few patterns that show up repeatedly in my audits. The first pitfall is confusing code descriptors with code numbers. The numbers themselves do not indicate whether guidance is bundled. Only reading the full descriptor will tell you. Take time to verify each code against the current CPT manual rather than relying on memory. The code set changes annually and old habits lead to systematic errors. The second pitfall is billing guidance for diagnostic procedures when the code already includes it. I showed you the breast biopsy example earlier. This same mistake shows up with bone marrow biopsies and excisional procedures. Always cross reference the code descriptor before appending a guidance code.
The third pitfall involves laterality and multiple sites. If you perform biopsies at two separate anatomical sites using the same imaging guidance session, you generally report the guidance code once. Do not double bill just because there are multiple target sites. The guidance is a single procedural component regardless of how many sites you accessed during that session. The fourth pitfall is documentation gaps. Coders cannot bill guidance they cannot verify. If the operative report does not state which imaging modality was used for guidance, you have to query the physician. Guessing leads to incorrect coding. I recommend building a simple checklist into your documentation review process: verify the biopsy code, check if guidance is bundled, identify the guidance modality, confirm documentation supports it, then submit.
What This System Gets Wrong
I should be straightforward about the limitations here. The CPT coding structure for guided biopsies is not clean. The bundling rules vary across code families without an obvious pattern. A coder cannot derive the bundling status by looking at the code number alone. You have to memorize or look up each individual code. That creates a high risk of systematic error, especially for coders who are new to musculoskeletal or breast procedures. The annual code changes make this worse. When the American Medical Association updates descriptors or adds new codes, the bundling relationships can shift. A code that excluded guidance last year might include it this year. Relying on outdated mental models produces consistent mistakes. I keep a personal reference sheet that I update every December after the code changes take effect. It has saved me from repeat errors. Another limitation is the lack of clarity around emerging technologies. Navigation systems, augmented reality guidance, and electromagnetic tracking are becoming more common. The existing CPT codes do not always map cleanly onto these newer techniques. You end up deciding whether a novel guidance method fits under 77012, 76497, or an unlisted code. There is no perfect answer and payer policies differ. I tend to default to the closest existing code and document thoroughly, knowing that some claims may face denial and require appeal. It is not ideal but it is the reality of coding in this space.

A Practical Workflow That Keeps Things Straight
Here is the process I use when I encounter a guided biopsy claim. It is not fancy but it works consistently. Step one is identifying the primary procedure code. Look at what was actually performed. Not what the physician mentioned first in the note, but what the code descriptor matches. Step two is checking the descriptor for bundled guidance language. Words like including imaging guidance or percutaneous means you likely do not add a separate guidance code. Step three is locating the appropriate guidance code if it is separately billable. Step four is verifying documentation support. The operative note must state the modality used. Step five is ensuring the guidance was actually performed for this procedure. Documentation of trial scans or scout images does not count as guidance. The imaging must have been used to direct the needle or instrument to the target site. This workflow takes about two minutes per claim once you are comfortable with it. Doing it manually every time prevents the kind of retrospective audit pain that comes from missing a bundled guidance rule. I have lost count of how many times I caught an error in the final review step that would have resulted in an overpayment if I had submitted it as written.
The billing side of guided biopsy coding is straightforward if you respect the descriptor language. The errors almost always come from assumptions rather than verification. Read the code. Check for bundling language. Confirm documentation. Submit with confidence. That is the routine I follow and it has kept my denial rates low over many years of reviewing these claims.