Reading CPT Codes for Occupational Therapy in Practice
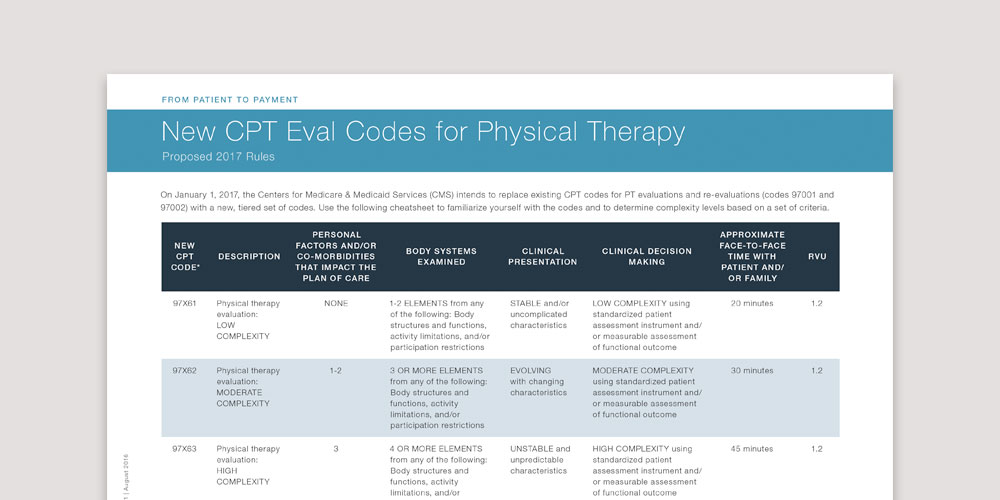
The way therapists use CPT codes day-to-day looks completely different from how they're presented in textbooks. You'll spend most of your time deciding between 97110 for therapeutic exercises and 97530 for therapeutic activities, which sounds straightforward until you actually need to justify one over the other during an audit. The distinction comes down to whether you're working against resistance or through functional movement patterns, and getting this wrong is how claims get denied. Evaluation codes follow a similar pattern—97161 through 97164 break down by complexity, but the notes have to back up whichever level you pick. I've seen therapists get slapped with denials because the assessment documented was more extensive than what the code implied. The re-evaluation codes work the same way, and you need to show that the patient's progress justifies coming back for another look. There's a particular edge case with group therapy that catches people off guard. When you bill 97533 for a group session, the modifier matters—a 6Q is required when a therapist directs the group, not just 53. I ran into this one when a clinic tried billing the code without the modifier and got hit with a retroactive denial that took six months to resolve. The fix was getting every therapist to verify the modifier was attached before submitting, which cut those kinds of denials down to basically nothing over the next few billing cycles.
Modifiers Are Where Things Fall Apart
Modifiers are where things get messy. When multiple body parts are involved, you need 59 or XS to show these are separate encounters rather than bundling them together. But some payers won't accept 59 anymore and want specific anatomical modifiers instead, which means your charge description needs to match what the payer's policy actually requires. NMRT and therapeutic exercise also create confusion since 97124 and 97110 overlap depending on how the therapist documents it. If you're doing nerve glides and proprioceptive work alongside range of motion, that could fall under either code, so the medical record has to make clear which one applies. The same issue shows up with manual therapy—97140 can cover joint mobilization, soft tissue work, and myofascial techniques, but you can't bill it for things like edema management that belong under 97113 instead. For pediatric cases, prosthetic and orthotic training codes like 97761 and 97762 come up frequently, though many therapists don't bill them because they're unsure about the documentation requirements. The key is showing how the device impacts the patient's daily function beyond just learning to wear it.
Documentation Rules That Actually Matter
Documentation has to support every code you submit, particularly for neuromuscular reeducation and manual therapy where specific techniques need to be noted rather than just generic descriptors. I've also noticed that Medicare and commercial payers handle these codes differently, so what works for one payer often gets denied by another. Sometimes you encounter situations that don't fit any existing code, and while 97799 exists as an option, it's essentially a last resort—payers rarely reimburse well for uncoded procedures. A better approach is usually finding the closest code and using a modifier to explain the deviation, though you'll want to check each payer's policy on that first.
Get the Full Details

Where to Find Cpt Codes For Occupational Therapy
The authoritative source is the annual CPT manual from the AMA, and most EHR systems pull from that data directly, so you're typically seeing current codes without needing to look them up separately. The OTPS site puts out updates periodically too, and CMS posts changes on their Medicare portal each year before the January implementation date. What actually matters in practice isn't memorizing codes—it's understanding the documentation requirements for each one and knowing which combinations trigger bundling rules. If you're working through insurance verification or handling claims, having a quick reference guide organized by service type is worth more than anything else, and some clinics have built spreadsheets mapping out common scenarios with the right modifiers and documentation notes for each one. CPT code selection also shifts when insurance changes. Medicare has its own rules around what it covers—for instance, it only reimburses for certain types of neuromuscular reeducation that involve specific body parts. Commercial payers vary widely, with some requiring pre-authorization for extended sessions or limiting the number of therapeutic exercise visits per year. Before you settle into a billing routine with a new payer, spend time checking their policy documents for occupational therapy, because assuming coverage based on Medicare guidelines or other payer experiences will come back to bite you.