
Diabetic Foot Exam Coding: The Actual Details
Most people who code this get it wrong because they skip the nuance between different CPT Diabetic Foot Exam codes. I spent six months straight billing these and learned where the denials actually come from. The codes themselves are straightforward. It's the documentation and modifier work that breaks. The main codes are 95250 and 95251. 95250 is for the self-management training component — that's teaching the patient how to do foot checks at home, proper footwear, nail care, skin inspection. 95251 is the actual clinical exam. When people say they bill a diabetic foot exam, they're usually talking about 95251, which requires a thorough lower extremity vascular and neurological assessment including monofilament testing, proprioception, vibration sense, reflexes, and pulse checks. Both require a diabetes diagnosis. Usually E11.9 or E11.65 depending on whether there's a documented complication. If the patient has peripheral neuropathy without diabetes, you can't use these codes. That trips up about a third of coders I see make that mistake. Use E11.42 instead for the neuropathy diagnosis and code the actual exam separately, though the reimbursement structure changes entirely.
What the Code Actually Requires
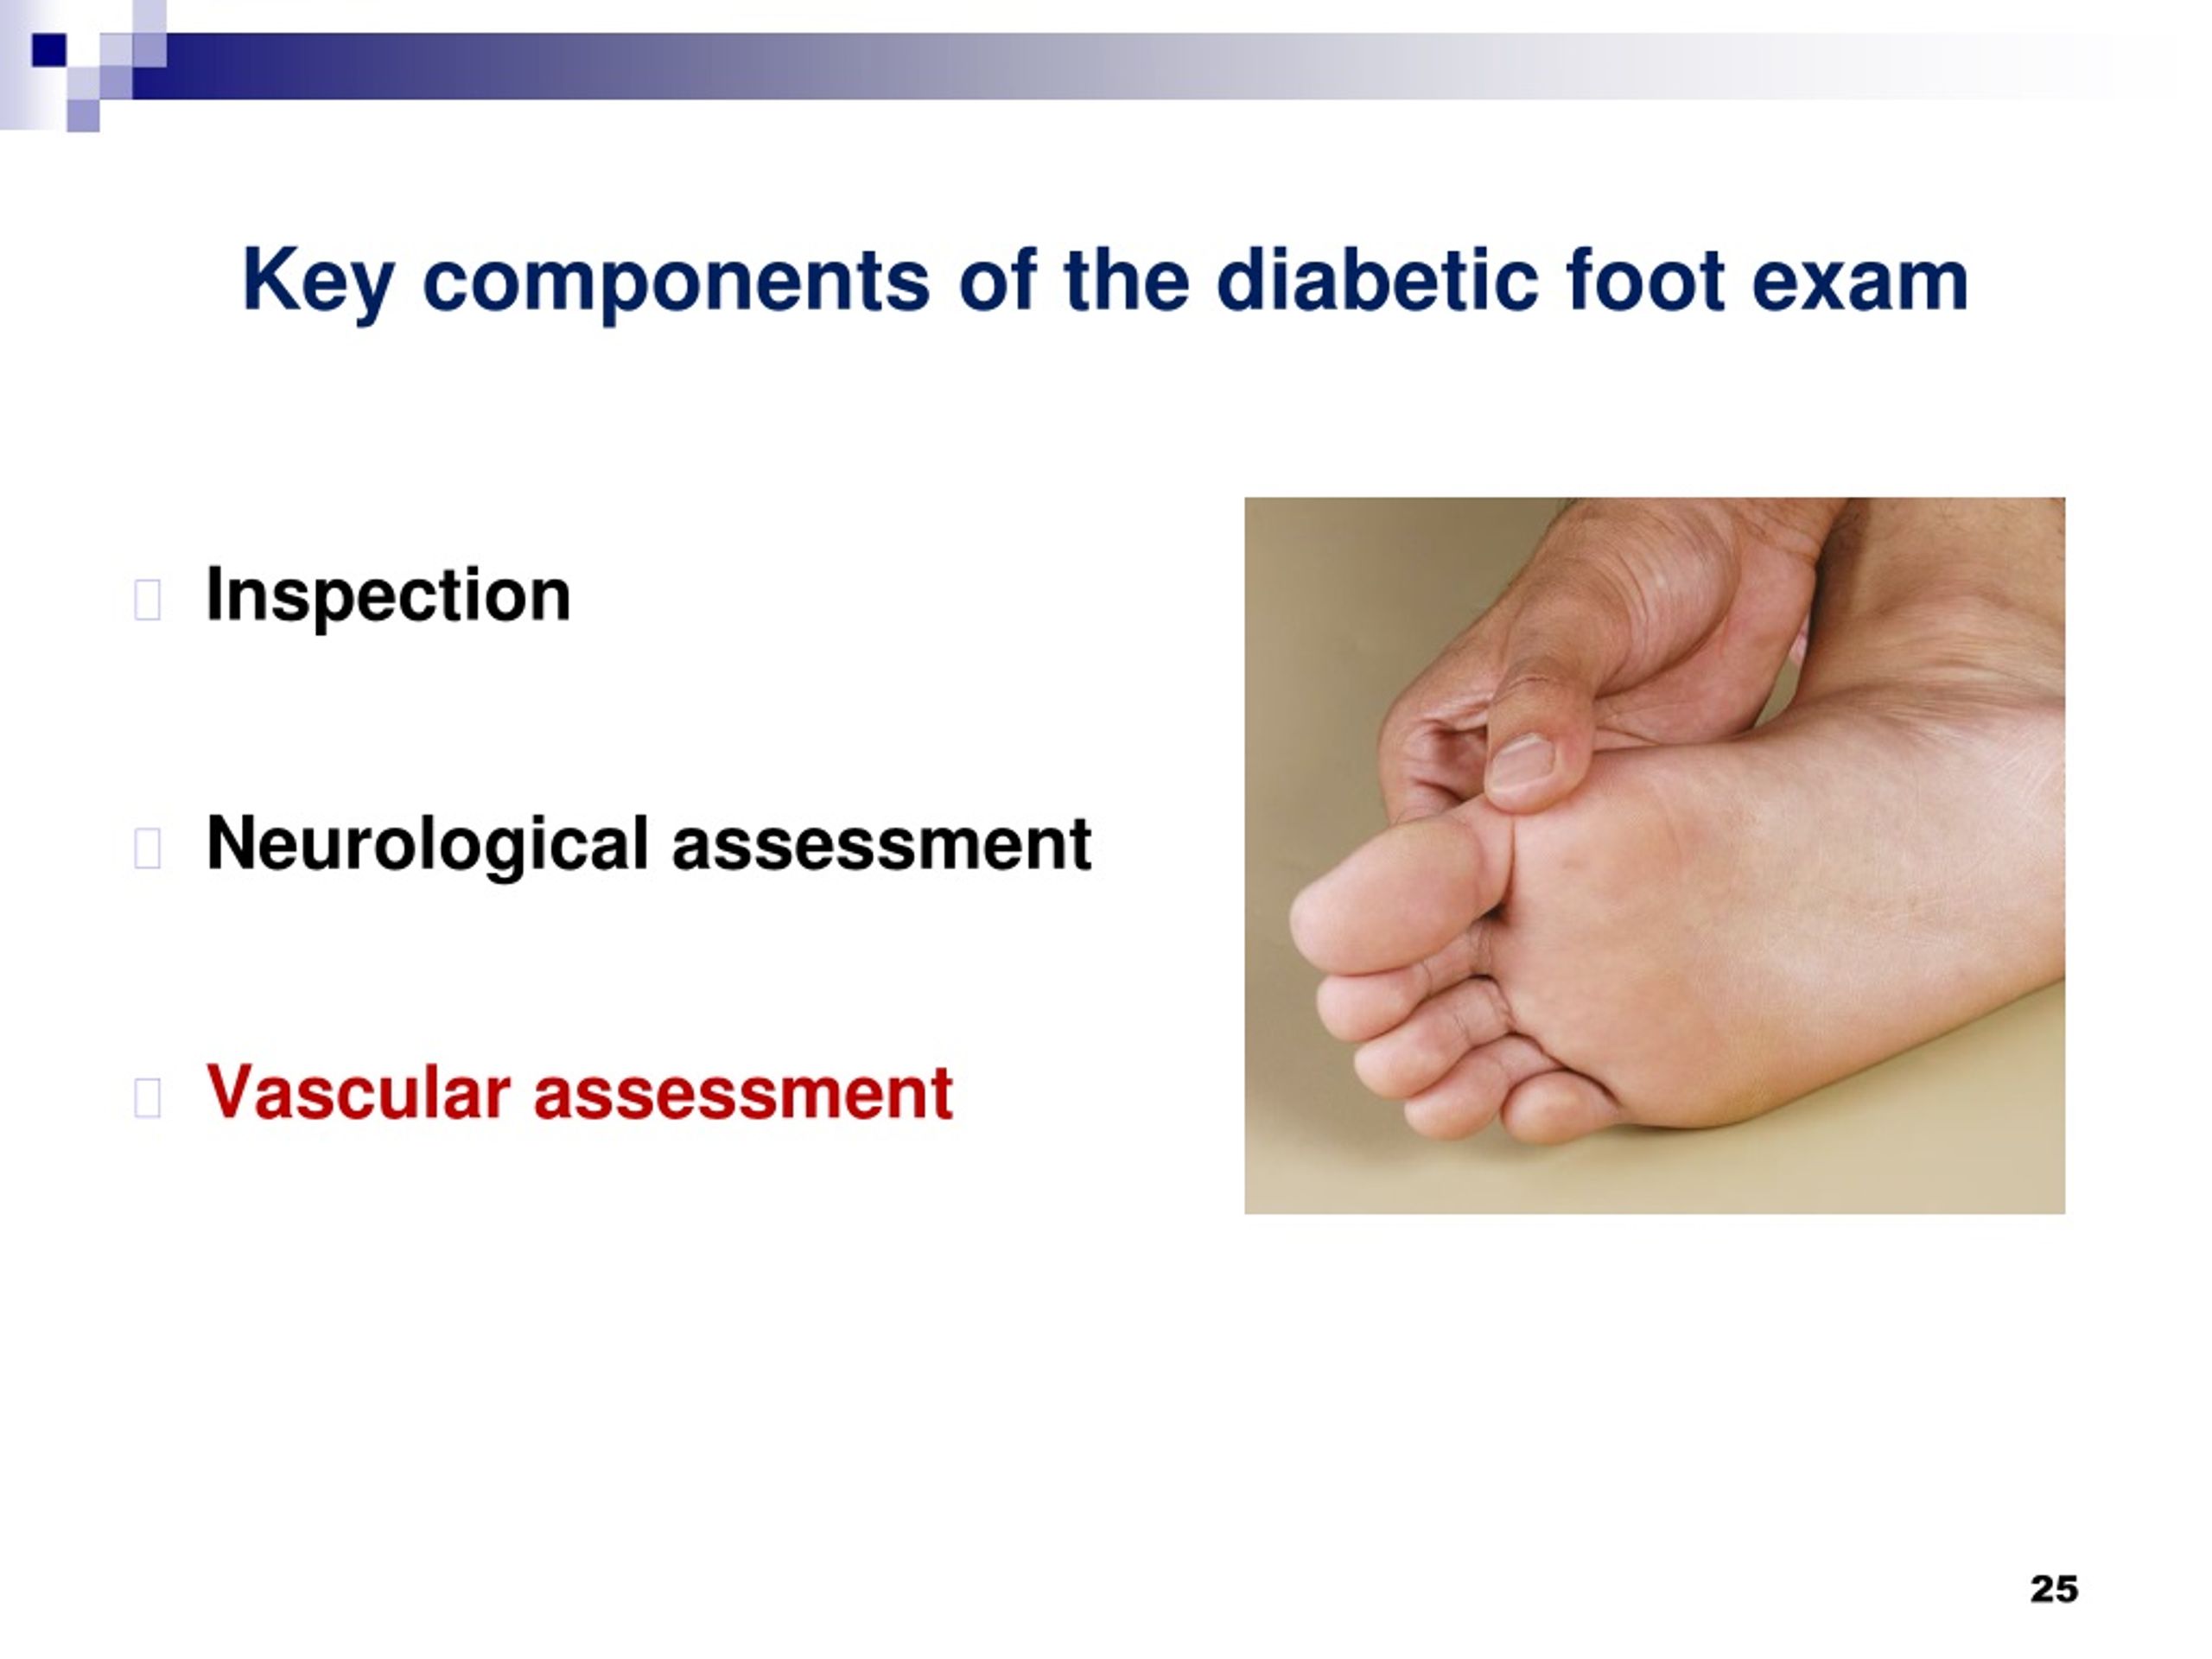
For 95251, every single component has to be documented. I mean every one. Monofilament at specific sites on each foot, dorsalis pedis and posterior tibial pulses, deep tendon reflexes in the ankles, vibration sense with a tuning fork, and proprioception. If your note says "neurological exam performed" but doesn't list the specific areas tested, it will get denied. It happens all the time. I had a case where a provider billed 95251 for a patient who only had monofilament testing done. No pulses, no reflexes, no vibration. Denied on the first submission. The fix was pulling up the actual exam documentation and seeing that the provider had checked reflexes but just forgot to write it down. We added the missing documentation and resubmitted. The lesson: document everything or don't bill it. There is no gray area here.
Modifiers That Matter
If you're billing this in a hospital outpatient setting, you might need modifier -25 on the E/M code if the exam is bundled. On the professional side, modifier -59 is sometimes used when multiple distinct procedures are performed alongside the foot exam. But use it carefully. Medicare audits modifier -59 aggressively. They want distinct procedural contexts, not just different body parts during the same session. For 95250, if it's being billed alongside a preventive visit like a G0438 annual wellness exam, the modifier setup becomes tricky. Most payers expect the educational component to be integral to the preventive visit rather than separately billable. Only bill it separately if the education is significant and documented apart from the standard counseling that comes with a wellness exam. And yes, I have run into this exact scenario multiple times across different payer policies.
Get the Full Details
Documentation Checklist
Every diabetic foot exam note needs at minimum: patient's diabetes status and type, laterality of examination, findings for each assessed component, any abnormal findings documented separately, patient education provided and understood, and the plan including follow-up interval. Anything less is a denial waiting to happen. I keep a simple checklist in my head now: M for monofilament, P for pulses, R for reflexes, V for vibration, T for training. MPVRT. If one is missing from the documentation, the code is incomplete. I still catch this in my review process even after all these years.
Common Denials and How to Fix Them
The most frequent denial reason is "service not medically necessary." This usually means the documentation doesn't establish medical necessity. For diabetic foot exams, medical necessity comes from the diabetes diagnosis itself plus evidence of risk factors. Documenting a previous ulcer, amputation history, or known peripheral vascular disease strengthens the claim significantly. Without those supporting details, some payers treat it as purely preventive and deny it under their preventive benefit rules. Another denial pattern: missing or invalid diagnosis linkage. Make sure the ICD-10 code maps correctly to the CPT code. E11.9 with 95251 works. A18.0 with 95251 does not. If the diagnosis doesn't support the procedure, the claim gets rejected at the clearinghouse level or shortly after.
Payer-Specific Quirks
Medicare covers the diabetic foot exam as part of routine diabetes management when medically necessary. Commercial payers vary widely. Some require prior authorization. Some have specific frequency limitations. Aetna allows annual exams with certain risk factors documented. UnitedHealthcare typically covers it but may require a qualifying diagnosis beyond just diabetes. Blue Cross plans differ by state and policy. The workaround I use is maintaining a payer matrix. I track which commercial payers in our service area have specific requirements for diabetic foot exam billing. When I encounter a new payer, I call their provider services line and ask directly about coverage criteria for 95251. Most representatives will tell you the specifics. Five minutes of a phone call saves you three weeks of denial appeals.

What Doesn't Work
Don't try to bundle this with CPT 9921x E/M codes without modifier support when the exam is the sole purpose of the visit. If the patient came in specifically for a diabetic foot exam and nothing else, you bill 95251 alone. Adding an E/M code on top without clear separate identifiable services will get flagged. Don't use modifier -25 unless there is a genuinely separate, significant E/M service that changed the treatment plan independently of the foot exam itself. Also, don't assume telehealth covers this. You can't perform monofilament testing, pulse checks, or reflex assessments remotely. Some payers have expanded telehealth coverage during public health emergencies, but the CPT guidelines for 95251 still require the physical examination components. If you're doing remote diabetes management consultations, use the appropriate telehealth E/M codes instead. The documentation for the Cpt Diabetic Foot Exam is unforgiving because the code is precise. You either documented every required component or you didn't perform the service according to the code descriptor. There isn't much middle ground, and the denials pile up fast when you're not meticulous about it.


