.jpg?width=1200&name=cpt code awv chart (1).jpg)
Understanding CPT Codes for Wellness Exams
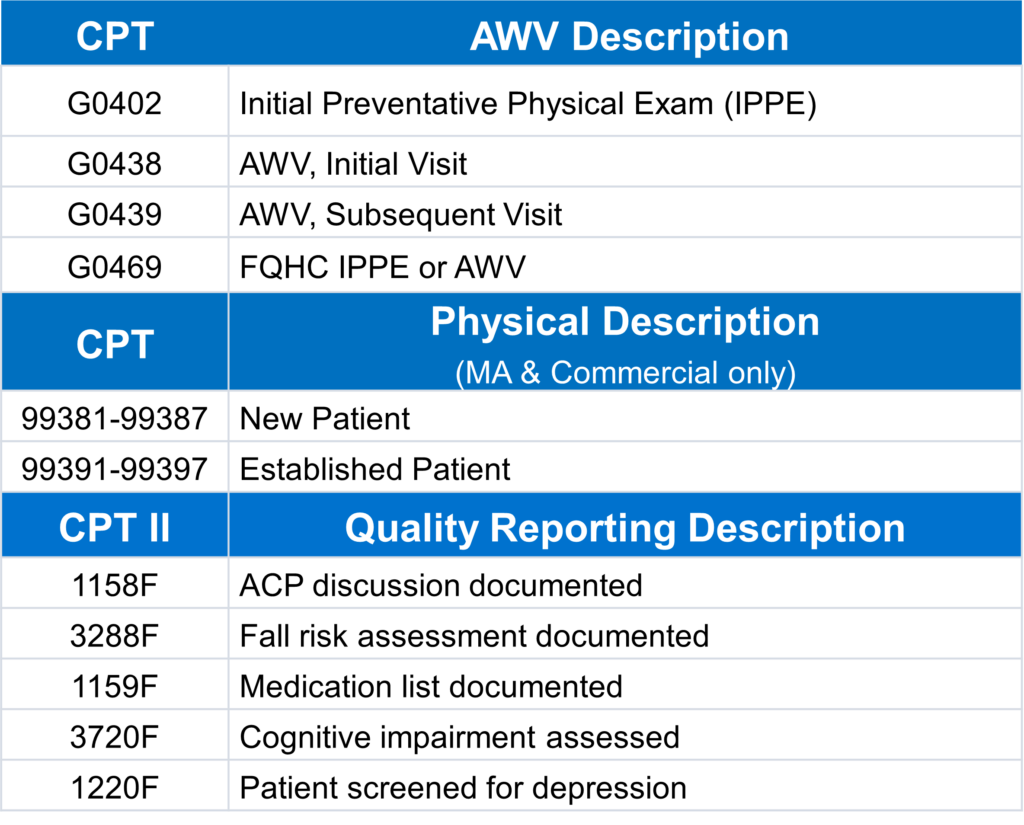
The current procedural terminology codes for preventive medicine visits are organized by patient age and whether the encounter is initial or subsequent. Range 99381 through 99397 covers these services, split into two categories: new patient codes (99381–99391) and established patient codes (99392–99397). The numbers themselves map to age brackets. You have pediatric well visits starting at birth through 17, then adult preventive exams from 18 through 64, and geriatric assessments for patients 65 and older. Most people get tripped up by the "new" versus "established" distinction. It has nothing to do with whether the patient has ever visited your practice before. A "new" preventive exam code simply means the patient hasn't had a comprehensive preventive medicine evaluation in your practice within the last three years. If they received one in 2021, you can use the new patient code again in 2024. That three-year window is arbitrary but it's the rule, so don't overthink it.
Cpt For Wellness Exam
The structure of these codes is based on the complexity of history, examination, and risk factor assessment documented during the visit. Preventive medicine CPT codes don't follow the same E/M decision-making framework as problem-focused visits. There's no calculating total time or rating complexity of medical decision making. The code selection hinges entirely on the patient's age category and new or established status, with the understanding that a comprehensive preventive service includes a complete or pertinent history, a comprehensive or pertinent physical exam, and a documented risk factor assessment. Here is the thing most coders miss on their first attempt: the counseling and risk factor reduction work must be integral to the visit, not an afterthought tacked on. If a patient schedules a "quick check-up" and you spend 45 minutes discussing diet, exercise, smoking cessation, and medication adherence, you still bill the same preventive medicine code. Time is not the determining factor for these particular CPT codes. What matters is that you documented the counseling components and they were medically appropriate for the patient's age and risk profile. I ran into a specific problem last year that highlighted how easily this goes wrong. A provider billed a 99395 for a well-exam on a 42-year-old established patient. The note was sparse. It contained a problem-oriented history because the patient had come in complaining of knee pain, and the physical exam focused on the lower extremities. There was a brief mention of reviewing systems and a checklist for preventive screening. The auditor denied it and recoded to 99213, an established patient office visit. The denial reason was straightforward: the documentation did not support a comprehensive preventive medicine examination. The provider had essentially performed a problem visit and wrapped a preventive screening around it, which does not qualify for the higher-value preventive code.
The workaround I suggested was to restructure the encounter documentation. If the patient presents with a complaint, the problem visit is appropriate and you bill an E/M code with the appropriate modifier if a separate preventive service is also performed. But if the intent is a true preventive exam, the history should be a complete review of systems across body areas appropriate to the patient's age, the physical exam should follow the comprehensive or chronological template for that age group, and the risk assessment needs to be explicit rather than implied by a checkbox. In that case, I had the provider document a complete ROS and a comprehensive exam, then add a separate problem-oriented evaluation for the knee issue on the same day with modifier 25 appended to the E/M code. That cleared the audit.
Get the Full Details
Code Breakdown by Age Group
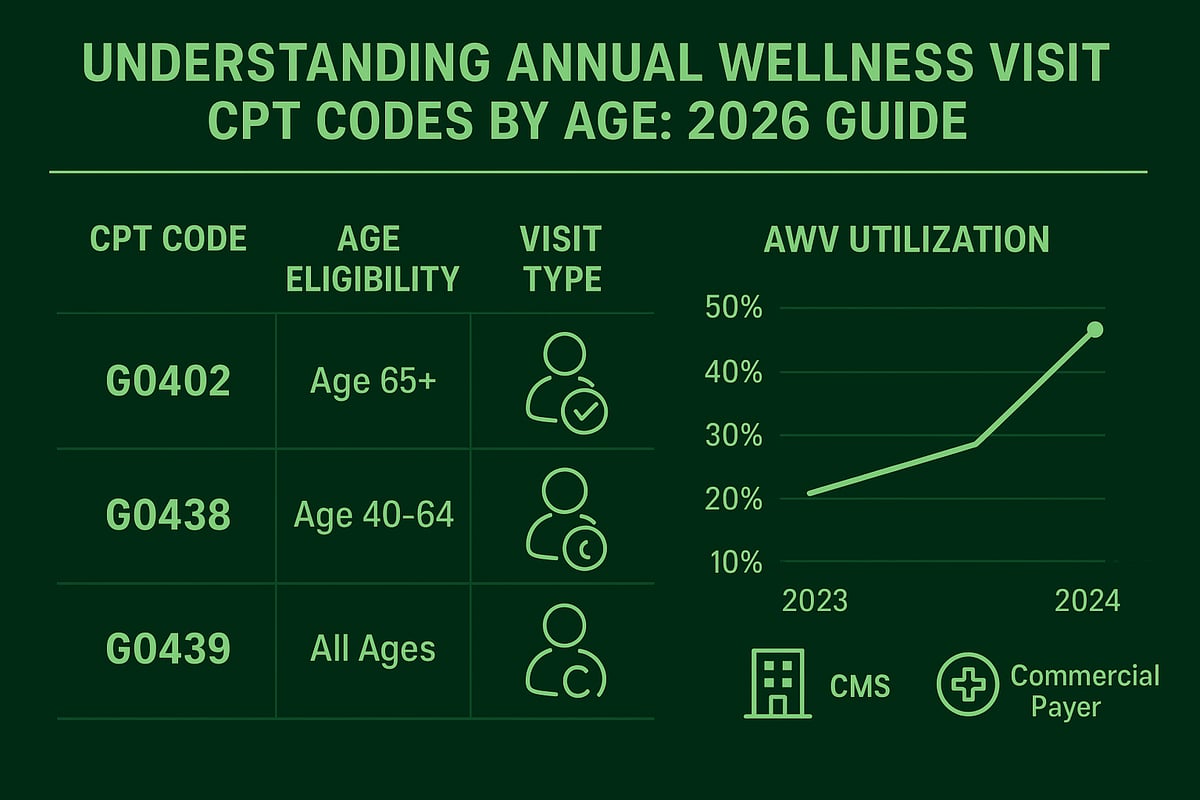
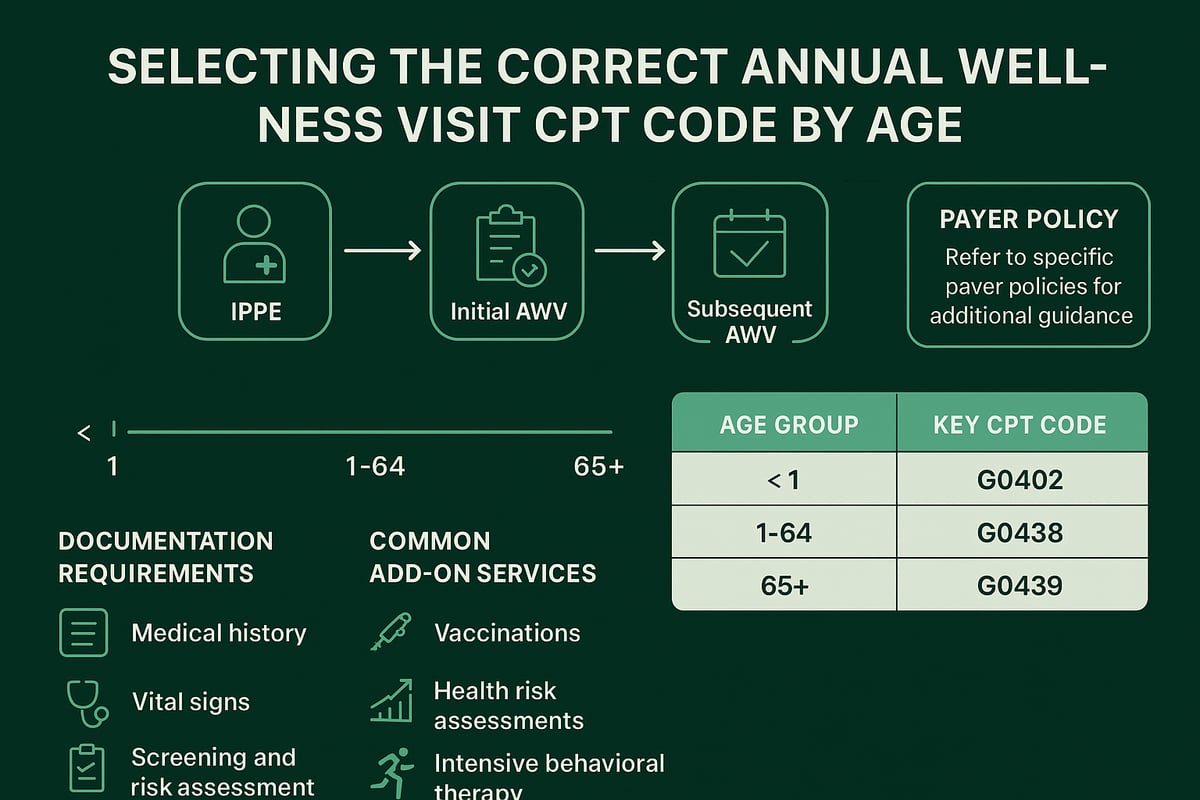
For new patients under 18, the range runs from 99381 for ages 0 through 3 up to 99391 for ages 17. Established pediatric patients fall into 99392 through 99397, with the same age brackets. Adult new patients span 99384 through 99391 covering ages 18 through 39, then 99392 through 99397 for ages 40 through 64. Geriatric patients, whether new or established, use 99396 and 99397 respectively for those aged 65 and older. The reimbursement difference between these codes is significant. A 99395 typically reimburses substantially more than a 99213 office visit because it encompasses a full preventive evaluation. But the documentation burden is proportionally higher. Payors are actively auditing these claims because the revenue differential makes them attractive targets. One counter-intuitive point that beginners consistently overlook: the preventive medicine codes include the performance of age-appropriate screening tests and immunizations as part of the global service. You generally should not bill separately for standard screenings like lipid panels, diabetes screening, or vaccinations administered during the same encounter. Those are bundled into the well-exam code. What you can bill separately are screenings that go beyond the recommended preventive schedule for that patient's age and risk category, or procedures that are diagnostic rather than preventive in nature.
Another nuance that catches people off guard involves the use of ICD-10 codes as the primary diagnosis. Some providers list Z0000 or Z0001 as the principal diagnosis and then wonder why the claim gets flagged. While these encounter codes are appropriate for preventive visits, your payer may require additional diagnosis codes if any chronic conditions or risk factors are addressed during the exam. If you spend time managing hypertension or diabetes during a wellness visit, the claim should reflect that with the relevant chronic disease codes. Leaving them out makes the encounter look artificially clean and triggers payer scrutiny.
Documentation Requirements That Actually Matter
Documentation for these codes needs to demonstrate three components: the history, the examination, and the risk factor assessment. The history section should cover chief complaint or reason for the visit, a complete or pertinent review of systems, and past, family, and social history as applicable to the patient's age. The examination portion requires either a comprehensive exam following the multi-system organ approach or a pertinent exam focused on the body areas relevant to the patient's age and health status. The risk factor assessment is where most notes fall short. A proper risk assessment goes beyond listing vitals. It should document behavioral risks like tobacco use, alcohol consumption, and dietary habits, as well as medical risks identified through screening results and family history. You need to show that you evaluated the patient's risk profile and provided counseling or referrals based on what you found. A one-line statement saying "risk factors discussed" without detailing what those risks were and what guidance was given will not satisfy a payor audit. These codes work well when the encounter is genuinely preventive. They fail when providers try to squeeze a problem visit into a wellness code to maximize reimbursement. If a patient comes in for a sore throat and you bill 99395, the claim will likely be denied because the encounter was not primarily preventive. Conversely, if a patient schedules a preventive exam and you discover an unrelated acute issue, you can address both. Bill the preventive code with the appropriate wellness diagnosis, and append a separate E/M code with modifier 25 for the acute problem, supported by distinct documentation.
Common Pitfalls and Workarounds
The biggest pitfall is documentation that is too generic to justify the code level. Using an electronic health record template that auto-populates "comprehensive exam performed" without actual findings is a fast track to denial. Payers are looking for specific findings, even in a normal exam. Listing "heart regular rate and rhythm" is acceptable. Writing "cardiovascular exam within normal limits" without any supporting details invites challenges. Another area of confusion involves annual wellness visits under Medicare Part B. These are different from CPT preventive medicine codes. Medicare annual wellness visits use G-codes like G0438 and G0439, which have their own distinct billing requirements and documentation standards. Mixing these up is one of the most common errors in preventive care billing. A Medicare patient who qualifies for an annual wellness visit should not be billed with a CPT 9939x code unless they are also receiving a separate comprehensive preventive medicine evaluation beyond the Medicare-established wellness visit scope. The limitation I want to flag honestly is that these codes do not account for the actual time spent. A preventive exam for a complex geriatric patient with multiple chronic conditions and a lengthy psychosocial history can take 60 to 90 minutes, yet it bills at the same rate as a straightforward 20-minute visit for a healthy 25-year-old. If your practice relies heavily on these codes and your caseload skews toward complex patients, the reimbursement per unit of time drops considerably. In those situations, some practices supplement with chronic care management codes or care plan oversight billing when appropriate, though those require separate eligibility criteria and patient consent.
The straightforward approach is to match the code to the actual service provided, document thoroughly, and avoid bending encounters to fit a higher-paying code. When you do that, the coding is accurate and defensible. When you don't, audits catch it quickly and the recoupment process is worse than the administrative headache of getting it right the first time.