Running Through the Twelve Without Losing Your Mind
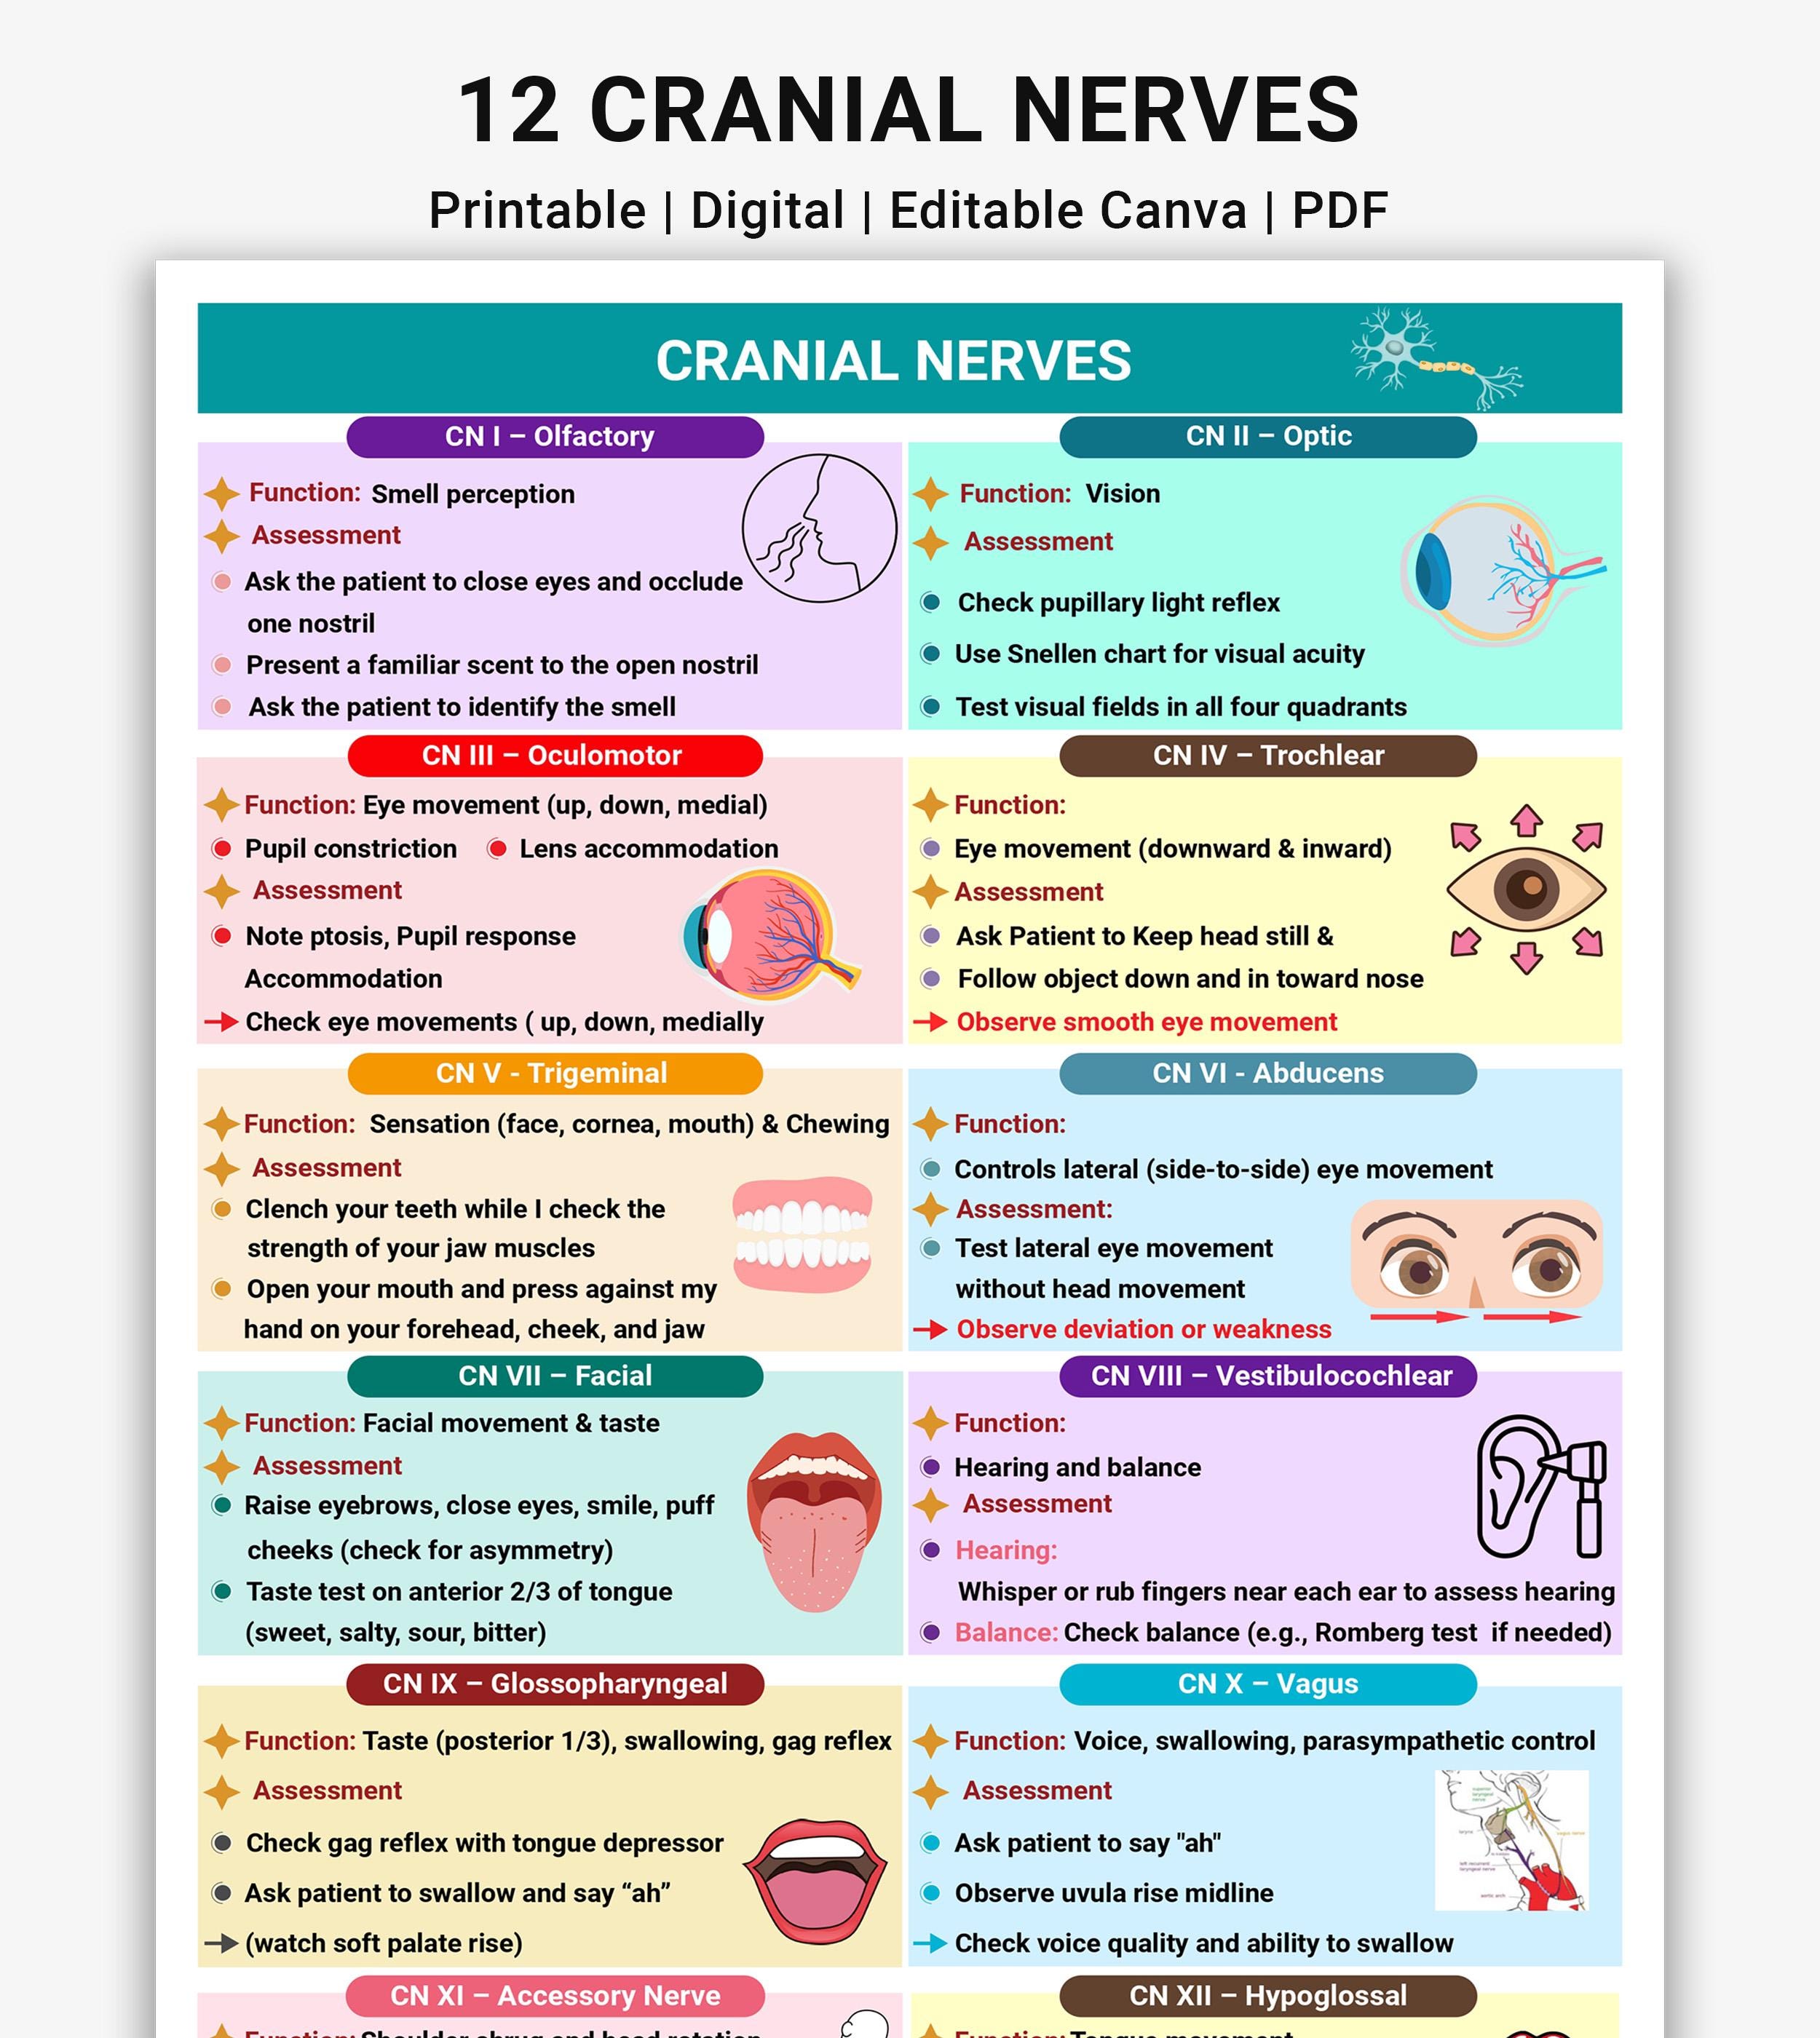
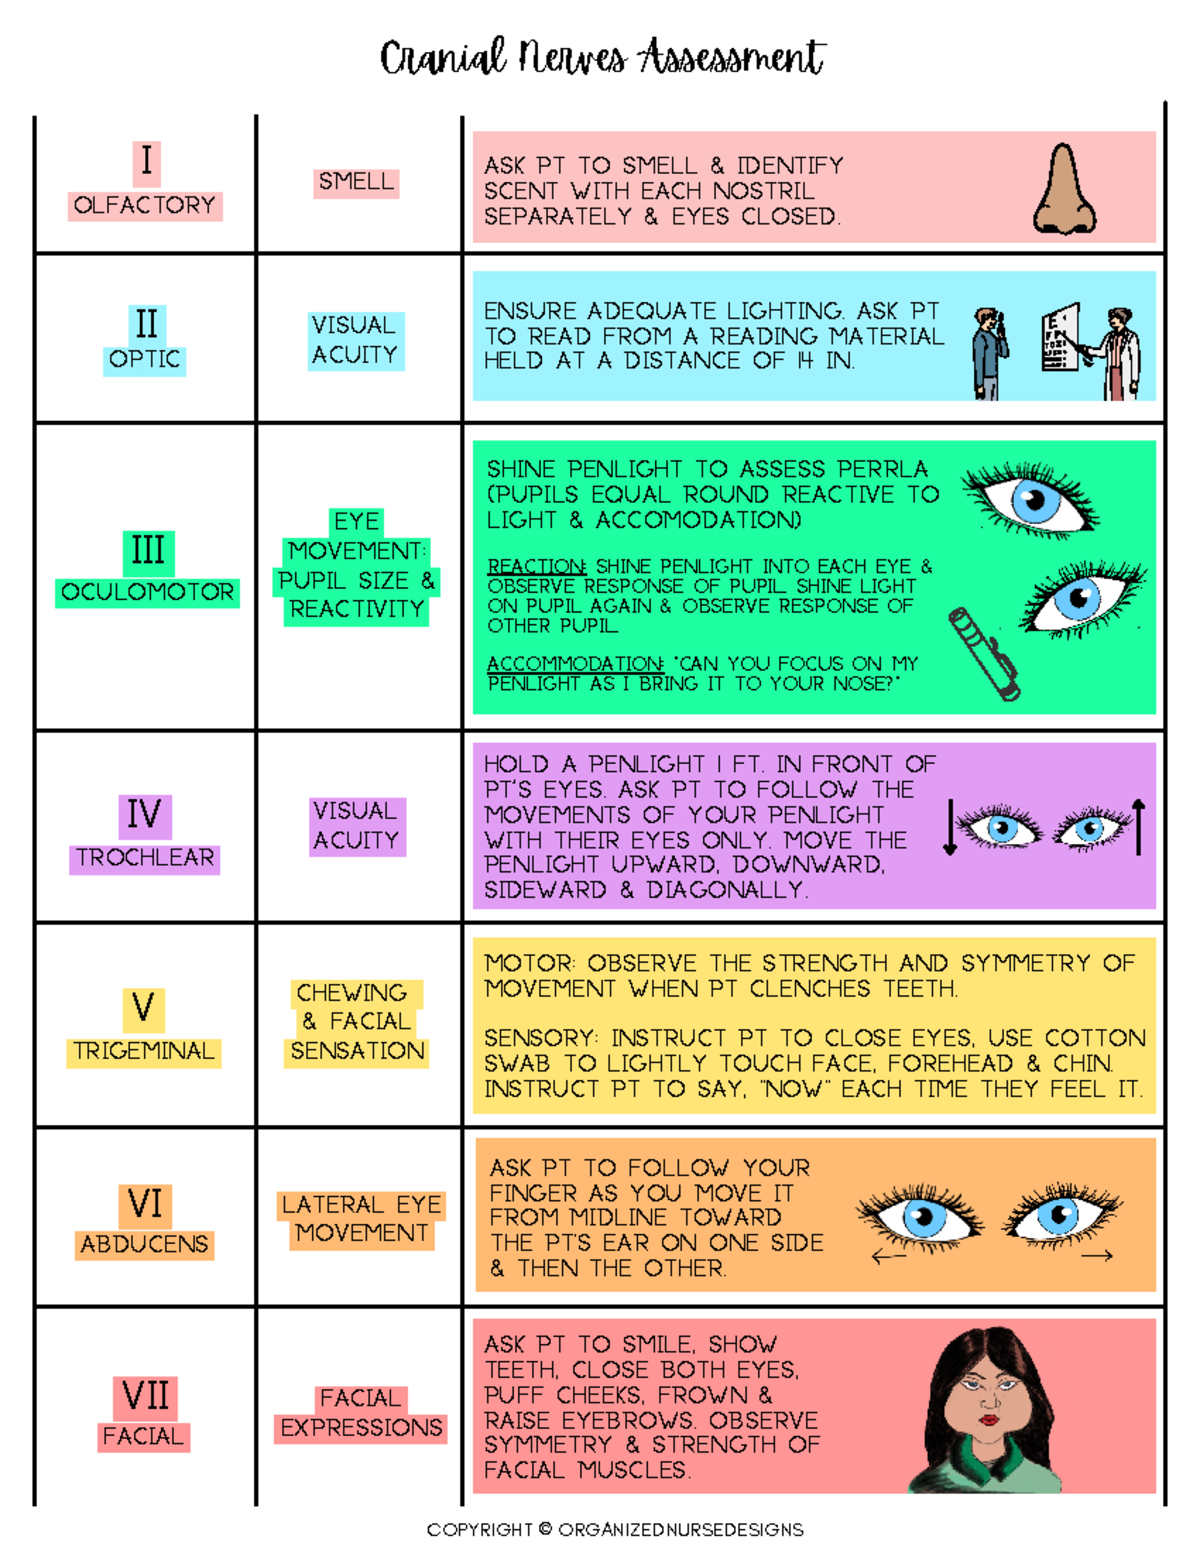
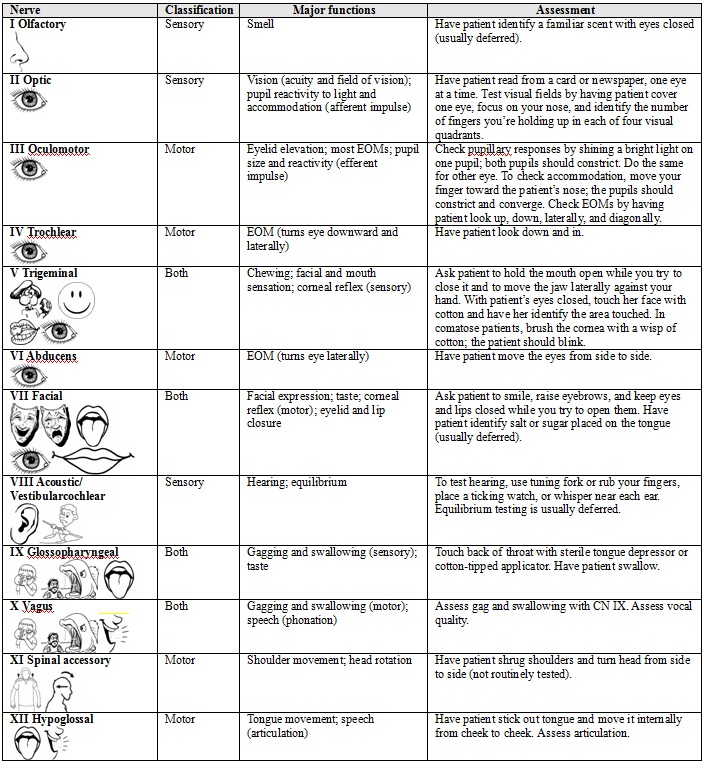
I spend half my clinical time running cranial nerve assessments on patients who already look like they've been hit by a truck, and the other half explaining to residents why we can't just skip CN II and start at CN V. The thing nobody tells you about this exam is that it's less about memorizing a checklist and more about pattern recognition. You learn to spot which nerves to prioritize before you even open the patient's chart. The traditional order taught in med school goes I through XII, but honestly, most clinicians abandon that sequence after their first year because it makes no practical sense. A functional approach starts with the nerves you can assess without moving the patient, then works through systems. Vision first, because if you can't see what you're doing, the rest of the exam is compromised. Then pupil response, facial sensation, eye movements, facial strength, hearing, gag reflex, tongue movement, and the accessory and vagus nerves that you can evaluate with relatively minimal patient cooperation. Cranial Nerve Assessment doesn't require expensive equipment. You need a penlight, a tuning fork set to 512 Hz, a cotton wisp, a tongue depressor, and a way to test gag reflex if the clinical situation calls for it. That's it. The real tool is your knowledge of neuroanatomy and the ability to localize lesions between the nucleus, the nerve course, and the target organ.
The Nerves and What Actually Matters
CN I — Olfaction. Most clinicians skip this entirely in the acute setting. It's genuinely hard to test reliably without standardized smell kits, and acute changes in smell are rarely the presenting complaint that lands someone in the ER. Document it if you have time, skip it if you don't. CN II — Optic nerve. Visual acuity, visual fields by confrontation, and the pupillary light reflex. The key insight people miss is that the pupillary reflex tests CN II indirectly through the afferent limb. A relative afferent pupillary defect (RAPD) detected with the swinging flashlight test can be the only early sign of optic neuritis or compressive optic neuropathy before visual acuity drops. I've caught posterior cerebral artery aneurysms presenting with subtle RAPD before the patient noticed any vision change. CN III, IV, VI — Oculomotor, trochlear, and abducens. These three travel together and should always be assessed as a unit. Extraocular movements in all nine gaze positions, looking for dysconjugate gaze, nystagmus, or limitation in any cardinal direction. Ptosis and pupillary involvement with a CN III palsy immediately raise the alarm for compressive pathology like a posterior communicating artery aneurysm versus microvascular ischemia from diabetes or hypertension. The pupil-sparing version is almost always ischemic; the pupil-involved version needs imaging stat. I once spent twenty minutes figuring out why a diabetic patient's CN III palsy wasn't behaving classically, only to realize the "pupil sparing" was borderline and the aneurysm was already causing subclinical compression. CT angiography confirmed it.
CN V — Trigeminal. This one has both sensory and motor components that get tested separately. Corneal reflex (afferent is V1, efferent is VII), facial sensation in all three dermatomes, and masseter/temporalis strength for the motor component. The common pitfall here is confusing a peripheral facial weakness (CN VII) with sensory loss on the same side of the face. They're different nerves. I've seen residents chart "facial numbness" when the patient actually had a peripheral Bell's palsy with secondary sensory complaints from muscle stiffness. CN VII — Facial nerve. Ask the patient to raise eyebrows, close eyes tightly, smile, and puff cheeks. Asymmetric forehead involvement points peripheral (lower motor neuron lesion); forehead sparing points central (upper motor neuron lesion). This distinction matters more than the nerve identification itself. A stroke patient who can't raise one eyebrow has a peripheral facial palsy and usually a worse prognosis for recovery than one whose forehead is spared. CN VIII — Vestibulocochlear. Rinne and Weber testing with the tuning fork, though these have limited sensitivity in primary care. The real clinical value is recognizing that isolated hearing loss with vestibular symptoms localizes differently than cochlear-only findings. Vertigo with normal hearing points peripheral vestibular; vertigo with hearing loss suggests labyrinthine or CNS involvement. I stopped relying on Weber and Rinne for routine screening after I missed a vestibular schwannoma in a patient who had "normal" tuning fork results but complained of unilateral hearing difficulty that he'd normalized over months.
Get the Full Details

CN IX and X — Glossopharyngeal and vagus. Gag reflex, palatal elevation, and voice quality. Dysphagia and hoarseness are the symptoms that change management. An absent gag reflex without bulbar weakness is often benign, but combined with other brainstem signs, it localizes fast. The palate should rise symmetrically when the patient says "ah." Asymmetry points to unilateral vagus pathology on the side of the deviation away from weakness. CN XI — Spinal accessory. Sternocleidomastoid and trapezius strength. Shoulder shrug against resistance and head rotation against resistance. Isolated weakness here is uncommon outside of surgical trauma or posterior fossa lesions, but it's worth checking when the presentation suggests it. CN XII — Hypoglossal. Tongue protrusion, looking for fasciculations, atrophy, or deviation. The tongue deviates toward the side of the lesion on protrusion — "the tongue licks the wound." This is one of the few cranial nerve findings that's reliably localizing in isolation.
Practical Workflow That Doesn't Waste Time
Most hospital-based cranial nerve assessments take between 5 and 15 minutes depending on patient acuity and cooperation. In a neurology clinic with complex presentations, expect 20 to 30 minutes if you're doing a thorough exam with documented findings. The bottleneck is almost always documentation, not the exam itself. Here's the sequence I use: mental status and speech first (they reflect CN I through XII broadly), then CN II through IV (vision and eye movements), then V through VII (face), then VIII (hearing if indicated), then IX and X (palate and gag), then XI and XII. This groups functionally related nerves and minimizes patient repositioning. For an ICU patient on a ventilator, you skip the things that are impossible — no gag reflex testing, no tongue examination unless you can safely visualize — and focus on what you can assess: pupils, corneal reflex, facial symmetry, and oculocephalic maneuver if cervical spine clearance exists. One practical note about pupil testing that textbooks understate: measure pupil size and reactivity in the dark, then in bright light, then with the swinging flashlight technique. Normal pupils vary from 2 to 5 mm in typical indoor lighting. Anisocoria of up to 1 mm is physiological in about 20 percent of the population, so don't panic over small differences unless the larger pupil is new or shows abnormal reactivity.
Where This Exam Falls Short
The cranial nerve assessment has well-documented limitations that nobody wants to discuss in grand rounds. The reliability of gag reflex testing is poor — inter-rater agreement is around 60 percent, and the reflex can be completely absent in healthy patients without any clinical significance. Tuning fork testing for CN VIII has sensitivity estimates ranging from 40 to 70 percent depending on the examiner's experience. Confrontational visual fields detect roughly 50 percent of visual field defects compared to formal perimetry. These numbers matter because overreliance on these tests produces false reassurance. Another hard truth: cranial nerve assessment has limited sensitivity for early CNS pathology. A normal exam doesn't rule out a small brainstem stroke, early multiple sclerosis plaque, or an expanding pituitary adenoma compressing the optic chiasm from below. The exam catches deficits; it doesn't catch everything. When clinical suspicion is high despite a normal cranial nerve assessment, imaging and formal neurologic testing are non-negotiable. If you're looking for a structured form to document findings consistently, there are several freely available cranial nerve assessment templates from hospital systems and medical education sites. A PDF version from standard nursing assessment resources works fine for basic documentation, but I usually build my own template that matches our institution's EMR structure rather than importing something generic.
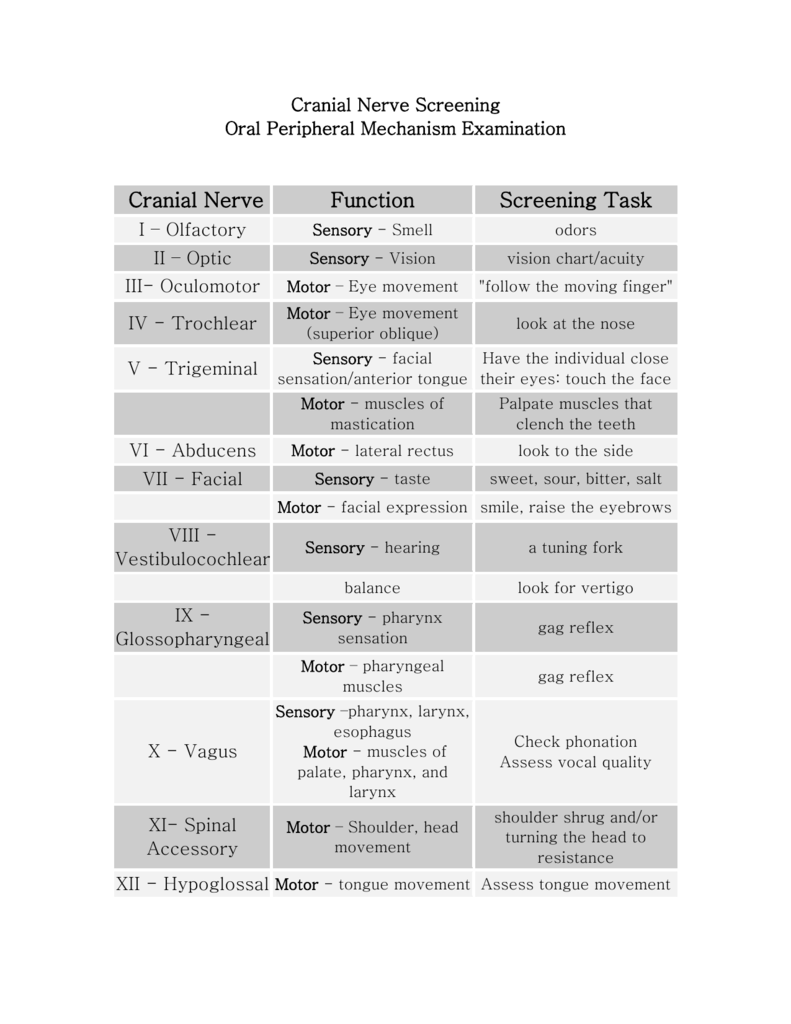
The skills matter more than the paper. You'll develop a faster, more reliable cranial nerve assessment through repetition and deliberate practice, not by filling out the prettiest form. Start with healthy colleagues and family members. Map the normal before you expect to recognize the abnormal. I didn't feel confident running a complete assessment until I'd examined at least two hundred normals across rotations and residency. The shortcut version you pick up in your second year of training will serve you fine for most acute presentations, but the thorough version takes years to internalize.