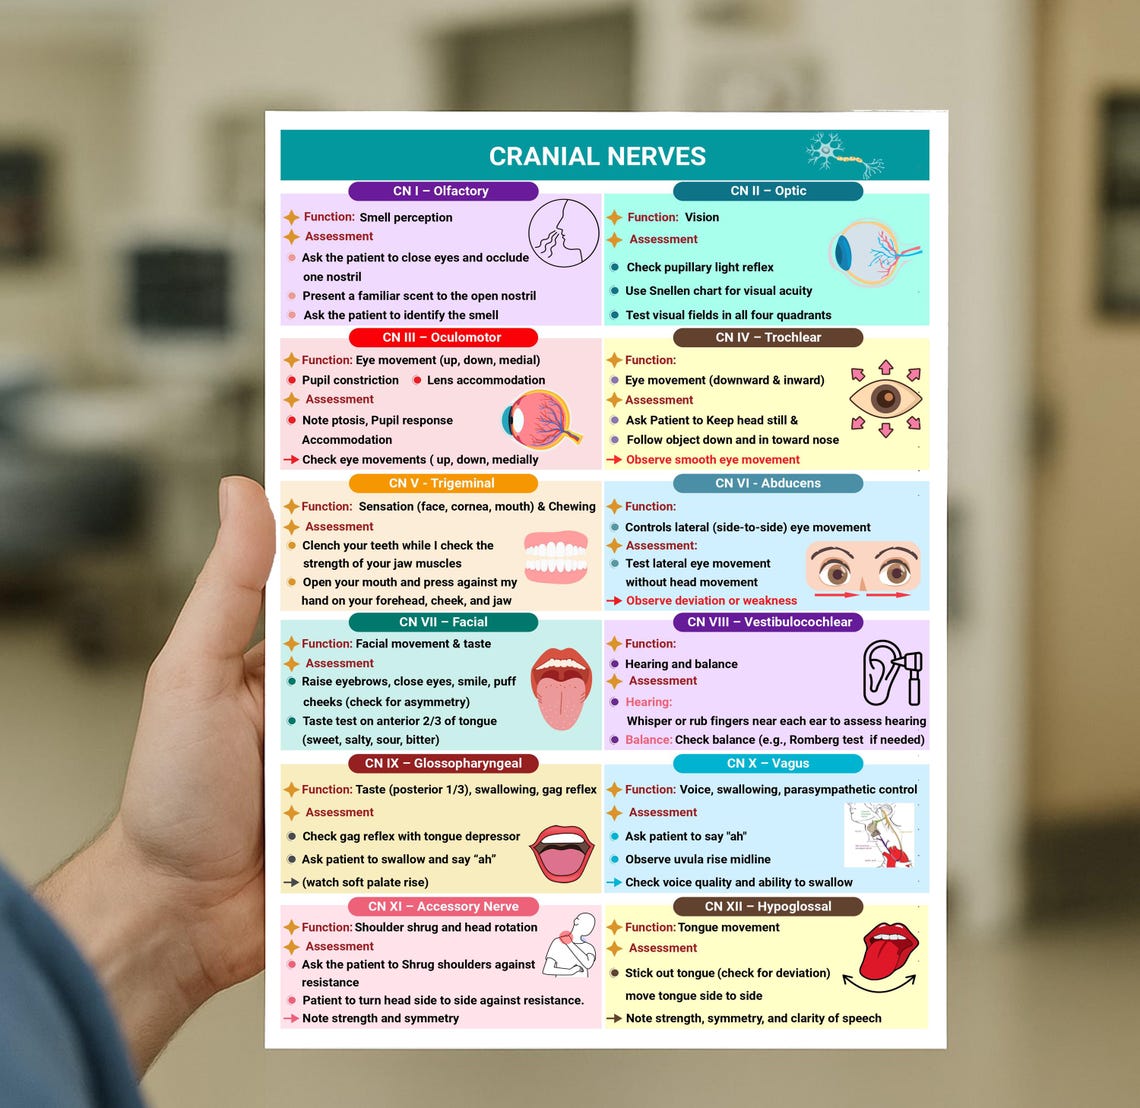
What You Actually Need to Know About Cranial Nerve Assessment
I spent three years doing neurology rotations before I stopped trying to memorize every single reflex arc and started using a proper Cranial Nerve Assessment Cheat Sheet during actual patient encounters. The difference is night and day. You will move faster, miss fewer deficits, and sound less like a textbook when you explain findings to attending physicians. The standard twelve cranial nerves break down into three functional groups: sensory-only nerves (I, VII, VIII), motor-only nerves (III, IV, VI, XI, XII), and mixed nerves that do both (V, VII, IX, X). Most people learning this topic get confused because they treat all twelve as equal players. They are not. Some nerves show up constantly in clinical work. Others barely matter outside of neurology fellowships.
How to Actually Use a Cranial Nerve Assessment Cheat Sheet
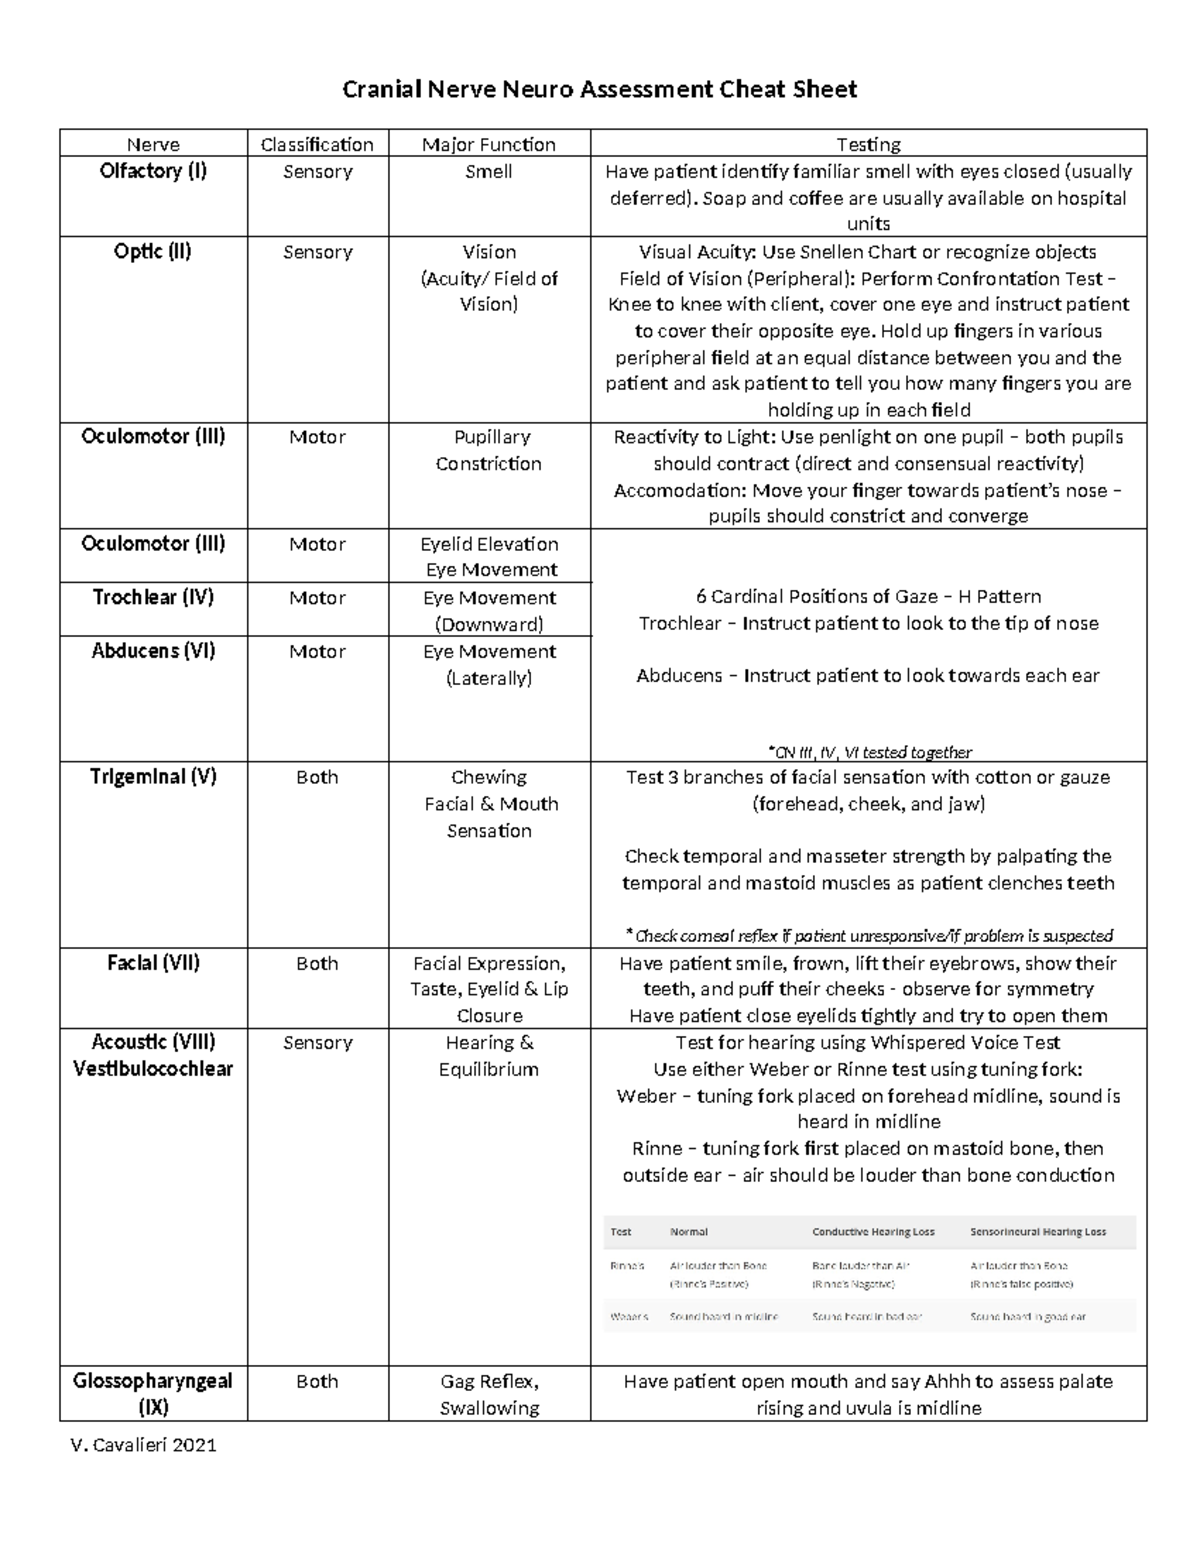
Start with the nerves that matter most in general practice. Optic nerve (II) gets tested with visual acuity and pupil responses. Oculomotor nerve (III), trochlear (IV), and abducens (VI) control eye movements and get assessed together through the six cardinal positions of gaze. If a patient cannot look laterally without nystagmus or reports double vision, you are dealing with either CN VI palsy or a more central brainstem issue. The trigeminal nerve (V) has three branches. V1 covers the forehead, V2 the cheek, and V3 the jaw. Test sensation in each area with light touch and pinprick, then ask the patient to clench their teeth while you palpate the masseter muscles. Weakness here points to lower motor neuron problems affecting the mandibular division specifically. Facial nerve (VII) gets checked by having the patient raise their eyebrows, close their eyes tightly, smile, and puff out their cheeks. Bell's palsy presents as complete unilateral facial weakness including the forehead, while a stroke spares the upper face because of bilateral cortical innervation. This distinction saves you from misdiagnosing peripheral versus central lesions.
Acoustic nerve (VIII) involves hearing and balance. Whisper test each ear separately, then do the Rinne and Weber tests if you suspect sensorineural versus conductive hearing loss. Balance assessment through Romberg testing helps localize vestibular pathology, though many patients with vestibular neuritis refuse to stand still long enough for a proper exam. Glossopharyngeal (IX) and vagus (X) nerves control gag reflex and swallowing. Shine a light on the posterior pharynx and watch for symmetric uvula elevation. Deviation away from the weak side indicates vagus nerve involvement on that side. I once missed a subtle CN X deficit in a patient with thyroid cancer because I only checked gag reflex and did not assess palate movement properly. The tumor was compressing the vagus nerve near the jugular foramen, and we caught it too late for effective surgical intervention. Accessory nerve (XI) gets tested by having the patient shrug shoulders against resistance and turn their head against resistance. Weakness points to spinal accessory nerve damage, often iatrogenic after lymph node biopsies in the posterior triangle.
Get the Full Details
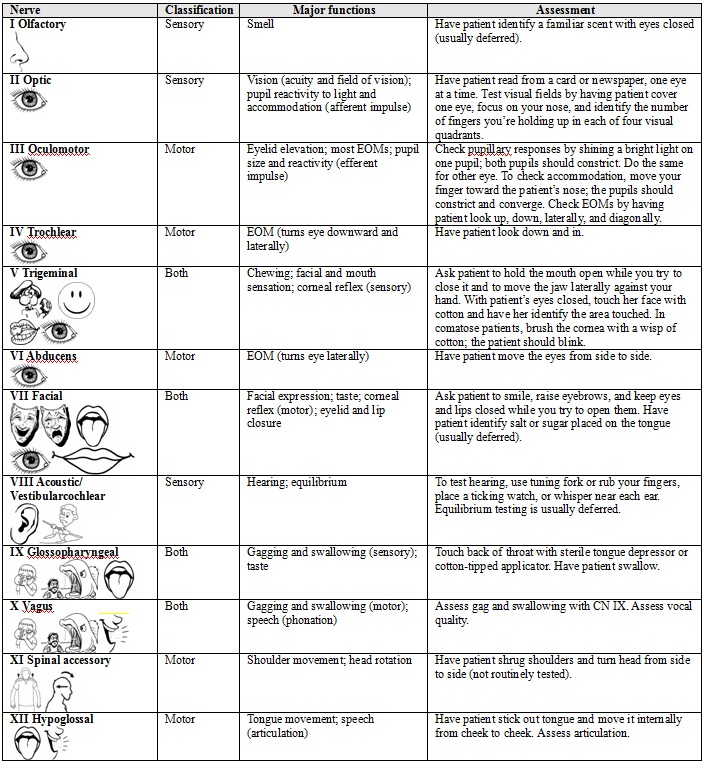
Hypoglossal nerve (XII) involves tongue movement. Ask the patient to stick out their tongue and move it side to side. Deviation toward the weak side indicates lower motor neuron lesion. fasciculations visible on the tongue surface suggest anterior horn cell disease.
Common Mistakes That Cost You Points on Rounds
Most students and residents make the same errors repeatedly. First, they test pupils without checking light reflex first. Always start with direct consensual response before swinging flashlight between eyes. Second, they forget to compare left and right sides systematically. Third, they do not document baseline findings properly, which makes follow-up assessments impossible. The tongue examination deserves more attention than it gets. Look for atrophy, fasciculations, and deviation before asking the patient to speak. A flaccid tongue with visible muscle wasting suggests chronic lower motor neuron disease. Normal tone with slight deviation points to recent upper motor neuron lesion. Pupillary assessment requires proper lighting conditions. Bright exam rooms make pupil testing unreliable. Close the shade or use an occluder to create darkness around the eye. Check for afferent pupillary defect by swinging flashlight test if you suspect optic nerve pathology. A relative afferent pupillary defect indicates optic neuritis or severe retinal disease.
Facial sensation testing often gets rushed. Use cotton wisp for light touch and disposable pin for sharp/dull discrimination. Test forehead, mid-face, and jaw symmetrically. Trigeminal neuralgia presents with trigger zones along V2 or V3 distribution, but remember that primary trigeminal neuralgia spares the forehead because V1 rarely involved.
When a Cheat Sheet Will Not Help You
A Cranial Nerve Assessment Cheat Sheet works well for straightforward cases. It fails completely when patients have altered mental status, intoxication, or pre-existing cognitive deficits that make cooperation impossible. You cannot reliably test coordination, sensation, or cranial nerve function in a confused patient. In those situations, focus on brainstem reflexes and gross motor responses instead. Certain anatomical variations make standard testing unreliable. Patients with prior facial surgery, orbital fractures, or prosthetic eyes require modified approaches. Contact lens wearers may have corneal sensation decreased bilaterally, mimicking trigeminal nerve dysfunction. Dental work including recent extractions affects V3 assessment through local anesthesia effects. Age-related changes complicate interpretation. Pupils constrict less with age, making pharmacological testing necessary for reliable assessment. Presbyopia affects near vision testing, so account for corrective lenses during visual acuity checks. Hearing loss common in elderly patients requires tuning fork testing at different frequencies to distinguish age-related presbycusis from pathological causes.
The greatest limitation of any quick reference guide is that it cannot replace systematic observation. You will miss subtle findings if you rush through the checklist mechanically. Take time to watch patients walk, talk, and perform activities of daily living. Gait assessment reveals information that formal cranial nerve testing sometimes misses entirely.
Practical Tips for Real-World Use
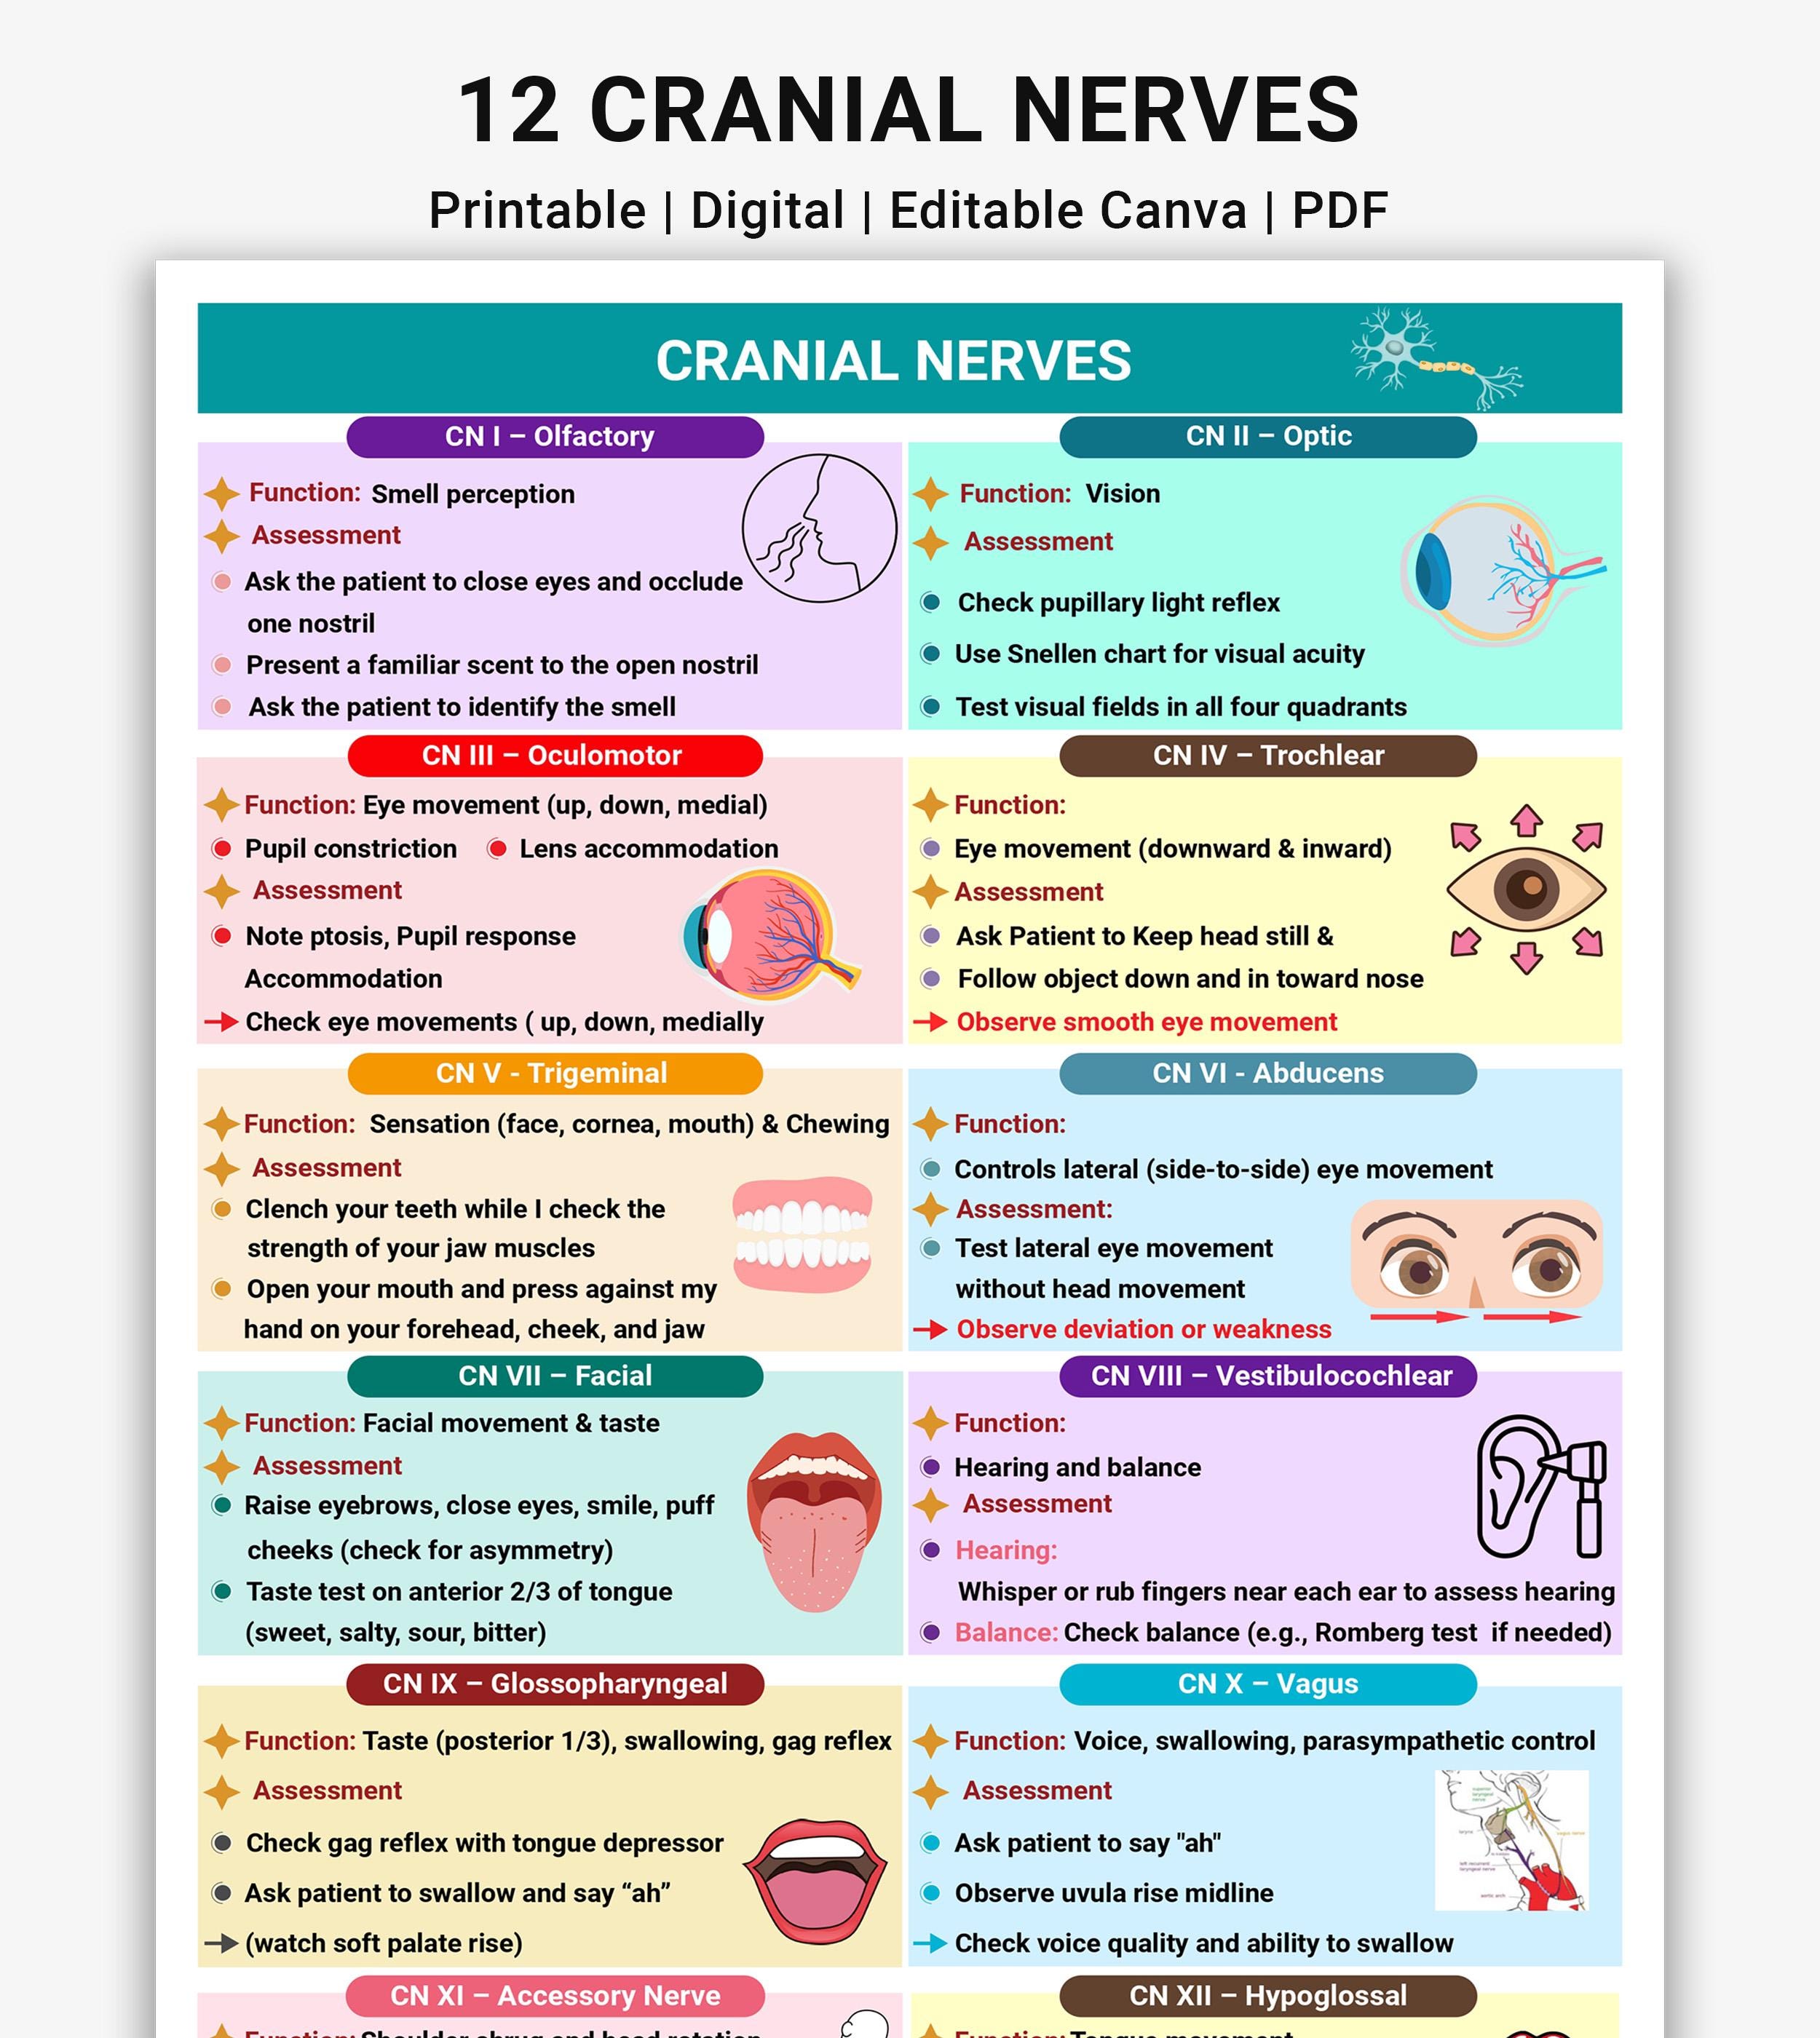
Keep your reference material organized by nerve number rather than by symptom. This approach matches how most neurological textbooks present the material and makes lookup faster during busy clinical shifts. Laminated cards fit conveniently in white coat pockets without bulging or getting damaged easily. Practice on colleagues before attempting assessment on actual patients. You will notice asymmetries, test technique variations, and build confidence in a low-stakes environment. Peer feedback improves your examination skills faster than solo study sessions ever will. Document findings using standardized terminology. Instead of writing "CN VII normal," specify which muscles tested, which movements assessed, and any subtle asymmetries observed. Precise documentation helps future clinicians track disease progression or treatment response accurately.
Combine cranial nerve assessment with general neurological examination rather than treating it as isolated component testing. Brainstem reflexes, cerebellar function, and sensory-motor integration provide context that makes individual nerve findings more meaningful clinically. An isolated CN VII weakness means something different when paired with contralateral hemiparesis versus occurring alone without other neurological signs.